Category: Navigating Regulatory Landscapes in Latin America

Explores the regulatory requirements and best practices for conducting clinical trials in Latin America, focusing on medical devices and biopharmaceuticals.

  • Unicamp Campinas: The NCT Campus String Is Not the ANVISA File

    Figures cited from a ClinicalTrials.gov LATAM facility sweep (API pull 1 September 2026, 6:32 PM ET) and published bioaccess® country pages. Registry ranking is not a bioaccess® claim that we ran any of these studies. General information, not legal or regulatory advice. Confirm current ANVISA, ethics, and FDA rules with qualified advisers. We name only the facility strings and example NCT IDs those sources support. We do not invent a principal investigator. We do not claim Unicamp Campinas as a bioaccess® client.

    If you searched Unicamp Campinas first-in-human, Hospital das Clinicas Unicamp clinical trial, Unicamp CRO, or “go direct Unicamp Campinas,” you followed a campus string ClinicalTrials.gov still publishes. Unicamp in Campinas, Brazil, is a real named university-campus string on ClinicalTrials.gov. It is not a first-in-human medical-device CRO, and it is not the operator of the ANVISA file.

    bioaccess®’s position is simple and it is not adversarial: the university is the site. The First-in-Human CRO still owns ANVISA, CEP / CONEP, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if this campus is not the only fit. Sponsors who skip the CRO and email the university still have to rebuild that stack. An NCT location row is not a CRO.

    This page is the named Campinas Unicamp campus (alias includes Hospital das Clinicas da Unicamp). It is not university-of-campinas-fih if already live under a different fold, not Hospital Celso Pierro Campinas (already live), not Loema Instituto Pesquisa Campinas, and not Centro Pesquisa São Lucas Campinas. Sharing Campinas is not a license to collapse them. Unicamp is not Celso Pierro. Unicamp is not Loema.

    Why the campus name wins the search — and why that is not a CRO

    Device registries write the city, the hospital, and a list of NCT IDs. They rarely write the CRO. On the 1 September 2026 ClinicalTrials.gov LATAM sweep (interventional studies; all years; complete dump), this campus sits here after filters:

    Counts come from leftover unique strings after the last live leftover-site batch plus unique NCT IDs in /workspace/five-trials/ctgov-raw/all_interventional.jsonl (17497 studies; ClinicalTrials.gov LATAM facility sweep, API pull 1 September 2026, 6:32 PM ET; dump confirmed 1 September 2026). Alias strings are listed separately. We do not publish a unique-study union across alias strings. We do not invent a global CSV rank. We do not invent unpublished CMS IDs. Registry ranking is not a bioaccess® claim that we ran any of these studies.

    • Unicamp (Campinas, Brazil) — canonical NCT string: ALL interventional n=147; DEVICE n=2. Example NCT IDs: NCT04171063, NCT05017636.

    Cite canonical ALL n=147 and DEVICE n=2. Do not clone Celso Pierro, Loema, or São Lucas Campinas onto this slug.

    Those are unique NCT IDs per facility string + city + country. They are not a count of first-in-human device programs bioaccess® ran. They are how a sponsor searching the hospital name lands on a campus without landing on an operator.

    We cite the IDs as facility evidence. We will not invent a PI. We will not claim bioaccess® ran any of them. No live bioaccess® case-study page names this university as a client site.

    That is the leak: a founder searching Unicamp Campinas first-in-human finds ALL n=147 (DEVICE n=2) without finding ANVISA. A named university campus is still a site. An NCT location row is not a CRO.

    The site is the site. The CRO is the operator.

    A named university can provide rooms, coordinators, institutional ethics calendars, and investigators who already appear on NCT rows. That is necessary. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What the university can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing service line.
    • Share institutional ethics-committee calendars and hospital research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the university is not built to own for an investigational device:

    • ANVISA. Device investigations sit under RDC 837/2023 (dossier in Portuguese: IB, protocol, ICF, insurance, GMP evidence). A hallway conversation at this campus is not that dossier. A hallway conversation at Unicamp is not a Celso Pierro file and is not a Loema file.
    • Investigational import. Ethics letter, investigator’s brochure, and an importation permit — end-to-end work, not a PI email. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a campus-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF. The site may run visits. The CRO runs the quality system the FDA will later ask about.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after GCP / ethics documentation. Eligibility is not clearance, and a site MSA does not produce it.
    • Multi-country optionality. If enrollment or the indication later needs another Latin American country, a single-hospital MSA will not stretch.

    Going direct to this campus is how you confirm a room. It is not how you open an investigational file.

    How ANVISA actually works (the short version)

    Use clinical-trials-brazil: combined ethics + ANVISA typically 6–10 weeks under Law 14874 and RDC 837/2023; CEPs capped at 30 business days; published per-patient range $20,000–$35,000. Trial authorization and later market registration are separate workstreams.

    Ask for a protocol-specific calendar. A hospital email is not ANVISA clearance. bioaccess® manages the file. That is CRO work, not site work.

    All bioaccess® device protocols in this country are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval. See OUS FIH and FDA IDE.

    Do not smear the hospital

    Unicamp is a serious named Campinas campus on the public registry. ALL n=147 and DEVICE n=2 are registry volume, not a punchline. Do not invent a PI. Use the site when the protocol fits. Hire the operator.

    What the CRO still does after you have the campus on a slide

    1. Regulatory-fit, not tourism. This geography is sourced. One campus is not automatically the right room for every indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the ANVISA / ethics packet.
    3. Importer of record and device accountability.
    4. Site activation that is more than a tour: contracts, training, investigational product, EDC, monitoring plan. Activate this campus only if it fits the protocol.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative so the dataset is built for a later Pre-Sub, IDE, 510(k), De Novo, PMA, or HDE — eligibility, not a promise of FDA action.

    The firm was founded in 2010. That is the operator layer around a campus string.

    Colombia is still on the map

    Public line, unchanged: bioaccess® still runs clinical trials in Colombia — local entity, Miami headquarters, own CRO in Colombia. Because INVIMA clinical-trial approval timelines have become unpredictable, bioaccess® does not currently recommend Colombia for new FIH trial execution. INVIMA commercial registration remains. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K as published on clinical-trials-panama. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract Unicamp Campinas directly for a device FIH?

    You can try. The university can discuss investigator interest, local visit costs, and ethics calendars. It cannot, by ranking on ClinicalTrials.gov, become your ANVISA applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Did bioaccess® run the NCT IDs listed here?

    No public bioaccess® case-study page names this university. We will not invent that claim. This page intercepts the search; it does not claim the studies.

    Is this the same page as Hospital Celso Pierro or Loema Campinas?

    No. Hospital Celso Pierro Campinas and Loema Instituto Pesquisa Campinas are already live on their own slugs. This page is Unicamp only.

    Did bioaccess® run NCT04171063?

    No. We cite it as facility evidence. We will not invent a sponsor or a PI.

    Next step

    If the search that brought you here was this campus, start as the operator: contact bioaccess® or book from First-in-Human CRO. Campinas sibling (do not merge): Hospital Celso Pierro Campinas.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • Hospital de Base São José do Rio Preto: The NCT Campus String Is Not the ANVISA File

    Figures cited from a ClinicalTrials.gov LATAM facility sweep (API pull 1 September 2026, 6:32 PM ET) and published bioaccess® country pages. Registry ranking is not a bioaccess® claim that we ran any of these studies. General information, not legal or regulatory advice. Confirm current ANVISA, ethics, and FDA rules with qualified advisers. We name only the facility strings and example NCT IDs those sources support. We do not invent a principal investigator. We do not claim Hospital de Base São José do Rio Preto as a bioaccess® client.

    If you searched Hospital de Base Sao Jose do Rio Preto first-in-human, Hospital de Base SJRP clinical trial, Hospital de Base Rio Preto CRO, or “go direct Hospital de Base São José do Rio Preto,” you followed a campus string ClinicalTrials.gov still publishes. Hospital de Base in São José do Rio Preto, Brazil, is a real named hospital-campus string on ClinicalTrials.gov. It is not a first-in-human medical-device CRO, and it is not the operator of the ANVISA file.

    bioaccess®’s position is simple and it is not adversarial: the hospital is the site. The First-in-Human CRO still owns ANVISA, CEP / CONEP, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if this campus is not the only fit. Sponsors who skip the CRO and email the hospital still have to rebuild that stack. An NCT location row is not a CRO.

    This page is the named São José do Rio Preto Hospital de Base campus. It is DISTINCT from hospital-de-base-distrito-federal-brasilia-fih (Brasília / Distrito Federal — different city, different campus). It is not FAMERP São José do Rio Preto (already live). Sharing a Hospital de Base name is not a license to collapse Brasília and São José do Rio Preto. SJRP Hospital de Base is not Brasília Hospital de Base.

    Why the campus name wins the search — and why that is not a CRO

    Device registries write the city, the hospital, and a list of NCT IDs. They rarely write the CRO. On the 1 September 2026 ClinicalTrials.gov LATAM sweep (interventional studies; all years; complete dump), this campus sits here after filters:

    Counts come from leftover unique strings after the last live leftover-site batch plus unique NCT IDs in /workspace/five-trials/ctgov-raw/all_interventional.jsonl (17497 studies; ClinicalTrials.gov LATAM facility sweep, API pull 1 September 2026, 6:32 PM ET; dump confirmed 1 September 2026). Alias strings are listed separately. We do not publish a unique-study union across alias strings. We do not invent a global CSV rank. We do not invent unpublished CMS IDs. Registry ranking is not a bioaccess® claim that we ran any of these studies.

    • Hospital de Base (São José do Rio Preto, Brazil) — canonical NCT string: ALL interventional n=210; DEVICE n=1. Example NCT IDs: NCT04701684.

    Cite canonical ALL n=210 and DEVICE n=1. Do not clone Hospital de Base Distrito Federal Brasília onto this slug.

    Those are unique NCT IDs per facility string + city + country. They are not a count of first-in-human device programs bioaccess® ran. They are how a sponsor searching the hospital name lands on a campus without landing on an operator.

    We cite the IDs as facility evidence. We will not invent a PI. We will not claim bioaccess® ran any of them. No live bioaccess® case-study page names this hospital as a client site.

    That is the leak: a founder searching Hospital de Base São José do Rio Preto first-in-human finds ALL n=210 (DEVICE n=1) without finding ANVISA. A named hospital campus is still a site. An NCT location row is not a CRO.

    The site is the site. The CRO is the operator.

    A named hospital can provide rooms, coordinators, institutional ethics calendars, and investigators who already appear on NCT rows. That is necessary. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What the hospital can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing service line.
    • Share institutional ethics-committee calendars and hospital research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the hospital is not built to own for an investigational device:

    • ANVISA. Device investigations sit under RDC 837/2023 (dossier in Portuguese: IB, protocol, ICF, insurance, GMP evidence). A hallway conversation at this campus is not that dossier. A hallway conversation at Hospital de Base São José do Rio Preto is not a Brasília Distrito Federal Hospital de Base file.
    • Investigational import. Ethics letter, investigator’s brochure, and an importation permit — end-to-end work, not a PI email. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a campus-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF. The site may run visits. The CRO runs the quality system the FDA will later ask about.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after GCP / ethics documentation. Eligibility is not clearance, and a site MSA does not produce it.
    • Multi-country optionality. If enrollment or the indication later needs another Latin American country, a single-hospital MSA will not stretch.

    Going direct to this campus is how you confirm a room. It is not how you open an investigational file.

    How ANVISA actually works (the short version)

    Use clinical-trials-brazil: combined ethics + ANVISA typically 6–10 weeks under Law 14874 and RDC 837/2023; CEPs capped at 30 business days; published per-patient range $20,000–$35,000. Trial authorization and later market registration are separate workstreams.

    Ask for a protocol-specific calendar. A hospital email is not ANVISA clearance. bioaccess® manages the file. That is CRO work, not site work.

    All bioaccess® device protocols in this country are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval. See OUS FIH and FDA IDE.

    Do not smear the hospital

    Hospital de Base São José do Rio Preto is a serious named Brazilian campus on the public registry. ALL n=210 and DEVICE n=1 are registry volume, not a punchline. Do not invent a PI. Use the site when the protocol fits. Hire the operator.

    What the CRO still does after you have the campus on a slide

    1. Regulatory-fit, not tourism. This geography is sourced. One campus is not automatically the right room for every indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the ANVISA / ethics packet.
    3. Importer of record and device accountability.
    4. Site activation that is more than a tour: contracts, training, investigational product, EDC, monitoring plan. Activate this campus only if it fits the protocol.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative so the dataset is built for a later Pre-Sub, IDE, 510(k), De Novo, PMA, or HDE — eligibility, not a promise of FDA action.

    The firm was founded in 2010. That is the operator layer around a campus string.

    Colombia is still on the map

    Public line, unchanged: bioaccess® still runs clinical trials in Colombia — local entity, Miami headquarters, own CRO in Colombia. Because INVIMA clinical-trial approval timelines have become unpredictable, bioaccess® does not currently recommend Colombia for new FIH trial execution. INVIMA commercial registration remains. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K as published on clinical-trials-panama. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract Hospital de Base São José do Rio Preto directly for a device FIH?

    You can try. The hospital can discuss investigator interest, local visit costs, and ethics calendars. It cannot, by ranking on ClinicalTrials.gov, become your ANVISA applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Did bioaccess® run the NCT IDs listed here?

    No public bioaccess® case-study page names this hospital. We will not invent that claim. This page intercepts the search; it does not claim the studies.

    Is this the same page as Hospital de Base Distrito Federal Brasília?

    No. hospital-de-base-distrito-federal-brasilia-fih is already live for the Brasília campus. This page is Hospital de Base São José do Rio Preto only — different city.

    Did bioaccess® run NCT04701684?

    No. We cite it as facility evidence. We will not invent a sponsor or a PI.

    Next step

    If the search that brought you here was this campus, start as the operator: contact bioaccess® or book from First-in-Human CRO. Distinct Brasília sibling (do not merge): Hospital de Base Distrito Federal Brasília.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • Understanding MDR Clinical Trials: An In-Depth Tutorial for Medical Professionals

    Understanding MDR Clinical Trials: An In-Depth Tutorial for Medical Professionals

    Introduction

    Navigating the intricate landscape of medical device regulation is crucial for the success of clinical trials under the Medical Device Regulation (MDR). As the industry grapples with a complex web of compliance requirements, particularly for startups facing unique challenges, understanding the nuances of these regulations becomes paramount.

    This article delves into essential strategies for ensuring compliance, effective data management, and ethical oversight throughout the lifecycle of MDR clinical trials. By addressing key considerations such as:

    • Informed consent
    • Ongoing monitoring
    • Adaptive marketing strategies

    medical professionals can enhance their trial outcomes and maintain a competitive edge in the evolving healthcare landscape.

    are subject to a multifaceted regulatory landscape, primarily governed by (EU) 2017/745, alongside various national laws that can influence the execution of these studies. Navigating these regulations is imperative for ensuring compliance and achieving successful outcomes, particularly for facing unique challenges such as regulatory hurdles, competition, recruitment issues, and financial constraints. Key considerations include:

    1. : Familiarizing yourself with the specific stipulations detailed in the MDR, including aspects such as risk classification and clinical evaluation processes, is fundamental to the study’s design and execution.
    2. : Each EU member state may impose additional regulations that can influence how experiments are conducted. Understanding these local nuances is crucial for seamless implementation and compliance in .
    3. Engagement with , such as the European Medicines Agency (EMA), is essential for ensuring that align with regulatory expectations and for preemptively addressing any compliance issues.
    4. : Timeliness and accuracy in to cannot be overstated, as these elements are critical for maintaining study integrity and fulfilling compliance obligations.

    Alongside these factors, our offerings include feasibility and selection of research locations and principal investigators (PIs), setup, and thorough study project management. In a recent presentation titled , Walker Bradham emphasized the challenges faced in medical device research, advocating for solutions that enhance efficiency and adaptability in operational processes. The conversation emphasized Zelta’s research platform as a valuable resource to simplify procedures and enhance speed to insights in studies.

    Furthermore, the importance of patient information in research studies is highlighted by the MAUDE Patient Information statistics:

    • 134032KB compressed
    • 1130935KB uncompressed
    • A total of 20457749 records

    This emphasizes the extent to which patient information can influence clinical research outcomes. Nicole Latimer, CEO of Medrio, stated, “Utilizing can provide invaluable insights that shape your commercialization plans.”

    This authoritative viewpoint emphasizes the significance of ePRO information in navigating the complexities of . Furthermore, it is essential to recognize that the file associated with these data does not comply with accessibility standards, a crucial compliance factor that must be addressed in the context of MDR studies. Integrating these components will enable healthcare professionals, including authorities like Ana Criado and Katherine Ruiz, to manage the intricacies of MDR assessments more efficiently.

    For additional help, we invite you to SCHEDULE A MEETING with our team to discuss how we can assist with your research requirements.

    The Role of Data Management and Integration in Successful MDR Trials

    depend on strong and integration strategies. At bioaccess®, we specialize in comprehensive , ensuring that every aspect of the study is meticulously handled. Our expertise encompasses a range of studies, including (EFS), (FIH), Pilot Studies, , and (PMCF).

    Key considerations include:

    1. : Implementing standardized methods for is crucial to ensure consistency and reliability across all trial sites. This not only enhances the integrity of the information but also supports accurate comparisons and analyses. For instance, in the old age subgroup, the response rate for the new therapy is 0.7 compared to 0.35 for the control, underscoring the importance of effective in achieving reliable outcomes.
    2. : Utilizing integrated systems streamlines entry, monitoring, and reporting processes. Such systems, as facilitated by bioaccess®, enable the secure movement of over 60 million healthcare records across thousands of organizations, which is essential for successful clinical studies.
    3. Real-Time Information Access: Ensuring that researchers have access to real-time information is vital for timely decision-making and risk mitigation. This capability allows for immediate responses to emerging issues, thus minimizing disruptions during the test.
    4. : Establishing stringent protocols for information security is essential for compliance with regulations such as GDPR, which protect patient information. Data security not only protects participant confidentiality but also boosts the credibility of the study results. Dr. John Griffin emphasizes the importance of these practices, stating, “Effective strategies are the backbone of successful clinical trials.”
    5. Discrepancy Management: Real-world applications of practices are illustrated through case studies, such as the discrepancy management approach where inconsistencies in information are identified and managed through clarification from investigators or self-evident corrections. The CDM team at bioaccess® regularly reviews discrepancies, ensuring resolutions are documented and maintaining the accuracy of the data, although some discrepancies may remain unresolved.

    By prioritizing these strategies and leveraging our specialized services, medical professionals can significantly enhance the quality and compliance of their MDR clinical trials. Moreover, the significance of confidence intervals in assessing effect size cannot be overstated, as low p-values alone do not indicate practical relevance. Incorporating these practices establishes the foundation for successful outcomes and guarantees compliance with best practices in research.

    Ensuring Compliance with Good Clinical Practice in MDR Trials

    Following (GCP) is essential for the successful execution of mdr . The following key aspects are essential:

    1. : It is essential that all participants provide , ensuring they fully comprehend the study’s nature, associated risks, and potential benefits.

      Current statistics indicate that rates in clinical studies have fluctuated, with recent data showing that only 65% of participants fully understand the consent they provide. This highlights the need for continued focus on effective consent processes.

    2. : Strict adherence to the study protocol is necessary to maintain the integrity and reproducibility of results.

      Variations from the protocol can compromise the validity of the results.

    3. : All personnel involved in the study must be adequately trained and qualified for their specific roles. Regular staff training is a strategy that upholds compliance and ensures that team members are well-versed in GCP requirements.

    4. : Implementing systematic processes is crucial for proactively identifying and addressing compliance issues. Recent news underscores the importance of these practices in maintaining adherence to GCP guidelines.

    5. : Establishing robust is essential for ensuring that all study processes meet and enhance the overall integrity of the research.

    6. : Encouraging a culture of compliance within the research team promotes ethical practices and adherence to GCP, further safeguarding participant rights and data integrity.

    7. Experiment Setup and Import Authorizations: Effective experiment setup and obtaining necessary import authorizations are crucial steps that ensure compliance with local regulations and facilitate the smooth conduct of research studies.

    8. Reporting: Comprehensive reporting on study status, inventory, and both serious and non-serious adverse events is essential for maintaining transparency and accountability throughout the research process.

    By emphasizing these GCP elements in mdr , medical professionals can uphold ethical standards and enhance the credibility of their research. Moreover, the extensive research management services we provide, including feasibility studies, site selection, compliance evaluations, setup, import permits, project oversight, and reporting, align with the regulatory requirements established by INVIMA, Colombia’s National Food and Drug Surveillance Institute. These principles provide a roadmap for researchers to conduct studies that respect participants and uphold scientific integrity, as noted in the case study titled ‘5 Essential Ethical Guidelines for Accurate Research in 2024.’

    As highlighted by Stocken DD, GCP but not as you know it, this emphasizes the evolving nature of compliance in .

    Post-Market Surveillance and Ethical Oversight in MDR Clinical Trials

    is a vital aspect of the device lifecycle, ensuring that safety and effectiveness are maintained long after a product’s initial approval. In Colombia, the (Instituto Nacional de Vigilancia de Medicamentos y Alimentos) plays a crucial role in this process as the national regulatory authority responsible for overseeing health products, including medical devices. Key components of an effective strategy include:

    1. Ongoing Monitoring: Developing comprehensive strategies for the continuous assessment of device performance and safety is essential. ‘s Directorate for Medical Devices and other Technologies monitors pre- and post-market programs through systematic data collection and analysis to ensure compliance with health standards.
    2. : Establishing a robust system for promptly reporting and addressing adverse events to regulatory authorities is crucial. This system not only fulfills regulatory obligations but also demonstrates a manufacturer’s commitment to . , such as those mandated by , is necessary for effective monitoring of device performance.
    3. : Engaging with ethics committees during the post-market phase is critical to ensuring that ethical standards are maintained. These committees play an essential role in overseeing the ethical implications of ongoing trials and surveillance efforts.
    4. : Creating effective channels for collecting patient feedback enables manufacturers to incorporate real-world experiences into safety evaluations. This patient-centered approach helps inform device improvements and enhances overall safety outcomes.
    5. : For instance, a case study titled “Regulatory Compliance in PMS” illustrates how compliance with ’s regulations is essential for manufacturers to demonstrate their commitment to and effective monitoring of device performance. This case study highlights specific methodologies employed by in monitoring and evaluating health devices post-market.
    6. : As industry leaders emphasize, a proactive stance on is fundamental for the future of health devices in the digital health and MedTech sectors. Katherine Ruiz, an expert in Regulatory Affairs, notes that continuous improvement in these areas is vital for addressing emerging challenges in public health.

    These elements together guarantee that healthcare practitioners follow safety regulations and ethical methods during their examinations, ultimately aiding in . Recent statistics indicate that rates have significantly increased in 2024, highlighting the growing emphasis on transparency and accountability in , further supported by ‘s classification as a Level 4 health authority by PAHO/WHO.

    Strategies for Maintaining Market Presence Post-Trial

    Following the completion of MDR , maintaining a robust market presence for demands a multifaceted strategic approach:

    1. : It is crucial to develop targeted marketing campaigns that not only highlight the unique benefits and safety of the device but also resonate with potential users. The IMARC Group has projected a , from $22.4 billion in 2022 to $29.2 billion by 2028, indicating a growing willingness among healthcare companies to invest in effective content and lead generation strategies. Furthermore, the , presenting a substantial opportunity for growth. Importantly, the ripple effects of Medtech clinical studies extend beyond the companies themselves, contributing to job creation and economic growth in local communities while also enhancing international recognition for the innovations developed.

    2. : Establishing and nurturing strong relationships with key stakeholders—such as healthcare providers, payers, and regulatory bodies—is essential for facilitating . As one leader in the defense sector observed,

      Thank you for sending and information. It looks quite comprehensive and the data is exactly what I was looking for. I appreciate the timeliness and responsiveness of you and your team.

      This feedback underscores the value of responsive stakeholder engagement. Additionally, experts emphasize that ongoing dialogue with stakeholders can lead to innovative solutions and improved market strategies, further enhancing the international collaboration aspect of Medtech initiatives.

    3. : Providing ongoing education and training for users ensures that they understand the proper use and application of the device. This initiative is critical in enhancing user confidence and compliance, which ultimately contributes to successful adoption and improved healthcare outcomes in the communities served.

    4. Adaptation to Market Changes: Staying attuned to industry trends and regulatory requirements is imperative. The COVID-19 pandemic has significantly accelerated the adoption of , emphasizing the need for device companies to adapt their marketing strategies accordingly. For instance, a study conducted by the National Center for Health Statistics revealed that 59% of U.S. adults seek health or wellness information online, emphasizing the importance of a strong online presence. Health-related searches significantly drive traffic to hospital websites, indicating that effective online engagement can enhance market visibility while also promoting healthcare improvement within local economies. By adapting to these changes, companies can not only improve healthcare outcomes but also solidify their position in the international market.

    By implementing these strategic considerations, medical professionals can effectively navigate the post-trial landscape, ensuring that their devices remain competitive, compliant, and responsive to market needs, all while contributing positively to the economic fabric of the regions they engage with.
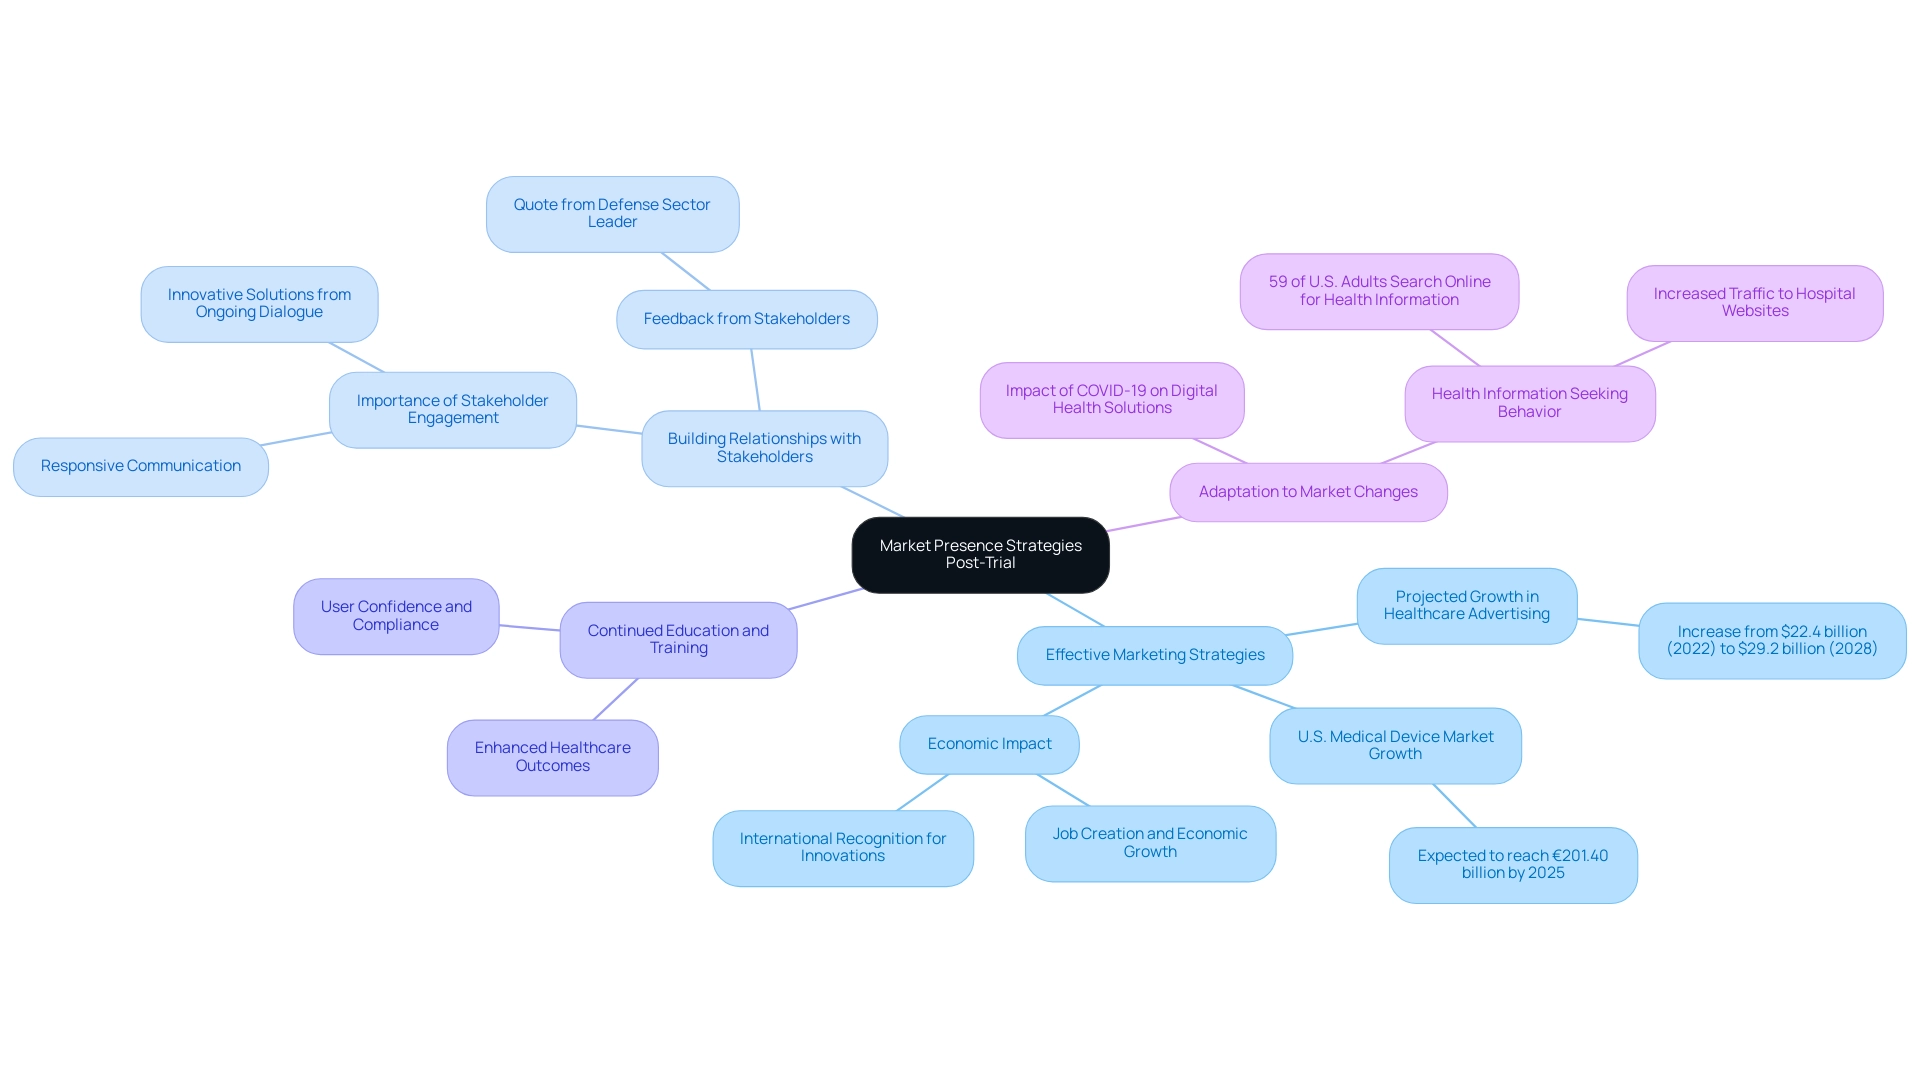
    Each branch represents a key strategy, with sub-branches detailing specific actions and insights related to that strategy.

    Conclusion

    Navigating the complexities of medical device regulation is essential for the success of clinical trials under the Medical Device Regulation (MDR). The article outlines several critical strategies that medical professionals and startups must adopt to ensure compliance and enhance trial outcomes. Understanding the specific requirements of the MDR, engaging with regulatory bodies, and maintaining rigorous documentation practices are foundational to successful trial execution.

    Moreover, effective data management and integration play a pivotal role in ensuring the integrity and reliability of clinical trials. By implementing standardized data collection methods and utilizing integrated data systems, researchers can foster a robust environment for decision-making and risk management. This is further complemented by a strong commitment to Good Clinical Practice (GCP), which safeguards ethical standards and participant rights throughout the trial lifecycle.

    Post-market surveillance and ethical oversight are equally important, as they ensure ongoing compliance and safety of medical devices after approval. The emphasis on continuous monitoring, adverse event reporting, and patient feedback mechanisms reflects a proactive approach to maintaining product efficacy and public trust.

    Finally, the strategies discussed for maintaining market presence post-trial highlight the necessity for effective marketing, stakeholder engagement, and adaptability to industry changes. By prioritizing these elements, medical professionals can not only enhance their competitive edge but also contribute positively to the healthcare landscape.

    In summary, a comprehensive understanding of MDR requirements, coupled with strategic planning and ethical oversight, is vital for the success of clinical trials. Embracing these practices will empower medical professionals to navigate the regulatory landscape effectively, ultimately leading to improved patient outcomes and sustained market presence.

    Frequently Asked Questions

    What governs MDR clinical trials?

    MDR clinical trials are primarily governed by the Medical Device Regulation (EU) 2017/745, along with various national laws that can influence the execution of these studies.

    Why is it important to navigate the regulatory landscape for MDR clinical trials?

    Navigating the regulatory landscape is crucial for ensuring compliance and achieving successful outcomes, especially for medical device startups that face unique challenges such as regulatory hurdles, competition, recruitment issues, and financial constraints.

    What are the key considerations for conducting MDR clinical trials?

    Key considerations include understanding MDR requirements, navigating national regulations, engaging with regulatory bodies like the European Medicines Agency (EMA), and ensuring timely and accurate documentation and reporting.

    How can understanding MDR requirements benefit a clinical trial?

    Familiarizing oneself with specific stipulations in the MDR, such as risk classification and clinical evaluation processes, is fundamental to the design and execution of the study.

    What role do national regulations play in MDR clinical trials?

    Each EU member state may impose additional regulations that influence how experiments are conducted, making it essential to understand these local nuances for seamless implementation and compliance.

    Why is engagement with regulatory bodies important?

    Engaging with regulatory bodies ensures that MDR clinical trials align with regulatory expectations and helps preemptively address any compliance issues.

    What is the significance of documentation and reporting in MDR studies?

    Timeliness and accuracy in documentation and reporting are critical for maintaining study integrity and fulfilling compliance obligations with regulatory bodies.

    What challenges do medical device researchers face according to recent discussions?

    Challenges include regulatory hurdles, competition, recruitment issues, and financial constraints, emphasizing the need for solutions that enhance efficiency and adaptability in operational processes.

    How can patient information impact clinical research outcomes?

    Patient information, particularly patient-reported outcomes, can provide invaluable insights that shape commercialization plans and influence clinical research outcomes.

    What is the importance of information management in MDR clinical trials?

    Effective information management is crucial for ensuring consistency, reliability, and compliance with regulations, thereby enhancing the quality of clinical trials.

    What strategies can enhance information management in clinical studies?

    Key strategies include standardized information gathering, integrated information systems, real-time information access, stringent security protocols, and effective discrepancy management.

    How does effective information management contribute to clinical trial success?

    It enables timely decision-making, enhances data integrity, and ensures compliance with regulations, ultimately leading to successful outcomes in MDR clinical trials.

    List of Sources

    1. Navigating Legal and Regulatory Frameworks in MDR Clinical Trials
      • MDR Data Files (https://fda.gov/medical-devices/medical-device-reporting-mdr-how-report-medical-device-problems/mdr-data-files)
      • bfarm.de (https://bfarm.de/SharedDocs/Downloads/EN/Service/Statistik/AM_statistics/stat-2024-internet.html)
      • scopesummit.com (https://scopesummit.com/24/medical-device-trials)
    2. The Role of Data Management and Integration in Successful MDR Trials
      • Common statistical concerns in clinical trials – PMC (https://pmc.ncbi.nlm.nih.gov/articles/PMC3059317)
      • datavant.com (https://datavant.com/clinical-research/clinical-data-management)
      • Data management in clinical research: An overview – PMC (https://pmc.ncbi.nlm.nih.gov/articles/PMC3326906)
    3. Ensuring Compliance with Good Clinical Practice in MDR Trials
      • infonetica.net (https://infonetica.net/articles/clinical-research-compliance)
      • blog.whitehalltraining.com (https://blog.whitehalltraining.com/good-clinical-practice/guidelines)
      • Good Statistical Practice—development of tailored Good Clinical Practice training for statisticians – PMC (https://pmc.ncbi.nlm.nih.gov/articles/PMC10858586)
    4. Post-Market Surveillance and Ethical Oversight in MDR Clinical Trials
      • nsf.org (https://nsf.org/knowledge-library/post-market-surveillance-what-you-need-to-know-to-ensure-patient-safety)
    5. Strategies for Maintaining Market Presence Post-Trial
      • statista.com (https://statista.com/outlook/hmo/medical-technology/worldwide)
      • Medical Devices Market Size, Share, Global Growth Report 2034 (https://fortunebusinessinsights.com/industry-reports/medical-devices-market-100085)
      • 29 Healthcare Marketing Statistics To Know for 2024 | NYTLicensing (https://nytlicensing.com/latest/trends/healthcare-marketing-stats)

  • Dr. Juan Osorio, Chondrograft FIH Principal Investigator in Panamá: The Named PI Is Not the MINSA File

    Figures cited from the PR Newswire release “Nanochon Performs First Case in the Chondrograft™ First in Human Clinical Study” (2 September 2026, 16:58 ET), the live ClinicalTrials.gov record NCT07542184 (last update posted 21 August 2026; first posted 21 April 2026), and published bioaccess® Panama pages, verified 3 September 2026. General information, not legal or regulatory advice. Confirm current MINSA, CNBI, and FDA rules with qualified advisers. We name only the investigators, facility, and trial those sources support, and we do not reprint site contact emails or phone numbers. Nanochon is not claimed as a bioaccess® client. bioaccess® is not listed on this NCT and did not run this study.

    If you searched Dr. Juan Osorio Panamá, Juan Osorio principal investigator Chondrograft, Emilio Tufiño knee cartilage trial, Nanochon first case Panamá, or “go direct to the surgeon,” you followed an investigator string that public press and ClinicalTrials.gov both publish. Dr. Juan Osorio is a real named principal investigator. He is not the operator of the MINSA file.

    bioaccess®’s position is simple and it is not adversarial: the investigator is the investigator and the hospital is the site. The First-in-Human CRO still owns MINSA / CNBI, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Panamá is not the only fit. Sponsors who skip the CRO and email the surgeon still have to rebuild that stack. A principal-investigator line does not become a CRO.

    This is a person-string intercept, and it exists only because the building already has its own page. The facility intercept stays at The Panama Clinic (Spanish: versión en español), and the distinct legal-entity string stays at CEVAXIN / The Panama Clinic. This page does not clone clinical trials in Panama. That page stays the country operating system.

    Why the surgeon’s name wins the search — and why that is not a CRO

    On 2 September 2026, Nanochon announced the successful treatment of the first patient in its First-in-Human study of Chondrograft™, a 3D-printed implant for articular cartilage defects of the knee. Per that release: Dr. Juan Osorio and Dr. Emilio Tufiño, both specialists in regenerative sports medicine, performed the first procedure at The Panama Clinic, Panamá. Dr. Osorio is quoted in the release identifying himself as the Principal Investigator for the study. Dr. Tufiño is quoted describing the procedure as “bone-sparing, minimally invasive, and streamlined.” The release also states that Nanochon plans a Level 1 multi-center, randomized, controlled pivotal trial after the FIH study, and that Chondrograft™ has FDA Breakthrough Device Designation. No CRO is named anywhere in that release.

    The registry says the same thing in registry language. NCT07542184 — brief title: Nanochon Chondrograft First in Human (FIH) Early Feasibility Study (EFS) – Panama. Official title: A First in Human (FIH) Early Feasibility Study (EFS) to Evaluate the Safety and Performance of the Nanochon Chondrograft™ Implant for Re-surfacing of Cartilage Lesions. Organization study ID: 101-2024 – PAN. Lead sponsor: Nanochon, Inc., class INDUSTRY, responsible party the sponsor. No collaborator is listed. No CRO is listed.

    Design on the 3 September 2026 snapshot: interventional; single-group; no masking; primary purpose treatment; phase N/A; estimated enrollment 5. Actual start 30 July 2026; estimated primary completion and completion September 2027. Study first posted 21 April 2026; last update posted 21 August 2026 — that is, before the 2 September first-case announcement. Status RECRUITING. Condition: knee cartilage lesions, with registry keywords for medial and lateral femoral condyle and trochlear articular cartilage lesions. Intervention: a device — mini-arthrotomy or arthroscopic surgical implantation of the Nanochon Chondrograft. Eligibility: male or female aged 22–60, MRI knee evaluation within six months, able to read and speak English and/or Spanish, and voluntary signature of the REB-approved informed consent.

    The single Panama location row is The Panama Clinic, Panama City, Provincia de Panamá, RECRUITING, with Juan Osorio, MD listed as PRINCIPAL_INVESTIGATOR. That is the registry’s own field, not our inference. A sister Canadian record, NCT07249489 (same official title, org study ID 101-2024-CAN, estimated n=10, NOT_YET_RECRUITING, last update posted 2 September 2026), lists University of British Columbia in Vancouver and an Orthopaedic Clinic in Toronto. Canada is outside the Latin American geography this page covers; we note it so nobody merges the two records.

    Read the two sources together. An estimated five patients, a 3D-printed implant, a Breakthrough-designated device, a planned pivotal RCT to follow — and the only human names a sponsor can find are two surgeons and a company CEO. That is the site-direct leak in its purest form: the search resolves to a person, and the person is not the operator of the file.

    The investigator is the investigator. The CRO is the operator.

    A regenerative sports-medicine surgeon in Panama City can carry the procedure, the surgical judgement, the follow-up exams, and the source documents. That is necessary, and on this program it is clearly working — the first case was enrolled and treated quickly enough that the sponsor made a point of it. It is still not the same job as owning a first-in-human file.

    What a named investigator and their hospital can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and surgical feasibility for a cartilage protocol — when that service is available and appropriate for your device, which is not automatic.
    • Share institutional ethics-committee calendars and hospital research rules.
    • Quote procedure, theatre, and local staffing costs for the cases they will physically perform.

    What an investigator is not built to own for an investigational device:

    • MINSA and the CNBI. The national file and the national bioethics pathway are not a hallway conversation with a surgeon.
    • Investigational import. Ethics letter, investigator’s brochure, and an importation permit, end to end. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. The published bioaccess® Panama planning band is $5,000–$15,000 depending on device risk and enrollment. That is a published planning band, not a quote for this study.
    • ISO 14155 monitoring, EDC, adverse-event reporting, and the TMF — across Panamá and any second country.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after the GCP and ethics documentation that rule defines. Eligibility is not clearance. See OUS FIH and FDA IDE.
    • Multi-country optionality. A five-patient EFS that is meant to feed a Level 1 pivotal trial is exactly when one surgeon’s calendar stops being the plan.

    Going direct to Dr. Osorio is how you confirm a surgeon. It is not how you open an investigational file.

    Investigator versus CRO

    Workstream What the named investigator and hospital typically own What the CRO still owns
    Procedure Mini-arthrotomy or arthroscopic implantation, imaging, follow-up exams Protocol fit, training, implant accountability
    Ethics Institutional committee calendar and local rules Packet, ICF, IB alignment, deficiency cycle
    National authority Not the permit holder by being named as PI MINSA / CNBI file
    Import Receiving and storage if contracted Importer of record for the investigational implant
    Quality Source documents from the cases performed ISO 14155 monitoring, EDC, AE reporting, TMF
    FDA conversation Clinical judgement and case data 21 CFR 812.28 narrative — eligibility, not clearance
    Scale-up One surgical team in Panama City Second country, pivotal readiness, Colombia (INVIMA) and the rest of the platform

    What the Nanochon public file actually supports — and what it does not

    • Device: Chondrograft™, a 3D-printed implant for focal articular cartilage defects of the knee, with FDA Breakthrough Device Designation per the company release.
    • Sponsor: Nanochon, Inc. (industry). No collaborator on the NCT. No CRO named in the release or on the record.
    • Site: The Panama Clinic, Panama City — the only Panama location row, RECRUITING. Already intercepted on its own page.
    • Named investigators (as published): Juan Osorio, MD — principal investigator on the NCT row and self-identified as PI in the 2 September release; Emilio Tufiño, MD — named in the release as performing the first procedure. We do not merge them into a single identity and we do not add a third name.
    • Milestone: first patient treated, announced 2 September 2026. Actual study start on the registry is 30 July 2026.
    • Not claimed here: that bioaccess® ran this study or is on this NCT; that Nanochon is a bioaccess® client; that we have Chondrograft outcomes; that Breakthrough Device Designation is clearance or approval; that the Panama and Canada records are one study.

    What the CRO still does after you have a surgeon’s name

    • Regulatory-fit, not tourism. Panamá is a lead first-in-human jurisdiction on the published platform. It is not automatically the right country for every indication. bioaccess® still runs clinical trials in Colombia and the rest of the platform.
    • Protocol, IB, ICF, insurance, and the MINSA / CNBI packet.
    • Importer of record and implant accountability.
    • ISO 14155 monitoring and the 21 CFR 812.28 narrative for the FDA conversation that a Breakthrough-designated implant will eventually need.
    • Optionality when a five-patient EFS has to become a multi-centre pivotal study.

    The founder podcast, when a conversation needs a voice, is Global Trial Accelerators™. Background: LATAM FIH hospitals vs the CRO.

    Frequently asked questions

    Why is there a page for a person rather than only for the hospital?

    Because sponsors search the string they see, and the 2 September release put two surgeons’ names in front of the building. The facility page already exists at The Panama Clinic, and the legal-entity page exists at CEVAXIN. This page answers the investigator query and links back rather than duplicating either one.

    Can I contract Dr. Osorio directly?

    You can try. A principal investigator can discuss surgical feasibility, institutional ethics calendars, and local case costs. He cannot become your MINSA applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager because a press release named him. Contract the CRO; let the CRO activate the site and the investigator.

    Did bioaccess® run the Chondrograft first-in-human study?

    No. No public bioaccess® page says so, bioaccess® is not on NCT07542184, and we will not invent that relationship. This page intercepts the search; it does not claim the study.

    Does Breakthrough Device Designation mean the implant is approved?

    No. The company release states the designation; a designation is a review-interaction pathway, not clearance or approval. A first-in-human EFS is still an investigational study, and foreign data still has to meet 21 CFR 812.28 conditions to be eligible for FDA submission and review.

    Is Colombia still an option?

    Yes. bioaccess® still runs trials in Colombia. A Panamá investigator search is not an instruction to abandon INVIMA. See CRO in Colombia.

  • Centro de Intervenciones Cardiovasculares Santiago de los Caballeros: Named Akura ATC Site, Not the DIGEMAPS File

    Figures cited from the live ClinicalTrials.gov record NCT06152341 (last update posted 31 August 2026; first posted 30 November 2023) and the published bioaccess® Dominican Republic country page, verified 3 September 2026. General information, not legal or regulatory advice. Confirm current DIGEMAPS, CONABIOS, and FDA rules with qualified advisers. We name only the facility and the trial those sources support. No principal investigator is named on this NCT location row; we will not invent one. Akura Medical is not claimed as a bioaccess® client. bioaccess® is not listed on this NCT.

    If you searched Centro de Intervenciones Cardiovasculares clinical trial, CIC Santiago de los Caballeros, Akura Medical ATC System, pulmonary embolism thrombectomy Dominican Republic, or “go direct to the Santiago site,” you followed a facility string ClinicalTrials.gov still publishes on 31 August 2026. Centro de Intervenciones Cardiovasculares in Santiago de los Caballeros, Santiago Province, is a real named cardiovascular facility on that record. It is not the operator of the DIGEMAPS file.

    bioaccess®’s position is simple and it is not adversarial: Centro de Intervenciones Cardiovasculares is the site. The First-in-Human CRO still owns DIGEMAPS, CONABIOS-overseen ethics, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia, Panama, or another Latin American country if Santiago is not the only fit. Sponsors who skip the CRO and email the hospital still have to rebuild that stack. An NCT location row does not become a CRO.

    This page is the intercept for the Santiago de los Caballeros query. It does not clone clinical trials in the Dominican Republic. That page stays the country operating system. Sister Dominican intercepts stay on their own buildings: Laser Center Santo Domingo, Instituto Espaillat Cabral, and Clínica Canela La Romana. Santiago de los Caballeros is a different city from Santo Domingo and from La Romana. Do not merge the slugs. The two São Paulo rows on the same NCT already have their own intercepts: Instituto Dante Pazzanese and InCor HCFMUSP.

    Why the hospital name wins the search — and why that is not a CRO

    NCT06152341 is an industry device listing. Brief title: Safety and Effectiveness of the ATC System in the Treatment of Acute PE. Official title: Safety and Effectiveness of the ATC System in the Treatment of Acute Pulmonary Embolism. Organization study ID: CP-60003. Lead sponsor: Akura Medical, class INDUSTRY, responsible party the sponsor. No collaborator is listed. No CRO is listed. The record publishes no central contact and no overall official.

    Design on the 3 September 2026 snapshot: interventional; prospective, single-arm, multicenter; no masking; primary purpose treatment; phase N/A; estimated enrollment 30. Actual start 15 May 2024; estimated primary completion April 2027; estimated completion May 2027. Study first posted 30 November 2023; last update posted 31 August 2026. Condition: acute pulmonary embolism.

    Status on that snapshot is SUSPENDED. The registry’s own reason, quoted as published: enrollment is temporarily paused pending device resupply to sites; enrollment is expected to resume to reach the target sample size following a recently approved protocol amendment; and the pause is not related to subject safety or device performance. We report that as written and add nothing to it.

    Intervention, in the registry’s words: a device — the ATC System, designed to mechanically remove emboli and restore blood flow through the pulmonary arteries in patients experiencing acute PE. The oversight module records the study as an FDA-regulated device study of an unapproved device that is a U.S. export. An unapproved, exported thrombectomy system running at 30 patients across three Latin American buildings is a CRO file, not a hospital favour.

    The three location rows currently published:

    • Instituto Dante Pazzanese de Cardiologia, São Paulo, Brazil — already intercepted.
    • Instituto do Coracao (InCor), São Paulo, Brazil — already intercepted.
    • Centro de Intervenciones Cardiovasculares, Santiago de los Caballeros, Santiago Province, Dominican Republic — this page. No principal investigator, contact, or row-level status is published for it.

    Read the record as it is. Two Brazilian cardiology institutes had public intercepts and the Dominican row did not, even though it is the only Caribbean building on an unapproved-device PE study. That is the site-direct leak: a sponsor searching Akura, ATC System, or Santiago de los Caballeros interventional cardiology lands on a named hospital with no operator in the public copy.

    Santiago de los Caballeros is a site. The CRO is the operator.

    A Dominican interventional-cardiology centre can provide cath-lab time, a PE response pathway, imaging, and operators who do pulmonary-artery work. That is necessary. It is not sufficient for an unapproved, U.S.-exported thrombectomy system a sponsor expects to defend to a U.S. board later.

    What a site can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and procedural feasibility for a PE protocol — when that service is available and appropriate for your device, which is not automatic.
    • Share institutional Research Ethics Committee calendars and hospital research rules.
    • Quote procedure, bed, and local staffing costs for the cases they will physically run.

    What the site is not built to own for an investigational device:

    • DIGEMAPS. The Ministry of Public Health, through the Dirección General de Medicamentos, Alimentos y Productos Sanitarios, is the national authority for health products including medical devices. A cath-lab conversation is not that submission.
    • CONABIOS-overseen ethics. The Consejo Nacional de Bioética en Salud oversees Research Ethics Committees; institutional REC review is tied to the host institution once the site is chosen.
    • Investigational import. A separate permit from the trial authorization and from a later commercial DIGEMAPS registration. The live importer-of-record guide already records DIGEMAPS as created by Decreto 82-15 (2015), with registration and import rules in Decreto 246-06. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a Santiago-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF — including across the two São Paulo rows on the same NCT.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after the GCP and ethics documentation that rule defines. Eligibility is not clearance. See OUS FIH and FDA IDE.
    • Multi-country optionality. A suspended-for-resupply study is precisely when a single-hospital MSA stops stretching.

    Going direct to Centro de Intervenciones Cardiovasculares is how you confirm a cath lab. It is not how you open an investigational file.

    Site versus CRO

    Workstream What the Santiago centre (site) typically owns What the CRO still owns
    Procedure Cath lab, PE pathway, imaging, local staff Protocol fit, training, device accountability and resupply logistics
    Ethics Institutional REC calendar and local rules Packet, ICF, IB alignment, deficiency cycle under CONABIOS oversight
    National authority Not the permit holder by being listed on an NCT DIGEMAPS clinical-trial file
    Import Receiving and storage if contracted Importer of record for an unapproved, U.S.-exported system
    Quality Hospital quality and the case ISO 14155 monitoring, EDC, SAE, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One Santiago building (plus two São Paulo rows on the same NCT) Colombia (INVIMA), Panama, and the rest of the bioaccess® platform

    How DIGEMAPS and CONABIOS sit next to the hospital

    Use clinical trials in the Dominican Republic for the full pathway. Facts a sponsor searching this hospital needs on one screen, already published there and not re-averaged here:

    • Institutional REC review averages ~30 days; CONABIOS-level review averages ~45 days, up to 120 depending on complexity.
    • DIGEMAPS is the national regulatory authority for health products including medical devices; CONABIOS oversees Research Ethics Committees.
    • Protocols follow the Declaration of Helsinki and the CIOMS international ethical guidelines. The submission package is in Spanish.
    • The country hub publishes ~30% lower program cost than a comparable U.S. or EU program — an experience-based estimate from work since 2010, not a formal study.
    • Under 21 CFR 812.28, foreign clinical data is eligible for FDA submission and review when the investigation meets that rule’s GCP conditions. Eligibility is not clearance or approval.
    • A commercial DIGEMAPS registration is a second, separate file from a clinical-trial authorization.

    We will not invent a Santiago-only day count. Ask for a protocol-specific calendar. A hospital email is not a DIGEMAPS authorization.

    What the Akura public file actually supports — and what it does not

    • Device: the ATC System for mechanical removal of emboli in acute pulmonary embolism, as described on NCT06152341.
    • Sponsor: Akura Medical (industry). No collaborator. No CRO named.
    • Sites: Instituto Dante Pazzanese and Instituto do Coracao, São Paulo (existing intercepts); Centro de Intervenciones Cardiovasculares, Santiago de los Caballeros (this page).
    • Design: prospective single-arm multicenter, phase N/A, estimated n=30, actual start 15 May 2024.
    • Status: SUSPENDED — enrollment paused pending device resupply, expected to resume after an approved protocol amendment; the registry states the pause is not related to subject safety or device performance.
    • Regulatory flags on the record: FDA-regulated device; unapproved device; U.S. export.
    • Not claimed here: that the NCT named bioaccess®; that Akura Medical is a bioaccess® client; that we have ATC outcomes; that a named investigator exists on this row when the registry prints none; that Santiago de los Caballeros is the same building as Santo Domingo or La Romana.

    What the CRO still does after you have a hospital name

    • Regulatory-fit, not tourism. The Dominican Republic is a lead first-in-human jurisdiction on the published platform. It is not automatically the right country for every indication. bioaccess® still runs clinical trials in Colombia and the rest of the platform.
    • Protocol, IB, ICF, insurance, and the DIGEMAPS / CONABIOS packet — in Spanish.
    • Importer of record and device accountability, including resupply across activated rows.
    • ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation.
    • Optionality when one Caribbean cath lab is not enough.

    The founder podcast, when a conversation needs a voice, is Global Trial Accelerators™. Background: ClinicalTrials.gov FIH sites vs the CRO.

    Frequently asked questions

    Can I contract Centro de Intervenciones Cardiovasculares directly?

    You can try. The facility can discuss investigator interest, local procedure costs, and REC calendars. It cannot become your DIGEMAPS applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager because Akura listed Santiago on a registry row. Contract the CRO; let the CRO activate the site.

    Did bioaccess® run the Akura ATC study?

    No public bioaccess® page says so. We will not invent that claim. This page intercepts the search; it does not claim the study.

    The study is SUSPENDED. Is that a safety problem?

    The registry says no. Its stated reason is a temporary enrollment pause pending device resupply to sites, with enrollment expected to resume after an approved protocol amendment, and it explicitly states the pause is not related to subject safety or device performance. We quote that; we do not reinterpret it. Resupply across three countries is, however, exactly the import-and-accountability workstream a site does not own.

    Who is the principal investigator in Santiago de los Caballeros?

    The registry does not name one on this location row, and neither will we.

    Is Colombia still an option?

    Yes. bioaccess® still runs trials in Colombia. A Dominican search is not an instruction to abandon INVIMA. See CRO in Colombia.

  • Centro de Retina Médica y Quirúrgica Zapopan: Named Alcon Feasibility IOL Site, Not the COFEPRIS File

    Figures cited from the live ClinicalTrials.gov record NCT05317728 (last update posted 1 September 2026; first posted 8 April 2022) and the published bioaccess® Mexico country page, verified 3 September 2026. General information, not legal or regulatory advice. Confirm current COFEPRIS, ethics-committee, and FDA rules with qualified advisers. We name only the facility and the trial those sources support. No principal investigator is named on this NCT location row; we will not invent one. Alcon is not claimed as a bioaccess® client. bioaccess® is not listed on this NCT.

    If you searched Centro de Retina Médica y Quirúrgica clinical trial, Zapopan Jalisco IOL study, Alcon fluid accommodating IOL Mexico, BAL-FAIOL site, or “go direct to the Zapopan site,” you followed a facility string ClinicalTrials.gov still publishes on 1 September 2026. Centro de Retina Medica y Quirurgica SC is a real named ophthalmology facility on that record. It is not the operator of the COFEPRIS file.

    bioaccess®’s position is simple and it is not adversarial: Centro de Retina Medica y Quirurgica SC is the site. The First-in-Human CRO still owns COFEPRIS, institutional ethics, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Zapopan is not the only fit. Sponsors who skip the CRO and email the clinic still have to rebuild that stack. An NCT location row does not become a CRO.

    This page is the intercept for the Zapopan query. It does not clone clinical trials in Mexico. That page stays the country operating system. The two Mexico City rows on this same NCT get their own slugs: Asociación Para Evitar la Ceguera en México and Salauno Salud. This slug is the Zapopan retina campus string (ZIP 45116, Jalisco) only. It is not any other Jalisco research centre already on this site. Do not merge them.

    Why the facility name wins the search — and why that is not a CRO

    NCT05317728 is an industry device feasibility listing. Brief title: Clinical Study of a Fluid Accommodating Intraocular Lens (IOL) Design. Official title: Randomized Controlled Study of Fluid Accommodating IOL Outcomes Versus Monofocal Control. Organization study ID: ILR286-E002. Lead sponsor: Alcon Research, class INDUSTRY, responsible party the sponsor. No collaborator is listed. No CRO is listed. The only overall official on the record is an unnamed “Clinical Trial Lead, Surgical” at Alcon Research, LLC. There is no central contact and no principal investigator is named on any location row — we will not invent one.

    Design on the 3 September 2026 snapshot: interventional; primary purpose DEVICE_FEASIBILITY; phase N/A; Cohort 1 randomized parallel-group with participant and outcomes-assessor masking, Cohort 2 single-group unmasked; actual enrollment 175; status ACTIVE_NOT_RECRUITING. Actual start 31 March 2023; estimated primary completion and completion November 2026. Study first posted 8 April 2022; last update posted 1 September 2026. Condition: cataract.

    Interventions, in the registry’s words: the BAL-FAIOL IOL, an investigational implantable medical device intended for long-term use over the lifetime of the cataract subject; a commercially available monofocal IOL control (other name AcrySof IQ monofocal IOL, SN60WF); and cataract surgery by phacoemulsification with a clear corneal incision. The oversight module records the study as an FDA-regulated device study of an unapproved device that is a U.S. export. That combination — unapproved investigational IOL, exported from the United States, run in Latin America under a feasibility purpose — is exactly the file a CRO carries.

    The six location rows currently published:

    Read the record as it is. Primary purpose is DEVICE_FEASIBILITY. The device is unapproved. Three of the six buildings are in Mexico, and until this batch none of the three had a dedicated public intercept. That is the site-direct leak: a sponsor searching a fluid-accommodating IOL, Alcon feasibility, or a Mexican ophthalmology campus lands on a named facility with no operator between them and the file.

    Zapopan is a site. The CRO is the operator.

    Centro de Retina Medica y Quirurgica SC can provide cataract surgical volume, biometry and refractive outcome measurement, and surgeons who implant IOLs every week. That is necessary. It is not sufficient for an unapproved, U.S.-exported investigational lens a sponsor expects to defend later.

    What a site can typically do when a sponsor “goes direct”:

    • Discuss surgeon interest and surgical feasibility for an investigational IOL — when that service is available and appropriate for your lens, which is not automatic.
    • Share institutional ethics-committee calendars and clinic research rules.
    • Quote surgery, visit, and local staffing costs for the cases they will physically run.

    What the site is not built to own for an investigational device:

    • COFEPRIS. Clinical investigations sit under the Ley General de Salud and its implementing regulations. The submission is in Spanish: protocol, investigator brochure, informed consent, ethics approval, proof of insurance. A conversation with a Monterrey dermatologist is not that dossier.
    • Institutional ethics. Ethics-committee review under NOM-012-SSA3-2012 sits in front of the COFEPRIS file, and the committee is tied to the host institution once the site is chosen.
    • Investigational import. Bringing an unapproved device into Mexico is a separate workstream from the trial authorization and from a later commercial registro sanitario. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a site-only premium here.
    • ISO 14155 monitoring, EDC, adverse-event reporting, and the TMF.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after the GCP and ethics documentation that rule defines. Eligibility is not clearance. See OUS FIH and FDA IDE.
    • Multi-country optionality. If one Mexican room is not enough, a single-clinic MSA will not stretch to Colombia, Panama, or Costa Rica.

    Going direct to Centro de Retina Medica y Quirurgica SC is how you confirm an operating list. It is not how you open an investigational file.

    Site versus CRO

    Workstream What the Zapopan retina centre (site) typically owns What the CRO still owns
    Procedure OR list, phacoemulsification, biometry, refractive follow-up, local staff Protocol fit, surgeon training, investigational IOL accountability
    Ethics Institutional committee calendar and local rules Packet, ICF, IB alignment, deficiency cycle (NOM-012-SSA3-2012)
    National authority Not the permit holder by being listed on an NCT COFEPRIS clinical-investigation file, in Spanish
    Import Receiving and storage if contracted Importer of record for an unapproved, U.S.-exported lens
    Quality Clinic quality and the case ISO 14155 monitoring, EDC, AE reporting, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One building on a six-site record Colombia (INVIMA) and the rest of the bioaccess® platform

    How COFEPRIS and ethics sit next to the clinic

    Use clinical trials in Mexico for the full pathway. Facts a sponsor searching this facility needs on one screen, already published there and not re-averaged here:

    • Ethics at 4–6 weeks under NOM-012-SSA3-2012; COFEPRIS review at 4–8 weeks after ethics clearance; 2.8-month median start-up (attributed on that hub to NIH ClinRegs).
    • Published per-patient range $18,000–$30,000; 10+ pre-qualified sites across Mexico City, Guadalajara, and Monterrey.
    • The ~30-working-day COFEPRIS figure is registro sanitario / vía abreviada — a commercial market-access clock, not this trial clock.
    • All COFEPRIS submissions are in Spanish, including protocol, investigator brochure, and informed consent.
    • Under 21 CFR 812.28, foreign clinical data is eligible for FDA submission and review when the investigation meets that rule’s GCP conditions. Eligibility is not a guarantee of clearance or approval.
    • bioaccess®’s published cost comparison versus a typical U.S. or EU program is an experience-based estimate from work since 2010, not a formal study.

    We will not invent a facility-only day count. Ask for a protocol-specific calendar. A clinic email is not a COFEPRIS authorization.

    What the Alcon public file actually supports — and what it does not

    • Device: BAL-FAIOL fluid-accommodating intraocular lens, investigational and implantable, versus an AcrySof IQ SN60WF monofocal control, as described on NCT05317728.
    • Sponsor: Alcon Research (industry). No collaborator. No CRO named.
    • Site: Centro de Retina Medica y Quirurgica SC — one of six published location rows.
    • Design: DEVICE_FEASIBILITY, phase N/A, actual n=175, ACTIVE_NOT_RECRUITING, actual start 31 March 2023, estimated completion November 2026.
    • Regulatory flags on the record: FDA-regulated device; unapproved device; U.S. export.
    • Not claimed here: that the NCT named bioaccess®; that Alcon is a bioaccess® client; that we have BAL-FAIOL outcomes; that a named investigator exists on this row when the registry prints none; that this facility is the same building as any sibling intercept.

    What the CRO still does after you have a clinic name

    • Regulatory-fit, not tourism. Mexico is a sourced device geography. It is not automatically the right country for every indication. bioaccess® still runs clinical trials in Colombia and the rest of the platform.
    • Protocol, IB, ICF, insurance, and the COFEPRIS / ethics packet — in Spanish.
    • Importer of record and device accountability across every activated row.
    • ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation.
    • Optionality across Costa Rica, the Dominican Republic, Panama, Colombia, and the rest of the platform when one campus is not enough.

    The founder podcast, when a conversation needs a voice, is Global Trial Accelerators™. Background on why registry rows keep outranking operators: ClinicalTrials.gov FIH sites vs the CRO and LATAM FIH hospitals vs the CRO.

    Frequently asked questions

    Can I contract Centro de Retina Medica y Quirurgica SC directly?

    You can try. The facility can discuss surgeon interest, local case costs, and ethics-committee calendars. It cannot become your COFEPRIS applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager because Alcon listed it on a registry row. Contract the CRO; let the CRO activate the site.

    Did bioaccess® run the Alcon fluid-accommodating IOL study?

    No public bioaccess® page says so. We will not invent that claim. This page intercepts the search; it does not claim the study.

    Who is the principal investigator at this site?

    The registry does not name one on this location row, and neither will we. The only official on the record is an unnamed “Clinical Trial Lead, Surgical” at Alcon Research, LLC. A page that invents a surgeon name to look authoritative is a page a sponsor should not trust.

    The study is ACTIVE_NOT_RECRUITING. Why does this page exist?

    Because the row is still published and still ranks. Sponsors planning the next feasibility IOL study search the campus strings on the last one. Enrollment status changes; the search behaviour does not.

    Is Colombia still an option?

    Yes. bioaccess® still runs trials in Colombia. A Mexican ophthalmology search is not an instruction to abandon INVIMA. See CRO in Colombia.

  • Salauno Salud Mexico City: Named Alcon Feasibility IOL Site, Not the COFEPRIS File

    Figures cited from the live ClinicalTrials.gov record NCT05317728 (last update posted 1 September 2026; first posted 8 April 2022) and the published bioaccess® Mexico country page, verified 3 September 2026. General information, not legal or regulatory advice. Confirm current COFEPRIS, ethics-committee, and FDA rules with qualified advisers. We name only the facility and the trial those sources support. No principal investigator is named on this NCT location row; we will not invent one. Alcon is not claimed as a bioaccess® client. bioaccess® is not listed on this NCT.

    If you searched Salauno clinical trial, Salauno Salud SAPI de CV Mexico City, Alcon fluid accommodating IOL Mexico, BAL-FAIOL site, or “go direct to the Mexico City site,” you followed a facility string ClinicalTrials.gov still publishes on 1 September 2026. Salauno Salud SAPI de CV is a real named ophthalmology facility on that record. It is not the operator of the COFEPRIS file.

    bioaccess®’s position is simple and it is not adversarial: Salauno Salud SAPI de CV is the site. The First-in-Human CRO still owns COFEPRIS, institutional ethics, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Mexico City is not the only fit. Sponsors who skip the CRO and email the clinic still have to rebuild that stack. An NCT location row does not become a CRO.

    This page is the intercept for the Mexico City query. It does not clone clinical trials in Mexico. That page stays the country operating system. The two other Mexican rows on this same NCT get their own slugs: Asociación Para Evitar la Ceguera en México and Centro de Retina Médica y Quirúrgica Zapopan. This slug is the Salauno legal-entity string only. Salauno is a separate organisation from APEC and from Conde de Valenciana. Do not merge them.

    Why the facility name wins the search — and why that is not a CRO

    NCT05317728 is an industry device feasibility listing. Brief title: Clinical Study of a Fluid Accommodating Intraocular Lens (IOL) Design. Official title: Randomized Controlled Study of Fluid Accommodating IOL Outcomes Versus Monofocal Control. Organization study ID: ILR286-E002. Lead sponsor: Alcon Research, class INDUSTRY, responsible party the sponsor. No collaborator is listed. No CRO is listed. The only overall official on the record is an unnamed “Clinical Trial Lead, Surgical” at Alcon Research, LLC. There is no central contact and no principal investigator is named on any location row — we will not invent one.

    Design on the 3 September 2026 snapshot: interventional; primary purpose DEVICE_FEASIBILITY; phase N/A; Cohort 1 randomized parallel-group with participant and outcomes-assessor masking, Cohort 2 single-group unmasked; actual enrollment 175; status ACTIVE_NOT_RECRUITING. Actual start 31 March 2023; estimated primary completion and completion November 2026. Study first posted 8 April 2022; last update posted 1 September 2026. Condition: cataract.

    Interventions, in the registry’s words: the BAL-FAIOL IOL, an investigational implantable medical device intended for long-term use over the lifetime of the cataract subject; a commercially available monofocal IOL control (other name AcrySof IQ monofocal IOL, SN60WF); and cataract surgery by phacoemulsification with a clear corneal incision. The oversight module records the study as an FDA-regulated device study of an unapproved device that is a U.S. export. That combination — unapproved investigational IOL, exported from the United States, run in Latin America under a feasibility purpose — is exactly the file a CRO carries.

    The six location rows currently published:

    Read the record as it is. Primary purpose is DEVICE_FEASIBILITY. The device is unapproved. Three of the six buildings are in Mexico, and until this batch none of the three had a dedicated public intercept. That is the site-direct leak: a sponsor searching a fluid-accommodating IOL, Alcon feasibility, or a Mexican ophthalmology campus lands on a named facility with no operator between them and the file.

    Mexico City is a site. The CRO is the operator.

    Salauno Salud SAPI de CV can provide cataract surgical volume, biometry and refractive outcome measurement, and surgeons who implant IOLs every week. That is necessary. It is not sufficient for an unapproved, U.S.-exported investigational lens a sponsor expects to defend later.

    What a site can typically do when a sponsor “goes direct”:

    • Discuss surgeon interest and surgical feasibility for an investigational IOL — when that service is available and appropriate for your lens, which is not automatic.
    • Share institutional ethics-committee calendars and clinic research rules.
    • Quote surgery, visit, and local staffing costs for the cases they will physically run.

    What the site is not built to own for an investigational device:

    • COFEPRIS. Clinical investigations sit under the Ley General de Salud and its implementing regulations. The submission is in Spanish: protocol, investigator brochure, informed consent, ethics approval, proof of insurance. A conversation with a Monterrey dermatologist is not that dossier.
    • Institutional ethics. Ethics-committee review under NOM-012-SSA3-2012 sits in front of the COFEPRIS file, and the committee is tied to the host institution once the site is chosen.
    • Investigational import. Bringing an unapproved device into Mexico is a separate workstream from the trial authorization and from a later commercial registro sanitario. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a site-only premium here.
    • ISO 14155 monitoring, EDC, adverse-event reporting, and the TMF.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after the GCP and ethics documentation that rule defines. Eligibility is not clearance. See OUS FIH and FDA IDE.
    • Multi-country optionality. If one Mexican room is not enough, a single-clinic MSA will not stretch to Colombia, Panama, or Costa Rica.

    Going direct to Salauno Salud SAPI de CV is how you confirm an operating list. It is not how you open an investigational file.

    Site versus CRO

    Workstream What Salauno (site) typically owns What the CRO still owns
    Procedure OR list, phacoemulsification, biometry, refractive follow-up, local staff Protocol fit, surgeon training, investigational IOL accountability
    Ethics Institutional committee calendar and local rules Packet, ICF, IB alignment, deficiency cycle (NOM-012-SSA3-2012)
    National authority Not the permit holder by being listed on an NCT COFEPRIS clinical-investigation file, in Spanish
    Import Receiving and storage if contracted Importer of record for an unapproved, U.S.-exported lens
    Quality Clinic quality and the case ISO 14155 monitoring, EDC, AE reporting, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One building on a six-site record Colombia (INVIMA) and the rest of the bioaccess® platform

    How COFEPRIS and ethics sit next to the clinic

    Use clinical trials in Mexico for the full pathway. Facts a sponsor searching this facility needs on one screen, already published there and not re-averaged here:

    • Ethics at 4–6 weeks under NOM-012-SSA3-2012; COFEPRIS review at 4–8 weeks after ethics clearance; 2.8-month median start-up (attributed on that hub to NIH ClinRegs).
    • Published per-patient range $18,000–$30,000; 10+ pre-qualified sites across Mexico City, Guadalajara, and Monterrey.
    • The ~30-working-day COFEPRIS figure is registro sanitario / vía abreviada — a commercial market-access clock, not this trial clock.
    • All COFEPRIS submissions are in Spanish, including protocol, investigator brochure, and informed consent.
    • Under 21 CFR 812.28, foreign clinical data is eligible for FDA submission and review when the investigation meets that rule’s GCP conditions. Eligibility is not a guarantee of clearance or approval.
    • bioaccess®’s published cost comparison versus a typical U.S. or EU program is an experience-based estimate from work since 2010, not a formal study.

    We will not invent a facility-only day count. Ask for a protocol-specific calendar. A clinic email is not a COFEPRIS authorization.

    What the Alcon public file actually supports — and what it does not

    • Device: BAL-FAIOL fluid-accommodating intraocular lens, investigational and implantable, versus an AcrySof IQ SN60WF monofocal control, as described on NCT05317728.
    • Sponsor: Alcon Research (industry). No collaborator. No CRO named.
    • Site: Salauno Salud SAPI de CV — one of six published location rows.
    • Design: DEVICE_FEASIBILITY, phase N/A, actual n=175, ACTIVE_NOT_RECRUITING, actual start 31 March 2023, estimated completion November 2026.
    • Regulatory flags on the record: FDA-regulated device; unapproved device; U.S. export.
    • Not claimed here: that the NCT named bioaccess®; that Alcon is a bioaccess® client; that we have BAL-FAIOL outcomes; that a named investigator exists on this row when the registry prints none; that this facility is the same building as any sibling intercept.

    What the CRO still does after you have a clinic name

    • Regulatory-fit, not tourism. Mexico is a sourced device geography. It is not automatically the right country for every indication. bioaccess® still runs clinical trials in Colombia and the rest of the platform.
    • Protocol, IB, ICF, insurance, and the COFEPRIS / ethics packet — in Spanish.
    • Importer of record and device accountability across every activated row.
    • ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation.
    • Optionality across Costa Rica, the Dominican Republic, Panama, Colombia, and the rest of the platform when one campus is not enough.

    The founder podcast, when a conversation needs a voice, is Global Trial Accelerators™. Background on why registry rows keep outranking operators: ClinicalTrials.gov FIH sites vs the CRO and LATAM FIH hospitals vs the CRO.

    Frequently asked questions

    Can I contract Salauno Salud SAPI de CV directly?

    You can try. The facility can discuss surgeon interest, local case costs, and ethics-committee calendars. It cannot become your COFEPRIS applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager because Alcon listed it on a registry row. Contract the CRO; let the CRO activate the site.

    Did bioaccess® run the Alcon fluid-accommodating IOL study?

    No public bioaccess® page says so. We will not invent that claim. This page intercepts the search; it does not claim the study.

    Who is the principal investigator at this site?

    The registry does not name one on this location row, and neither will we. The only official on the record is an unnamed “Clinical Trial Lead, Surgical” at Alcon Research, LLC. A page that invents a surgeon name to look authoritative is a page a sponsor should not trust.

    The study is ACTIVE_NOT_RECRUITING. Why does this page exist?

    Because the row is still published and still ranks. Sponsors planning the next feasibility IOL study search the campus strings on the last one. Enrollment status changes; the search behaviour does not.

    Is Colombia still an option?

    Yes. bioaccess® still runs trials in Colombia. A Mexican ophthalmology search is not an instruction to abandon INVIMA. See CRO in Colombia.

  • Asociación Para Evitar la Ceguera en México: Named Alcon Feasibility IOL Site, Not the COFEPRIS File

    Figures cited from the live ClinicalTrials.gov record NCT05317728 (last update posted 1 September 2026; first posted 8 April 2022) and the published bioaccess® Mexico country page, verified 3 September 2026. General information, not legal or regulatory advice. Confirm current COFEPRIS, ethics-committee, and FDA rules with qualified advisers. We name only the facility and the trial those sources support. No principal investigator is named on this NCT location row; we will not invent one. Alcon is not claimed as a bioaccess® client. bioaccess® is not listed on this NCT.

    If you searched Asociación Para Evitar la Ceguera en México clinical trial, APEC Mexico City IOL study, Alcon fluid accommodating IOL Mexico, BAL-FAIOL site, or “go direct to the Mexico City site,” you followed a facility string ClinicalTrials.gov still publishes on 1 September 2026. Asociación Para Evitar la Ceguera en México is a real named ophthalmology facility on that record. It is not the operator of the COFEPRIS file.

    bioaccess®’s position is simple and it is not adversarial: Asociación Para Evitar la Ceguera en México is the site. The First-in-Human CRO still owns COFEPRIS, institutional ethics, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Mexico City is not the only fit. Sponsors who skip the CRO and email the clinic still have to rebuild that stack. An NCT location row does not become a CRO.

    This page is the intercept for the Mexico City query. It does not clone clinical trials in Mexico. That page stays the country operating system. Sibling Mexico City intercepts stay on their own buildings: Instituto de Oftalmología Conde de Valenciana. The two other Mexican rows on this same NCT get their own slugs: Salauno Salud and Centro de Retina Médica y Quirúrgica Zapopan. This slug is the APEC campus string only. It is not CODET Vision Institute Tijuana and it is not Conde de Valenciana. Do not merge them.

    Why the facility name wins the search — and why that is not a CRO

    NCT05317728 is an industry device feasibility listing. Brief title: Clinical Study of a Fluid Accommodating Intraocular Lens (IOL) Design. Official title: Randomized Controlled Study of Fluid Accommodating IOL Outcomes Versus Monofocal Control. Organization study ID: ILR286-E002. Lead sponsor: Alcon Research, class INDUSTRY, responsible party the sponsor. No collaborator is listed. No CRO is listed. The only overall official on the record is an unnamed “Clinical Trial Lead, Surgical” at Alcon Research, LLC. There is no central contact and no principal investigator is named on any location row — we will not invent one.

    Design on the 3 September 2026 snapshot: interventional; primary purpose DEVICE_FEASIBILITY; phase N/A; Cohort 1 randomized parallel-group with participant and outcomes-assessor masking, Cohort 2 single-group unmasked; actual enrollment 175; status ACTIVE_NOT_RECRUITING. Actual start 31 March 2023; estimated primary completion and completion November 2026. Study first posted 8 April 2022; last update posted 1 September 2026. Condition: cataract.

    Interventions, in the registry’s words: the BAL-FAIOL IOL, an investigational implantable medical device intended for long-term use over the lifetime of the cataract subject; a commercially available monofocal IOL control (other name AcrySof IQ monofocal IOL, SN60WF); and cataract surgery by phacoemulsification with a clear corneal incision. The oversight module records the study as an FDA-regulated device study of an unapproved device that is a U.S. export. That combination — unapproved investigational IOL, exported from the United States, run in Latin America under a feasibility purpose — is exactly the file a CRO carries.

    The six location rows currently published:

    Read the record as it is. Primary purpose is DEVICE_FEASIBILITY. The device is unapproved. Three of the six buildings are in Mexico, and until this batch none of the three had a dedicated public intercept. That is the site-direct leak: a sponsor searching a fluid-accommodating IOL, Alcon feasibility, or a Mexican ophthalmology campus lands on a named facility with no operator between them and the file.

    Mexico City is a site. The CRO is the operator.

    Asociación Para Evitar la Ceguera en México can provide cataract surgical volume, biometry and refractive outcome measurement, and surgeons who implant IOLs every week. That is necessary. It is not sufficient for an unapproved, U.S.-exported investigational lens a sponsor expects to defend later.

    What a site can typically do when a sponsor “goes direct”:

    • Discuss surgeon interest and surgical feasibility for an investigational IOL — when that service is available and appropriate for your lens, which is not automatic.
    • Share institutional ethics-committee calendars and clinic research rules.
    • Quote surgery, visit, and local staffing costs for the cases they will physically run.

    What the site is not built to own for an investigational device:

    • COFEPRIS. Clinical investigations sit under the Ley General de Salud and its implementing regulations. The submission is in Spanish: protocol, investigator brochure, informed consent, ethics approval, proof of insurance. A conversation with a Monterrey dermatologist is not that dossier.
    • Institutional ethics. Ethics-committee review under NOM-012-SSA3-2012 sits in front of the COFEPRIS file, and the committee is tied to the host institution once the site is chosen.
    • Investigational import. Bringing an unapproved device into Mexico is a separate workstream from the trial authorization and from a later commercial registro sanitario. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a site-only premium here.
    • ISO 14155 monitoring, EDC, adverse-event reporting, and the TMF.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after the GCP and ethics documentation that rule defines. Eligibility is not clearance. See OUS FIH and FDA IDE.
    • Multi-country optionality. If one Mexican room is not enough, a single-clinic MSA will not stretch to Colombia, Panama, or Costa Rica.

    Going direct to Asociación Para Evitar la Ceguera en México is how you confirm an operating list. It is not how you open an investigational file.

    Site versus CRO

    Workstream What the APEC campus (site) typically owns What the CRO still owns
    Procedure OR list, phacoemulsification, biometry, refractive follow-up, local staff Protocol fit, surgeon training, investigational IOL accountability
    Ethics Institutional committee calendar and local rules Packet, ICF, IB alignment, deficiency cycle (NOM-012-SSA3-2012)
    National authority Not the permit holder by being listed on an NCT COFEPRIS clinical-investigation file, in Spanish
    Import Receiving and storage if contracted Importer of record for an unapproved, U.S.-exported lens
    Quality Clinic quality and the case ISO 14155 monitoring, EDC, AE reporting, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One building on a six-site record Colombia (INVIMA) and the rest of the bioaccess® platform

    How COFEPRIS and ethics sit next to the clinic

    Use clinical trials in Mexico for the full pathway. Facts a sponsor searching this facility needs on one screen, already published there and not re-averaged here:

    • Ethics at 4–6 weeks under NOM-012-SSA3-2012; COFEPRIS review at 4–8 weeks after ethics clearance; 2.8-month median start-up (attributed on that hub to NIH ClinRegs).
    • Published per-patient range $18,000–$30,000; 10+ pre-qualified sites across Mexico City, Guadalajara, and Monterrey.
    • The ~30-working-day COFEPRIS figure is registro sanitario / vía abreviada — a commercial market-access clock, not this trial clock.
    • All COFEPRIS submissions are in Spanish, including protocol, investigator brochure, and informed consent.
    • Under 21 CFR 812.28, foreign clinical data is eligible for FDA submission and review when the investigation meets that rule’s GCP conditions. Eligibility is not a guarantee of clearance or approval.
    • bioaccess®’s published cost comparison versus a typical U.S. or EU program is an experience-based estimate from work since 2010, not a formal study.

    We will not invent a facility-only day count. Ask for a protocol-specific calendar. A clinic email is not a COFEPRIS authorization.

    What the Alcon public file actually supports — and what it does not

    • Device: BAL-FAIOL fluid-accommodating intraocular lens, investigational and implantable, versus an AcrySof IQ SN60WF monofocal control, as described on NCT05317728.
    • Sponsor: Alcon Research (industry). No collaborator. No CRO named.
    • Site: Asociación Para Evitar la Ceguera en México — one of six published location rows.
    • Design: DEVICE_FEASIBILITY, phase N/A, actual n=175, ACTIVE_NOT_RECRUITING, actual start 31 March 2023, estimated completion November 2026.
    • Regulatory flags on the record: FDA-regulated device; unapproved device; U.S. export.
    • Not claimed here: that the NCT named bioaccess®; that Alcon is a bioaccess® client; that we have BAL-FAIOL outcomes; that a named investigator exists on this row when the registry prints none; that this facility is the same building as any sibling intercept.

    What the CRO still does after you have a clinic name

    • Regulatory-fit, not tourism. Mexico is a sourced device geography. It is not automatically the right country for every indication. bioaccess® still runs clinical trials in Colombia and the rest of the platform.
    • Protocol, IB, ICF, insurance, and the COFEPRIS / ethics packet — in Spanish.
    • Importer of record and device accountability across every activated row.
    • ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation.
    • Optionality across Costa Rica, the Dominican Republic, Panama, Colombia, and the rest of the platform when one campus is not enough.

    The founder podcast, when a conversation needs a voice, is Global Trial Accelerators™. Background on why registry rows keep outranking operators: ClinicalTrials.gov FIH sites vs the CRO and LATAM FIH hospitals vs the CRO.

    Frequently asked questions

    Can I contract Asociación Para Evitar la Ceguera en México directly?

    You can try. The facility can discuss surgeon interest, local case costs, and ethics-committee calendars. It cannot become your COFEPRIS applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager because Alcon listed it on a registry row. Contract the CRO; let the CRO activate the site.

    Did bioaccess® run the Alcon fluid-accommodating IOL study?

    No public bioaccess® page says so. We will not invent that claim. This page intercepts the search; it does not claim the study.

    Who is the principal investigator at this site?

    The registry does not name one on this location row, and neither will we. The only official on the record is an unnamed “Clinical Trial Lead, Surgical” at Alcon Research, LLC. A page that invents a surgeon name to look authoritative is a page a sponsor should not trust.

    The study is ACTIVE_NOT_RECRUITING. Why does this page exist?

    Because the row is still published and still ranks. Sponsors planning the next feasibility IOL study search the campus strings on the last one. Enrollment status changes; the search behaviour does not.

    Is Colombia still an option?

    Yes. bioaccess® still runs trials in Colombia. A Mexican ophthalmology search is not an instruction to abandon INVIMA. See CRO in Colombia.

  • Especialistas de la Piel y Cirugía Monterrey: Named Jeisys Linear Z Site, Not the COFEPRIS File

    Figures cited from the live ClinicalTrials.gov record NCT07802431 (study first posted 3 September 2026; last update posted 3 September 2026) and the published bioaccess® Mexico country page, verified 3 September 2026. General information, not legal or regulatory advice. Confirm current COFEPRIS, ethics-committee, and FDA rules with qualified advisers. We name only the facility, the investigator, and the trial those sources support. We do not publish site contact emails or phone numbers here. Jeisys Medical is not claimed as a bioaccess® client. bioaccess® is not listed on this NCT.

    If you searched Especialistas de la Piel y Cirugía clinical trial, Jeisys Linear Z Mexico, LinearZ HIFU body contouring study, Hector Leal Leal Monterrey, or “go direct to the Monterrey site,” you followed a facility string ClinicalTrials.gov published for the first time on 3 September 2026. Especialistas de la Piel y Cirugía, S.C. in Monterrey, Nuevo León is a real named facility on that record. It is not the operator of the COFEPRIS file.

    bioaccess®’s position is simple and it is not adversarial: Especialistas de la Piel y Cirugía is the site. The First-in-Human CRO still owns COFEPRIS, institutional ethics, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Monterrey is not the only fit. Sponsors who skip the CRO and email the clinic still have to rebuild that stack. A recruiting location row does not become a CRO.

    This page is the intercept for the Monterrey query. It does not clone clinical trials in Mexico. That page stays the country operating system. Sibling Mexican intercepts stay on their own buildings: Centro de Dermatología de Monterrey, CODET Vision Institute Tijuana, and Instituto de Oftalmología Conde de Valenciana. Do not merge them into this slug.

    Why the clinic name wins the search — and why that is not a CRO

    NCT07802431 is a brand-new industry device listing. The registry’s own dates, retrieved 3 September 2026: study first submitted 27 August 2026; QC submitted 1 September 2026; first posted 3 September 2026; last update posted 3 September 2026. Brief title: Clinical Evaluation of Linear Z for Body Contouring. Official title: Prospective, Single-center, Single-arm Clinical Research Evaluating the Safety and Effectiveness of Linear Z for Non-invasive Body Contouring of the Abdomen and Flanks. Organization study ID: LIN-BD-01-2026. Lead sponsor: Jeisys Medical Inc, class INDUSTRY, responsible party the sponsor. No collaborator is listed. No CRO is listed.

    Design on the 3 September 2026 snapshot: interventional; single-center, single-arm; allocation N/A; no masking; primary purpose treatment; phase N/A; estimated enrollment 30; status RECRUITING. Estimated start 1 September 2026; estimated primary completion 20 December 2026; estimated completion 31 December 2026. Condition: non-invasive body contouring. Registry keywords: body contouring; high-intensity focused ultrasound (HIFU); localized adiposity; fat reduction.

    Intervention, in the registry’s words: a device — high intensity focused ultrasound. Participants receive a single treatment with the LinearZ focused ultrasound device to the lower abdomen and bilateral flanks, delivered at specific depths within subcutaneous tissue per the sponsor-approved treatment manual, with roughly 90 days of follow-up. The registry’s oversight module records no data monitoring committee, and marks the study as not FDA-regulated drug and not FDA-regulated device — a sponsor-entered flag about this listing, not a statement about what a later U.S. filing would require.

    Location rows currently published:

    • Especialistas de la Piel y Cirugía, S.C. — the only location on the record — RECRUITING. The registry prints the geography as city “Nuevo León,” state “Monterrey,” ZIP 64060, Mexico. We report that as published; the two fields appear transposed on the row and we will not silently rewrite a sponsor’s entry.
    • Named site contact on that row: Hector Leal Leal, Dr. Central contact on the record: Narendra Kumar, Dr., PhD, Jeisys. We do not reprint their direct contact details here.

    Read the record as it is. A single Mexican site, an estimated 30 participants, a 90-day endpoint window, an industry sponsor in Korea, and no CRO in the public copy. That is the site-direct leak: a sponsor searching LinearZ, Jeisys, or Monterrey body contouring now lands on a named clinic with no operator between them and the file.

    Monterrey is a site. The CRO is the operator.

    A Monterrey dermatology and surgery practice can provide treatment rooms, standardized photography and 3D imaging, subjects with localized abdominal and flank adiposity, and an investigator the registry already named. That is necessary. It is not sufficient for an investigational-device study a U.S. board expects to survive later scrutiny.

    What a site can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and procedural feasibility for an energy-device protocol — when that service is available and appropriate for your device, which is not automatic.
    • Share institutional ethics-committee calendars and clinic research rules.
    • Quote procedure, visit, and local staffing costs for the sessions they will physically run.

    What the site is not built to own for an investigational device:

    • COFEPRIS. Clinical investigations sit under the Ley General de Salud and its implementing regulations. The submission is in Spanish: protocol, investigator brochure, informed consent, ethics approval, proof of insurance. A conversation with a Monterrey dermatologist is not that dossier.
    • Institutional ethics. Ethics-committee review under NOM-012-SSA3-2012 sits in front of the COFEPRIS file, and the committee is tied to the host institution once the site is chosen.
    • Investigational import. Bringing an unapproved device into Mexico is a separate workstream from the trial authorization and from a later commercial registro sanitario. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a site-only premium here.
    • ISO 14155 monitoring, EDC, adverse-event reporting, and the TMF.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after the GCP and ethics documentation that rule defines. Eligibility is not clearance. See OUS FIH and FDA IDE.
    • Multi-country optionality. If one Mexican room is not enough, a single-clinic MSA will not stretch to Colombia, Panama, or Costa Rica.

    Going direct to Especialistas de la Piel y Cirugía is how you confirm a room. It is not how you open an investigational file.

    Site versus CRO

    Workstream What the Monterrey clinic (site) typically owns What the CRO still owns
    Procedure Treatment room, HIFU sessions, photography and 3D imaging, local staff Protocol fit, training, device accountability
    Ethics Institutional committee calendar and local rules Packet, ICF, IB alignment, deficiency cycle (NOM-012-SSA3-2012)
    National authority Not the permit holder by being listed on an NCT COFEPRIS clinical-investigation file, in Spanish
    Import Receiving and storage if contracted Importer of record for the investigational system
    Quality Clinic quality and the treatment session ISO 14155 monitoring, EDC, AE reporting, TMF
    FDA conversation Source documents from sessions they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One Monterrey practice Colombia (INVIMA) and the rest of the bioaccess® platform

    How COFEPRIS and ethics sit next to the clinic

    Use clinical trials in Mexico for the full pathway. Facts a sponsor searching this facility needs on one screen, already published there and not re-averaged here:

    • Ethics at 4–6 weeks under NOM-012-SSA3-2012; COFEPRIS review at 4–8 weeks after ethics clearance; 2.8-month median start-up (attributed on that hub to NIH ClinRegs).
    • Published per-patient range $18,000–$30,000; 10+ pre-qualified sites across Mexico City, Guadalajara, and Monterrey.
    • The ~30-working-day COFEPRIS figure is registro sanitario / vía abreviada — a commercial market-access clock, not this trial clock.
    • All COFEPRIS submissions are in Spanish, including protocol, investigator brochure, and informed consent.
    • Under 21 CFR 812.28, foreign clinical data is eligible for FDA submission and review when the investigation meets that rule’s GCP conditions. Eligibility is not a guarantee of clearance or approval.
    • bioaccess®’s published cost comparison versus a typical U.S. or EU program is an experience-based estimate from work since 2010, not a formal study.

    We will not invent a facility-only day count. Ask for a protocol-specific calendar. A clinic email is not a COFEPRIS authorization.

    What the Jeisys public file actually supports — and what it does not

    • Device: LinearZ high-intensity focused ultrasound for non-invasive body contouring of the lower abdomen and flanks, as described on NCT07802431.
    • Sponsor: Jeisys Medical Inc (industry). No collaborator. No CRO named.
    • Site: Especialistas de la Piel y Cirugía, S.C., Monterrey / Nuevo León, Mexico — the only location row, RECRUITING.
    • Design: single-center, single-arm, phase N/A; estimated n=30; estimated start 1 September 2026; ~90-day follow-up.
    • Named investigator (as published): Hector Leal Leal, Dr., site contact on the location row.
    • Not claimed here: that the NCT named bioaccess®; that Jeisys is a bioaccess® client; that we have LinearZ outcomes; that this listing is an FDA IDE; that the clinic holds a COFEPRIS authorization because it is printed on a registry row.

    What the CRO still does after you have a clinic name

    • Regulatory-fit, not tourism. Mexico is a sourced device geography. It is not automatically the right country for every indication. bioaccess® still runs clinical trials in Colombia and the rest of the platform.
    • Protocol, IB, ICF, insurance, and the COFEPRIS / ethics packet — in Spanish.
    • Importer of record and device accountability for the investigational system.
    • ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation.
    • Optionality if one Nuevo León room is not enough.

    The founder podcast, when a conversation needs a voice, is Global Trial Accelerators™. Background on why registry rows keep outranking operators: ClinicalTrials.gov FIH sites vs the CRO.

    Frequently asked questions

    Can I contract Especialistas de la Piel y Cirugía directly?

    You can try. The facility can discuss investigator interest, local session costs, and ethics-committee calendars. It cannot become your COFEPRIS applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager because Jeisys listed Monterrey. Contract the CRO; let the CRO activate the site.

    Did bioaccess® run the Linear Z study?

    No public bioaccess® page says so. We will not invent that claim. This page intercepts the search; it does not claim the study.

    The registry says this is not an FDA-regulated device study. Does 21 CFR 812.28 still matter?

    It matters the moment you want the data to travel. That sponsor-entered flag describes this listing. If a U.S. submission is ever the goal, the GCP, ethics, and documentation conditions in 21 CFR 812.28 are what make foreign data eligible for FDA submission and review — and eligibility is still not clearance.

    Why does the record print Nuevo León as the city and Monterrey as the state?

    Because that is what the sponsor entered. Monterrey is the city and Nuevo León is the state. We report the row as published and flag the transposition rather than quietly rewriting a public record.

    Is Colombia still an option?

    Yes. bioaccess® still runs trials in Colombia. A Monterrey search is not an instruction to abandon INVIMA. See CRO in Colombia.

  • Hospital Nacional Hipólito Unanue: The NCT Campus String Is Not the INS File

    Figures cited from a ClinicalTrials.gov LATAM facility sweep (API pull 1 September 2026, 6:32 PM ET) and published bioaccess® country pages. Registry ranking is not a bioaccess® claim that we ran any of these studies. General information, not legal or regulatory advice. Confirm current INS, ethics, and FDA rules with qualified advisers. We name only the facility strings and example NCT IDs those sources support. We do not invent a principal investigator. We do not claim Hospital Nacional Hipólito Unanue as a bioaccess® client.

    If you searched Hospital Nacional Hipolito Unanue first-in-human, Hipolito Unanue Lima clinical trial, Unanue CRO, or “go direct Hospital Nacional Hipólito Unanue,” you followed a campus string ClinicalTrials.gov still publishes. Hospital Nacional Hipólito Unanue in Lima, Peru, is a real named national-hospital string on ClinicalTrials.gov. It is not a first-in-human medical-device CRO, and it is not the operator of the INS file.

    bioaccess®’s position is simple and it is not adversarial: the hospital is the site. The First-in-Human CRO still owns INS / DIGEMID, accredited ethics, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if this campus is not the only fit. Sponsors who skip the CRO and email the hospital still have to rebuild that stack. An NCT location row is not a CRO.

    This page is the named Lima Hipólito Unanue campus. Skip INEN Lima (CMS 95644) on this slug. It is not Clínica Vesalio Lima (CMS 96116), not Clínica San Borja Lima (already live), and not a DIGESA invention. Sharing Lima is not a license to collapse them. Unanue is not INEN. Unanue is not Vesalio.

    Why the campus name wins the search — and why that is not a CRO

    Device registries write the city, the hospital, and a list of NCT IDs. They rarely write the CRO. On the 1 September 2026 ClinicalTrials.gov LATAM sweep (interventional studies; all years; complete dump), this campus sits here after filters:

    Counts come from leftover unique strings after the last live leftover-site batch plus unique NCT IDs in /workspace/five-trials/ctgov-raw/all_interventional.jsonl (17497 studies; ClinicalTrials.gov LATAM facility sweep, API pull 1 September 2026, 6:32 PM ET; dump confirmed 1 September 2026). Alias strings are listed separately. We do not publish a unique-study union across alias strings. We do not invent a global CSV rank. We do not invent unpublished CMS IDs. Registry ranking is not a bioaccess® claim that we ran any of these studies.

    • Hospital Nacional Hipólito Unanue (Lima, Peru) — canonical NCT string: ALL interventional n=8; DEVICE n=1. Example NCT IDs: NCT00685360, NCT00868959, NCT01284517.

    Cite canonical ALL n=8 and DEVICE n=1. Do not clone INEN or Vesalio onto this slug. We do not invent a Peruvian legal entity.

    Those are unique NCT IDs per facility string + city + country. They are not a count of first-in-human device programs bioaccess® ran. They are how a sponsor searching the hospital name lands on a campus without landing on an operator.

    We cite the IDs as facility evidence. We will not invent a PI. We will not claim bioaccess® ran any of them. No live bioaccess® case-study page names this hospital as a client site.

    That is the leak: a founder searching Hipólito Unanue first-in-human finds ALL n=8 (DEVICE n=1) without finding INS / DIGEMID. A named national hospital is still a site. An NCT location row is not a CRO.

    The site is the site. The CRO is the operator.

    A named hospital can provide rooms, coordinators, institutional ethics calendars, and investigators who already appear on NCT rows. That is necessary. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What the hospital can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing service line.
    • Share institutional ethics-committee calendars and hospital research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the hospital is not built to own for an investigational device:

    • INS. INS (DIIS, formerly OGITT) authorizes trials in Peru. DIGEMID under MINSA regulates devices and investigational import. Accredited ethics is required. A hallway conversation in Lima is not that stack. We will not invent DIGESA onto this page. We do not invent a Peruvian legal entity. A hallway conversation at Hipólito Unanue is not an INEN file and is not a Vesalio file.
    • Investigational import. Ethics letter, investigator’s brochure, and an importation permit — end-to-end work, not a PI email. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a campus-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF. The site may run visits. The CRO runs the quality system the FDA will later ask about.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after GCP / ethics documentation. Eligibility is not clearance, and a site MSA does not produce it.
    • Multi-country optionality. If enrollment or the indication later needs another Latin American country, a single-hospital MSA will not stretch.

    Going direct to this campus is how you confirm a room. It is not how you open an investigational file.

    How INS actually works (the short version)

    Use clinical-trials-peru. INS (DIIS, formerly OGITT) authorizes trials. A published statutory target on that hub is 40 business days in the drug-trial framework, and 60 business days when a biologics / technical commission applies. A novel first-in-human device may take longer. We will not invent a new Peruvian clock on this page. DIGEMID under MINSA regulates devices and investigational import. Accredited ethics is required. The Peru hub already cites experience-based cost on the order of ~30% lower versus US/EU — that is a country-page figure, not a campus quote we invent here. We do not invent a Peruvian legal entity on this page.

    Ask for a protocol-specific calendar. A hospital email is not INS clearance. bioaccess® manages the file. That is CRO work, not site work.

    All bioaccess® device protocols in this country are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval. See OUS FIH and FDA IDE.

    Do not smear the hospital

    Hospital Nacional Hipólito Unanue is a serious named Lima campus on the public registry. ALL n=8 and DEVICE n=1 are registry volume, not a punchline. Do not invent a PI. Do not invent DIGESA. Do not invent a Peruvian legal entity. Use the site when the protocol fits. Hire the operator.

    What the CRO still does after you have the campus on a slide

    1. Regulatory-fit, not tourism. This geography is sourced. One campus is not automatically the right room for every indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the INS / ethics packet.
    3. Importer of record and device accountability.
    4. Site activation that is more than a tour: contracts, training, investigational product, EDC, monitoring plan. Activate this campus only if it fits the protocol.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative so the dataset is built for a later Pre-Sub, IDE, 510(k), De Novo, PMA, or HDE — eligibility, not a promise of FDA action.

    The firm was founded in 2010. That is the operator layer around a campus string.

    Colombia is still on the map

    Public line, unchanged: bioaccess® still runs clinical trials in Colombia — local entity, Miami headquarters, own CRO in Colombia. Because INVIMA clinical-trial approval timelines have become unpredictable, bioaccess® does not currently recommend Colombia for new FIH trial execution. INVIMA commercial registration remains. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K as published on clinical-trials-panama. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract Hospital Nacional Hipólito Unanue directly for a device FIH?

    You can try. The hospital can discuss investigator interest, local visit costs, and ethics calendars. It cannot, by ranking on ClinicalTrials.gov, become your INS applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Did bioaccess® run the NCT IDs listed here?

    No public bioaccess® case-study page names this hospital. We will not invent that claim. This page intercepts the search; it does not claim the studies.

    Is this the same page as INEN Lima or Clínica Vesalio?

    No. INEN Lima is CMS 95644 and stays skipped on this slug. Clínica Vesalio Lima is CMS 96116. This page is Hospital Nacional Hipólito Unanue only.

    Did bioaccess® run NCT00685360?

    No. We cite it as facility evidence. We will not invent a sponsor or a PI.

    Next step

    If the search that brought you here was this campus, start as the operator: contact bioaccess® or book from First-in-Human CRO. Lima sibling (do not merge): Clínica Vesalio Lima.

    Julio G. Martinez-Clark, CEO · bioaccess®