Category: Navigating Regulatory Landscapes in Latin America

Explores the regulatory requirements and best practices for conducting clinical trials in Latin America, focusing on medical devices and biopharmaceuticals.

  • Universidade Nove de Julho: The NCT Campus String Is Not the ANVISA File

    Figures cited from a ClinicalTrials.gov LATAM facility sweep (API pull 1 September 2026, 6:32 PM ET) and the published bioaccess® Brazil country page. Registry ranking is not a bioaccess® claim that we ran any of these studies. General information, not legal or regulatory advice. Confirm current ANVISA, CEP, and FDA rules with qualified advisers. We name only the merged facility strings and example NCT IDs those sources support. We do not invent a principal investigator. We do not claim Universidade Nove de Julho as a bioaccess® client.

    If you searched Universidade Nove de Julho first-in-human, University of Nove de Julho CRO, Nove de Julho University clinical trials, or “go direct UNINOVE São Paulo,” you followed campus strings ClinicalTrials.gov still publishes as three separate labels. They are one university. They are not a first-in-human medical-device CRO, and they are not the operator of the ANVISA file.

    bioaccess®’s position is simple and it is not adversarial: the campus is the site. The First-in-Human CRO still owns ANVISA/CEP, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if São Paulo is not the only fit. Sponsors who skip the CRO and email the university still have to rebuild that stack. An NCT location row is not a CRO.

    This page merges three accent/language aliases into one slug: Universidade Nove de Julho, University of Nove de Julho, and Nove de Julho University. It does not clone InCor HCFMUSP or Dante Pazzanese. Those are different São Paulo buildings.

    Why the three spellings win the search — and why that is not a CRO

    ClinicalTrials.gov stores Portuguese and English campus names as separate facility keys. On the 1 September 2026 LATAM DEVICE sweep they sit as:

    Public snapshots of those IDs list lead sponsor University of Nove de Julho (or the Portuguese equivalent) and the matching location string. Brief titles cluster around photobiomodulation / phototherapy, low-level laser, kinesio taping, acupuncture on trapezius, neuromuscular stimulus, and tDCS in hemiparesis. We cite the IDs as facility evidence. We will not invent a PI. We will not claim bioaccess® ran any of them. No live bioaccess® case-study page names this university as a client site. Combined DEVICE n=11+9+6 is how a sponsor searching any of the three spellings finds a campus without finding an operator.

    The site is the site. The CRO is the operator.

    A São Paulo private university can provide labs, coordinators, institutional CEP calendars, and investigators who have already appeared on NCT rows under three English/Portuguese spellings. That is necessary. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What the university can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing lab.
    • Share institutional CEP calendars and university research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the university is not built to own for an investigational device:

    • ANVISA. Device investigations sit under RDC 837/2023 (dossier in Portuguese). Three NCT spellings do not become that dossier.
    • CEP. Institutional ethics under Law 14874. The CEP is tied to the host institution once the site is chosen.
    • Investigational import — a separate permit from trial authorization and from later market registration. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a UNINOVE-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF.
    • The 21 CFR 812.28 package. Eligibility is not clearance. A site MSA does not produce it.
    • Multi-country optionality. If São Paulo enrollment or the indication later needs Colombia, Panama, Recife, or Porto Alegre, a single-university MSA will not stretch.

    Going direct to Universidade Nove de Julho is how you confirm a room. It is not how you open an investigational file.

    Site versus CRO

    Workstream What Nove de Julho (site) typically owns What the CRO still owns
    Procedure Labs, rooms, local staff, source documents Protocol fit, training, device accountability
    Ethics Institutional CEP calendar and local rules Packet, ICF, IB alignment, deficiency cycle
    National authority Not the permit holder by appearing on an NCT ANVISA clinical-investigation dossier (RDC 837/2023)
    Import Receiving and storage if contracted Importer of record
    Quality University quality and the case ISO 14155 monitoring, EDC, SAE, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One São Paulo university (three NCT spellings) Colombia (INVIMA) and the rest of the bioaccess® platform

    How ANVISA and CEP actually work (the short version)

    Use clinical-trials-brazil for the full pathway. Facts a sponsor searching this campus needs on one screen, already published there and not re-averaged here:

    • Combined ethics + ANVISA typically 6–10 weeks under Law 14874 and RDC 837/2023.
    • Ethics committees (CEPs) are capped at 30 business days. The CEP is tied to the host institution once the site is chosen — which is why “we already have this campus” still leaves the packet to write.
    • Published per-patient range $20,000–$35,000; 15+ pre-qualified sites; ANVISA is a WHO-listed authority.
    • For early feasibility studies not intended for Brazilian market clearance, only institutional CEP approval is required — no CONEP review for most investigations under Law 14874.
    • Trial authorization and later ANVISA market registration (RDC 751/2022 / BRH) are separate workstreams.
    • Under 21 CFR 812.28, foreign clinical data from Brazil is eligible for FDA submission and review when studies are conducted under ISO 14155 with proper ANVISA authorization and CEP ethics approval. Eligibility is not a guarantee of clearance or approval. See OUS FIH and FDA IDE.

    Ask for a protocol-specific calendar. A hospital or university email is not an ANVISA approval. bioaccess® manages the dossier in Portuguese. That is CRO work, not site work.

    All bioaccess® Brazil device protocols are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval.

    Do not smear the university — and do not merge São Paulo buildings

    Universidade Nove de Julho is a serious academic resource. Combined DEVICE volume across three spellings is a signal of how the registry indexes the same campus, not a punchline. This page is not a critique of phototherapy or rehabilitation listings. Volume is still not a device-CRO quality system. Use the site when the protocol fits. Hire the operator.

    Do not merge this campus into InCor HCFMUSP, Dante Pazzanese, or the University of Sao Paulo NCT-string page. Different queries. Different buildings.

    What the CRO still does after you have a UNINOVE slide

    1. Regulatory-fit, not tourism. Brazil is a sourced device geography. Three NCT aliases of one private university are not automatically the right room for every indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the ANVISA/CEP packet.
    3. Importer of record and device accountability.
    4. Site activation that is more than a tour. Activate Nove de Julho only if it fits the protocol.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation — eligibility, not a promise of FDA action.

    The firm was founded in 2010. That is the operator layer around a campus string.

    Colombia is still on the map

    A site-name search sometimes arrives with a stale story that bioaccess® “left Colombia.” That is false. bioaccess® still runs clinical trials in Colombia. Always bioaccess® — local entity and office, Miami headquarters, INVIMA clocks in-country. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K as published on clinical-trials-panama. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract Universidade Nove de Julho directly for a device FIH?

    You can try. The university can discuss investigator interest, local visit costs, and CEP calendars. It cannot, by appearing under three NCT spellings (n=11+9+6 DEVICE), become your ANVISA applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Why merge three names onto one page?

    Because they are accent and language aliases of one campus. ClinicalTrials.gov counted them separately. Sponsors search all three. One slug. We do not invent a fourth hospital.

    Did bioaccess® run these NCT IDs?

    No public bioaccess® case-study page says so. We will not invent that claim.

    Next step

    If the search that brought you here was Universidade Nove de Julho, University of Nove de Julho, or Nove de Julho University, start as the operator: contact bioaccess® or book from First-in-Human CRO. Country: clinical trials in Brazil. Sibling São Paulo NCT string: University of Sao Paulo.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • Universidade Federal de Pernambuco: The NCT Campus String Is Not the ANVISA File

    Figures cited from a ClinicalTrials.gov LATAM facility sweep (API pull 1 September 2026, 6:32 PM ET) and the published bioaccess® Brazil country page. Registry ranking is not a bioaccess® claim that we ran any of these studies. General information, not legal or regulatory advice. Confirm current ANVISA, CEP, and FDA rules with qualified advisers. We name only the facility string and example NCT IDs those sources support. We do not invent a principal investigator. We do not claim Universidade Federal de Pernambuco as a bioaccess® client.

    If you searched Universidade Federal de Pernambuco first-in-human, UFPE clinical trials, Federal University of Pernambuco CRO, or “go direct UFPE Recife,” you followed a campus string ClinicalTrials.gov still publishes. Universidade Federal de Pernambuco in Recife is a real federal university. It is not a first-in-human medical-device CRO, and it is not the operator of the ANVISA file.

    bioaccess®’s position is simple and it is not adversarial: the campus is the site. The First-in-Human CRO still owns ANVISA/CEP, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Recife is not the only fit. Sponsors who skip the CRO and email the university still have to rebuild that stack. An NCT location row is not a CRO.

    This page is the intercept for the NCT campus string Universidade Federal de Pernambuco. It does not clone São Paulo intercepts already live (InCor, Dante Pazzanese) or the Porto Alegre pages. Recife is a different city.

    Why the campus name wins the search — and why that is not a CRO

    On the 1 September 2026 ClinicalTrials.gov LATAM DEVICE sweep, Universidade Federal de Pernambuco, Recife, Brazil, is rank 8, n=12, sponsor class OTHER:12 on that ranking row. Example NCT IDs: NCT01449643, NCT01932684, NCT02600052.

    Public snapshots of those three IDs list lead sponsor Universidade Federal de Pernambuco. Brief titles concern inspiratory muscle training and diaphragmatic mobility, incentive spirometry / breath stacking in Parkinson’s disease, and proprioceptive neuromuscular facilitation breathing plus aerobic training. We cite the IDs as facility evidence. We will not invent a PI. We will not claim bioaccess® ran any of them. No live bioaccess® case-study page names this university as a client site. Ranking n=12 is registry volume, not a CRO product.

    That is the leak: a founder searching “UFPE device trial” or “Recife first-in-human” finds a federal campus without finding ANVISA, import, insurance, or 21 CFR 812.28.

    The site is the site. The CRO is the operator.

    A Recife federal university can provide labs, coordinators, institutional CEP calendars, and investigators who have already appeared on NCT rows. That is necessary. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What the university can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing department.
    • Share institutional CEP calendars and university research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the university is not built to own for an investigational device:

    • ANVISA. Device investigations sit under RDC 837/2023 (dossier in Portuguese: IB, protocol, ICF, insurance, GMP evidence). A Recife hallway conversation is not that dossier.
    • CEP. Institutional ethics under Law 14874. The CEP is tied to the host institution once the site is chosen.
    • Investigational import into Brazil is a separate permit from trial authorization and from later market registration. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a Recife-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF.
    • The 21 CFR 812.28 package. Eligibility is not clearance. A site MSA does not produce it.
    • Multi-country optionality. If Recife enrollment or the indication later needs São Paulo, Porto Alegre, Bogotá, or Panama City, a single-campus MSA will not stretch.

    Going direct to Universidade Federal de Pernambuco is how you confirm a room. It is not how you open an investigational file.

    Site versus CRO

    Workstream What UFPE (site) typically owns What the CRO still owns
    Procedure Labs, rooms, local staff, source documents Protocol fit, training, device accountability
    Ethics Institutional CEP calendar and local rules Packet, ICF, IB alignment, deficiency cycle
    National authority Not the permit holder by appearing on an NCT ANVISA clinical-investigation dossier (RDC 837/2023)
    Import Receiving and storage if contracted Importer of record
    Quality University quality and the case ISO 14155 monitoring, EDC, SAE, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One Recife campus Colombia (INVIMA) and the rest of the bioaccess® platform

    How ANVISA and CEP actually work (the short version)

    Use clinical-trials-brazil for the full pathway. Facts a sponsor searching this campus needs on one screen, already published there and not re-averaged here:

    • Combined ethics + ANVISA typically 6–10 weeks under Law 14874 and RDC 837/2023.
    • Ethics committees (CEPs) are capped at 30 business days. The CEP is tied to the host institution once the site is chosen — which is why “we already have this campus” still leaves the packet to write.
    • Published per-patient range $20,000–$35,000; 15+ pre-qualified sites; ANVISA is a WHO-listed authority.
    • For early feasibility studies not intended for Brazilian market clearance, only institutional CEP approval is required — no CONEP review for most investigations under Law 14874.
    • Trial authorization and later ANVISA market registration (RDC 751/2022 / BRH) are separate workstreams.
    • Under 21 CFR 812.28, foreign clinical data from Brazil is eligible for FDA submission and review when studies are conducted under ISO 14155 with proper ANVISA authorization and CEP ethics approval. Eligibility is not a guarantee of clearance or approval. See OUS FIH and FDA IDE.

    Ask for a protocol-specific calendar. A hospital or university email is not an ANVISA approval. bioaccess® manages the dossier in Portuguese. That is CRO work, not site work.

    All bioaccess® Brazil device protocols are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval.

    Do not smear the university

    Universidade Federal de Pernambuco is a serious academic resource. Ranking eighth on a public DEVICE facility list is a signal of registry volume, not a punchline. This page is not a critique of physiotherapy or respiratory-device listings on ClinicalTrials.gov. Volume is still not a device-CRO quality system. Use the site when the protocol fits. Hire the operator. Do not merge Recife into InCor, Dante Pazzanese, or Hospital de Clínicas de Porto Alegre.

    What the CRO still does after you have a UFPE slide

    1. Regulatory-fit, not tourism. Brazil is a sourced device geography. Recife is not automatically the right room for every indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the ANVISA/CEP packet.
    3. Importer of record and device accountability.
    4. Site activation that is more than a tour. Activate UFPE only if it fits the protocol.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation — eligibility, not a promise of FDA action.

    The firm was founded in 2010. That is the operator layer around a campus string.

    Colombia is still on the map

    A site-name search sometimes arrives with a stale story that bioaccess® “left Colombia.” That is false. bioaccess® still runs clinical trials in Colombia. Always bioaccess® — local entity and office, Miami headquarters, INVIMA clocks in-country. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K as published on clinical-trials-panama. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract Universidade Federal de Pernambuco directly for a device FIH?

    You can try. The university can discuss investigator interest, local visit costs, and CEP calendars. It cannot, by ranking n=12 on the DEVICE sweep, become your ANVISA applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Did bioaccess® run NCT01449643, NCT01932684, or NCT02600052?

    No public bioaccess® case-study page says so. We will not invent that claim. This page intercepts the search; it does not claim the studies.

    If I already have Recife, what does the CRO still do?

    Regulatory-fit (Brazil vs Colombia vs a multi-site Brazil design); the ANVISA/CEP packet; insurance; import; contracts and activation; ISO 14155 and the 812.28 narrative; optionality if one Recife room is not enough.

    Next step

    If the search that brought you here was Universidade Federal de Pernambuco or UFPE, start as the operator: contact bioaccess® or book from First-in-Human CRO. Country: clinical trials in Brazil.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • Panama Eye Center: The NCT Campus String Is Not the MINSA File

    Figures cited from a ClinicalTrials.gov LATAM facility sweep (API pull 1 September 2026, 6:32 PM ET) and the published bioaccess® Panama country page. Registry ranking is not a bioaccess® claim that we ran any of these studies. General information, not legal or regulatory advice. Confirm current MINSA, CNBI, and FDA rules with qualified advisers. We name only the NCT facility string “Panama Eye Center” and example NCT IDs those sources support. We do not invent a principal investigator. We do not claim Panama Eye Center as a bioaccess® client.

    If you searched Panama Eye Center first-in-human, Panama Eye Center CRO, Panama Eye Center clinical trials, or “go direct Panama Eye Center,” you followed the exact location string ClinicalTrials.gov still publishes. Panama Eye Center in Panama City is a real ophthalmic facility string in the public file. It is not a first-in-human medical-device CRO, and it is not the operator of the MINSA device file.

    bioaccess®’s position is simple and it is not adversarial: the clinic is the site. The First-in-Human CRO still owns MINSA/CNBI, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Panama City is not the only fit. Sponsors who skip the CRO and email the clinic still have to rebuild that stack. An NCT location row is not a CRO.

    This page is the intercept for the NCT campus string Panama Eye Center (n=13 DEVICE studies on the 1 September 2026 sweep — the highest new Panama device site after The Panama Clinic / CEVAXIN strings already intercepted). It does not clone the live MINIject / STAR-I intercept Panama Eye Centre / Orillac-Calvo MINIject (CMS 95530). That page is a different query: NCT03193736 STAR-I and the British Journal of Ophthalmology site name. Link it. Do not copy it. Do not invent PIs to reconcile spellings.

    Why the campus string wins the search — and why that is not a CRO

    Device registries write the implant class, the city, and the facility name. They rarely write the CRO. On the 1 September 2026 ClinicalTrials.gov LATAM DEVICE sweep, Panama Eye Center, Panama City, Panama, is rank 7, n=13, all INDUSTRY-sponsored in that ranking row. Example NCT IDs: NCT03374553, NCT03996200, NCT04517786.

    Public snapshots of those three IDs list lead sponsor iSTAR Medical and location facility Panama Eye Center (alongside other countries’ eye hospitals on some records). Brief titles concern MINIject in open-angle glaucoma. That is facility evidence for this NCT string. It is not a reason to republish the STAR-I / Orillac-Calvo page. We will not invent a PI. We will not claim bioaccess® ran these NCTs. No live bioaccess® case-study page names this clinic as a client. iSTAR Medical / MINIject is not claimed as a bioaccess® client here either — the live STAR-I intercept already says the same.

    That is the leak: a founder searching “Panama Eye Center clinical trial” finds n=13 device rows without finding MINSA, CNBI, import, insurance, or 21 CFR 812.28. Ranking after TPC/CEVAXIN is a registry fact, not a CRO product.

    The site is the site. The CRO is the operator.

    A Panama City eye clinic can provide an OR, imaging, and coordinators who have already appeared on industry device NCT rows. That is necessary. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What the clinic can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing ophthalmic service.
    • Share institutional ethics-committee calendars and local research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the clinic is not built to own for an investigational device:

    • MINSA and CNBI. The national device file is not a hallway conversation with a coordinator.
    • Investigational import. Ethics letter, investigator’s brochure, and an importation permit — end-to-end work already described on the Panama pages, not a clinic email. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. The Panama essay publishes a typical premium range of $5,000–$15,000 depending on device risk and enrollment; that is a published planning band, not a quote for your protocol.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF. The site may run visits. The CRO runs the quality system the FDA will later ask about.
    • The 21 CFR 812.28 package. Eligibility is not clearance. A site MSA does not produce it.
    • Multi-country optionality. If Panama enrollment or the indication later needs Colombia, El Salvador, Brazil, or another bioaccess® market, a single-clinic MSA will not stretch.

    Going direct to Panama Eye Center is how you confirm a room. It is not how you open a first-in-human device investigation.

    Site versus CRO

    Workstream What Panama Eye Center (site) typically owns What the CRO still owns
    Procedure OR, imaging, ophthalmic service, local staff Protocol fit, training, device accountability
    Ethics Institutional committee calendar and local rules Packet, ICF, IB, CNBI-registered process
    National authority Not the permit holder by appearing on an NCT MINSA / CNBI
    Import Receiving and storage if contracted Importer of record
    Quality Clinic quality and the case ISO 14155 monitoring, EDC, SAE, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One Panama City NCT string Colombia (INVIMA) and the rest of the bioaccess® platform

    How MINSA and CNBI actually work (the short version)

    Use the country pages for the full pathway. Panama’s Ministry of Health (MINSA), through the Dirección Nacional de Farmacia y Drogas, is the national health authority sponsors meet on device investigations. Ethics review runs through institutional bioethics committees registered with the Comité Nacional de Bioética de la Investigación (CNBI).

    Two published bioaccess® clocks, both live, both kept here as published rather than averaged into a third number:

    • On clinical-trials-panama: ethics typically 3–5 weeks; with bioaccess® coordination, protocol submission to first-patient enrollment averages 6–8 weeks. Per-patient costs on that page: $12,000–$22,000. Currency is the U.S. dollar.
    • On the March 2026 blog: early-feasibility is ethics-committee-driven (no separate national device-authority step of the INVIMA/ANVISA type); CNBI often 4–8 weeks; conservative submission-to-first-patient envelope 3–5 months including site prep and screening.

    Ask for a protocol-specific calendar. Do not treat a clinic hallway estimate as MINSA clearance. bioaccess® manages the submission and keeps the reviewer relationship. That is CRO work, not site work.

    All bioaccess® Panama protocols are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval. See OUS FIH and FDA IDE.

    Do not clone the STAR-I page — and do not smear the clinic

    Panama Eye Center is a serious ophthalmic resource on the public NCT file. This page is not a critique of that work. A cluster of industry glaucoma-device rows is a signal of registry volume, not a substitute for a CRO quality system. Use the site when the protocol fits. Hire the operator.

    For STAR-I / Orillac-Calvo / Panama Eye Centre (British spelling) stay on panama-eye-centre-orillac-calvo-miniject. For hospital-named Panama City FIH stay on The Panama Clinic first-in-human. For the vaccine-network brand stay on CEVAXIN FIH. Those are different queries.

    What the CRO still does after you have a Panama Eye Center slide

    1. Regulatory-fit, not tourism. Panama is fast and bilingual. An ophthalmic NCT string is not automatically the right room for every device indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the MINSA/CNBI packet.
    3. Importer of record and device accountability.
    4. Site activation that is more than a tour. Activate Panama Eye Center only if it fits the protocol.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation — eligibility, not a promise of FDA action.

    bioaccess® has been active in Panama since the early 2010s. The firm was founded in 2010. That is the operator layer around a campus string.

    Colombia is still on the map

    A site-name search sometimes arrives with a stale story that bioaccess® “left Colombia.” That is false. bioaccess® still runs clinical trials in Colombia. Always bioaccess® — local entity and office, Miami headquarters, INVIMA clocks in-country. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K as published on clinical-trials-panama. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract Panama Eye Center directly for a device FIH?

    You can try. A clinic can discuss investigator interest, local visit costs, and institutional ethics calendars. It cannot, by appearing as n=13 DEVICE rows, become your MINSA/CNBI applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Is this the MINIject / Orillac-Calvo page?

    No. That intercept is CMS 95530 for STAR-I (NCT03193736). This page is the NCT campus string “Panama Eye Center” (n=13). Some of those n=13 rows are other iSTAR MINIject listings. Linking is correct. Cloning is not. We do not invent a PI to merge the spellings.

    Did bioaccess® run NCT03374553, NCT03996200, or NCT04517786?

    No public bioaccess® case-study page says so. We will not invent that claim.

    Next step

    If the search that brought you here was Panama Eye Center, start as the operator: contact bioaccess® or book from First-in-Human CRO. STAR-I sibling: Panama Eye Centre / Orillac-Calvo MINIject. Hospital: The Panama Clinic first-in-human. Country: clinical trials in Panama.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • University of Sao Paulo: The NCT Campus String Is Not the ANVISA File

    Figures cited from a ClinicalTrials.gov LATAM facility sweep (API pull 1 September 2026, 6:32 PM ET) and the published bioaccess® Brazil country page. Registry ranking is not a bioaccess® claim that we ran any of these studies. General information, not legal or regulatory advice. Confirm current ANVISA, CEP, and FDA rules with qualified advisers. We name only the NCT facility string “University of Sao Paulo” and example NCT IDs those sources support. We do not invent InCor, HCFMUSP, or a principal investigator on this page. We do not claim University of Sao Paulo as a bioaccess® client.

    If you searched University of Sao Paulo first-in-human, University of Sao Paulo CRO, USP clinical trials Brazil device, or “go direct University of Sao Paulo,” you followed the exact location string ClinicalTrials.gov still publishes. University of Sao Paulo is a real university. It is not a first-in-human medical-device CRO, and it is not the operator of the ANVISA file.

    bioaccess®’s position is simple and it is not adversarial: the campus string is the site label. The First-in-Human CRO still owns ANVISA/CEP, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if São Paulo is not the only fit. Sponsors who skip the CRO and email the university still have to rebuild that stack. An NCT location row is not a CRO.

    This page answers the registry string University of Sao Paulo only. It does not invent InCor or HCFMUSP as this page’s campus. Heart-institute searches already have a live intercept: InCor HCFMUSP (CMS 95522). Link that page. Do not clone it. “University of Sao Paulo General Hospital” is a different NCT string (DEVICE n=7 on the same sweep) and is not merged here.

    Why the NCT string wins the search — and why that is not a CRO

    Sponsors type what the registry prints. On the 1 September 2026 ClinicalTrials.gov LATAM sweep, the facility string University of Sao Paulo, São Paulo, Brazil, is DEVICE rank 5, n=15, and ALL interventional rank 6, n=73. Example DEVICE NCT IDs: NCT01033084, NCT01149213, NCT01525524.

    Public snapshots of those three IDs list lead sponsor University of Sao Paulo and location facility University of Sao Paulo. Brief titles on those records are transcranial direct current stimulation studies in major depressive disorder, including post-stroke depression. We cite the IDs as facility evidence. We will not invent a PI. We will not claim they are first-in-human device programs bioaccess® ran. We will not stretch them into a heart-institute claim. No live bioaccess® case-study page names this NCT string as a client site.

    That is the leak: a founder searching “University of Sao Paulo clinical trial” or “USP FIH Brazil” finds a campus without finding ANVISA, import, insurance, or 21 CFR 812.28. Ranking n=15 device studies is registry volume, not a CRO product.

    The site is the site. The CRO is the operator.

    A São Paulo university campus can provide rooms, coordinators, institutional CEP calendars, and investigators who have already appeared on NCT rows under this English facility string. That is necessary. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What the university can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing lab or clinic.
    • Share institutional CEP calendars and university research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the university is not built to own for an investigational device:

    • ANVISA. Device investigations sit under RDC 837/2023 (dossier in Portuguese). A campus email is not that dossier.
    • CEP. Institutional ethics under Law 14874. The CEP is tied to the host institution once the site is chosen.
    • Investigational import — a separate permit from trial authorization and from later market registration. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a USP-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF.
    • The 21 CFR 812.28 package. Eligibility is not clearance. A site MSA does not produce it.
    • Multi-country optionality. If São Paulo enrollment or the indication later needs Colombia, Panama, or another campus, a single-university MSA will not stretch.

    Going direct to the University of Sao Paulo NCT string is how you confirm a label. It is not how you open an investigational file.

    Site versus CRO

    Workstream What the USP campus string (site) typically owns What the CRO still owns
    Procedure Rooms, labs, local staff, source documents Protocol fit, training, device accountability
    Ethics Institutional CEP calendar and local rules Packet, ICF, IB alignment, deficiency cycle
    National authority Not the permit holder by appearing on an NCT ANVISA clinical-investigation dossier (RDC 837/2023)
    Import Receiving and storage if contracted Importer of record
    Quality University quality and the case ISO 14155 monitoring, EDC, SAE, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One NCT spelling in São Paulo Colombia (INVIMA) and the rest of the bioaccess® platform

    How ANVISA and CEP actually work (the short version)

    Use clinical-trials-brazil for the full pathway. Facts a sponsor searching this campus needs on one screen, already published there and not re-averaged here:

    • Combined ethics + ANVISA typically 6–10 weeks under Law 14874 and RDC 837/2023.
    • Ethics committees (CEPs) are capped at 30 business days. The CEP is tied to the host institution once the site is chosen — which is why “we already have this campus” still leaves the packet to write.
    • Published per-patient range $20,000–$35,000; 15+ pre-qualified sites; ANVISA is a WHO-listed authority.
    • For early feasibility studies not intended for Brazilian market clearance, only institutional CEP approval is required — no CONEP review for most investigations under Law 14874.
    • Trial authorization and later ANVISA market registration (RDC 751/2022 / BRH) are separate workstreams.
    • Under 21 CFR 812.28, foreign clinical data from Brazil is eligible for FDA submission and review when studies are conducted under ISO 14155 with proper ANVISA authorization and CEP ethics approval. Eligibility is not a guarantee of clearance or approval. See OUS FIH and FDA IDE.

    Ask for a protocol-specific calendar. A hospital or university email is not an ANVISA approval. bioaccess® manages the dossier in Portuguese. That is CRO work, not site work.

    All bioaccess® Brazil device protocols are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval.

    Sibling heart-institute page — do not merge it here

    If the search you actually meant was Instituto do Coração / HCFMUSP / InCor, stay on incor-hcfmosp-fih. That page already covers public device rows such as Cephea and Leaflex under InCor spellings. This page will not copy those claims onto “University of Sao Paulo.” The Brazil country page already notes that São Paulo’s Hospital das Clínicas is one of the largest medical complexes in Latin America as a landscape fact; bioaccess® does not claim to operate that hospital. Dante Pazzanese remains a separate intercept. Do not smear the university.

    What the CRO still does after you have a USP slide

    1. Regulatory-fit, not tourism. Brazil is a sourced device geography. An English NCT campus string is not automatically the right room for every indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the ANVISA/CEP packet.
    3. Importer of record and device accountability.
    4. Site activation that is more than a tour. Activate a University of Sao Paulo site only if it fits the protocol — and only the building the protocol actually needs, not a merged InCor identity.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation — eligibility, not a promise of FDA action.

    The firm was founded in 2010. That is the operator layer around a campus string.

    Colombia is still on the map

    A site-name search sometimes arrives with a stale story that bioaccess® “left Colombia.” That is false. bioaccess® still runs clinical trials in Colombia. Always bioaccess® — local entity and office, Miami headquarters, INVIMA clocks in-country. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K as published on clinical-trials-panama. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract University of Sao Paulo directly for a device FIH?

    You can try. A university can discuss investigator interest, local visit costs, and CEP calendars. It cannot, by appearing as n=15 DEVICE / n=73 ALL on ClinicalTrials.gov, become your ANVISA applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Is this the InCor page?

    No. InCor / HCFMUSP is already live at incor-hcfmosp-fih. This page is the NCT string “University of Sao Paulo” only.

    Did bioaccess® run NCT01033084, NCT01149213, or NCT01525524?

    No public bioaccess® case-study page says so. We will not invent that claim.

    Next step

    If the search that brought you here was University of Sao Paulo, start as the operator: contact bioaccess® or book from First-in-Human CRO. Country: clinical trials in Brazil. Heart-institute sibling: InCor HCFMUSP.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • Hospital de Clínicas de Porto Alegre: The NCT Campus String Is Not the ANVISA File

    Figures cited from a ClinicalTrials.gov LATAM facility sweep (API pull 1 September 2026, 6:32 PM ET) and the published bioaccess® Brazil country page. Registry ranking is not a bioaccess® claim that we ran any of these studies. General information, not legal or regulatory advice. Confirm current ANVISA, CEP, and FDA rules with qualified advisers. We name only the facility strings and example NCT IDs those sources support. We do not invent a principal investigator. We do not claim Hospital de Clínicas de Porto Alegre as a bioaccess® client.

    If you searched Hospital de Clínicas de Porto Alegre first-in-human, HCPA clinical trials, Hospital de Clinicas de Porto Alegre CRO, or “go direct HCPA Brazil,” you followed a campus string ClinicalTrials.gov still publishes. Hospital de Clínicas de Porto Alegre (HCPA) in Porto Alegre, Rio Grande do Sul, is a real university hospital. It is not a first-in-human medical-device CRO, and it is not the operator of the ANVISA file.

    bioaccess®’s position is simple and it is not adversarial: the hospital is the site. The First-in-Human CRO still owns ANVISA/CEP, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Porto Alegre is not the only fit. Sponsors who skip the CRO and email the hospital still have to rebuild that stack. An NCT location row is not a CRO.

    This page is one intercept for three registry spellings of the same campus. ClinicalTrials.gov stores them as separate facility strings; we do not. Accented Hospital de Clínicas de Porto Alegre, unaccented Hospital de Clinicas de Porto Alegre, and Hospital de Clinicas e Porto Alegre (HCPA) are one page. It does not clone Fundação Universitaria de Cardiologia Porto Alegre (CMS 95612). That is a different hospital, on a different NCT (Polares MRace / NCT06113354). Linking is correct. Cloning that Polares page is not.

    Why the campus name wins the search — and why that is not a CRO

    Device registries write the city, the hospital, and a list of NCT IDs. They rarely write the CRO. On the 1 September 2026 ClinicalTrials.gov LATAM sweep (interventional DEVICE studies; all years; complete dump), this campus sits at the top of named Brazilian device facilities after filters:

    On the same sweep’s ALL interventional ranking (not device-only): accented n=293 (rank 1) and unaccented n=213 (rank 2). Those are unique NCT IDs per facility string + city + country. They are not a count of first-in-human device programs bioaccess® ran. They are not a quality score. They are how a sponsor searching “Porto Alegre hospital clinical trial” lands on a campus without landing on an operator.

    Public snapshots of those example IDs show mixed hospital- and industry-sponsored interventional work. We cite the IDs as facility evidence. We will not invent a PI. We will not claim bioaccess® ran any of them. No live bioaccess® case-study page names this hospital as a client site.

    The site is the site. The CRO is the operator.

    A Porto Alegre university hospital can provide rooms, coordinators, institutional CEP calendars, and investigators who have already appeared on hundreds of NCT rows. That is necessary. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What the hospital can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing service line.
    • Share institutional CEP calendars and hospital research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the hospital is not built to own for an investigational device:

    • ANVISA. Device investigations sit under RDC 837/2023 (dossier in Portuguese: IB, protocol, ICF, insurance, GMP evidence). A hallway conversation in Porto Alegre is not that dossier.
    • CEP. Institutional ethics under Law 14874. The CEP is tied to the host institution once the site is chosen.
    • Investigational import into Brazil is a separate permit from trial authorization and from later market registration. See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent an HCPA-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF. The site may run visits. The CRO runs the quality system the FDA will later ask about.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after GCP / ethics documentation. Eligibility is not clearance, and a site MSA does not produce it.
    • Multi-country optionality. If Porto Alegre enrollment or the indication later needs São Paulo, Bogotá, or Panama City, a single-hospital MSA will not stretch.

    Going direct to Hospital de Clínicas de Porto Alegre is how you confirm a room. It is not how you open an investigational file.

    Site versus CRO

    Workstream What HCPA (site) typically owns What the CRO still owns
    Procedure Rooms, caseload, local staff, source documents Protocol fit, training, device accountability
    Ethics Institutional CEP calendar and local rules Packet, ICF, IB alignment, deficiency cycle
    National authority Not the permit holder by appearing on an NCT ANVISA clinical-investigation dossier (RDC 837/2023)
    Import Receiving and storage if contracted Importer of record
    Quality Hospital quality and the case ISO 14155 monitoring, EDC, SAE, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One Porto Alegre campus (three NCT spellings, one building) Colombia (INVIMA) and the rest of the bioaccess® platform

    How ANVISA and CEP actually work (the short version)

    Use clinical-trials-brazil for the full pathway. Facts a sponsor searching this campus needs on one screen, already published there and not re-averaged here:

    • Combined ethics + ANVISA typically 6–10 weeks under Law 14874 and RDC 837/2023.
    • Ethics committees (CEPs) are capped at 30 business days. The CEP is tied to the host institution once the site is chosen — which is why “we already have this campus” still leaves the packet to write.
    • Published per-patient range $20,000–$35,000; 15+ pre-qualified sites; ANVISA is a WHO-listed authority.
    • For early feasibility studies not intended for Brazilian market clearance, only institutional CEP approval is required — no CONEP review for most investigations under Law 14874.
    • Trial authorization and later ANVISA market registration (RDC 751/2022 / BRH) are separate workstreams.
    • Under 21 CFR 812.28, foreign clinical data from Brazil is eligible for FDA submission and review when studies are conducted under ISO 14155 with proper ANVISA authorization and CEP ethics approval. Eligibility is not a guarantee of clearance or approval. See OUS FIH and FDA IDE.

    Ask for a protocol-specific calendar. A hospital or university email is not an ANVISA approval. bioaccess® manages the dossier in Portuguese. That is CRO work, not site work.

    All bioaccess® Brazil device protocols are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval.

    Do not smear the hospital — and do not merge Porto Alegre buildings

    Hospital de Clínicas de Porto Alegre is a serious academic resource. Ranking first on a public DEVICE facility list is a signal of registry volume, not a punchline. This page is not a critique of that work. Volume on ClinicalTrials.gov is still not a device-CRO quality system. Use the site when the protocol fits. Hire the operator.

    Do not merge this campus into Fundação Universitaria de Cardiologia. Do not merge it into São Paulo intercepts already live: InCor HCFMUSP and Instituto Dante Pazzanese. Different buildings. Different queries.

    What the CRO still does after you have an HCPA slide

    1. Regulatory-fit, not tourism. Brazil is a sourced device geography. One Porto Alegre campus is not automatically the right room for every indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the ANVISA/CEP packet.
    3. Importer of record and device accountability.
    4. Site activation that is more than a tour: contracts, training, investigational product, EDC, monitoring plan. Activate HCPA only if it fits the protocol.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative so the dataset is built for a later Pre-Sub, IDE, 510(k), De Novo, PMA, or HDE — eligibility, not a promise of FDA action.

    The firm was founded in 2010. That is the operator layer around a campus string.

    Colombia is still on the map

    A site-name search sometimes arrives with a stale story that bioaccess® “left Colombia.” That is false. bioaccess® still runs clinical trials in Colombia. Always bioaccess® — local entity and office, Miami headquarters, INVIMA clocks in-country. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K as published on clinical-trials-panama. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract Hospital de Clínicas de Porto Alegre directly for a device FIH?

    You can try. The hospital can discuss investigator interest, local visit costs, and CEP calendars. It cannot, by ranking high on ClinicalTrials.gov, become your ANVISA applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Did bioaccess® run the NCT IDs listed here?

    No public bioaccess® case-study page names this hospital. We will not invent that claim. This page intercepts the search; it does not claim the studies. Registry n=30+26+5 (DEVICE) and n=293+213 (ALL) are ClinicalTrials.gov counts, not bioaccess® enrollment.

    Is this the same hospital as Fundação Universitaria de Cardiologia?

    No. Fundação Universitaria de Cardiologia is a different Porto Alegre facility already intercepted for Polares MRace (NCT06113354). This page is the HCPA campus-string intercept.

    If I already have HCPA, what does the CRO still do?

    Regulatory-fit (Brazil vs Colombia vs a multi-site Brazil design); the ANVISA/CEP packet; insurance; import; contracts and activation; ISO 14155 and the 812.28 narrative; optionality if one Porto Alegre room is not enough.

    Next step

    If the search that brought you here was Hospital de Clínicas de Porto Alegre or HCPA, start as the operator: contact bioaccess® or book from First-in-Human CRO. Country: clinical trials in Brazil. Other Porto Alegre hospital: Fundação Universitaria de Cardiologia.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • CEVAXIN FIH: A Vaccine Research Center Is Not the Device CRO

    Figures cited from CEVAXIN public pages (retrieved 1 September 2026), ClinicalTrials.gov NCT06673264, and published bioaccess® Panama and case-study pages. General information, not legal or regulatory advice. Confirm current MINSA, CNBI, and FDA rules with qualified advisers. We name only the facility, sponsor, and trial those sources support. We do not invent a principal investigator the NCT did not publish. We do not claim CEVAXIN as a bioaccess® client.

    If you searched CEVAXIN first-in-human, CEVAXIN CRO, CEVAXIN Panama clinical trials, or “go direct CEVAXIN Panama,” you followed a research-center brand that is genuinely in the public file. Centro de Vacunación e Investigación SA (CEVAXIN) is a real Panama site network. It is not a first-in-human medical-device CRO, and it is not the operator of the MINSA device file.

    bioaccess®’s position is simple and it is not adversarial: CEVAXIN is a site. The First-in-Human CRO still owns MINSA/CNBI, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if a CEVAXIN room is not the only fit. Sponsors who skip the CRO and email the research center still have to rebuild that stack. A vaccine-trial brand does not become a device CRO because a founder typed “CEVAXIN CRO.”

    This page is the CEVAXIN-brand intercept. It does not clone The Panama Clinic first-in-human (the hospital-name page, CMS 95513) or the NCT hyphen page CEVAXIN / The Panama Clinic FIH. Those stay the building query and the registry-string query. This page answers the CEVAXIN-only search.

    Why the CEVAXIN name wins the search — and why that is not a CRO

    Site marketing writes the studies, the volunteer count, and the MINSA endorsement. It rarely writes a device CRO. CEVAXIN’s own about page (retrieved 1 September 2026) is the clean public example:

    • Medical research center founded in 2013 in the Republic of Panama.
    • Public claims: more than ten years; +40 clinical studies; +25,000 participants; +15 national and international sponsors; more than 200 research professionals.
    • Five Panama sites: The Panama Clinic, 24 de diciembre, Chorrera, and (on the same page) Avenida México and Chiriquí.
    • The work it advertises: clinical, epidemiological, and public-health studies of vaccine-preventable disease — polio, dengue, RSV, zoster, norovirus, pneumococcus, hepatitis A, meningitis, pertussis, chikungunya, COVID-19 — under national ethics committees and MINSA endorsement.
    • Staff specialties named on that page: pediatrics, epidemiology, pneumology, internal medicine, tropical medicine, health economics.

    That copy is useful. It is how a sponsor finds a Panama research center without finding a device operator. It is also how a founder concludes that “CEVAXIN CRO” is the whole first-in-human plan. It is not. MINSA still exists after you have the brand. Pediatrics and vaccine epidemiology on a staff page do not become ISO 14155 device monitoring, an investigational-device importer of record, or a 21 CFR 812.28 package.

    This article will not invent a bioaccess® relationship CEVAXIN’s pages do not contain. We do not claim CEVAXIN as a client.

    The public device NCT is a location string, not a CRO product

    One completed device registry row lists CEVAXIN as a facility. Read it as a location string.

    NCT06673264, retrieved 1 September 2026: FINESSE, first-in-human soft neural probe; lead sponsor Axoft, Inc. (INDUSTRY); no collaborator; no CRO; status COMPLETED; actual enrollment 5; actual start 14 March 2025; completion 21 August 2025. The only location row is Centro de Vacunación e Investigación SA (CEVAXIN) – The Panama Clinic, Panama City, Panama. No central contacts, no overall officials, no site investigators on that snapshot. We will not invent a PI name to fill that blank.

    That NCT is how a “CEVAXIN first-in-human” search leaks into device FIH. It is not proof that CEVAXIN sells a device-CRO stack. The live bioaccess® case study Axoft — Panama First-in-Human is the operator claim for that building: four patients implanted during brain-tumor resection at The Panama Clinic, ethics ~4 weeks, FDA Breakthrough 2022, $55M Series A April 2026 as cited on that page. The NCT did not name the CRO. We will not pretend it did. We will not invent a reconciliation of 4 versus 5 beyond what each page already prints.

    Newrotex — SilkAxons™ is a second live bioaccess® case study at The Panama Clinic (world-first SilkAxons™ implant; FIH start August 2025). That is a hospital-level operator claim. It is not a CEVAXIN-client claim.

    CEVAXIN is a site. The CRO is the operator.

    A Panama vaccine and epidemiology network can provide rooms, coordinators, volunteer pipelines, and investigators who have run MINSA-endorsed public-health studies. That is necessary for the work they publish. It is not sufficient for a first-in-human medical device study a U.S. board expects to survive FDA review.

    What a research center can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing site.
    • Share institutional ethics-committee calendars and local research rules.
    • Quote visit, staffing, and local procedure costs for the cases they will physically run.

    What the center is not built to own for an investigational device:

    • MINSA and CNBI. The national device file is not a hallway conversation with a research coordinator.
    • Investigational import. Ethics letter, investigator’s brochure, and an importation permit — end-to-end work already described on the Panama pages, not a site email.
    • Clinical trial insurance. Required. The Panama essay publishes a typical premium range of $5,000–$15,000 depending on device risk and enrollment; that is a published planning band, not a quote for your protocol.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF. The site may run visits. The CRO runs the quality system the FDA will later ask about.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after ISO 14155 / ethics documentation. Eligibility is not clearance, and a site MSA does not produce it.
    • Multi-country optionality. If Panama enrollment or the indication later needs Colombia, El Salvador, Brazil, or another bioaccess® market, a single-center MSA will not stretch.

    Going direct to CEVAXIN is how you confirm a room. It is not how you open a first-in-human device investigation.

    How MINSA and CNBI actually work (the short version)

    Use the country pages for the full pathway.

    Panama’s Ministry of Health (MINSA), through the Dirección Nacional de Farmacia y Drogas, is the national health authority sponsors meet on device investigations. Ethics review runs through institutional bioethics committees registered with the Comité Nacional de Bioética de la Investigación (CNBI).

    Two published bioaccess® clocks, both live, both kept here as published rather than averaged into a third number:

    • On clinical-trials-panama: ethics typically 3–5 weeks; with bioaccess® coordination, protocol submission to first-patient enrollment averages 6–8 weeks. Per-patient costs on that page: $12,000–$22,000. Currency is the U.S. dollar.
    • On the March 2026 blog: early-feasibility is ethics-committee-driven (no separate national device-authority step of the INVIMA/ANVISA type); CNBI often 4–8 weeks; conservative submission-to-first-patient envelope 3–5 months including site prep and screening.

    Ask for a protocol-specific calendar. Do not treat a research-center hallway estimate as MINSA clearance. bioaccess® manages the submission and keeps the reviewer relationship. That is CRO work, not site work.

    All bioaccess® Panama protocols are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval.

    What the CRO still does after you have a CEVAXIN slide

    1. Regulatory-fit, not tourism. Panama is fast and bilingual. A vaccine site network is not automatically the right room for every device indication. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the MINSA/CNBI packet.
    3. Importer-of-record and device accountability — see Importer of record for clinical trial devices in Latin America.
    4. Site activation that is more than a tour: contracts, training, investigational product, EDC, monitoring plan. Activate a CEVAXIN site only if it fits the protocol.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative so the dataset is built for a later Pre-Sub, IDE, 510(k), De Novo, PMA, or HDE — eligibility, not a promise of FDA action. See Can OUS first-in-human data support an FDA IDE submission?.

    bioaccess® has been active in Panama since the early 2010s. The firm was founded in 2010. That is the operator layer around a research-center brand.

    Do not smear the research center

    CEVAXIN is a serious vaccine and epidemiology resource. Five named Panama sites and a decade of public-health studies are not a punchline. This page is not a critique of that work. MINSA endorsement of vaccine and epi protocols is a real operating fact. It is still not a device-CRO quality system. Use the site when the protocol fits. Hire the operator. For the hospital-named search, stay on The Panama Clinic first-in-human. For the NCT hyphen, stay on CEVAXIN / The Panama Clinic FIH.

    Colombia is still on the map

    A Panama site-brand search sometimes arrives with a stale story that bioaccess® “left Colombia.” That is false. bioaccess® still runs clinical trials in Colombia. Always bioaccess® — local entity and office, Miami headquarters, INVIMA clocks in-country. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract CEVAXIN directly for a device FIH?

    You can try. A research center can discuss investigator interest, local visit costs, and institutional ethics calendars. It cannot, by publishing vaccine-trial volume, become your MINSA/CNBI device applicant, importer of record, insurer, ISO 14155 monitor, or FDA 21 CFR 812.28 packager. Contract the CRO, then let the CRO activate the site if the site fits.

    Is CEVAXIN a CRO?

    CEVAXIN publishes itself as a medical research center for clinical, epidemiological, and public-health studies. That is a site network. It is not the First-in-Human CRO for investigational devices. We do not claim CEVAXIN as a bioaccess® client.

    Is this the same page as The Panama Clinic first-in-human?

    No. That page is the hospital-named intercept (CMS 95513). The NCT hyphen is a separate page. This page is the CEVAXIN-brand intercept.

    Next step

    If the search that brought you here was CEVAXIN, start as the operator: contact bioaccess® or book from First-in-Human CRO. Hospital: The Panama Clinic first-in-human. NCT hyphen: CEVAXIN / The Panama Clinic FIH. Country: clinical trials in Panama. Named work at The Panama Clinic that is ours: Axoft and Newrotex.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • CEVAXIN / The Panama Clinic FIH: The NCT Site String Is Not the MINSA File

    Figures cited from ClinicalTrials.gov NCT06673264 (retrieved 1 September 2026), CEVAXIN public pages, published bioaccess® Panama and case-study pages, and named public press. General information, not legal or regulatory advice. Confirm current MINSA, CNBI, and FDA rules with qualified advisers. We name only the facility, sponsor, and trial those sources support. We do not invent a principal investigator the NCT did not publish. We do not claim CEVAXIN as a bioaccess® client.

    If you searched CEVAXIN Panama Clinic, CEVAXIN first-in-human, The Panama Clinic NCT, or “go direct to the site in Panama City,” you followed a facility string ClinicalTrials.gov actually published. Centro de Vacunación e Investigación SA (CEVAXIN) at The Panama Clinic is a real research center inside a real hospital. It is not the operator of the MINSA file.

    bioaccess®’s position is simple and it is not adversarial: CEVAXIN is a site (and The Panama Clinic is the building). The First-in-Human CRO still owns MINSA/CNBI, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Panama is not the only fit. Sponsors who skip the CRO and email the research center still have to rebuild that stack. An NCT location row does not become a CRO.

    This page is the intercept for that search. It does not clone The Panama Clinic first-in-human (the hospital-name page) or clinical trials in Panama. Those stay the hospital intercept and the country operating system. This page answers the CEVAXIN / NCT query.

    Why the NCT site string wins the search — and why that is not a CRO

    Device registries write the facility, the city, and the sponsor. They rarely write the CRO. NCT06673264 is the clean public example.

    Retrieved 1 September 2026 from ClinicalTrials.gov:

    • Brief title: First-In-human Trial of a NovEl Soft and Stretchable Neural probE.
    • Official title: FINESSE: First-In-Human Trial Using a NovEl Soft Neural Probe: an IDEAL StagE 1 Study.
    • Lead sponsor: Axoft, Inc. (INDUSTRY). No collaborator listed. No CRO listed.
    • Status: COMPLETED. Actual start 14 March 2025. Actual primary completion and completion 21 August 2025. Last update posted 18 September 2025.
    • Design: interventional; phase N/A; single-group; device feasibility; no masking. Actual enrollment 5.
    • Intervention, in the registry’s words: device, Soft Neural Probe — sub-acute insertion with neural signal recording during already-scheduled brain-tumor or epileptogenic-tissue resection; 30-day follow-up.
    • The only location row: Centro de Vacunación e Investigación SA (CEVAXIN) – The Panama Clinic, Panama City, Panama.
    • On that snapshot: no central contacts, no overall officials, no site contacts, no investigators. We will not invent a PI name to fill that blank.

    That is useful public information about a completed first-in-human device study at this building. It is also how a founder googles “Panama Clinic neural probe” and lands on a vaccine-research center with no operator on the page.

    The same leak exists in trade press that never touches this NCT. Medical Device Network (retrieved 23 August 2026) placed Nanochon’s Chondrograft first-in-human at The Panama Clinic, with named sports-medicine surgeons, MINSA approval, and no CRO in the copy. As of this writing, bioaccess® does not list Nanochon as a client. We cite that press for one reason: this is how a sponsor finds the hospital without finding the operator. We will not add Nanochon to a bioaccess® hospital list.

    CEVAXIN is a site. The Panama Clinic is a building. The CRO is the operator.

    CEVAXIN’s own about page (retrieved 1 September 2026) describes a medical research center founded in 2013 in Panama. Public claims on that page: more than ten years; +40 clinical studies; +25,000 participants; +15 national and international sponsors; more than 200 research professionals; five Panama sites, including The Panama Clinic, 24 de diciembre, and Chorrera (the same page also lists Avenida México and Chiriquí). The work it advertises is clinical, epidemiological, and public-health studies of vaccine-preventable disease — polio, dengue, RSV, zoster, norovirus, pneumococcus, hepatitis A, meningitis, pertussis, chikungunya, COVID-19 — under national ethics committees and MINSA endorsement.

    That is a real vaccine and epidemiology site network. It is not a first-in-human medical-device CRO. Pediatrics, epidemiology, and tropical medicine on a staff page do not become ISO 14155 device monitoring, an investigational-device importer of record, or a 21 CFR 812.28 package because one NCT row hyphenated the legal name onto The Panama Clinic.

    What a site can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and whether a protocol can sit in an existing research center or a surgical service in the same building.
    • Share institutional ethics-committee calendars and hospital research rules.
    • Quote procedure, bed, and local staffing costs for the cases they will physically run.

    What the site is not built to own for an investigational device:

    • MINSA and CNBI. The national file is not a hallway conversation with a research coordinator, and it is not an NCT location string.
    • Investigational import. Ethics letter, investigator’s brochure, and an importation permit — end-to-end work already described on the Panama pages, not a site email.
    • Clinical trial insurance. Required. The Panama essay publishes a typical premium range of $5,000–$15,000 depending on device risk and enrollment; that is a published planning band, not a quote for your protocol.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF. The hospital runs the case. The research center may run visits. The CRO runs the quality system the FDA will later ask about.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after ISO 14155 / ethics documentation. Eligibility is not clearance, and a site MSA does not produce it.
    • Multi-country optionality. If Panama enrollment or the indication later needs Colombia, El Salvador, Brazil, or another bioaccess® market, a single-site MSA will not stretch.

    Going direct to CEVAXIN or The Panama Clinic is how you confirm a room. It is not how you open a first-in-human device investigation.

    How MINSA and CNBI actually work (the short version)

    Use the country pages for the full pathway. The facts a sponsor searching this NCT needs on one screen:

    Panama’s Ministry of Health (MINSA), through the Dirección Nacional de Farmacia y Drogas, is the national health authority sponsors meet on device investigations. Ethics review runs through institutional bioethics committees registered with the Comité Nacional de Bioética de la Investigación (CNBI).

    Two published bioaccess® clocks, both live, both kept here as published rather than averaged into a third number:

    • On clinical-trials-panama: ethics typically 3–5 weeks; with bioaccess® coordination, protocol submission to first-patient enrollment averages 6–8 weeks. Per-patient costs on that page: $12,000–$22,000. Currency is the U.S. dollar.
    • On the March 2026 blog: early-feasibility is ethics-committee-driven (no separate national device-authority step of the INVIMA/ANVISA type); CNBI often 4–8 weeks; conservative submission-to-first-patient envelope 3–5 months including site prep and screening.

    Ask for a protocol-specific calendar. Do not treat a research-center hallway estimate as MINSA clearance. bioaccess® manages the submission and keeps the reviewer relationship. That is CRO work, not site work.

    All bioaccess® Panama protocols are run under ISO 14155 and the Declaration of Helsinki. Data is designed to be eligible for FDA submission and review under 21 CFR 812.28 on a case-by-case basis — not a guarantee of clearance or approval.

    Which first-in-human studies has bioaccess® already run at this building?

    Two named programs, already on live case-study pages. We will not add a third hospital-level claim we have not verified on a bioaccess® page. We will not pretend the NCT named the CRO; it did not.

    Axoft — ultra-soft BCI at The Panama Clinic

    Live case study Axoft — Panama First-in-Human: ultra-soft implantable BCI; FDA Breakthrough Device Designation (2022). With bioaccess®, the FIH ran at The Panama Clinicfour patients implanted during brain-tumor resection — inside a worldwide effort the same page reports as 11 implants, then a $55M Series A in April 2026. Ethics on that page: 4 weeks. bioaccess® ran the regulatory submission, site prep, surgical coordination, and FDA-oriented data collection.

    NCT06673264 is the public registry row for that Axoft FINESSE study: completed, actual n=5, location string CEVAXIN–The Panama Clinic, no CRO on the record. Read both sources as they are. The case study is the operator claim. The NCT is the site-direct leak. We will not invent a reconciliation of 4 versus 5 beyond what each page already prints.

    Newrotex — world’s first SilkAxons™ implant

    Live case study Newrotex — SilkAxons™: investigational silk nerve guide. World-first SilkAxons™ implant at The Panama Clinic through bioaccess®; FIH start August 2025; still investigational; regulatory approval on that page ~2 weeks. bioaccess® found the microsurgery team and ran screening, surgical logistics, implant tracking, and follow-up under ISO 14155-aligned protocols.

    The country page also names other Panama work. Those are Panama-country claims, not “at CEVAXIN” claims, so they stay off this list.

    What the CRO still does after you have a facility string

    Once CEVAXIN–The Panama Clinic is on the slide, the remaining job is the one sponsors skip when they go site-direct:

    1. Regulatory-fit, not tourism. Panama is fast and bilingual. It is not automatically the right country for every indication or every FDA plan. bioaccess® still runs trials in Colombia and the rest of the platform.
    2. Protocol, IB, ICF, insurance, and the MINSA/CNBI packet.
    3. Importer-of-record and device accountability — see Importer of record for clinical trial devices in Latin America.
    4. Site activation that is more than a tour: contracts, training, investigational product, EDC, monitoring plan. Activate CEVAXIN, The Panama Clinic, or both only if they fit the protocol. A vaccine-research center is not automatically a neurosurgical FIH site.
    5. ISO 14155 monitoring and the 21 CFR 812.28 narrative so the dataset is built for a later Pre-Sub, IDE, 510(k), De Novo, PMA, or HDE — eligibility, not a promise of FDA action. See Can OUS first-in-human data support an FDA IDE submission?.

    bioaccess® has been active in Panama since the early 2010s. The firm was founded in 2010. That is the operator layer around a site string like this one.

    Colombia is still on the map

    A Panama Clinic search sometimes arrives with a stale story that bioaccess® “left Colombia.” That is false. bioaccess® still runs clinical trials in Colombia. Always bioaccess® — local entity and office, Miami headquarters, INVIMA clocks in-country. The country page’s published comparison: Panama ethics 3–5 weeks vs. Colombia 4–6 weeks; per-patient $12K–$22K vs. $15K–$25K. We pick the country the device needs. The founder podcast is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract CEVAXIN or The Panama Clinic directly?

    You can try. A research center can discuss investigator interest, local procedure costs, and institutional ethics calendars. It cannot, by appearing on an NCT row, become your MINSA/CNBI applicant, importer of record, insurer, ISO 14155 monitor, or FDA 21 CFR 812.28 packager. If the goal is a first-in-human device study, contract the CRO that already ran FIH implants at that building, then let the CRO activate the site.

    Does CEVAXIN run device first-in-human studies?

    CEVAXIN publishes vaccine, epidemiology, and public-health work. One completed device NCT lists it as the location for Axoft FINESSE. That is a facility string, not a device-CRO product. We do not claim CEVAXIN as a bioaccess® client.

    Which FIH studies has bioaccess® already run at The Panama Clinic?

    Two on live case-study pages: Axoft and Newrotex. We do not add Nanochon. Nanochon’s public press places Chondrograft at The Panama Clinic; it does not make Nanochon a bioaccess® client.

    Next step

    If the search that brought you here was CEVAXIN or the NCT location, start as the operator: contact bioaccess® or book from First-in-Human CRO. Keep the hospital intercept on The Panama Clinic first-in-human and the country system on clinical trials in Panama. Named work at this building: Axoft and Newrotex.

    CEVAXIN-brand query (no hospital hyphen): CEVAXIN FIH: a vaccine research center is not the device CRO.

    Julio G. Martinez-Clark, CEO · bioaccess®

  • Understanding DHR Compliance for Medical Device Manufacturing

    Understanding DHR Compliance for Medical Device Manufacturing

    Introduction

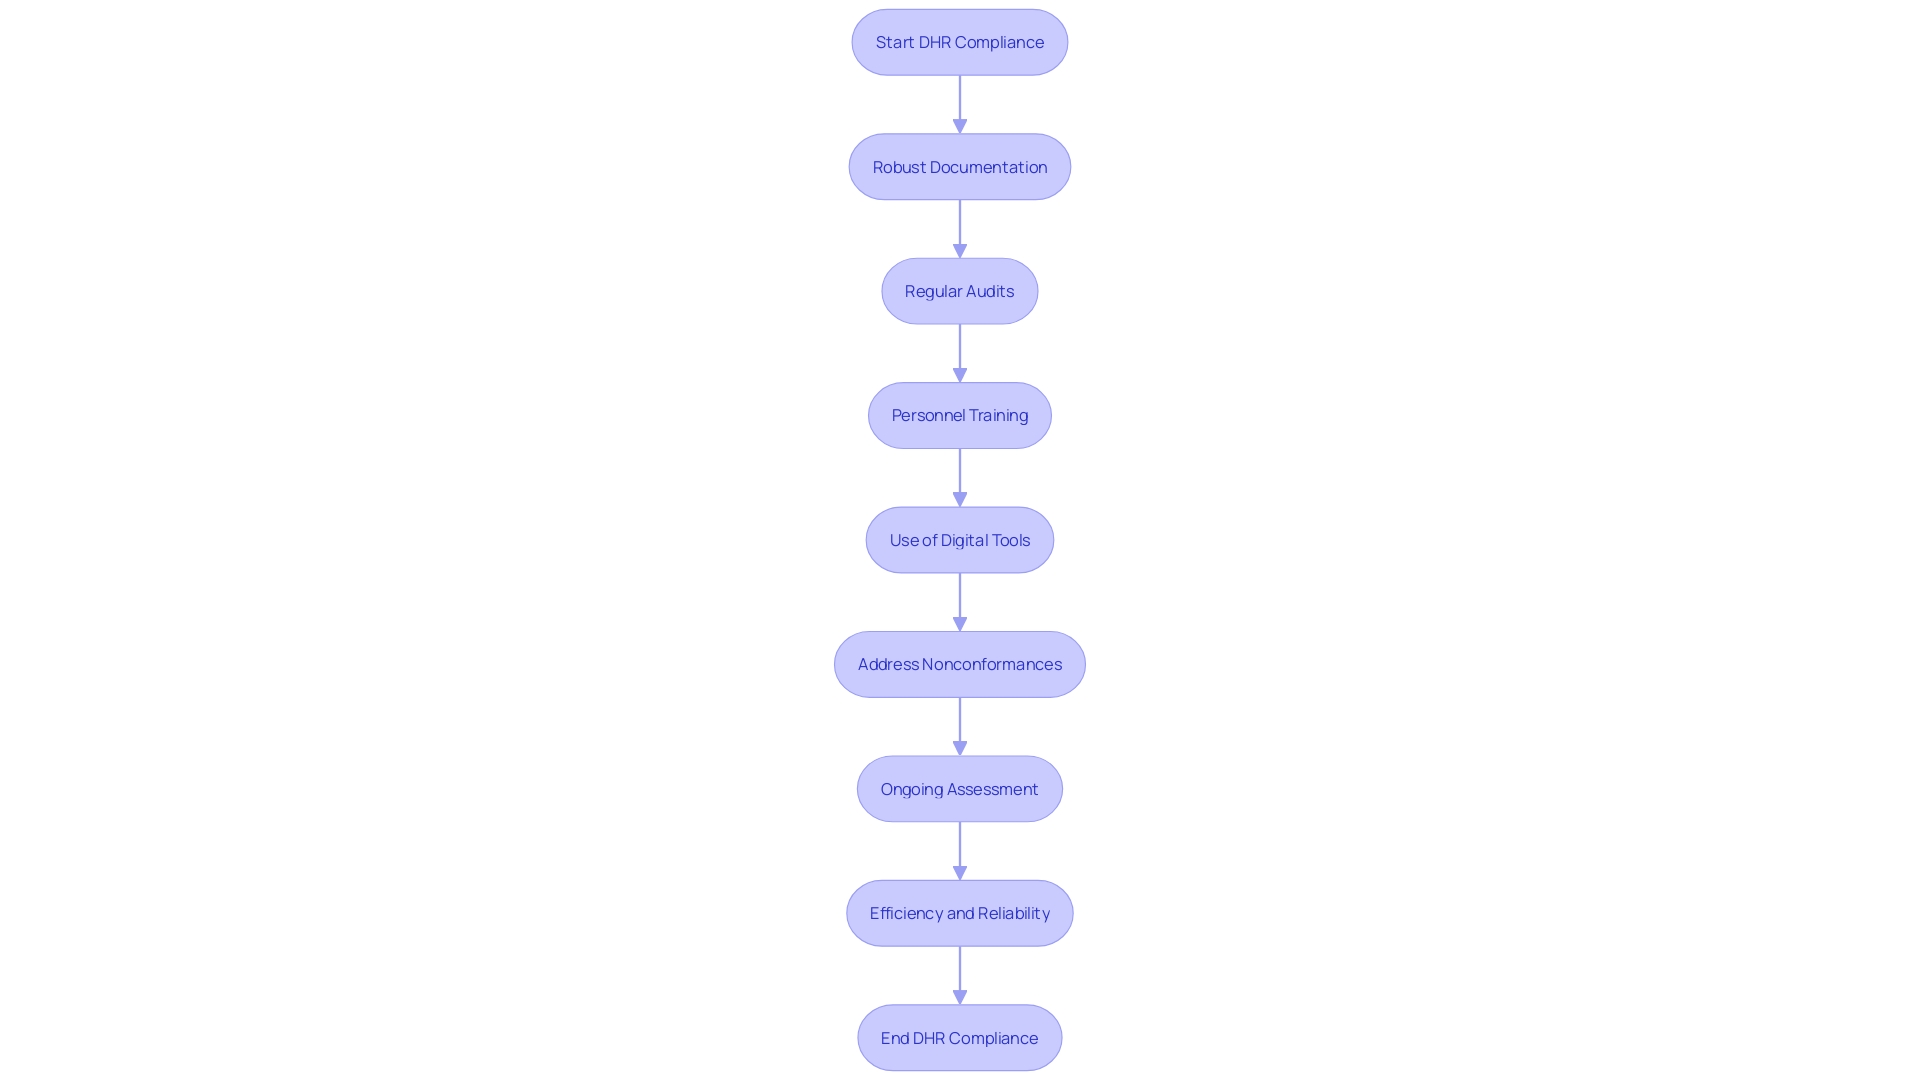
    Medical devices play a vital role in modern healthcare, and ensuring their safety and efficacy is paramount. A Device History Record (DHR) serves as a comprehensive documentation tool that meticulously traces the life of a medical device from its initial design through production and into post-market surveillance. This article delves into the intricate details of what constitutes a DHR, the regulatory requirements set forth by bodies such as the FDA and the European Medicines Agency, and best practices for maintaining compliance.

    By exploring key components and emphasizing the importance of thorough documentation, the aim is to highlight how DHRs contribute to the overall safety, quality, and regulatory adherence of medical devices.

    What is a Device History Record (DHR)?

    A (DHR) meticulously documents the entire lifecycle of a medical instrument, from its design and manufacturing to . This comprehensive compilation is crucial for ensuring that each item adheres to its specified requirements and complies with regulatory standards. Maintaining complete visibility into the (BOM), including component serialization and lot traceability, is essential for risk management. This traceability becomes particularly important when regulations evolve, as it allows producers to quickly identify and address any components at risk. highlight the significance of a comprehensive benefit-risk evaluation during both the design and development stages, as well as in post-market monitoring, to verify the safety and effectiveness of the product throughout its lifecycle. ‘In the intricate supply networks characteristic of healthcare equipment production, it is standard procedure for producers to seek compliance details from their upstream providers as a component of the certification process.’. This ensures a traceable history that can be reviewed during audits and inspections, safeguarding both the manufacturer and the end-users.

    Key Components of a DHR

    ‘A (DHR) is a crucial element of medical equipment manufacturing, meticulously documenting the entire production process to ensure adherence to safety and efficacy standards.’. Key elements of a DHR include equipment identification, production records, and . Additionally, it records any modifications made during manufacturing, results from inspections and tests, and reports of complaints or non-conformances.

    ‘This comprehensive documentation is crucial for and FDA inspections, providing a transparent trail of the product’s journey from production to market.’. Effective and monitoring are imperative, as emphasized by the Quality Management System Regulation (QMSR). Manufacturers must establish procedures to monitor and analyze post-market information, such as complaints and adverse events, to identify potential risks and take appropriate actions to mitigate them. ‘These measures are vital for maintaining the safety and effectiveness of throughout their lifecycle.’.

    The recent recall of Philips’ DreamStation for sleep apnea, which revealed that the company was aware of defects for over a decade before taking action, underscores the importance of rigorous . This event emphasizes the importance for producers to actively handle risks and guarantee adherence to legal standards.

    Integrating into the design, production, and post-market processes can result in the creation of high-quality products that fulfill compliance standards and ensure optimal patient results. As the regulatory environment keeps changing, producers must remain alert and adjust to guarantee their products consistently meet the necessary standards.

    This flowchart illustrates the key steps and elements involved in the Product History Record (DHR) process for medical equipment manufacturing, highlighting the importance of documentation and post-market surveillance.

    Regulatory Requirements for DHR

    Regulatory organizations such as the FDA and the European Medicines Agency require that producers maintain as part of their quality system regulations. This requirement ensures traceability and adherence to established guidelines, which is critical for demonstrating the safety and effectiveness of healthcare products. According to the new (MDR), all new medical instruments entering the European market must be compliant with these stringent requirements, and manufacturers of existing products must recertify them accordingly.

    The importance of maintaining comprehensive DHS is underscored by the need for robust , which serves as the backbone of . As Article 62 of the EU MDR states, must ensure the protection of participants’ rights, safety, and well-being while generating scientifically valid data. This data is pivotal for proving that a product is both safe and effective, a necessity for market approval. For instance, in the US, approximately 10-15% of successful 510(k) submissions for Class II products rely on , while all Class III products require extensive clinical trials to establish their safety and efficacy.

    Additionally, the evolving environment of healthcare equipment rules necessitates producers to adjust constantly to new compliance requirements. Recent initiatives, such as the UK’s refreshed , aim to expedite the marketing authorization process while ensuring patient safety. Dr. Laura Squire, Med Tech Regulatory Reform Lead, emphasized the importance of these advancements, stating that they offer significant opportunities for patient care improvements without compromising safety or quality.

    In summary, adherence to DHR and other legal requirements is not only essential for avoiding penalties but also for ensuring the safety and effectiveness of medical devices. The changing oversight environment requires careful compliance with quality systems, strong management, and continuous adjustment to new governance frameworks.

    This flowchart outlines the process of compliance with Device History Records (DHR) and regulatory requirements for medical devices.

    Best Practices for DHR Compliance

    To ensure under the MDR, manufacturers must adopt a comprehensive approach that includes such as and . Utilizing electronic record-keeping systems can significantly reduce errors associated with manual handling, thereby enhancing accuracy and traceability. Training personnel on the criticality of maintaining accurate DHS and updating work instructions based on real-time data can further mitigate risks of nonconformance.

    ‘Regular assessment and ongoing enhancement of DHR processes are essential to comply with compliance standards.’. Addressing nonconformances promptly is crucial, as errors can arise from various factors including supplier changes, manufacturing defects, and human error. Utilizing digital tools for data linkage and intelligent mock-ups ensures that every workstation maintains high standards of quality and accuracy. This multi-faceted strategy not only aids in but also enhances the overall efficiency and reliability of the .

    This flowchart illustrates the comprehensive approach manufacturers should take to ensure Device History Record (DHR) compliance under the MDR. It outlines the key steps and best practices involved in maintaining compliance, including documentation, audits, training, and addressing nonconformances.

    Conclusion

    The significance of Device History Records (DHRs) in the medical device industry cannot be overstated. DHRs serve as comprehensive documentation that tracks the entire lifecycle of medical devices, ensuring compliance with regulatory standards and enhancing safety and effectiveness. By meticulously recording each stage—from design and manufacturing to post-market surveillance—DHRs facilitate risk management and enable manufacturers to quickly identify and address potential issues.

    Key components of a DHR include device identification, production records, quality control documentation, and records of any modifications or non-conformances. This thorough documentation not only supports internal audits and regulatory inspections but also plays a crucial role in post-market surveillance. The case of the Philips DreamStation recall underscores the necessity for proactive risk management and compliance, highlighting the consequences of inadequate monitoring.

    Regulatory requirements established by bodies such as the FDA and the European Medicines Agency mandate the maintenance of DHRs as part of quality system regulations. These requirements emphasize the importance of robust clinical data for regulatory submissions, ensuring that medical devices meet safety and efficacy standards. As the regulatory landscape evolves, manufacturers must remain vigilant and adapt their practices to comply with new demands, which is essential for maintaining market approval and ensuring patient safety.

    Best practices for DHR compliance involve adopting systematic documentation procedures, utilizing electronic record-keeping systems, and conducting regular audits. Continuous improvement and prompt addressing of nonconformances are critical to maintaining high standards of quality. By implementing these strategies, manufacturers can enhance the efficiency and reliability of their processes, ultimately contributing to better patient outcomes and regulatory adherence.

    Ready to navigate the evolving regulatory landscape with confidence? Connect with bioaccess™ today to streamline your clinical research and ensure compliance with the highest standards.

    Frequently Asked Questions

    What is a Device History Record (DHR)?

    A Device History Record (DHR) is a detailed document that tracks the entire lifecycle of a medical instrument, from its design and manufacturing to quality control measures. It ensures that each item meets specified requirements and complies with regulatory standards.

    Why is maintaining a DHR important?

    Maintaining a DHR is crucial for ensuring traceability, risk management, and compliance with regulations. It provides complete visibility into components, which is essential for identifying and addressing any risks associated with medical devices.

    What key elements are included in a DHR?

    Key elements of a DHR include equipment identification, production records, quality control documentation, modifications made during manufacturing, inspection and test results, and reports of complaints or non-conformances.

    How does a DHR support regulatory compliance?

    Regulatory organizations, such as the FDA and the European Medicines Agency, require DHRs to ensure adherence to quality system regulations. This documentation demonstrates the safety and effectiveness of healthcare products, which is critical for market approval.

    What is the role of post-market surveillance in DHR?

    Post-market surveillance involves monitoring and analyzing post-market information, such as complaints and adverse events. This practice is essential for identifying potential risks and ensuring the ongoing safety and effectiveness of medical instruments throughout their lifecycle.

    What are the consequences of not maintaining a DHR?

    Failure to maintain a DHR can lead to penalties and compliance issues. It may also compromise the safety and effectiveness of medical devices, potentially putting patients at risk.

    How can manufacturers ensure compliance with DHR requirements?

    Manufacturers can ensure compliance by implementing robust documentation procedures, conducting regular audits, utilizing electronic record-keeping systems, training personnel on the importance of accurate DHR maintenance, and promptly addressing nonconformances.

    What recent regulatory changes affect DHR compliance?

    Recent regulations, such as the EU Medical Equipment Regulation (MDR), require that all new medical instruments comply with stringent requirements before entering the European market. Existing products also need to be recertified.

    How does risk management integrate with DHR?

    Integrating risk management principles into design, production, and post-market processes helps create high-quality products that fulfill compliance standards and ensure optimal patient outcomes.

    What is the significance of clinical data in DHR?

    Robust clinical data is critical for regulatory submissions and must demonstrate that a product is safe and effective. This data supports market approval and compliance with regulatory requirements.

    How do evolving regulations impact manufacturers?

    Manufacturers must remain vigilant and adapt to changing regulations to ensure their products consistently meet necessary standards. This includes staying updated with new compliance requirements and enhancing DHR processes accordingly.

    List of Sources

    1. What is a Device History Record (DHR)?
      • starfishmedical.com (https://starfishmedical.com/blog/esg-medical-device-impact)
      • medtechintelligence.com (https://medtechintelligence.com/feature_article/role-of-clinical-evaluation-report-consultants)
      • greenlight.guru (https://greenlight.guru/blog/navigating-clinical-evaluations-and-investigations-in-medtech)
      • schlafenderhase.com (https://schlafenderhase.com/ebooks/medical-device-report-how-are-compliance-strategies-evolving)
      • medicaldevice-network.com (https://medicaldevice-network.com/news/mhra-puts-technology-in-the-spotlight-in-2024-25-business-plan)
      • medicaldevice-network.com (https://medicaldevice-network.com/features/10-medtech-stories-that-made-headlines-in-2023)
      • alirahealth.com (https://alirahealth.com/our-services/medical-device-regulation-mdr)
      • infomeddnews.com (https://infomeddnews.com/ambulatory-ehr-market)
    2. Key Components of a DHR
      • medicaldevice-network.com (https://medicaldevice-network.com/news/curavit-launches-heor-services-for-digital-therapeutic-trials)
      • medicaldevice-network.com (https://medicaldevice-network.com/features/10-medtech-stories-that-made-headlines-in-2023)
      • schlafenderhase.com (https://schlafenderhase.com/ebooks/medical-device-report-how-are-compliance-strategies-evolving)
      • greenlight.guru (https://greenlight.guru/blog/navigating-clinical-evaluations-and-investigations-in-medtech)
      • fda.gov (https://fda.gov/medical-devices/postmarket-requirements-devices/quality-system-qs-regulationmedical-device-current-good-manufacturing-practices-cgmp)
      • medtechintelligence.com (https://medtechintelligence.com/feature_article/risk-management-in-medical-devices-harmonizing-iso-14971-2019-fda-qmsr)
      • greenlight.guru (https://greenlight.guru/blog/enterprise-guide-to-postmarket-management-for-medical-devices)
      • fda.gov (https://fda.gov/medical-devices/postmarket-requirements-devices/quality-system-qs-regulationmedical-device-current-good-manufacturing-practices-cgmp)
    3. Regulatory Requirements for DHR
      • greenlight.guru (https://greenlight.guru/blog/guide-clinical-data-management-medtech)
      • medtechintelligence.com (https://medtechintelligence.com/feature_article/role-of-clinical-evaluation-report-consultants)
      • fda.gov (https://fda.gov/medical-devices/postmarket-requirements-devices/quality-system-qs-regulationmedical-device-current-good-manufacturing-practices-cgmp)
      • alirahealth.com (https://alirahealth.com/our-services/medical-device-regulation-mdr)
      • schlafenderhase.com (https://schlafenderhase.com/ebooks/medical-device-report-how-are-compliance-strategies-evolving)
      • medtechintelligence.com (https://medtechintelligence.com/news_article/mhra-releases-roadmap-of-future-uk-medical-device-regulation)
      • medicaldevice-network.com (https://medicaldevice-network.com/news/mhra-puts-technology-in-the-spotlight-in-2024-25-business-plan)
      • alirahealth.com (https://alirahealth.com/our-services/medical-device-regulation-mdr)
    4. Best Practices for DHR Compliance
      • elsevier.com (https://elsevier.com/industry/medical-device-regulation?dgcid=RN_CM_Sourced_400006591#2-mdr-webinars)
      • greenlight.guru (https://greenlight.guru/blog/mdr-ivdr-challenges-opportunities)
      • schlafenderhase.com (https://schlafenderhase.com/ebooks/medical-device-report-how-are-compliance-strategies-evolving)
      • greenlight.guru (https://greenlight.guru/blog/guide-clinical-data-management-medtech)
      • medtechintelligence.com (https://medtechintelligence.com/feature_article/digital-continuity-strategies-for-product-recall-resilience)
      • medtechintelligence.com (https://medtechintelligence.com/feature_article/role-of-clinical-evaluation-report-consultants)
      • medicaldevice-network.com (https://medicaldevice-network.com/news/curavit-launches-heor-services-for-digital-therapeutic-trials)
      • medicaldevice-network.com (https://medicaldevice-network.com/news/sdc-byod-epro-trials)
      • medicaldevice-network.com (https://medicaldevice-network.com/news/mhra-puts-technology-in-the-spotlight-in-2024-25-business-plan)
      • medtechintelligence.com (https://medtechintelligence.com/feature_article/digital-continuity-strategies-for-product-recall-resilience)
      • biopharminternational.com (https://biopharminternational.com/view/digitalization-the-route-to-biopharma-4-0)

  • Fundação Universitaria de Cardiologia Porto Alegre: Polares MRace EFS Site, Not the ANVISA File

    Figures cited from the live ClinicalTrials.gov record NCT06113354 (last update posted 1 September 2026; first posted 2 November 2023) and the published bioaccess® Brazil country page, verified 1 September 2026. General information, not legal or regulatory advice. Confirm current ANVISA, CEP, and FDA rules with qualified advisers. We name only the facility, investigators, and trial those sources support. Polares Medical is not claimed as a bioaccess® client. bioaccess® is not listed on this NCT.

    If you searched Fundação Universitaria de Cardiologia clinical trial, Porto Alegre MRace, Polares Medical Brazil EFS, EXPLORE MRace BR, or “go direct to the Porto Alegre mitral site,” you followed a facility string ClinicalTrials.gov still publishes on 1 September 2026. Fundação Universitaria de Cardiologia in Porto Alegre, Rio Grande do Sul, is a real cardiology facility on that record. It is not the operator of the ANVISA file.

    bioaccess®’s position is simple and it is not adversarial: Fundação Universitaria de Cardiologia is the site. The First-in-Human CRO still owns ANVISA / CEP, investigational import, insurance, ISO 14155 monitoring, and the FDA 21 CFR 812.28 package — plus the option to add Colombia or another Latin American country if Porto Alegre is not the only fit. Sponsors who skip the CRO and email the hospital still have to rebuild that stack. A recruiting location row does not become a CRO.

    This page is the intercept for the Porto Alegre query. It does not clone clinical trials in Brazil. That page stays the country operating system. The São Paulo sister row on the same NCT already has its own intercept: InCor HCFMUSP. Do not merge Porto Alegre into InCor. PercAssist AVANXA remains a separate city-plus-KOL intercept with no hospital invented: PercAssist AVANXA Brazil.

    Why the hospital name wins the search — and why that is not a CRO

    NCT06113354 is an industry device early-feasibility listing. Brief title: EXPLORE MRace (BR): Early Feasibility Experience of Posterior Leaflet Restoration to Reduce Mitral Regurgitation Using the MRace Implant. Official title: Early Feasibility Experience of Posterior Leaflet Restoration to Reduce Mitral Regurgitation Using the MRace Implant Brazil (EXPLORE MRace – BR). Acronym: EXPLORE MRace. Lead sponsor: Polares Medical SA, class INDUSTRY. Collaborator listed: Polares Medical, Inc. only. No CRO is listed.

    Design on the 1 September 2026 snapshot: interventional; single-group registry; no masking; primary purpose DEVICE_FEASIBILITY; phase N/A; estimated enrollment 10; status RECRUITING. Actual start 8 April 2024. Study first posted 2 November 2023; last update posted 1 September 2026. Condition: mitral valve disease. Intervention, in the registry’s words: Transcatheter mitral valve repair (MRace Implant and Delivery System), other name TMVr — femoral-vein / transseptal placement of a prosthesis intended to augment the posterior mitral leaflet.

    Location rows currently published:

    • Fundação Universitaria de Cardiologia, Porto Alegre, Rio Grande do Sul, Brazil — RECRUITING. Site contact named as Rogerio Leite, MD. Principal investigator listed as Roberio Leite, MD (names as published on ClinicalTrials.gov; we will not invent a single merged identity or invent a hospital email beyond what the public row shows).
    • InCor – Instituto do Coração do Hospital das Clínicas da FMUSP, São Paulo, Brazil — RECRUITING. Principal investigators / contacts named include Alexandre Abizaid, MD and Fabio Sandoli de Brito, MD. Already intercepted on incor-hcfmosp-fih.

    Central contact on the record: Kristine Orosz, Polares Medical. Study director: Robin Eckert, Polares Medical. The brief summary still says “up to 10 patients at one (1) center in Brazil,” while the locations module lists two recruiting Brazilian facilities. We report both facts as published. We do not invent which building ran which case.

    Read the record as it is. Primary purpose is DEVICE_FEASIBILITY and the title says Early Feasibility. Estimated n=10 is classic EFS scale. No CRO collaborator appears. That is the site-direct leak: a sponsor searching MRace, Polares, or Porto Alegre cardiology now lands on a named hospital with InCor already known and Fundação Universitaria still without a dedicated public intercept until this page.

    Porto Alegre is a site. The CRO is the operator.

    A Porto Alegre cardiology foundation can provide imaging, structural-heart rooms, and an investigator the registry already named. That is necessary. It is not sufficient for an early-feasibility TMVr study a U.S. board expects to survive FDA review — including a later IDE conversation after OUS feasibility.

    What a site can typically do when a sponsor “goes direct”:

    • Discuss investigator interest and procedural feasibility for a mitral protocol — when that service is available and appropriate for your device, which is not automatic.
    • Share institutional CEP calendars and hospital research rules.
    • Quote procedure, visit, and local staffing costs for the cases they will physically run.

    What the site is not built to own for an investigational device:

    • ANVISA. Device investigations sit under RDC 837/2023 (dossier in Portuguese: IB, protocol, ICF, insurance, GMP evidence). A hallway conversation in Porto Alegre is not that dossier.
    • CEP. Institutional ethics under Law 14874; published country-page cap of 30 business days. The CEP is tied to the host institution once the site is chosen — which is why “we already have Fundação Universitaria” still leaves the packet to write.
    • Investigational import into Brazil is a separate permit from the trial authorization and from later ANVISA market registration (RDC 751/2022 / BRH). See importer of record for clinical trial devices in Latin America.
    • Clinical trial insurance. Required. We will not invent a Porto Alegre-only premium here.
    • ISO 14155 monitoring, EDC, SAE reporting, and the TMF — including if you later use the InCor row on the same NCT or add Colombia.
    • The 21 CFR 812.28 package. Foreign data is eligible for FDA submission and review after GCP / ethics documentation as that rule defines it. Eligibility is not clearance. See OUS FIH and FDA IDE.
    • Multi-country optionality. If Porto Alegre enrollment, imaging, or the indication later needs São Paulo capacity already on this NCT, Bogotá, or Panama City, a single-hospital MSA will not stretch.

    Going direct to Fundação Universitaria de Cardiologia is how you confirm a room. It is not how you open an investigational file.

    Site versus CRO

    Workstream What Fundação Universitaria (site) typically owns What the CRO still owns
    Procedure OR / hybrid room, imaging, mitral caseload, local staff Protocol fit, training, MRace-class device accountability
    Ethics Institutional CEP calendar and local rules Packet, ICF, IB alignment, deficiency cycle
    National authority Not the permit holder by being listed on an NCT ANVISA clinical-investigation dossier (RDC 837/2023)
    Import Receiving and storage if contracted Importer of record
    Quality Hospital quality and the case ISO 14155 monitoring, EDC, SAE, TMF
    FDA conversation Source documents from cases they run 21 CFR 812.28 narrative — eligibility, not clearance
    Country optionality One Porto Alegre building (plus InCor on the same NCT) Colombia (INVIMA) and the rest of the bioaccess® platform

    How ANVISA and CEP sit next to the hospital

    Use clinical-trials-brazil for the full pathway. Facts a sponsor searching this hospital needs on one screen, already published there and not re-averaged here:

    • Combined ethics + ANVISA typically 6–10 weeks under Law 14874 and RDC 837.
    • Published per-patient range $20,000–$35,000; 15+ pre-qualified sites; ANVISA is a WHO-listed authority.
    • Trial authorization and market registration are separate workstreams.
    • Under 21 CFR 812.28, foreign clinical data from Brazil is eligible for FDA submission and review when studies are conducted under ISO 14155 with proper ANVISA authorization and CEP ethics approval. Eligibility is not a guarantee of clearance or approval.
    • bioaccess®’s published Brazil cost comparison versus a typical U.S. or EU program is an experience-based estimate from work since 2010, not a formal study. Headline ~40% faster / ~30% lower per-patient figures on llms.txt and LATAM FIH benchmarks 2026 are the same class of estimate.

    We will not invent a Fundação Universitaria-only day-count. Ask for a protocol-specific calendar. A hospital email is not an ANVISA approval.

    What the Polares public file actually supports — and what it does not

    • Device: MRace Implant and Delivery System (TMVr / posterior leaflet restoration), as described on NCT06113354.
    • Sponsor: Polares Medical SA (industry). Collaborator: Polares Medical, Inc. No CRO named.
    • Sites: Fundação Universitaria de Cardiologia, Porto Alegre (this page); InCor HCFMUSP, São Paulo (existing intercept).
    • Design: interventional DEVICE_FEASIBILITY early feasibility; estimated n=10; actual start 8 April 2024; RECRUITING on the 1 September 2026 last-update snapshot.
    • Named investigators (as published): Rogerio Leite, MD (Porto Alegre contact); Roberio Leite, MD (Porto Alegre PI listing); Alexandre Abizaid, MD and Fabio Sandoli de Brito, MD (InCor).
    • Not claimed here: that the NCT named bioaccess®; that Polares Medical is a bioaccess® client; that we have Polares outcomes; that the brief summary’s “one center” line erases the second location row; that Porto Alegre is the same building as InCor, Dante Pazzanese, or PercAssist AVANXA.

    Sister São Paulo intercepts stay on their own buildings: InCor and Instituto Dante Pazzanese. Do not merge them into Porto Alegre.

    What the CRO still does after you have a hospital name

    • Regulatory-fit, not tourism. Brazil is a sourced device geography. It is not automatically the right country for every indication. bioaccess® still runs clinical trials in Colombia and the rest of the platform.
    • Protocol, IB, ICF, insurance, and the ANVISA / CEP packet.
    • Importer of record and device accountability across Porto Alegre and, if used, the InCor row.
    • ISO 14155 monitoring and the 21 CFR 812.28 narrative for a later FDA conversation.
    • Optionality if one Rio Grande do Sul room is not enough.

    The founder podcast, when a conversation needs a voice, is Global Trial Accelerators™.

    Frequently asked questions

    Can I contract Fundação Universitaria de Cardiologia directly?

    You can try. The facility can discuss investigator interest, local procedure costs, and CEP calendars. It cannot become your ANVISA applicant, importer of record, insurer, ISO 14155 monitor, or 21 CFR 812.28 packager because Polares listed Porto Alegre. Contract the CRO; let the CRO activate the site.

    Did bioaccess® run EXPLORE MRace / Polares in Brazil?

    No public bioaccess® page says so. We will not invent that claim. This page intercepts the search; it does not claim the study.

    InCor is on the same NCT. Why a separate Porto Alegre page?

    Because sponsors search the facility string they see. InCor already has incor-hcfmosp-fih. Fundação Universitaria de Cardiologia is a different building in a different city. Linking is correct. Duplicating the InCor slug is not.

    If I already have Porto Alegre, what does the CRO still do?

    Regulatory-fit (Brazil vs Colombia vs a multi-site Brazil design that already includes InCor on this NCT); the ANVISA / CEP packet; insurance; import; contracts and activation; ISO 14155 and the 812.28 narrative; optionality if one Porto Alegre room is not enough.

    Is Colombia still an option?

    Yes. bioaccess® still runs trials in Colombia. A Porto Alegre EFS search is not an instruction to abandon INVIMA.

  • Regulatory Considerations for Trial Design: An Authoritative Overview

    Regulatory Considerations for Trial Design: An Authoritative Overview

    Introduction

    In the intricate world of clinical trials, regulatory frameworks serve as the backbone of ethical and effective research practices. With pivotal authorities like the U.S. Food and Drug Administration (FDA) and the European Medicines Agency (EMA) at the helm, these regulations ensure that trials are designed and conducted with the utmost safety and integrity.

    As the landscape evolves, particularly with the introduction of decentralized clinical trials and the emphasis on patient engagement, understanding these frameworks becomes increasingly vital for researchers.

    This article delves into the complexities of regulatory compliance, the impact of digital technologies, and the ethical considerations that shape modern clinical trial design, all while highlighting best practices that can lead to successful outcomes in this competitive arena.

    Understanding Regulatory Frameworks in Clinical Trials

    Regulatory considerations for trial design represent fundamental elements established by various agencies, particularly the and the . These considerations govern the framework for the design, execution, and reporting of research studies, ensuring compliance with . Central to these regulations is , which safeguards the rights and welfare of participants, alongside the Declaration of Helsinki, which delineates ethical principles for medical research involving human subjects.

    As we approach 2025, notable updates to research regulations have emerged, particularly with the FDA’s Final Guidance on released in September 2024. This guidance underscores a growing trend towards more adaptable study designs that enhance participant access and diversity, addressing the imperative for underrepresented populations to have greater choices in onboarding and participation.

    Statistics reveal that adherence to GCP not only bolsters participant safety but also elevates the quality of data collected, which is vital for compliance submissions. Research indicates that experiments designed with in mind are 30% more likely to achieve successful results and approvals compared to those that do not adhere to these standards.

    A significant case study highlighting this is Lilly’s commitment to patient access, which has been enhancing diversity in research through since 2002. Their accelerated initiatives during the Covid-19 pandemic underscore the effectiveness of this approach in improving patient access and outcomes. Lilly’s experience illustrates the necessity for ongoing collaboration and policy updates to standardize in medical research, aligning with compliance and risk management strategies.

    In light of the increasingly saturated medical markets, as noted by , ‘Entering 2025, we observe biotech encountering essential business model challenges as medical end-markets become increasingly crowded.’ This observation emphasizes the importance of refining development journeys while adhering to legal frameworks for commercial success. Understanding these frameworks not only aids researchers in aligning their experimental designs with regulatory considerations for trial design, but also facilitates smoother approvals and compliance throughout the research lifecycle.

    At bioaccess, we provide comprehensive management services for , encompassing:

    • Feasibility assessments
    • Site selection
    • Compliance evaluations
    • Setup
    • Import permits
    • Project management
    • Reporting

    Our offerings also include thorough reviews and feedback on study documents to ensure compliance with country requirements and reporting on serious and non-serious adverse events. Our team, featuring professionals such as Ana Criado, Director of Compliance Affairs, and Katherine Ruiz, an expert in Compliance Affairs for Medical Devices and In Vitro Diagnostics, is dedicated to ensuring that your meet all compliance standards while fostering innovation and excellence in the Medtech industry across Latin America.
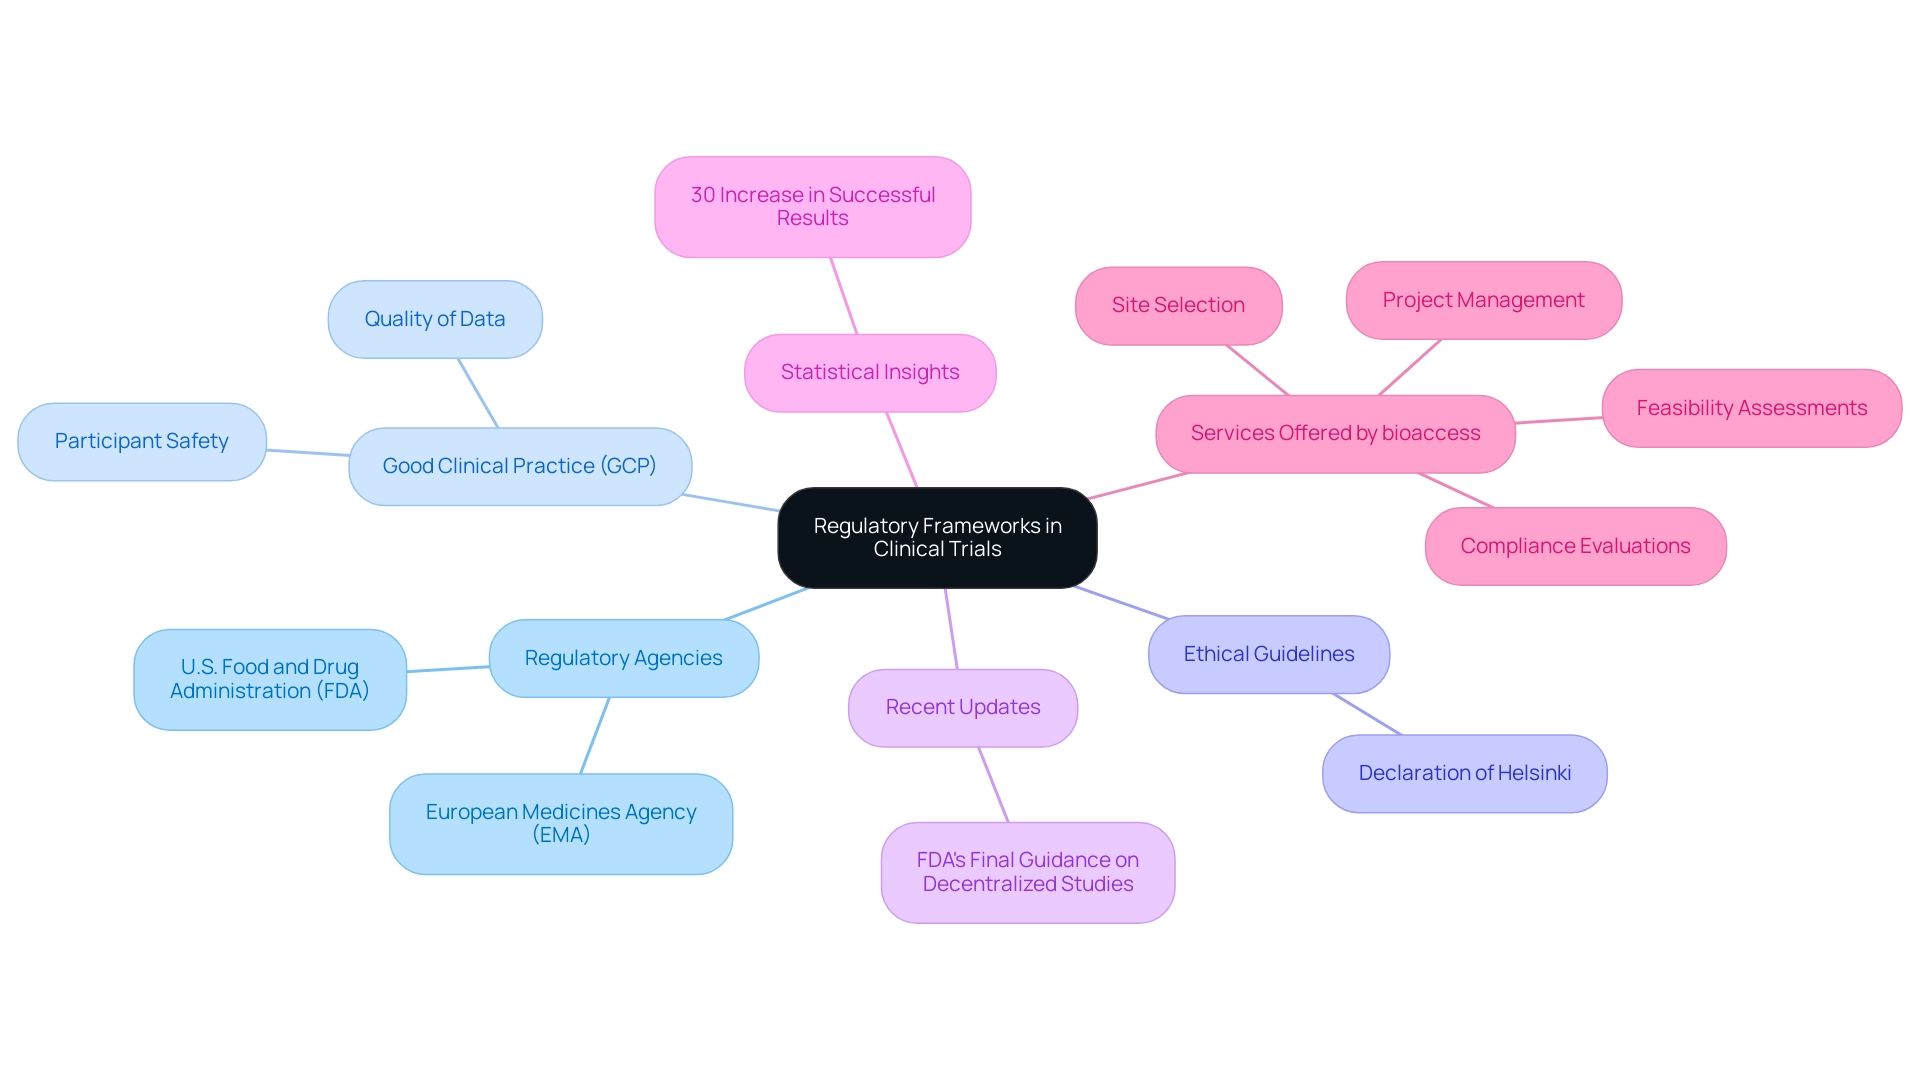
    The central node represents the overall regulatory framework, with branches illustrating various components such as agencies, practices, updates, and services.

    Key Considerations for Medical Device Trial Design

    Designing trials for medical devices necessitates a comprehensive understanding of . Central to this process is the classification of the device, which plays a crucial role in determining the appropriate . For significant risk devices, obtaining an is essential, as it permits the investigation of devices that may pose a higher risk to patients.

    As we look to 2025, successful IDE applications increasingly rely on robust , underscoring the importance of operationalizing research in-house to maintain control over data quality and integrity. The Head of Clinical Data Engineering notes, “Traditionally, data management was outsourced to our CRO vendor partners. Part of the initiative is to bring all our research in-house so that our internal teams can start working on it. They can be more hands-on, and we operationalize studies in-house and we are able to take control of our data, and we deliver for our patients with high quality.”

    Moreover, study designs must meticulously define endpoints pertinent to both device efficacy and safety. This encompasses not only primary outcomes but also secondary endpoints that may inform . Engaging with regulatory bodies early in the design process is vital, as it facilitates a clearer understanding of requirements and can significantly streamline the approval process.

    Statistics reveal that the remain challenging, with only about 5-14% of treatments completing all phases and obtaining approval. This highlights the rigorous evaluation process necessary to ensure patient safety and treatment efficacy. Additionally, the new encourages sponsors to enroll more patients from underrepresented groups, emphasizing the significance of diversity in research studies.

    As the landscape of evolves, staying informed about —including the latest IDE requirements and compliance factors—is crucial for achieving successful research outcomes.

    At bioaccess®, with over 20 years of experience in Medtech, we focus on . Our offerings include:

    • Feasibility assessments
    • Site selection
    • Compliance reviews
    • Setup
    • Import permits
    • Project management
    • Reporting

    Our expertise spans Early-Feasibility, , Pilot, Pivotal, and Post-Market Follow-Up Studies, ensuring that your medical investigations are designed and executed with the utmost precision and care. The case analysis titled ‘Success Rates and Statistics’ illustrates the rigorous nature of medical research, emphasizing the necessity for thorough evaluation processes.

    Ethical Considerations in Clinical Trial Design

    in research design are paramount, encompassing the necessity of obtaining informed consent, safeguarding participant confidentiality, and balancing risks with potential benefits. Adhering to established ethical guidelines, such as those outlined in , is essential. This report emphasizes three core principles: respect for persons, beneficence, and justice, which serve as a foundation for ethical research practices.

    At bioaccess, our comprehensive support these through meticulous feasibility studies and site selection processes. We ensure that study protocols undergo thorough , facilitating setup, start-up, and obtaining necessary import permits in accordance with country requirements. This structured approach not only adheres to ethical standards but also fosters an environment of trust and transparency, crucial for and stakeholder confidence.

    are essential to this process, as they meticulously examine research protocols to ensure compliance with ethical standards. Their oversight helps to foster an environment of trust and transparency, which is crucial for and stakeholder confidence.

    , allowing participants to make educated decisions about their involvement. Recent statistics indicate that approximately 70% of participants in clinical trials express a desire for more information regarding the risks and benefits associated with their participation. This highlights the need for researchers to prioritize effective communication during the consent process.

    Moreover, extend beyond consent. A notable case analysis examined of expanding diabetic retinopathy screening through artificial intelligence (AI) without ensuring access to necessary treatments. Participants in this study underscored the importance of addressing alongside screening initiatives to prevent ethical dilemmas and ensure that AI interventions genuinely benefit underserved populations.

    One participant remarked, “If the AI is efficacious, it’s an accurate diagnostic, but is this cost-effective if it costs a million dollars to run?”

    Incorporating these from the outset not only enhances the integrity of research studies but also promotes compliance and trust among participants and stakeholders alike. As the landscape of medical research evolves, remains crucial for the advancement of medical technology. Furthermore, the fragility of moral progress in research ethics necessitates strong commitments from international codes and professional societies, as highlighted in discussions from The Lancet Global Health Series on Clinical Trials.

    By utilizing our knowledge in project management and reporting, bioaccess guarantees that ethical standards are maintained throughout the process, ultimately aiding in job creation, economic growth, and healthcare enhancement in local economies.

    The Role of Patient Engagement in Trial Design

    has emerged as a cornerstone of efficient research design, significantly influencing both recruitment and retention rates. By actively engaging patients in discussions about study objectives, design, and outcomes, researchers can obtain invaluable insights that enhance the study’s relevance and acceptability. In 2025, the incorporation of patient viewpoints is expected to further elevate the quality of medical studies, as will enhance disease diagnosis and treatment assessment.

    The collaboration between bioaccess™ and Caribbean Health Group aims to position Barranquilla as a leading hub for medical studies in Latin America, supported by Colombia’s Minister of Health. This initiative not only transforms the but also underscores the critical role of in achieving successful study outcomes. encompass diverse approaches, including:

    • Focus groups
    • Surveys
    • The integration of patient advocates in the planning process

    These methodologies not only foster a sense of ownership among participants but also ensure that the study design aligns with patient needs and expectations. For example, that studies integrating patient feedback during the design phase experience enhanced and reduced dropout rates, ultimately leading to more robust data collection.

    Statistics reveal that studies employing can witness soar by up to 30%, highlighting the necessity of prioritizing patient perspectives. Additionally, as sponsors increasingly seek to insource data management processes for improved control and transparency, the significance of patient engagement in shaping study outcomes becomes even more pronounced. This trend emphasizes the imperative for researchers to maintain direct access to live data, ensuring that is not only acknowledged but also effectively woven into the study process.

    Moreover, the partnership with GlobalCare Clinical Trials has demonstrated the potential for remarkable improvements in research operations, achieving over a 50% reduction in recruitment time and 95% retention rates. This case analysis illustrates the need for early-stage drug developers to factor in commercial outcomes within their strategies. By focusing on patient participation, researchers can refine their study designs, which must also accommodate , paving the way for in an increasingly competitive landscape.

    As Peng Lu, chief medical officer of Dutch biotech Pharvaris, articulated, “Harmonizing the use of specific outcomes and outcome measures for trials will aid in the development of guidelines and future indirect comparisons among interventions.” This statement emphasizes the significance of patient viewpoints in study design, further reinforcing the case for heightened .

    Ensuring Compliance with Regulatory Standards

    Ensuring adherence to regulatory standards is essential in research design and involves , necessitating a deep understanding of applicable laws and guidelines, including and local regulations. At bioaccess, our extensive encompass:

    • Feasibility assessments
    • Site selection
    • Setup
    • Import permits
    • Project oversight
    • Reporting

    This includes the review and feedback on research documents to meet country requirements, all of which are critical for maintaining compliance throughout the procedure.

    Key strategies for maintaining compliance include the creation of a robust , which serves as the foundation for all project activities. Regular training for research staff is crucial; studies indicate that effective training can significantly enhance compliance rates. .

    Implementing is another essential strategy. This involves performing regular audits and monitoring to identify areas for enhancement and ensure compliance with regulatory requirements during the study. The integration of diverse data sources is increasingly vital for modern research methods, necessitating streamlined data flows that can enhance compliance and operational efficiency.

    By , further highlighting the significance of technology in ensuring compliance.

    Moreover, maintaining open communication with regulatory authorities can facilitate timely feedback, allowing for the proactive resolution of potential compliance issues before they escalate. Innovations in medical studies are also simplifying the site experience, with user-friendly systems designed to enhance data entry efficiency and lessen the load on research personnel.

    A recent case analysis highlighted by the Tufts Center for the Study of Drug Development illustrates the . These technologies have been shown to reduce study timelines by up to 30% and costs by as much as 20%, while also improving patient recruitment and retention. As noted by the Head of Clinical Data Engineering, “Traditionally, data management was outsourced to our CRO vendor partners. Part of the initiative is to bring all our research in-house so that our internal teams can start working on it. They can be more hands-on, and we operationalize studies in-house, allowing us to take control of our data and deliver high quality for our patients.” Such advancements not only streamline operations but also help maintain adherence to standards.

    As we approach 2025, the focus on will continue to evolve, emphasizing the use of technology and training to improve the overall quality of research studies. By adopting these strategies, organizations can ensure that their testing protocols align with while also contributing to the successful advancement of medical technologies.
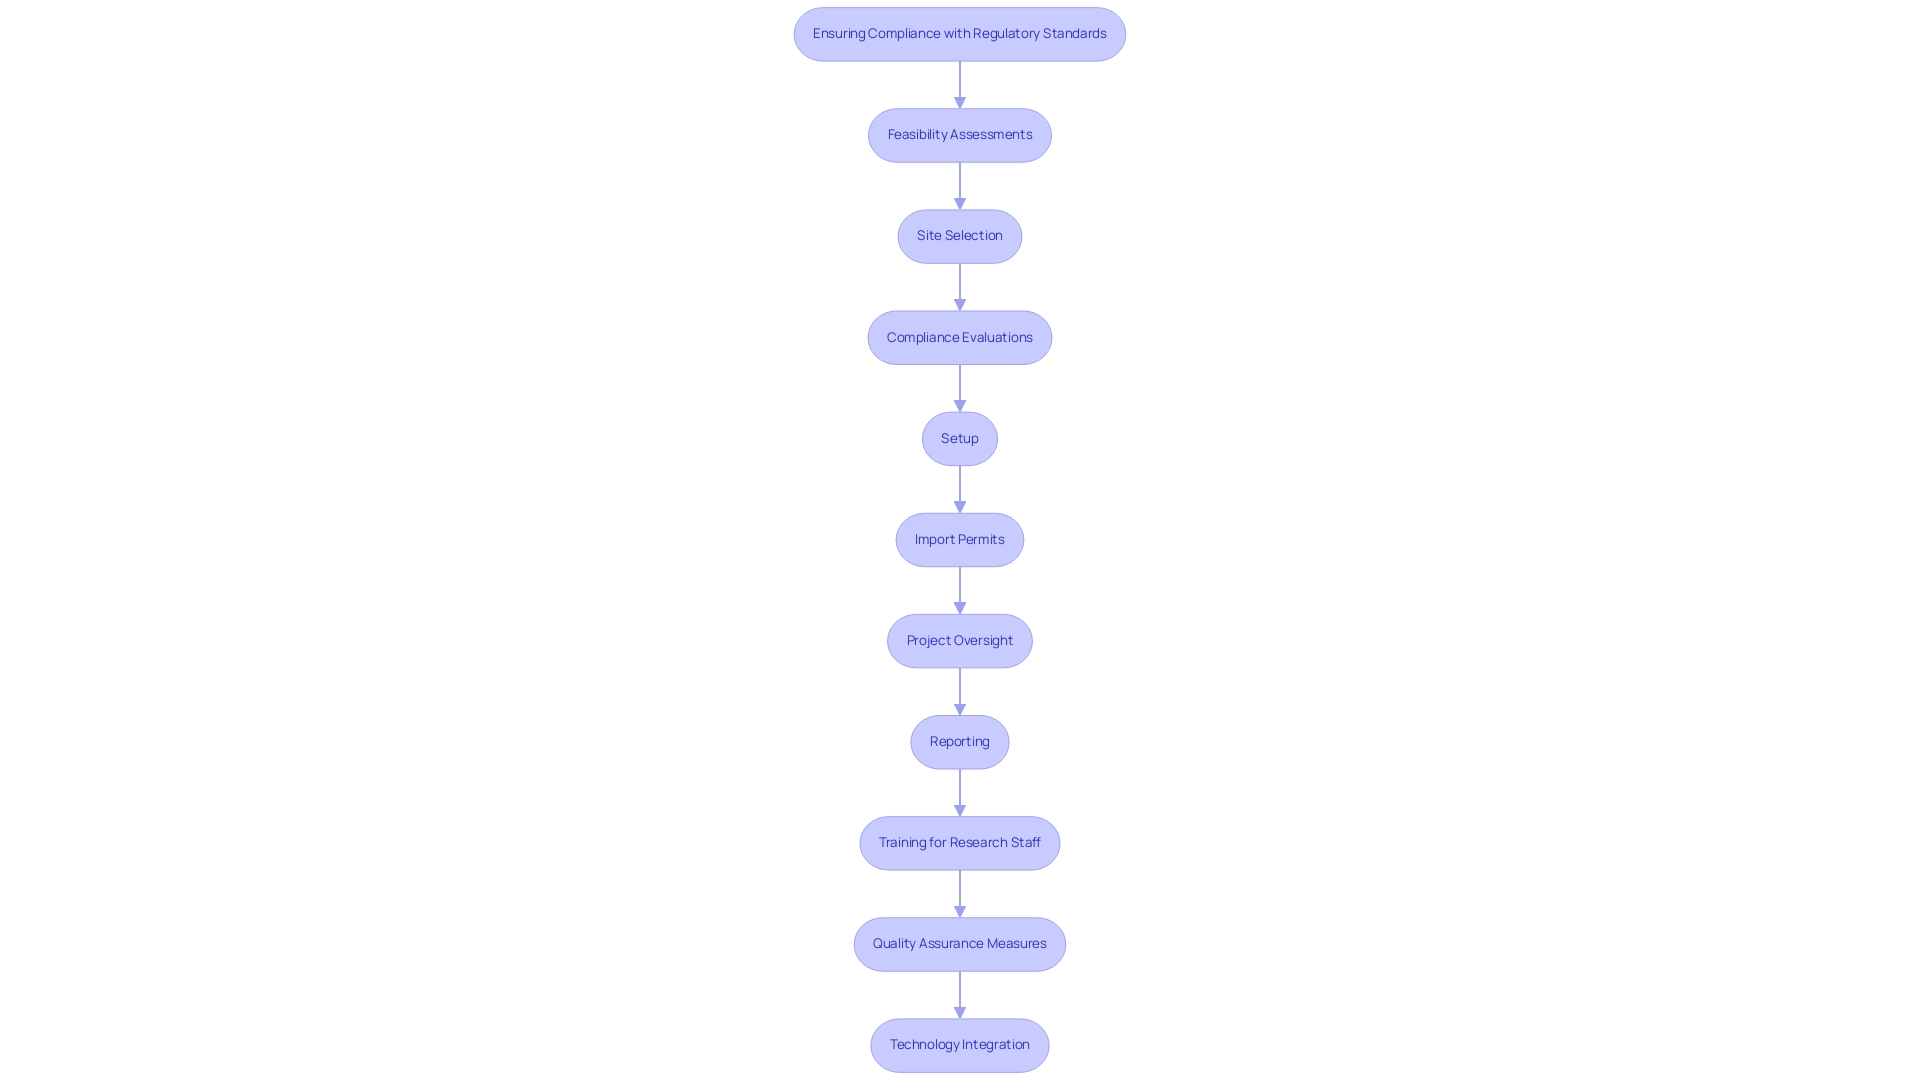
    Each box represents a key strategy or service in the compliance process, with arrows indicating the flow and relationship between strategies.

    Impact of Digital Technologies on Regulatory Considerations

    , paving new avenues for data collection, , and remote participation. By 2025, the integration of these technologies has significantly enhanced and patient engagement. Recent statistics reveal that 45% of data from major research studies is now entered on the same day as the visit date, illustrating the speed and accuracy that digital tools can deliver.

    However, the swift adoption of digital technologies also introduces , particularly regarding , security, and integrity. Regulatory organizations are actively updating their guidelines to address these challenges, underscoring the necessity for robust and clearly defined procedures for employing digital tools in research studies. This evolution is evident as sponsors increasingly assume control of , transitioning from outsourcing to insourcing to improve quality and oversight.

    As the Head of Clinical Data Engineering remarked, “Traditionally, data management was outsourced to our CRO vendor partners. Part of the initiative is to bring all our research in-house so that our internal teams can start working on it. They can be more hands-on, and we operationalize studies in-house, allowing us to take control of our data and deliver high quality for our patients.”

    Moreover, the rise of exemplifies how technology can enhance patient retention and reduce costs compared to conventional methods. The concept of is gaining traction as a means to boost patient involvement and facilitate remote participation and data collection. These studies not only demonstrate significant advantages in patient engagement and cost-effectiveness but also serve as a practical illustration of how digital technologies can transform medical research.

    As researchers navigate this evolving landscape, staying informed about the related to digital technologies is paramount. This knowledge will empower them to ensure compliance while fully leveraging the benefits that these innovations can provide to their research. Furthermore, will , further highlighting the importance of integrating digital technologies into study design.

    At bioaccess, our comprehensive research study management services encompass:

    1. Feasibility studies
    2. Site selection
    3. Compliance assessments
    4. Study setup
    5. Import permits
    6. Project management
    7. Reporting

    Compliance assessments are vital in ensuring that all aspects of the experiment align with the latest legal standards, emphasizing the as these regulations evolve. With experts like Katherine Ruiz overseeing our operations for medical devices and in vitro diagnostics in Colombia, we are well-equipped to navigate the complexities of research studies while ensuring compliance with and adherence to changing rules.

    This holistic approach not only elevates the quality of our studies but also contributes to local economies through job creation, economic growth, and improved healthcare outcomes.
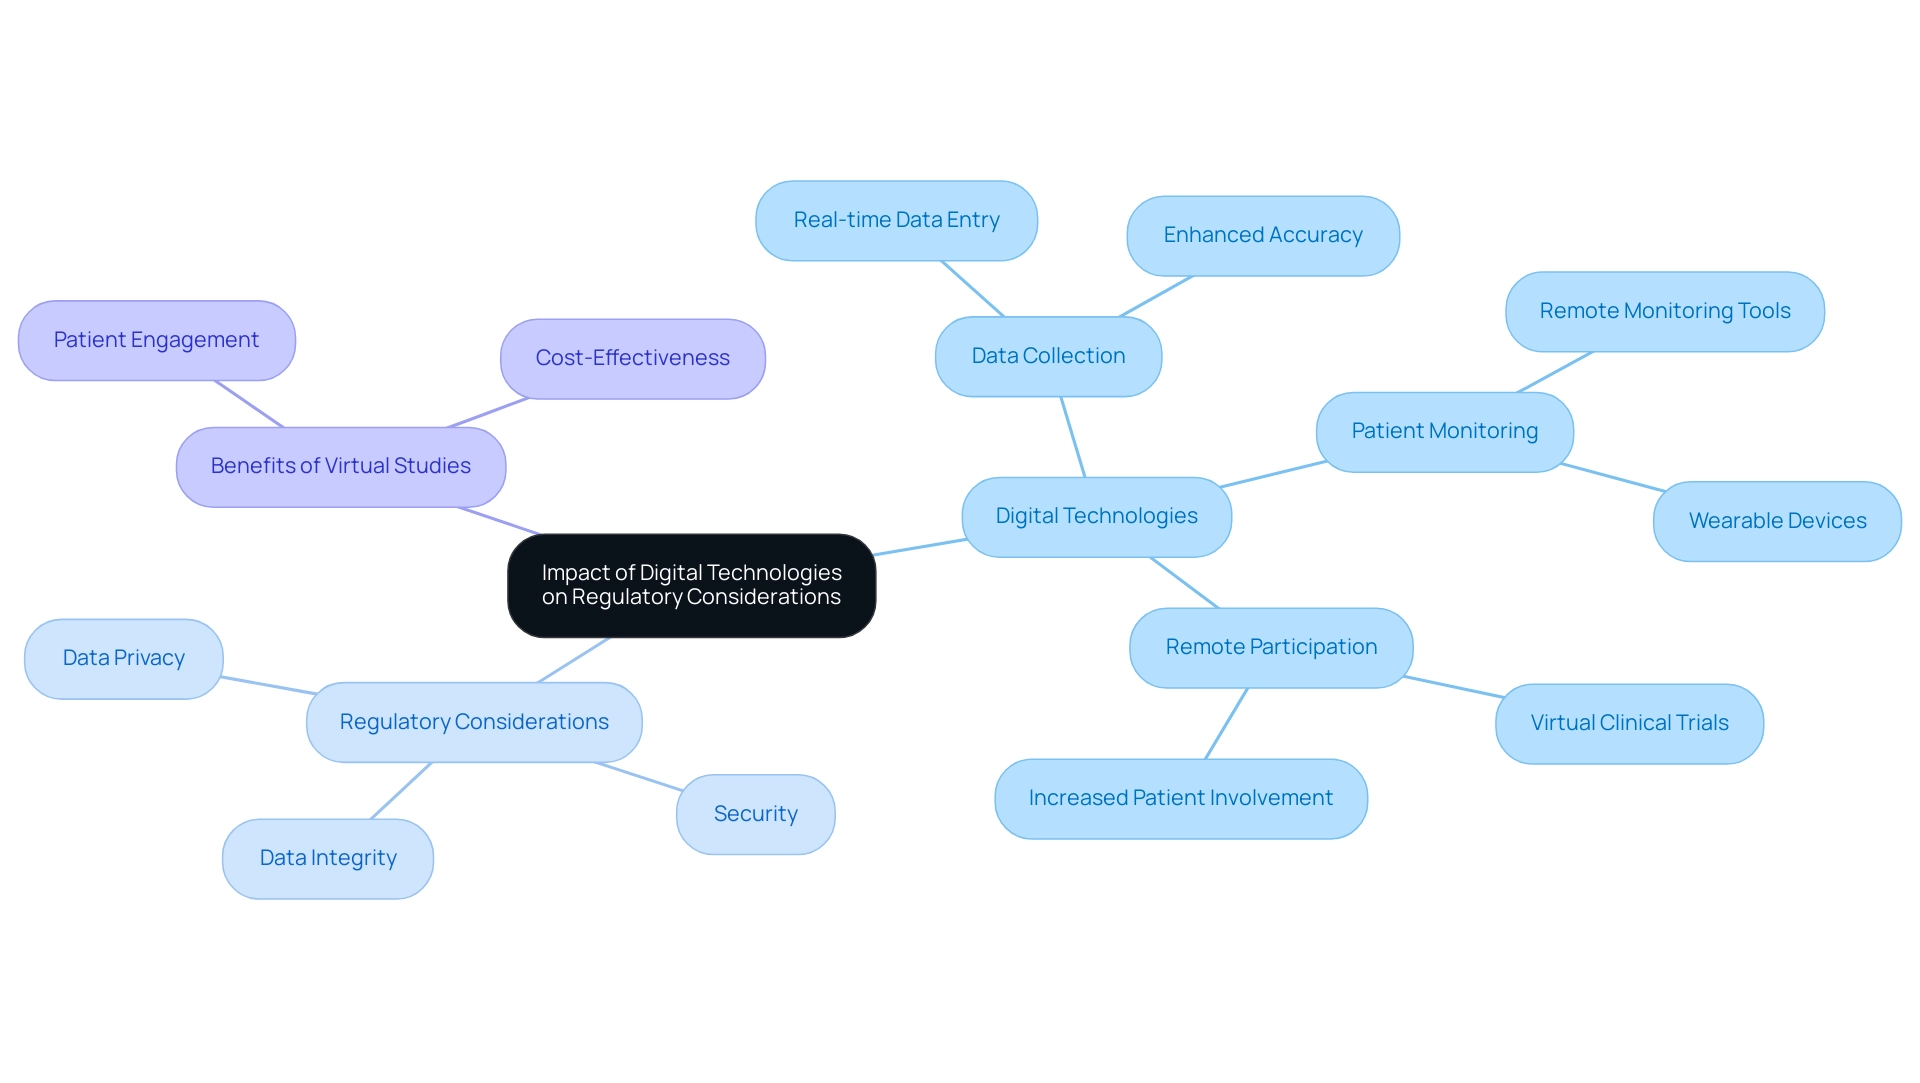
    Each branch represents a key topic: Digital Technologies (green), Regulatory Considerations (blue), and Benefits of Virtual Studies (orange), with sub-branches detailing specific aspects under each category.

    Regional Regulatory Challenges in Clinical Trials

    Carrying out research studies in Latin America requires that encompasses , varying requirements across nations, language barriers, and differing ethical norms. In 2025, researchers face significant , particularly due to the necessity of adapting to country-specific regulations, which can differ markedly from one nation to another. For instance, Colombia has introduced incentives such as to attract more research projects, transforming it into an increasingly appealing destination for medical studies in the region.

    Notably, ReGelTec’s Early Feasibility Study on HYDRAFIL™ for addressing chronic low back pain in Barranquilla exemplifies the potential for successful , bolstered by local partnerships like that between bioaccess and Caribbean Health Group, which aim to establish the region as a prominent center for clinical research in Latin America.

    To effectively navigate these intricacies, it is essential for researchers to engage who possess a comprehensive understanding of the specific to each nation involved in the study. Building robust relationships with local regulatory authorities is crucial, as these considerations can facilitate smoother approval processes and enhance compliance, ultimately reducing the time to market for innovative medical devices. The collaboration between ‘GlobalCare Clinical Trials’ and bioaccess has demonstrated for research in Colombia, achieving over a 50% reduction in recruitment duration and 95% retention rates, showcasing the efficacy of thorough management services for research projects, including:

    1. Feasibility assessments
    2. Site selection
    3. Compliance evaluations
    4. Setup
    5. Import permits
    6. Project management
    7. Reporting

    Furthermore, of medical recommendations, complicating informed consent processes. This is particularly relevant in a region where literacy rates, such as Chile’s at 95.7%, underscore the necessity for clear communication. As Saisuman Revankar aptly states, “Clear communication is critical for navigating the complexities of clinical studies, ensuring that all parties remain aligned.”

    Customizing study designs to accommodate these regional differences is vital, especially considering the . This approach not only enhances participant recruitment and retention but also leads to more successful outcomes.

    As the governance landscape continues to evolve, addressing challenges such as insufficient preparation and underrepresentation of patients will be essential in meeting the across diverse populations in Latin America. Policies that concentrate on these issues will improve the overall effectiveness of trials in the region, supported by the oversight of INVIMA, Colombia’s National Food and Drug Surveillance Institute, which plays a critical role in as a Level 4 health authority by PAHO/WHO.
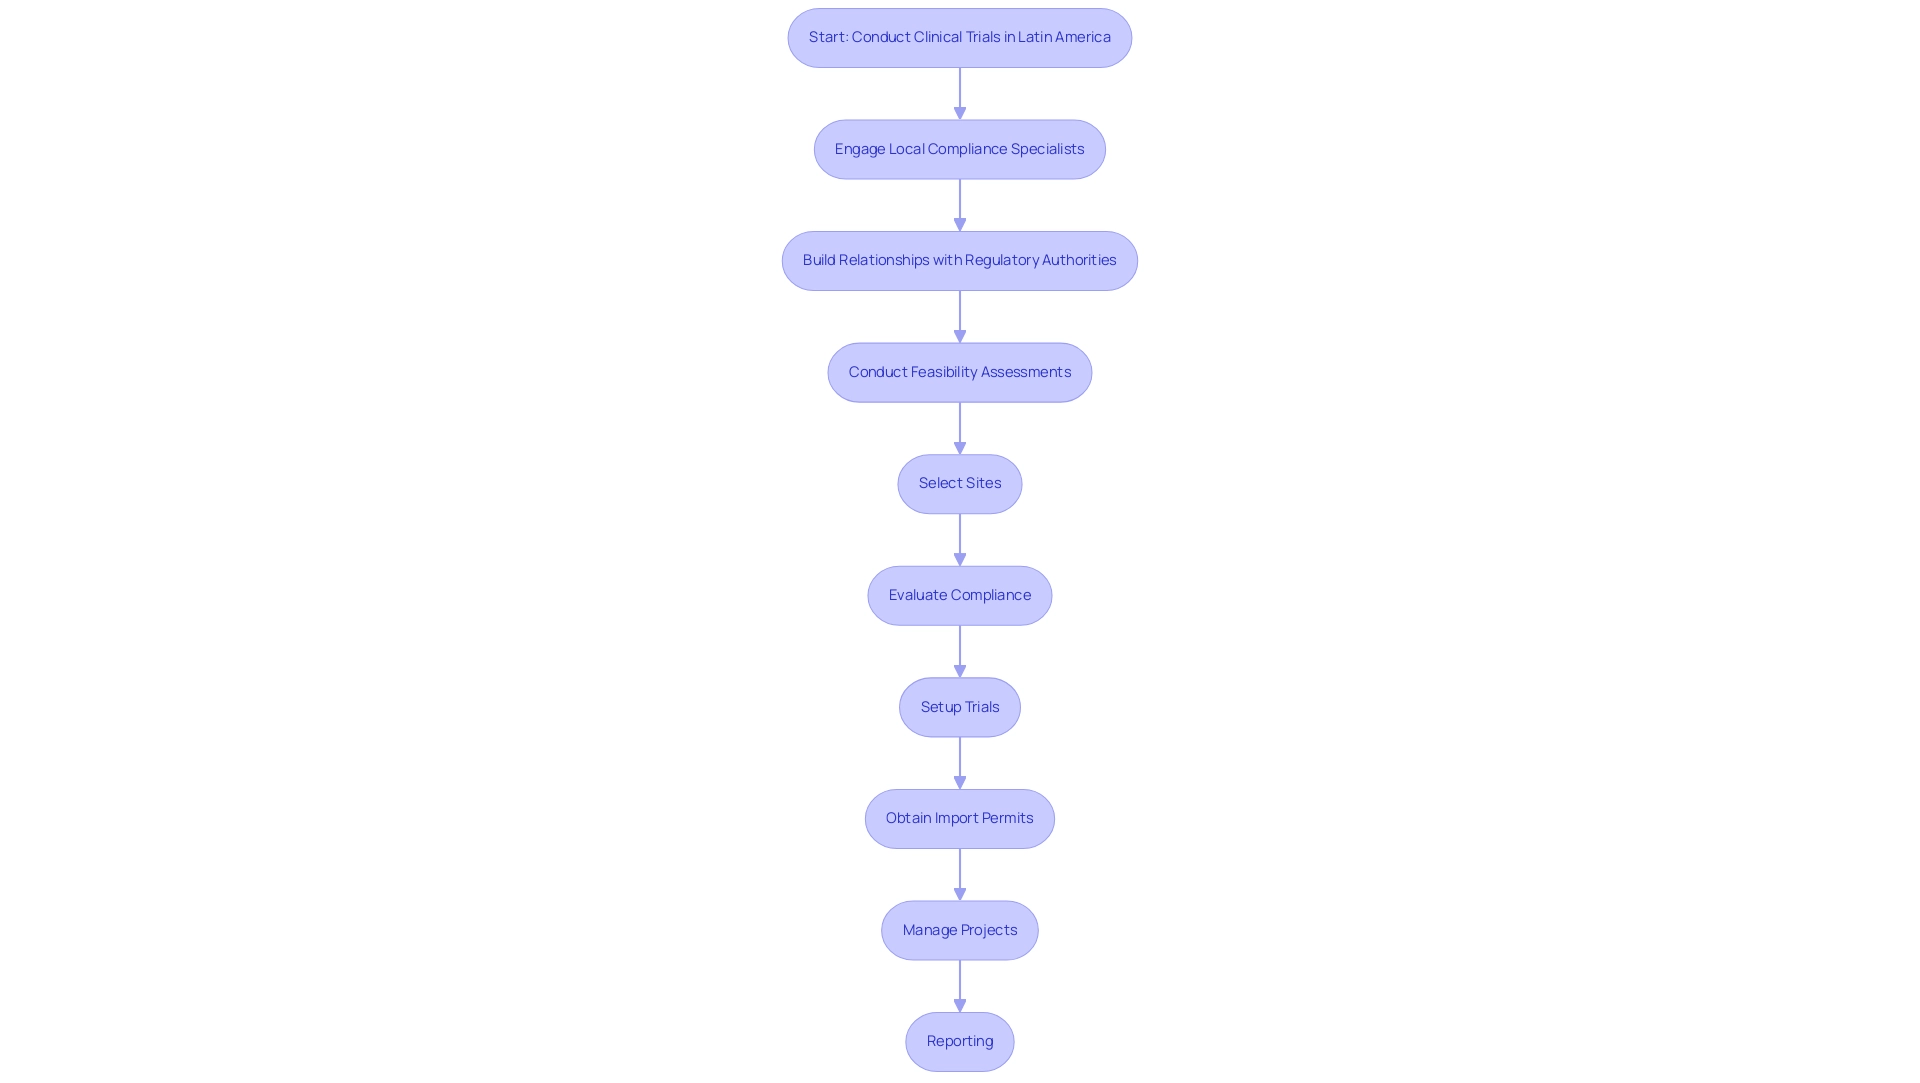
    Each box represents a step in the clinical trial process, and arrows indicate the flow from one step to the next.

    Best Practices for Navigating Regulatory Landscapes

    Navigating for trial design in medical research requires a strategic approach, particularly as the sector evolves in 2025. Key :

    • Staying informed, which is crucial for to remain updated on current regulations and guidelines. This foundational knowledge is essential for ensuring compliance and adapting to any changes that may arise.
    • Engaging with oversight authorities early in the study design process can significantly streamline the approval process. This proactive engagement fosters a clearer understanding of expectations and requirements, ultimately enhancing the likelihood of success.
    • Fostering strong partnerships among stakeholders—including sponsors, oversight bodies, and clinical sites—can strengthen , leading to more effective study designs. Collaborative efforts enable the sharing of insights and resources, which is vital for navigating complex compliance environments.
    • Developing comprehensive training initiatives for research staff ensures that all team members are well-versed in their roles and responsibilities regarding compliance. This not only enhances adherence to regulations but also promotes a culture of accountability within the research team.
    • Continuous evaluation and updating of study protocols in response to are vital practices. This diligence helps maintain compliance and adapt to new requirements, thereby safeguarding the integrity of the trial.

    In 2025, research sponsors are expected to adhere to a . This emphasis on will aid in developing guidelines and facilitating indirect comparisons among interventions. Such a shift underscores the importance of standardizing patient-reported outcomes and biomarker identification, as highlighted in recent discussions among experts. This standardization is crucial for enhancing the assessment of drug effectiveness and safety, especially in intricate therapeutic fields, as demonstrated in the case study titled ‘Measuring Outcomes,’ which emphasizes these elements in research.

    Additionally, as the biotech landscape becomes increasingly crowded, early-stage developers must concentrate on commercial outcomes in their strategies. Max Baumann, Head of Execution at Tree Hill Partners, noted, “We expect continued focus on optimizing the development journeys of assets to achieve not only an approval-enabling endpoint but to qualify for commercial success.” Insights from industry leaders highlight the necessity of enhancing development journeys to reach endpoints that facilitate approval and position products for commercial success.

    By following these best practices and promoting collaboration, research teams can improve their compliance and risk management strategies, incorporating , ultimately aiding in the success of their studies.

    At bioaccess, our service offerings encompass:

    • Feasibility studies
    • Site selection
    • Trial preparation
    • Import permits
    • Project management
    • Thorough reporting on study status and adverse occurrences

    We ensure that your trials are executed effectively and in accordance with all legal requirements. Our methodologies focus on integrating the latest regulatory insights and best practices, particularly regarding , to support your .

    Conclusion

    Regulatory frameworks are paramount to the integrity and success of clinical trials, ensuring adherence to stringent ethical standards and the safeguarding of participant rights. As the landscape evolves—particularly with advancements in decentralized trials and digital technologies—it is essential for researchers to remain informed and compliant with the latest regulations. The integration of patient engagement strategies alongside robust data management practices enhances the quality and relevance of trial outcomes, illustrating that the journey to successful approvals transcends mere regulatory compliance; it is also about cultivating trust and transparency.

    As we approach 2025, the focus on ethical considerations, compliance with Good Clinical Practice (GCP), and proactive engagement with regulatory authorities will be critical. Insights drawn from case studies, including community-based trials and the application of artificial intelligence, highlight the necessity of adapting to the unique challenges posed by diverse regulatory environments, particularly in regions such as Latin America.

    Ultimately, navigating the complexities of clinical trial regulations demands a collaborative approach among stakeholders, continuous education, and a steadfast commitment to ethical research practices. By embracing these principles and leveraging cutting-edge technological advancements, researchers can not only bolster their compliance and operational efficiency but also contribute to the broader advancement of medical technologies and improved patient outcomes in an ever-evolving landscape.

    Frequently Asked Questions

    What are the key regulatory agencies involved in trial design?

    The key regulatory agencies involved in trial design are the U.S. Food and Drug Administration (FDA) and the European Medicines Agency (EMA).

    What is Good Clinical Practice (GCP)?

    Good Clinical Practice (GCP) is a set of guidelines that ensures the rights and welfare of participants in clinical trials, as well as the integrity of the data collected.

    What is the Declaration of Helsinki?

    The Declaration of Helsinki is a set of ethical principles for medical research involving human subjects, aimed at ensuring ethical standards are upheld in clinical trials.

    What notable updates to research regulations were highlighted for 2025?

    Notable updates include the FDA’s Final Guidance on decentralized studies, which promotes more adaptable study designs to enhance participant access and diversity.

    How does adherence to GCP impact research studies?

    Adherence to GCP enhances participant safety and improves the quality of data collected, making studies designed with GCP principles 30% more likely to achieve successful results and approvals.

    Can you provide an example of a company enhancing diversity in research?

    Lilly has been enhancing diversity in research through community-based studies since 2002, with accelerated initiatives during the Covid-19 pandemic to improve patient access and outcomes.

    What challenges are anticipated in the biotech industry as we approach 2025?

    The biotech industry is expected to face essential business model challenges due to increasingly crowded medical end-markets, necessitating refined development journeys and adherence to legal frameworks.

    What services does bioaccess provide for medical experiments?

    Bioaccess provides comprehensive management services including feasibility assessments, site selection, compliance evaluations, setup, import permits, project management, and reporting.

    What is an Investigational Device Exemption (IDE)?

    An Investigational Device Exemption (IDE) is a regulatory approval that allows the investigation of significant risk devices that may pose a higher risk to patients.

    Why is data management important for successful IDE applications?

    Robust data management practices are crucial for successful IDE applications as they ensure control over data quality and integrity, which is vital for maintaining high standards in research.

    What is the significance of engaging with regulatory bodies early in the trial design process?

    Engaging with regulatory bodies early helps clarify requirements and can significantly streamline the approval process for clinical trials.

    What does the new FDA draft guidance on Diversity Action Plans emphasize?

    The new FDA draft guidance emphasizes the importance of enrolling more patients from underrepresented groups in clinical research studies to enhance diversity.

    What types of studies does bioaccess specialize in?

    Bioaccess specializes in Early-Feasibility, First-In-Human, Pilot, Pivotal, and Post-Market Follow-Up Studies in the Medtech sector.

    List of Sources

    1. Understanding Regulatory Frameworks in Clinical Trials
      • novotech-cro.com (https://novotech-cro.com/articles/navigating-future-clinical-trials-expert-insights-2025)

      • clinicalresearchnewsonline.com (https://clinicalresearchnewsonline.com/news/2025/01/07/trendspotting-predictions-for-clinical-research-in-2025)
      • statnews.com (https://statnews.com/sponsor/2024/11/12/the-path-to-more-inclusive-and-accessible-clinical-trials-is-clear-what-stands-in-the-way)
    2. Key Considerations for Medical Device Trial Design
      • appliedclinicaltrialsonline.com (https://appliedclinicaltrialsonline.com/view/considerations-medical-device-trials)
      • veeva.com (https://veeva.com/2025-clinical-data-trend-report)
      • about.cmrad.com (https://about.cmrad.com/articles/clinical-trial-phases-complete-guide-to-all-4-stages)
    3. Ethical Considerations in Clinical Trial Design
      • who.int (https://who.int/news-room/events/detail/2025/03/28/default-calendar/shaping-the-future-of-clinical-trials–building-an-ethical–efficient–and-equitable-ecosystem)
      • statnews.com (https://statnews.com/2025/02/16/usaid-shutdown-stop-work-order-clinical-trials-ethics)
      • jamanetwork.com (https://jamanetwork.com/journals/jamanetworkopen/fullarticle/2823294)
    4. The Role of Patient Engagement in Trial Design
      • veeva.com (https://veeva.com/2025-clinical-data-trend-report)
      • novotech-cro.com (https://novotech-cro.com/articles/navigating-future-clinical-trials-expert-insights-2025)
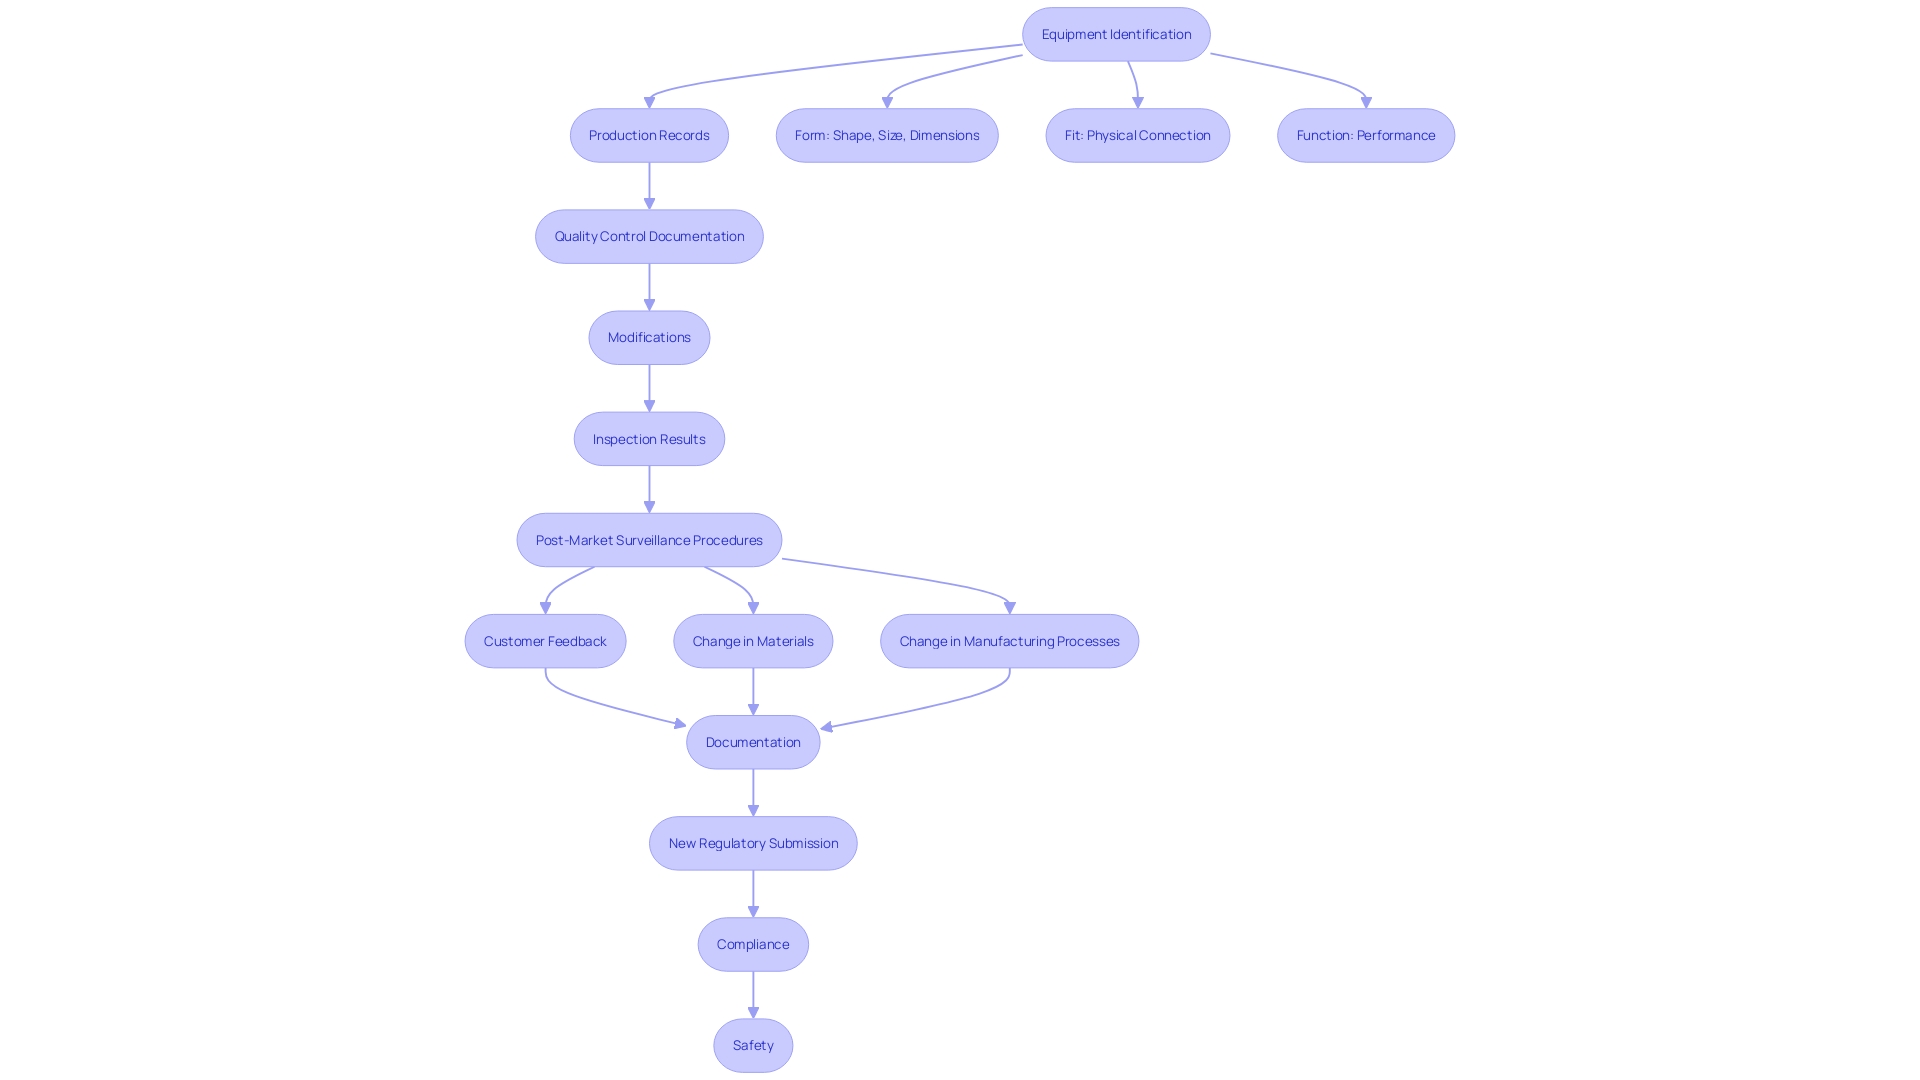
    5. Ensuring Compliance with Regulatory Standards
      • acldigital.com (https://acldigital.com/blogs/future-clinical-data-research-management-trends-and-predictions-2025)
      • wcgclinical.com (https://wcgclinical.com/insights/clinical-trial-trends-insights-2025)
      • veeva.com (https://veeva.com/2025-clinical-data-trend-report)
    6. Impact of Digital Technologies on Regulatory Considerations
      • veeva.com (https://veeva.com/2025-clinical-data-trend-report)
      • novotech-cro.com (https://novotech-cro.com/articles/navigating-future-clinical-trials-expert-insights-2025)
    7. Regional Regulatory Challenges in Clinical Trials
      • Clinical Trials in Latin America (https://languageconnections.com/clinical-trials-in-latin-america)
      • Best Practices for Latin America CRO Selection: Ensuring Quality and Efficiency in Clinical Trials | bioaccess® (https://blog.bioaccessla.com/best-practices-for-latin-america-cro-selection-ensuring-quality-and-efficiency-in-clinical-trials)
      • globalforum.diaglobal.org (https://globalforum.diaglobal.org/issue/february-2025/regulatory-systems-trends-and-innovations-in-latin-america-and-the-caribbean)
    8. Best Practices for Navigating Regulatory Landscapes
      • novotech-cro.com (https://novotech-cro.com/articles/navigating-future-clinical-trials-expert-insights-2025)