Blog

  • CE Certification: Essential Steps for Clinical Research Success

    CE Certification: Essential Steps for Clinical Research Success

    Introduction

    CE marking serves as a symbol of compliance with stringent EU safety and health standards, playing a pivotal role in the landscape of clinical research, particularly for medical devices and pharmaceuticals. This certification not only ensures product safety and efficacy but also enhances market access and consumer trust, making it an essential focus for companies aiming to succeed in Europe.

    However, the recent tightening of regulations, including the Medical Device Regulation (MDR), has rendered the path to obtaining CE certification increasingly complex. This complexity raises critical questions about how organizations can navigate these challenges while maintaining ethical standards and ensuring patient safety.

    Define CE Certification and Its Importance in Clinical Research

    CE marking, or , serves as a crucial symbol for items sold within the European Economic Area (EEA), signifying adherence to EU safety, health, and environmental protection standards. In the realm of medical research, particularly concerning and pharmaceuticals, is indispensable as it guarantees that products are safe for use and effective for their intended purposes. This accreditation not only facilitates but also bolsters , making it an essential step for companies aiming to introduce their offerings in Europe. Without CE approval, products cannot be marketed within the EU, underscoring its vital role in the research environment.

    Recent developments, including the implementation of (MDR), have further tightened the requirements for CE approval, ensuring that undergo rigorous assessments to enhance patient protection. For instance, the MDR mandates that producers provide empirical evidence from at least one well-structured research trial, particularly for higher-risk devices, thereby highlighting the significance of in maintaining . The requirement for producers of class III devices to disclose critical performance and risk information in a ‘Summary of performance outcomes’ document further illustrates the stringent criteria established by the MDR.

    Additionally, the introduction of the improves traceability and monitoring of in the EU, contributing to post-market surveillance and overall device safety.

    At bioaccess®, our comprehensive encompass:

    Our unwavering commitment to data protection ensures that client information is managed with the highest level of care. Our Director of Regulatory Affairs, Ana Criado, possesses extensive expertise in biomedical engineering and regulatory compliance, enabling our clients to navigate the complexities of with confidence.

    Case studies demonstrate that companies achieving not only gain credibility but also experience enhanced market access, ultimately leading to increased consumer trust and improved health outcomes.

    Outline the Requirements and Process for Obtaining CE Certification

    Obtaining involves several critical steps that ensure compliance with EU regulations:

    1. : Identify your medical device’s classification according to EU regulations, as this will dictate the specific CE marking requirements.
    2. Compile : Gather comprehensive documentation demonstrating compliance with relevant directives, including design specifications, risk assessments, and evaluation reports. This technical file must be maintained for at least 10 years from the last manufacturing date.
    3. : Perform a medical assessment to gather evidence of the item’s safety and performance, which may involve trials or reviewing existing data. Leveraging the expertise of a specialized team, such as bioaccess®, can enhance the , ensuring thorough compliance reviews and effective management of and .
    4. Select a Notified Body: For higher-risk devices, choose a Notified Body to evaluate your item’s conformity with EU regulations. This independent organization plays a crucial role in the certification CE process.
    5. : Prepare and sign a , certifying that your item meets all applicable EU requirements. This document must be available to authorities at the EU point of entry and should include the date of issue, the signer’s name, signature, and work title.
    6. : Once all requirements are satisfied, to your item, allowing it to be marketed within the European Economic Area (EEA). The CE mark must be easily visible and legible, with a minimum height of 5 mm.
    7. Maintain Compliance: Continuously monitor and ensure adherence to EU regulations, as changes may influence your item’s status. Routine follow-up evaluations are necessary for higher-risk items to preserve their validity. Utilizing comprehensive project management and reporting services can facilitate ongoing compliance monitoring.

    The typical duration to achieve CE approval can vary from 10 working days for simpler items to 16 to 18 months for more complicated devices, based on their classification and the manufacturer’s quality management system (QMS) condition. Successful certification CE approvals in biopharma underscore the significance of comprehensive documentation and compliance with the latest requirements, which are crucial for effectively navigating the regulatory landscape. Unlabeled items encounter dangers like customs seizure and market oversight inquiries, highlighting the significance of .
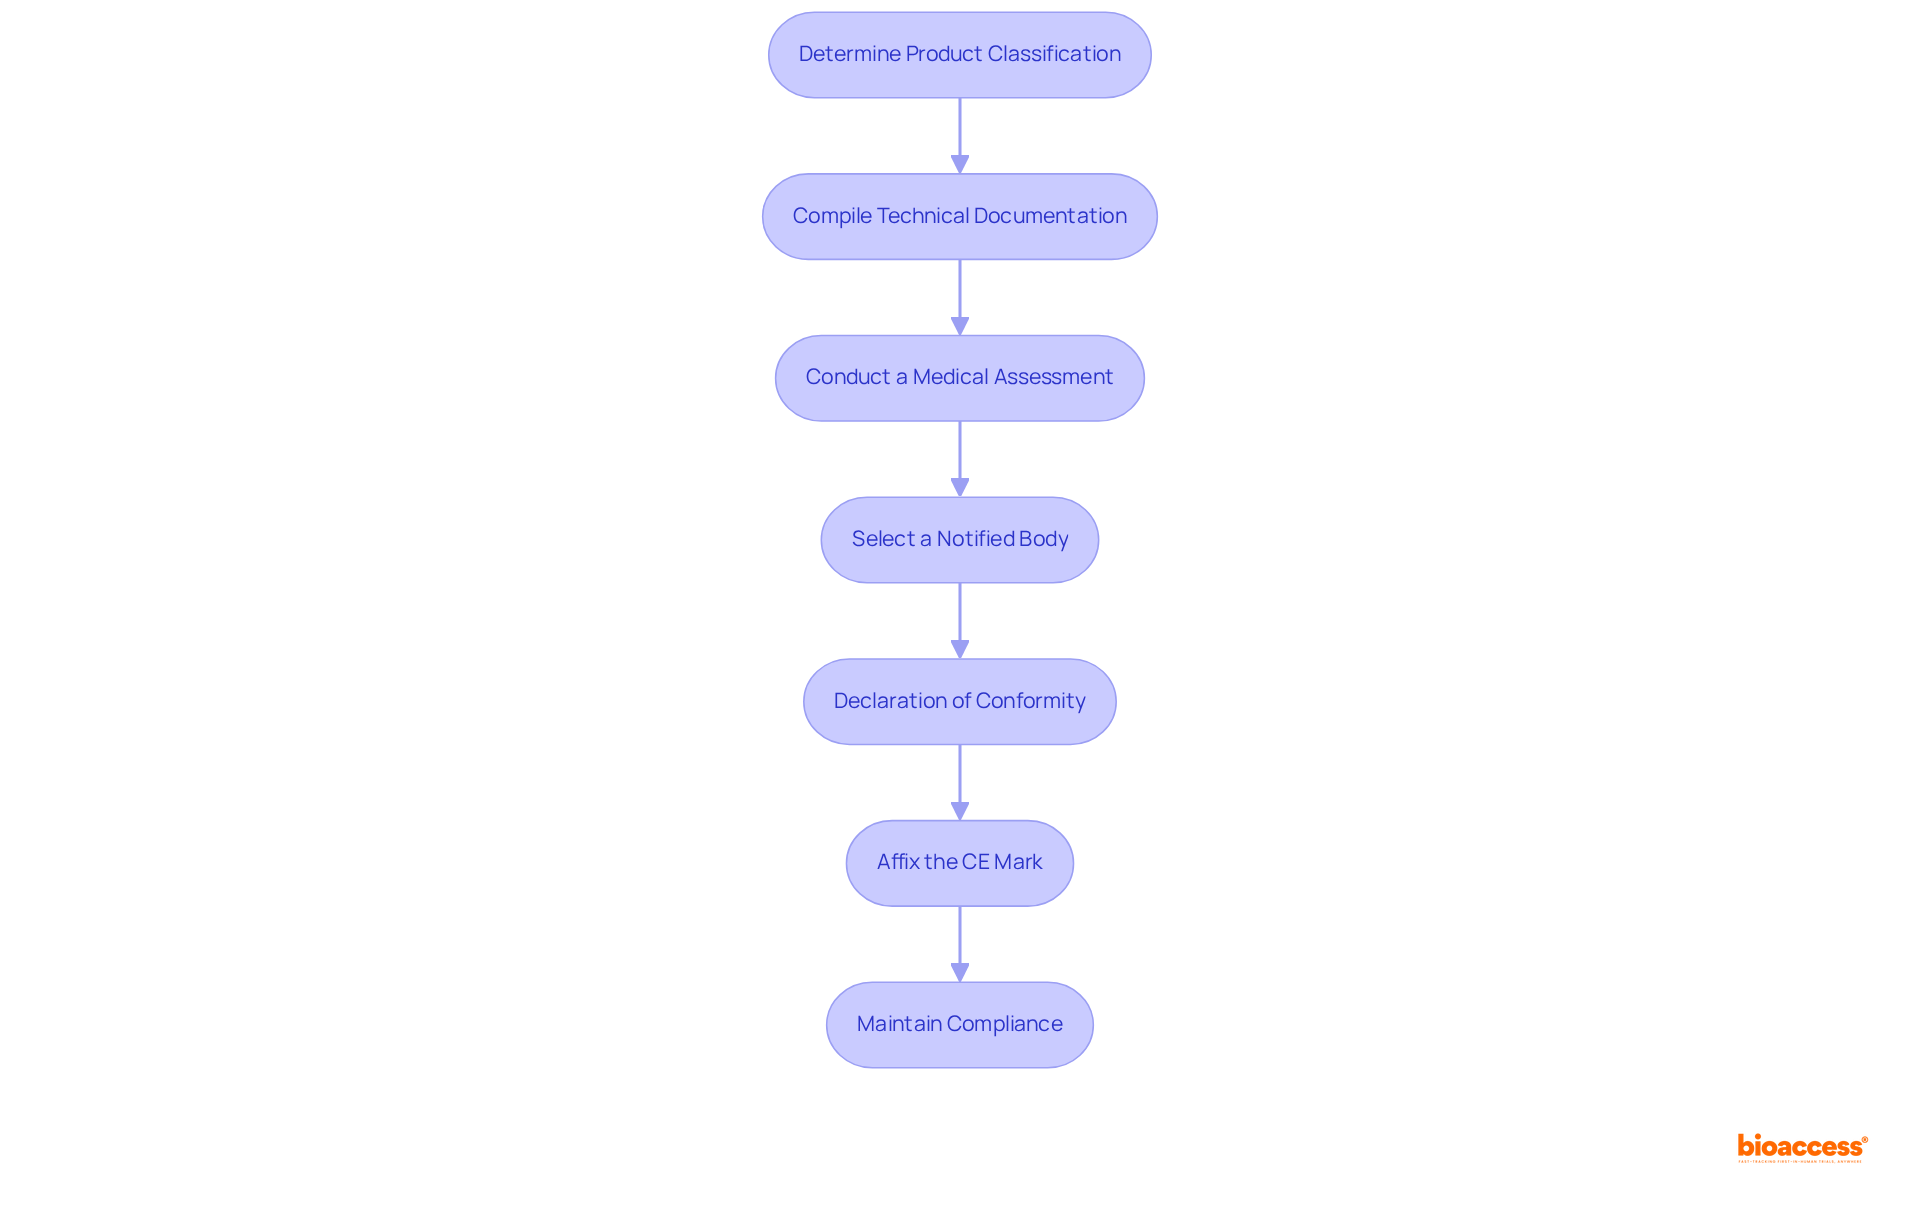
    Each box represents a step in the journey to obtaining CE certification for medical devices — follow the arrows to see how each step leads to the next.

    Discuss Compliance and Ethical Considerations in CE Certification

    Adhering to CE certification transcends mere ; it fundamentally encompasses . Companies must ensure the security and efficacy of their products through rigorous testing and evaluation. Key ethical considerations include:

    • : Participants in clinical trials must be thoroughly informed about the study’s nature and voluntarily provide their consent. Studies indicate that while 96% of participants understand their right to withdraw, remains alarmingly low, with only 7% grasping the associated risks. This gap underscores the necessity for to ensure participants are genuinely informed.
    • : Prioritizing is a fundamental ethical obligation throughout the research process. that implementing protective measures can identify serious concerns an average of 18 months earlier than conventional methods, significantly enhancing patient safeguarding.
    • Transparency: Maintaining openness in reporting trial results, including both positive and negative outcomes, is vital for upholding research integrity. A systematic review revealed that many patients overestimate their understanding of trial information, emphasizing the importance of .
    • : Adhering to all applicable regulations and guidelines not only ensures legal compliance but also builds trust among stakeholders. Organizations that embrace can navigate the complexities of compliance more effectively.

    By addressing these ethical considerations, companies can bolster their credibility and contribute to the advancement of medical knowledge while ensuring patient safety. The incorporation of is not merely a regulatory requirement but a commitment to the well-being of participants and the integrity of clinical research.
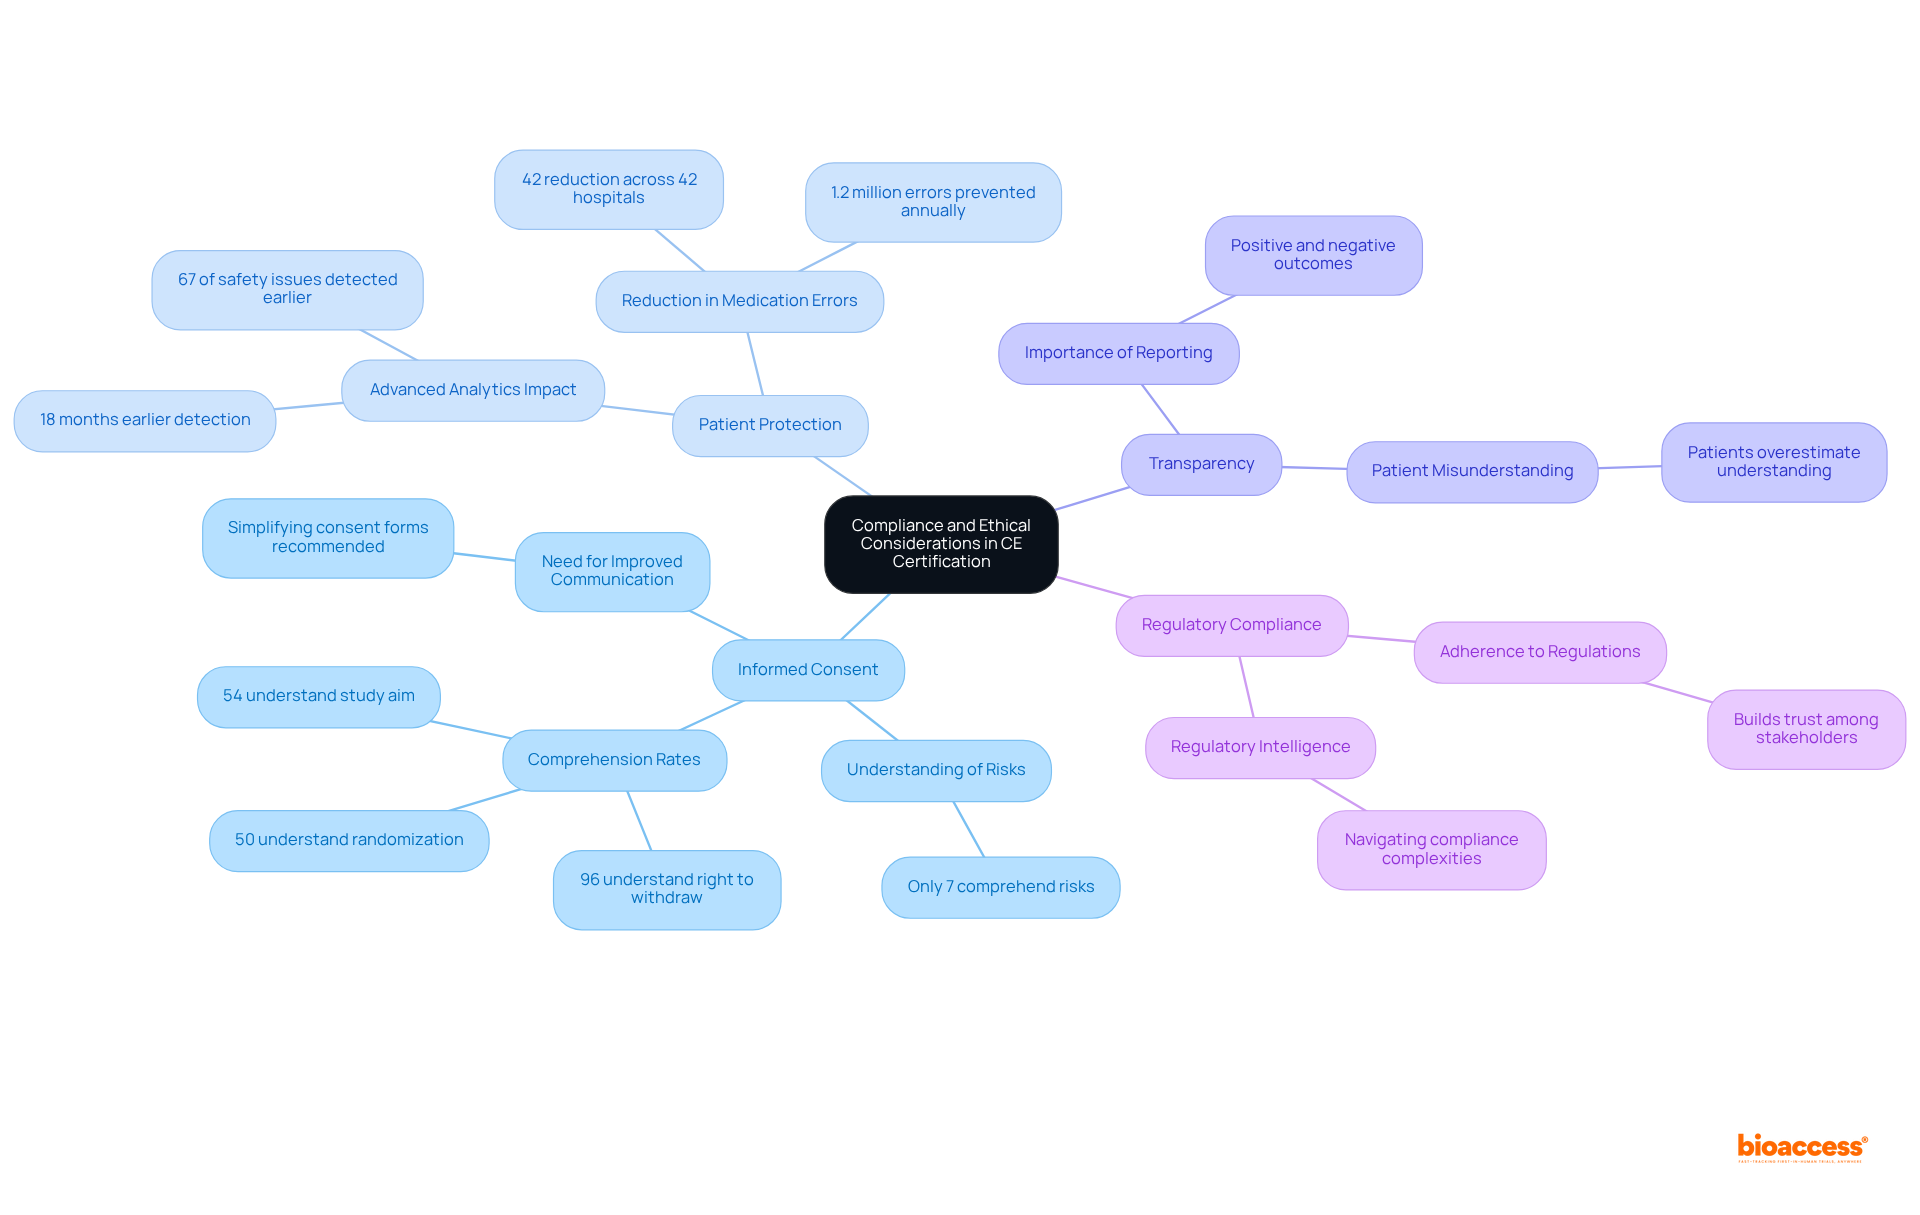
    The central node represents the main theme. Each branch highlights a key ethical consideration, with further details branching out from each. This layout shows how these ethical factors interconnect and contribute to the overall goal of patient safety and research integrity.

    Examine the Role of CE Certification in Market Access and Commercialization

    is essential for the and commercialization of medical devices and pharmaceuticals, serving as a passport that enables products to be marketed freely within the European Economic Area (EEA). This certification significantly expands the potential customer base and provides several key advantages:

    • : Products bearing are recognized as compliant with EU regulations, enhancing their marketability and fostering consumer trust. The security standard of CE-marked items is rated at 8.31 on a scale of 1 to 10, reinforcing their reliability in the market. Achieving certification offers a distinct over non-certified products, signaling a commitment to quality and safety that influences purchasing decisions.
    • : streamlines the entry process into various European markets, eliminating the need for additional national approvals and accelerating time to market.
    • : It ensures that products meet essential , which is vital for . Companies with CE marking reported an average competitiveness rating of 8.5, compared to 9.65 for the best-in-class in Serbia, underscoring the significance of compliance in enhancing market position.

    In summary, extends beyond being a mere regulatory requirement; it is a strategic asset that profoundly impacts a company’s success in the competitive European market landscape. The positive influence of certification on sales growth and market access is evident, as organizations that align their strategies with CE marking requirements are better positioned to succeed.
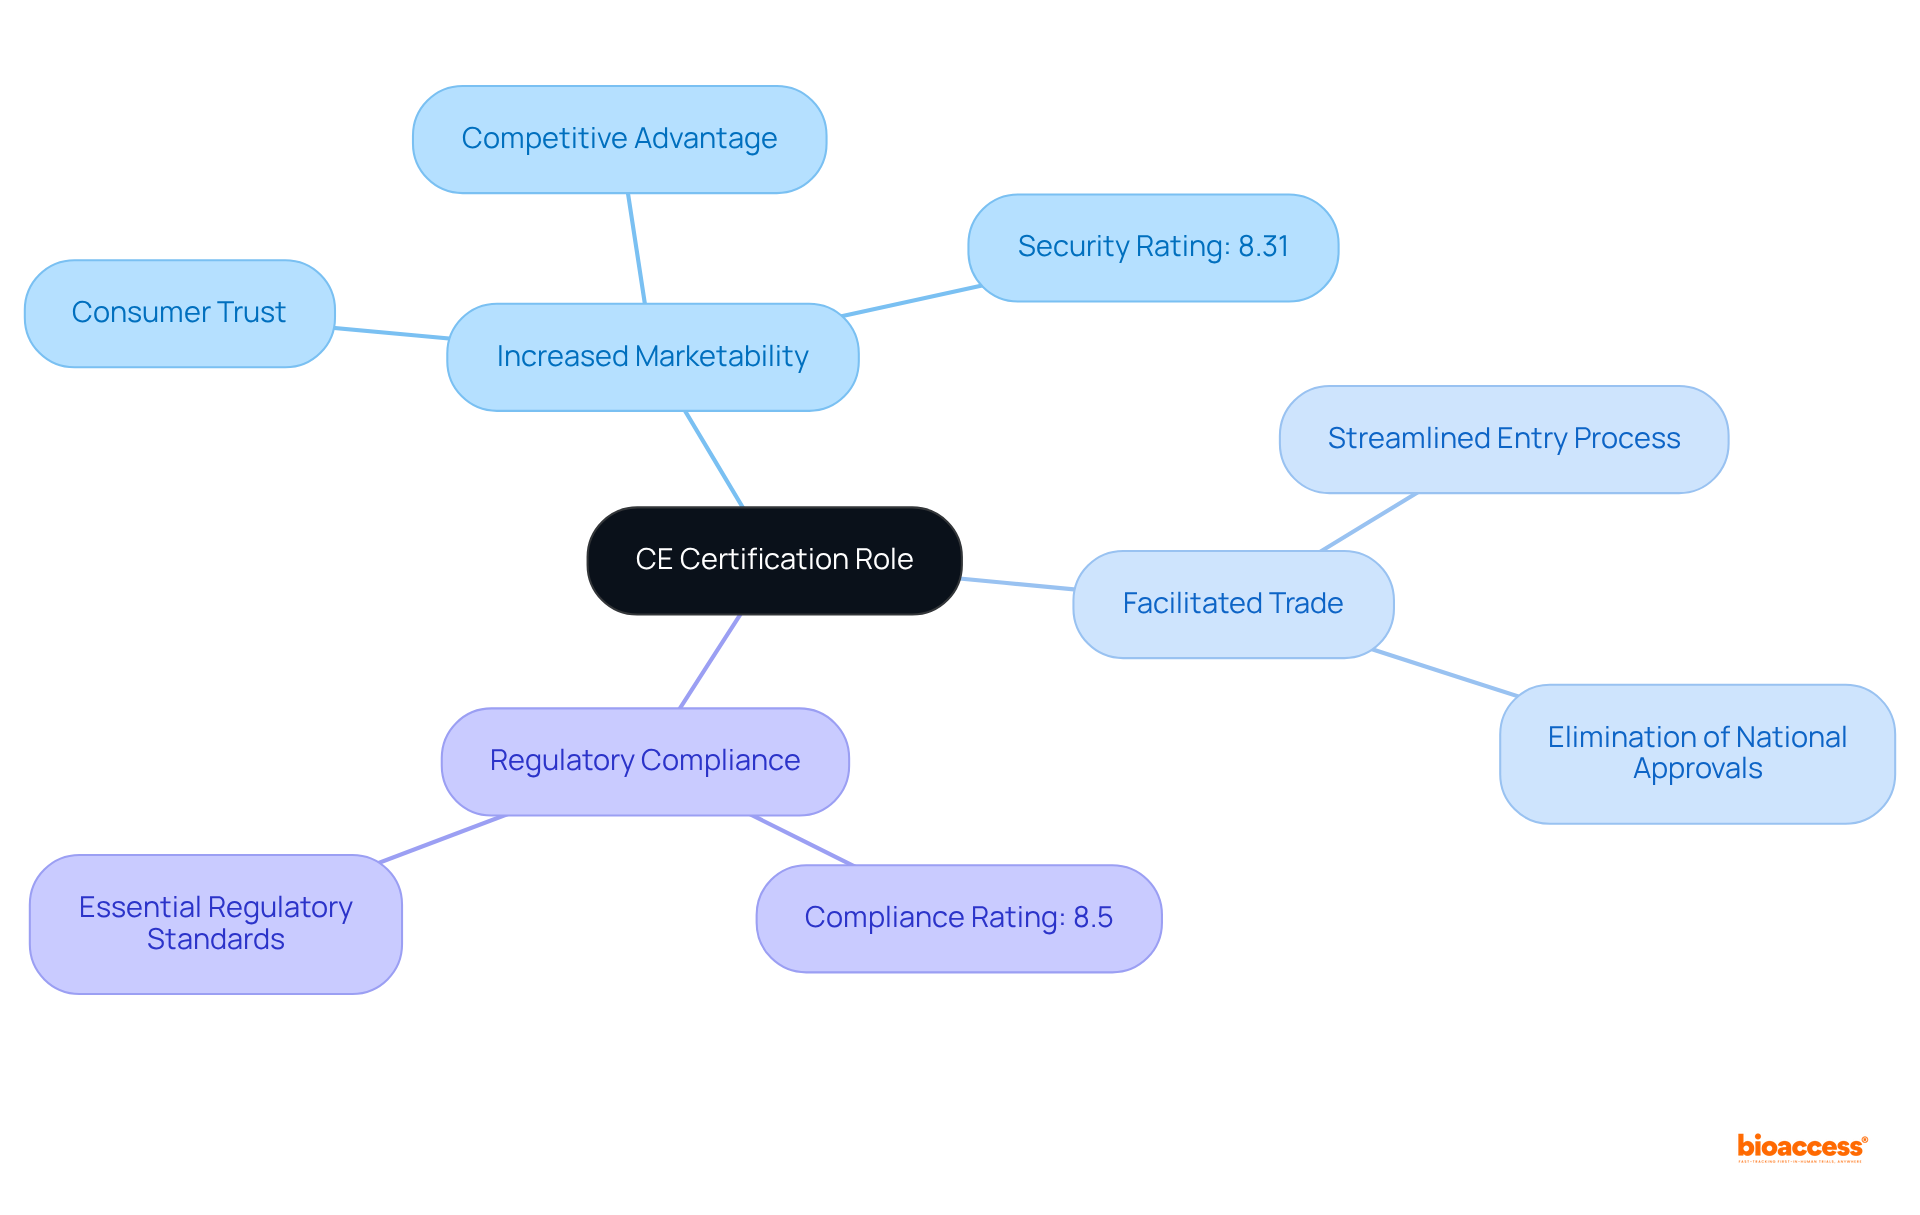
    The central node represents CE certification, while branches illustrate its key benefits. Each benefit can be explored further to understand how it contributes to market access and commercialization.

    Conclusion

    CE certification stands as a pivotal element in the landscape of clinical research, particularly for medical devices and pharmaceuticals. It signifies compliance with EU safety and health standards and serves as a key to market access within the European Economic Area (EEA). The rigorous process of obtaining CE certification ensures that products are safe and effective, fostering consumer confidence and enhancing the credibility of companies in a competitive market.

    Throughout this article, critical steps for achieving CE certification have been outlined, including:

    1. Determining product classification
    2. Compiling technical documentation
    3. Conducting medical assessments
    4. Maintaining ongoing compliance

    The discussion also emphasizes the ethical dimensions of CE certification, such as informed consent, patient protection, and transparency, which are essential for building trust and ensuring the integrity of clinical research. Moreover, the role of CE certification in facilitating market entry and commercialization is highlighted, demonstrating its impact on a company’s growth and competitive positioning.

    Reflecting on the significance of CE certification, it becomes clear that adherence to these standards is not merely a regulatory obligation but a commitment to quality, safety, and ethical responsibility. Companies are encouraged to prioritize CE certification as a strategic asset that enhances marketability and contributes to improved health outcomes for patients. By embracing the rigorous processes and ethical considerations associated with CE certification, organizations can effectively navigate the complexities of the regulatory landscape and position themselves for success in the ever-evolving field of clinical research.

    Frequently Asked Questions

    What is CE certification?

    CE certification, or Conformité Européenne marking, is a symbol that indicates a product’s adherence to EU safety, health, and environmental protection standards, allowing it to be sold within the European Economic Area (EEA).

    Why is CE certification important in clinical research?

    CE certification is crucial in clinical research as it ensures that medical devices and pharmaceuticals are safe for use and effective for their intended purposes. It facilitates market entry and enhances consumer confidence.

    What happens if a product does not have CE approval?

    Without CE approval, products cannot be marketed within the EU, making certification essential for companies aiming to introduce their offerings in Europe.

    How have recent regulations affected CE certification requirements?

    Recent regulations, particularly the Medical Device Regulation (MDR), have tightened CE approval requirements, mandating rigorous assessments and empirical evidence from structured research trials, especially for higher-risk devices.

    What is the significance of the ‘Summary of performance outcomes’ document?

    The ‘Summary of performance outcomes’ document is required for class III devices and must disclose critical performance and risk information, reflecting the stringent criteria established by the MDR.

    What is the Unique Device Identification (UDI) system?

    The UDI system is an initiative that improves traceability and monitoring of medical devices in the EU, contributing to post-market surveillance and overall device safety.

    What services does bioaccess® provide in relation to clinical trials?

    bioaccess® offers comprehensive clinical trial management services, including feasibility studies, site selection, compliance reviews, trial setup, import permits, project management, and reporting.

    Who is the Director of Regulatory Affairs at bioaccess® and what expertise do they have?

    The Director of Regulatory Affairs at bioaccess® is Ana Criado, who has extensive expertise in biomedical engineering and regulatory compliance, helping clients navigate the complexities of CE certification.

    What benefits do companies experience after achieving CE certification?

    Companies that achieve CE certification gain credibility, enhanced market access, increased consumer trust, and improved health outcomes.

    List of Sources

    1. Define CE Certification and Its Importance in Clinical Research
      • mdpi.com (https://mdpi.com/2076-3417/14/20/9304)
      • medtecheurope.org (https://medtecheurope.org/medical-devices-regulation-ce-marking-regime)
      • emergobyul.com (https://emergobyul.com/services/european-ce-marking-strategy-medical-devices)
      • pmc.ncbi.nlm.nih.gov (https://pmc.ncbi.nlm.nih.gov/articles/PMC8647605)
      • hmedicalinc.com (https://hmedicalinc.com/2025/01/28/the-importance-of-ce-marking-in-medical-devices)
    2. Outline the Requirements and Process for Obtaining CE Certification
      • blog.clevercompliance.io (https://blog.clevercompliance.io/ce-marking/the-ce-marking-process-explained-in-7-steps)
      • knowledgebase.nexpcb.com (https://knowledgebase.nexpcb.com/articles/ce)
      • tradecommissioner.gc.ca (https://tradecommissioner.gc.ca/en/market-industry-info/search-country-region/region/canada-europe-export/six-steps-ce-marketing-goods-european-union.html)
      • simplerqms.com (https://simplerqms.com/ce-marking-for-medical-devices)
      • business.gov.nl (https://business.gov.nl/products-services-and-innovation/product-safety/step-by-step-plan-for-arranging-ce-marking)
    3. Discuss Compliance and Ethical Considerations in CE Certification
      • pmc.ncbi.nlm.nih.gov (https://pmc.ncbi.nlm.nih.gov/articles/PMC10760836)
      • numberanalytics.com (https://numberanalytics.com/blog/5-critical-stats-patient-safety-analytics-pharma-healthcare)
      • gh.bmj.com (https://gh.bmj.com/content/8/5/e012007)
      • news-medical.net (https://news-medical.net/life-sciences/Consent-in-Clinical-Trials.aspx)
      • trialsjournal.biomedcentral.com (https://trialsjournal.biomedcentral.com/articles/10.1186/s13063-020-04969-w)
    4. Examine the Role of CE Certification in Market Access and Commercialization
      • Medical Devices Market Size, Share, Global Growth Report 2034 (https://fortunebusinessinsights.com/industry-reports/medical-devices-market-100085)
      • straitsresearch.com (https://straitsresearch.com/report/medical-device-testing-and-certification-market)
      • researchgate.net (https://researchgate.net/publication/291848265_The_impact_of_CE_marking_on_the_competitiveness_of_enterprises)
      • media.market.us (https://media.market.us/medical-devices-statistics)
      • movley.com (https://movley.com/blog/understanding-conformite-europeenne-a-complete-tutorial-on-ce-marking)

  • Medical Device Regulatory Strategy: How to Sequence FDA and LATAM Approvals

    Medical Device Regulatory Strategy: How to Sequence FDA and LATAM Approvals

    WordPress Category: Navigating Regulatory Landscapes in Latin America


    Most MedTech founders treat regulatory strategy as a linear problem: get FDA clearance, then figure out the rest. That framing costs time and money. The smarter approach treats your FDA pathway and your first-in-human data strategy as a single sequenced plan — not two separate workstreams running independently.

    If you're a startup CEO or CSO sitting on an IDE approval or approaching a Series A close, this article walks through how to think about that sequence, why Latin American regulatory jurisdictions belong in your plan, and how to structure the evidence you generate so it holds up at every step.


    Why Sequencing Matters More Than Speed Alone

    Speed is the obvious reason founders look at Latin America. Ethics and regulatory approvals in jurisdictions like Panama, El Salvador, Chile, and the Dominican Republic take 30 to 90 days, compared to 6 to 12 months in the US or EU. That gap alone can determine whether you have first human data before your next funding round closes — or after it.

    But speed without regulatory alignment creates its own problem. If your LATAM trial isn't structured to FDA's foreign clinical data requirements from day one, the data you generate may not be usable for your IDE, 510(k), De Novo, or PMA submission. You'll have spent the time and the budget, and FDA will ask for more.

    The goal isn't just to run a trial fast. It's to generate a submission-ready evidence package that bridges directly to your next FDA step.


    Understand Your FDA Pathway First

    Before you select a country, a site, or a protocol design, you need to know which FDA pathway your device is targeting. That determination shapes everything downstream.

    The Five Core Pathways

    IDE (Investigational Device Exemption): Required for significant risk devices entering US clinical investigation. LATAM FIH data can support the IDE application or inform the protocol for the US pivotal study that follows.

    510(k): Clearance through substantial equivalence to a predicate device. First-in-human data from a LATAM feasibility study can strengthen a 510(k) by demonstrating clinical performance in a controlled setting.

    De Novo: For novel low-to-moderate risk devices with no predicate. The clinical evidence standard is higher than 510(k), and a well-documented LATAM FIH study can serve as the primary clinical evidence basis.

    PMA (Premarket Approval): For high-risk Class III devices. LATAM FIH and early feasibility data typically forms the foundation for a subsequent US pivotal study. The quality of your early data directly affects how FDA evaluates your pivotal protocol.

    HDE (Humanitarian Device Exemption): For rare disease devices affecting fewer than 8,000 US patients annually. Early clinical data from a LATAM feasibility study can satisfy the probable benefit standard.

    Knowing your pathway tells you what evidence FDA will need — which tells you what your LATAM protocol must produce.


    The FDA Framework That Makes LATAM Data Count

    Under FDA 21 CFR 812.28 (see FDA's official page on Acceptance of Data from Clinical Investigations for Medical Devices), data from foreign clinical investigations of medical devices may be accepted in support of an IDE or marketing submission, provided the study was conducted in accordance with Good Clinical Practice, including review and approval by an independent ethics committee, and the sponsor can verify data quality and integrity.

    This isn't a loophole. It's a documented, established framework. What it requires is that your LATAM study be designed and executed to the same quality standard you'd apply to a US study — ISO 14155 protocol architecture, ICH-GCP compliance, independent ethics review, and an audit-ready data room.

    If any of those elements are missing or inconsistently applied, the data's usability for FDA submissions becomes uncertain. This is exactly why protocol design and regulatory strategy must be aligned before enrollment begins, not after.


    Choosing the Right LATAM Jurisdiction for Your Device

    Not every Latin American country offers the same regulatory environment. For a startup, the practical distinction comes down to approval timeline and regulatory body predictability.

    Fast-Approval Jurisdictions

    Panama (MINSA/CNBI): Consistently among the fastest ethics and regulatory approval timelines in the region. Well-suited for first-in-human feasibility studies across a broad range of device classes.

    El Salvador (SRS/CNEIS): Regulatory approvals in the 30-to-90-day range. A strong option for sponsors who need to move quickly and have a straightforward device profile.

    Dominican Republic: Comparable approval timelines, with a growing clinical research infrastructure.

    Chile (ISP/MINSAL): A slightly more structured process, but still substantially faster than US or EU timelines. Well-regarded for cardiovascular and interventional device studies.

    Colombia: An established clinical research ecosystem with experienced investigator networks, particularly for complex device categories.

    What Drives Jurisdiction Selection

    Three factors should drive your choice: the device class and indication (some jurisdictions have deeper investigator experience in specific specialties), the regulatory body's familiarity with your device category, and your target FDA pathway. A device heading toward De Novo has different evidence requirements than one supporting a PMA, and those differences affect which jurisdiction and site network best fits your protocol.


    How to Sequence the Two Tracks

    Here's a practical sequencing framework for a startup that is IDE-ready or approaching that milestone.

    Phase 1: FDA Strategy Alignment (Months 1 to 2)

    Before any country selection or protocol drafting, align your LATAM study design to your FDA pathway. That means defining the primary and secondary endpoints your submission will need, confirming the study design (feasibility vs. pivotal), and identifying what a Pre-Submission meeting with FDA should accomplish before you enroll the first patient.

    If you haven't had a Pre-Sub meeting yet, this is the time. The output of that meeting shapes your protocol. Running a LATAM study without it is a sequencing error that's difficult to correct after the fact.

    Phase 2: Protocol Development and Jurisdiction Selection (Months 2 to 3)

    With FDA alignment in place, develop your protocol under ISO 14155 architecture. Select your LATAM jurisdiction based on device class, indication, and approval timeline requirements, then submit to the relevant ethics committee and regulatory authority.

    In Panama, El Salvador, and the Dominican Republic, ethics and regulatory approvals typically come back within 30 to 90 days of a complete submission. That window is your planning horizon for site activation.

    Phase 3: Site Activation and Enrollment (Months 3 to 8)

    Activate pre-qualified sites, enroll patients, and collect data under ICH-GCP standards with audit-ready documentation at every step.

    The quality of your data management during this phase determines how clean your evidence package will be. Errors in data collection that seem minor during enrollment tend to become significant problems during FDA review.

    Phase 4: Evidence Package Assembly (Months 8 to 12)

    Compile your clinical study report, statistical analysis, and organized data room structured for your specific FDA next step. Whether that's an IDE application, a 510(k) submission, or the clinical evidence section of a PMA, the deliverable should be organized to FDA's expectations — not just internally coherent.


    The Startup-Specific Consideration: Runway and Milestones

    For a seed-to-Series-B startup, the regulatory strategy question is inseparable from the capital question. Your investors have a milestone schedule. Your board has a timeline. Your next round has a closing date.

    A US or EU CRO timeline of 18 to 24 months for first human data doesn't fit inside a typical startup runway. A LATAM FIH study structured for FDA bridgeability can deliver a submission-ready evidence package within 12 months under the right program structure. That difference is often the difference between having data for your Series B and not having it.

    This isn't an argument to cut corners on quality. It's an argument to select the regulatory jurisdictions and execution model that match your actual timeline constraints — without compromising the standards that make the data usable.


    Common Sequencing Mistakes to Avoid

    Starting protocol development before confirming your FDA pathway. If you don't know whether you're targeting a De Novo or a PMA, you can't write the right protocol. The evidence standard is different, and rewriting a protocol after enrollment has started is expensive.

    Selecting a jurisdiction for speed alone. A fast approval timeline only matters if the site network in that jurisdiction has genuine experience with your device category and can execute to ISO 14155 standards. Speed and quality aren't mutually exclusive, but they require deliberate site selection.

    Treating the LATAM study as separate from the FDA strategy. Every decision in your LATAM trial — from endpoint selection to data collection procedures — should be made with your FDA submission in mind. The two tracks are one plan.

    Underestimating the data room requirement. FDA reviewers expect organized, auditable data. A clinical study report that's internally coherent but not structured for FDA review creates unnecessary friction at submission. Build the data room to FDA's expectations from the start.


    How bioaccess® Structures This for Sponsors

    bioaccess® is a CRO that manages first-in-human clinical trials for MedTech, Biopharma, and Radiopharma startups through exactly this kind of sequenced approach. The FIH-12™ program covers all nine workstreams — from FDA strategy alignment and protocol development through site activation, patient enrollment, data management, and delivery of a submission-ready clinical evidence package — within 12 months.

    One accountable team manages all nine workstreams across a network of 50-plus pre-qualified sites in Panama, Colombia, El Salvador, Chile, and the Dominican Republic. Every study is anchored to the sponsor's intended FDA pathway from day one, and the final deliverable is a clinical study report and organized data room structured for the sponsor's next FDA step.

    Intake is limited to a maximum of eight new programs per quarter — worth factoring into your planning timeline.


    FAQs

    Does FDA actually accept clinical data from Latin American trials?
    Yes. Under FDA 21 CFR 812.28, data from foreign clinical investigations of medical devices may be accepted in support of IDE and marketing submissions, provided the study was conducted in accordance with Good Clinical Practice and the sponsor can verify data quality and integrity. The key requirement is that the study is designed and executed to the same standards FDA would expect from a US study.

    How long do regulatory approvals take in Panama, El Salvador, and the Dominican Republic?
    Ethics and regulatory approvals in these jurisdictions typically take 30 to 90 days from a complete submission. That refers to the approval process specifically, not the overall trial duration.

    What is the difference between a feasibility study and a pivotal study in this context?
    A feasibility study evaluates the preliminary safety and performance of a device in a small patient population. A pivotal study generates the primary clinical evidence for a marketing submission. For most startups, the LATAM FIH study is a feasibility study that informs and supports the subsequent US pivotal study.

    Can LATAM FIH data support a 510(k) submission directly?
    In some cases, yes. If the 510(k) requires clinical data to demonstrate substantial equivalence, a well-documented LATAM feasibility study conducted under ISO 14155 and ICH-GCP standards can serve as that clinical evidence. The specific requirements depend on the device class and the predicate.

    What is ISO 14155 and why does it matter for FDA submissions?
    ISO 14155 is the international standard for Good Clinical Practice in clinical investigations of medical devices. FDA recognizes it as the applicable GCP standard for medical device trials, and studies conducted under its framework are structured to meet FDA's foreign clinical data acceptance requirements under 21 CFR 812.28.

    When should a startup begin thinking about LATAM regulatory strategy?
    Ideally, before protocol development begins. The earlier you align your LATAM study design to your FDA pathway, the less rework you'll face later. For most startups, the right entry point is at or shortly after an IDE approval or Series A close, when both the capital and the regulatory authorization to proceed are in place.

    What happens if the LATAM jurisdiction doesn't have experienced investigators for my device category?
    This is a real risk — and a reason why jurisdiction selection should be based on more than approval timelines alone. Site networks with documented experience in your device category reduce protocol execution risk. Evaluating investigator experience and site qualification before finalizing your jurisdiction is an important part of the planning process.


    Where to Start

    Sequencing LATAM approvals with your FDA pathway isn't complicated in principle. It requires knowing your FDA pathway before you design your protocol, selecting jurisdictions based on both approval timelines and site capability, and building your evidence package to FDA's expectations from the first day of enrollment.

    If you're approaching that planning window, the bioaccess® FIH-12™ program is structured specifically for this sequence. Learn more at bioaccessla.com.

  • Best EDC Systems for Clinical Trials: How to Pick the Right Platform for a FIH Study

    Best EDC Systems for Clinical Trials: How to Pick the Right Platform for a FIH Study

    Your electronic data capture system isn't a back-office detail when you're running a first-in-human trial. It's the infrastructure that determines whether your dataset is FDA-submittable or a rework project. Pick the wrong platform and you'll spend months cleaning data that should have been clean from day one.

    This guide covers what actually matters when selecting an EDC for a FIH study — not a 200-site Phase III, but an early-feasibility or first-in-human trial where your team is lean, your timeline is tight, and the data package you generate needs to hold up under FDA scrutiny.


    Why EDC Selection Looks Different for FIH Studies

    Most EDC comparisons are written for large-scale trials with dedicated IT teams, established data management departments, and long build timelines. FIH studies operate under different conditions.

    You're typically working with a small investigator team, a limited subject count, and a protocol that may still be evolving close to site activation. You need a platform that configures quickly, doesn't require months of validation work before you can collect a single data point, and produces outputs that map cleanly to your regulatory submission format — whether that's an IDE, a 510(k) package, or an IND.

    The compliance bar doesn't change. ICH-GCP standards apply regardless of study size. If your trial runs outside the US, FDA 21 CFR 812.28 governs how that foreign clinical data is accepted. Your EDC needs to support audit trails, access controls, and data integrity standards that will survive a regulatory review.


    The Core Requirements for a FIH-Ready EDC

    21 CFR Part 11 Compliance

    This is non-negotiable. Any EDC used in a trial intended to support an FDA submission must meet 21 CFR Part 11 requirements for electronic records and electronic signatures — audit trails for every data entry and modification, role-based access controls, and validated software with documented testing.

    If a vendor can't provide a current validation package and a 21 CFR Part 11 compliance statement, move on.

    ISO 14155 Compatibility for Medical Device Trials

    Medical device FIH studies follow ISO 14155, the international standard for clinical investigation of medical devices. Your EDC needs to support data collection structures that align with this standard: adverse event capture, device accountability, protocol deviation tracking, and investigator assessments that map to the endpoints defined in your clinical investigation plan.

    Not every EDC vendor has experience with device trials. Many are built primarily for drug studies, where the data architecture looks different. Ask specifically about ISO 14155 support and request examples of prior device study builds.

    Fast Configuration and Startup

    A FIH study on a 12-month timeline cannot absorb a 16-week EDC build. The best platforms for early-phase device and biopharma studies offer library-based form building, pre-validated study templates, and configuration timelines measured in weeks. Look for vendors who can demonstrate how quickly they activate a study from a finalized protocol — and get a realistic timeline in writing before you sign.

    Multi-Site and Multi-Country Data Collection

    If your trial runs across sites in Panama, Colombia, El Salvador, Chile, or the Dominican Republic, your EDC needs to support multi-language data entry, local time zone handling, and site-level access controls. Data collected across different regulatory jurisdictions still needs to flow into a single, clean, centralized database.

    This is especially relevant when site staff are working in Spanish and your data management team is reviewing in English. The platform needs to handle that workflow without introducing transcription risk.

    Regulatory Submission Export Formats

    Your EDC should export data in CDISC CDASH and SDTM formats — the standards FDA expects for data submissions. If it can't produce clean SDTM datasets, your data management team will be doing manual conversions, which adds time, cost, and the risk of errors entering your submission package. Confirm the export formats before you commit to a platform.


    What to Evaluate Beyond the Feature List

    Vendor Experience with Early-Phase Studies

    A vendor's reference list matters. Ask how many FIH or Phase I studies they've supported, and specifically whether any involved medical devices or international sites. A platform built primarily for large Phase III oncology trials may not have the configuration flexibility or support model that works for a 15-subject FIH feasibility study.

    Data Management Support Model

    Some EDC vendors sell software only. Others offer managed data management services alongside the platform. For a startup running its first FIH trial, a fully managed model often makes more sense than purchasing a license and building out your own DM team. Understand what's included in the contract and what's billed separately before you sign.

    Integration with Your CRO’s Workflow

    If you're working with a CRO that manages data management as part of its engagement, your EDC selection may be partially dictated by that CRO's existing infrastructure. This is worth discussing early. A CRO with validated workflows built around a specific EDC platform will execute faster and with fewer errors than one adapting to an unfamiliar system mid-study.

    At bioaccess®, data management is one of the nine workstreams covered under the FIH-12™ program. EDC setup, data monitoring, and preparation of the final evidence package are handled by the same team managing your protocol, your sites, and your regulatory submissions — not handed off to a separate vendor.


    Platforms Commonly Used in Early-Phase Trials

    This isn't an exhaustive market review, and the right choice depends on your specific protocol, budget, and CRO relationship. That said, a few platforms appear consistently in early-phase and FIH study contexts.

    Medidata Rave is the most widely deployed EDC in clinical research globally. It has strong 21 CFR Part 11 compliance infrastructure and broad regulatory acceptance. The tradeoff is configuration complexity and cost — it's better suited to sponsors with experienced data management teams or CROs with deep Medidata expertise.

    REDCap is widely used in academic and early-phase settings for its low cost and fast setup. It can be configured for 21 CFR Part 11 compliance, but that requires careful validation work. It's not a commercial EDC and lacks some of the enterprise support features larger trials need. For a lean FIH study with a strong data management team, it can work — but the validation burden needs to be managed carefully when the data is intended to support an FDA submission.

    Veeva Vault EDC has gained adoption in recent years, particularly in biopharma. It integrates well with other Veeva modules and has strong audit trail and compliance features. Configuration is generally faster than Medidata for straightforward protocols.

    Castor EDC is built specifically for early-phase and academic trials, with a faster setup model and strong multi-language support. It's used in international studies and has a compliance framework that supports 21 CFR Part 11. For FIH studies with international sites, it's worth evaluating.

    OpenClinica has a strong compliance pedigree, particularly in studies requiring CDISC output. It has both a commercial and an open-source version; the commercial version includes the validation documentation needed for regulatory submissions.


    The Biggest Mistakes Sponsors Make with EDC Selection

    Selecting based on price alone. The cheapest platform often carries the highest total cost once you factor in configuration time, data cleaning, and conversion work at submission. A platform that produces clean SDTM output from day one is worth more than one that requires manual post-processing.

    Treating EDC as a standalone decision. Your EDC choice affects your CRO, your data management team, your regulatory timeline, and your submission package. Make the decision in context, not in isolation.

    Underestimating the validation requirement. Every EDC used in a regulated trial needs to be validated. If the platform isn't already validated for your use case, that work takes time and costs money. Build it into your timeline from the start.

    Locking in a platform before your protocol is finalized. EDC configuration is driven by your data collection requirements, which come from your protocol. Starting the build before the protocol is stable leads to expensive amendments and delays.


    How EDC Fits Into a FIH Program

    A FIH study generates the foundational dataset your entire regulatory pathway depends on. The EDC is the system that captures, validates, and stores that data. Set it up correctly and your final data package is clean, audit-ready, and formatted for submission. Get it wrong and you're looking at data remediation that can delay your IDE or 510(k) by months.

    The most efficient path is to select your EDC as part of your overall FIH program design — not as a separate procurement. When your CRO manages data management as an integrated workstream alongside protocol development, site activation, and regulatory submissions, the EDC configuration is built to match the protocol from the start.

    That integration is part of what makes a structured FIH program different from assembling vendors independently. If you're evaluating CRO options, it's worth understanding how each handles data management and what EDC infrastructure they bring to the engagement.


    FAQs

    What is an EDC system in clinical trials?
    An electronic data capture (EDC) system is software used to collect, manage, and store clinical trial data in a structured, validated digital format. It replaces paper case report forms and provides the audit trail and access controls required for regulatory submissions.

    Does my EDC need to be 21 CFR Part 11 compliant for a FIH study?
    Yes. Any EDC used in a trial intended to support an FDA submission must comply with 21 CFR Part 11, which governs electronic records and electronic signatures. This includes audit trails, role-based access, and validated software with documented testing.

    Can I use REDCap for a trial intended to support an FDA submission?
    REDCap can be configured to meet 21 CFR Part 11 requirements, but it requires careful validation work that the sponsor or CRO must manage. It doesn't come with built-in regulatory validation packages the way commercial platforms do, so the compliance burden is higher.

    How long does EDC configuration typically take for a FIH study?
    For a straightforward FIH protocol, commercial EDCs with template libraries can typically be configured in four to eight weeks. More complex protocols or custom builds take longer. Factor this into your overall study startup plan.

    What data export formats does FDA expect for EDC submissions?
    FDA expects CDISC-compliant formats — specifically CDASH for data collection standards and SDTM for submission datasets. Your EDC should produce these formats directly. If it can't, your data management team will need to perform conversions, which adds time and risk.

    Does the EDC need to support multiple languages for international FIH studies?
    If your trial runs at sites where staff work in a language other than English, multi-language data entry support is important. For studies conducted in Latin American countries, site staff typically work in Spanish. Clean data collection in the local language reduces transcription errors and simplifies data review.

    How does EDC selection affect my FDA submission timeline?
    A well-configured EDC that produces clean, CDISC-compliant data shortens the time between last patient visit and a submission-ready data package. A poorly configured one can add months of cleaning and reformatting. EDC selection is a direct input to your regulatory timeline — not a separate operational decision.


    Choosing the right EDC for a FIH study comes down to one question: will this platform produce a clean, FDA-submittable dataset within your timeline? Get the compliance infrastructure right, align the platform with your protocol and your CRO's workflow, and treat EDC selection as part of your overall program design from day one.

    If you're planning a first-in-human trial and want to understand how data management fits into a structured FIH program, bioaccess® manages all nine workstreams under one engagement — including EDC setup and data management — across its network of sites in Panama, Colombia, El Salvador, Chile, and the Dominican Republic.

  • Colombia MedTech Study Site Qualification: A Practical Readiness Framework

    Colombia MedTech Study Site Qualification: A Practical Readiness Framework

    Colombia MedTech study site qualification should answer more than whether a hospital has a respected name or a specialist who is interested in the study. For an early-feasibility or FIH investigation, the sponsor must establish that the site can perform the procedure safely, capture reliable data, manage foreseeable complications, and maintain traceability from investigational material to participant record. A structured qualification review turns those assumptions into evidence before the first site is activated.

    This matters particularly for a leading MedTech startup working with an evolving product and a small initial cohort. A site that is clinically excellent but lacks the required equipment, emergency pathway, document controls, or trained support staff can create protocol deviations and delay the learning the sponsor needs. Qualification is therefore a risk-control decision, not a procurement formality.

    Start with the study’s real operating profile

    Define the procedure as it will actually occur in Colombia before comparing sites. List the patient population, imaging or monitoring needs, procedure duration, anesthesia or sedation requirements, sterile supplies, investigational-material storage, follow-up schedule, and expected adverse-event response. A site should be evaluated against this operating profile, not against a generic checklist that treats every medical device study as interchangeable.

    Separate essential capabilities from preferred capabilities. Essential capabilities are those that must be present before activation, such as the required procedure room, calibrated equipment, trained personnel, emergency response, and secure source-data access. Preferred capabilities can strengthen recruitment or throughput but may be addressed through a documented mitigation plan. This distinction makes site selection more transparent and prevents a prestigious location from passing while a critical control remains unresolved.

    Four qualification domains for a Colombian MedTech site

    Equipment and environment. Confirm that the site has the exact category of equipment needed for the protocol, suitable room layout, reliable utilities, infection-prevention controls, and a maintenance and calibration program. Ask for evidence rather than verbal assurance: asset lists, calibration records, preventive-maintenance logs, room diagrams, and photographs reviewed through the approved process. If a critical instrument is shared, document booking priority, backup availability, and what happens during service interruption.

    Investigator and team capability. Verify relevant procedural experience, training records, delegation plans, and availability during the enrollment window. Early-stage studies often require close coordination between the principal investigator, procedural staff, research coordinators, biomedical engineering, pharmacy or supply personnel, and data staff. Map who performs each critical task and who covers absences. A capable investigator cannot compensate for an untrained team member who handles accountability, consent, or a safety escalation.

    Emergency coverage. Qualification should trace the participant journey from arrival to discharge. Identify who recognizes a complication, who has authority to stop the procedure, where the participant is transferred, how emergency equipment is accessed, and how the event is documented and reported. Confirm that the pathway works during the hours the study will operate, including nights or weekends if the schedule requires them. A written policy is useful, but a walkthrough or tabletop exercise is stronger evidence of readiness.

    Data traceability and records. Confirm how source data are created, corrected, reviewed, and retained. The site should be able to link participant consent, procedure notes, device accountability, imaging or measurement outputs, adverse-event records, and follow-up assessments without relying on informal spreadsheets. Review access controls, audit trails, backup procedures, and the process for resolving discrepancies. If systems are shared with routine care, document how research records remain identifiable, attributable, contemporaneous, original, accurate, and complete.

    Build an evidence-based site qualification file

    A defensible file begins with the completed feasibility questionnaire, but it should not end there. Add the investigator curriculum vitae and training evidence, licenses or certifications as applicable, equipment and calibration records, emergency pathway, staffing matrix, facilities review, data-flow map, source-document examples, and a list of open actions. Label each item with an owner, due date, and activation impact.

    Use a red-amber-green decision model with explicit rules. Red means a prerequisite is absent or a safety risk is unresolved. Amber means a mitigation exists but must be closed before a defined milestone. Green means the evidence is complete and current. The sponsor should also record the decision not to select a site, because that creates a useful audit trail and improves future country planning.

    For Colombia, coordinate the qualification file with the submission and institutional review strategy. INVIMA’s clinical-investigation information is a starting point for understanding the national context, but site-level requirements and institutional procedures must be confirmed for the specific study. The site package should match the protocol, investigator materials, consent process, and any applicable import or accountability controls.

    From qualification to activation without losing control

    Qualification is a point-in-time assessment; activation is a controlled release. Before activation, confirm that open actions are closed, the current approved documents are in the investigator file, the team has completed role-based training, essential equipment is available, and the emergency pathway has been tested. Confirm that the site can receive and account for investigational materials and that the source-data workflow is live.

    After activation, monitor whether the assumptions made during qualification remain true. Track screening failures, protocol deviations, missing source records, equipment interruptions, response-time issues, and recurring data queries. These signals can show that a site passed the paper review but needs additional coaching or a revised mitigation. A short requalification trigger list—major staff change, equipment relocation, serious safety event, or prolonged enrollment pause—keeps readiness current without repeating the entire review unnecessarily.

    FAQ: Colombia MedTech study site qualification

    What is the most important site qualification question?

    Ask whether the site can perform the complete protocol safely and reproducibly with evidence. The answer should cover the procedure, staffing, equipment, emergency response, data capture, and follow-up—not just investigator interest.

    Can a site use shared equipment for a MedTech study?

    Yes, if availability, maintenance, calibration, booking priority, backup arrangements, and accountability are documented. Shared equipment becomes a risk when the study team cannot demonstrate reliable access during the protocol’s required windows.

    When should site qualification be repeated?

    Repeat or refresh qualification after material changes such as a principal-investigator transition, relocation of critical equipment, a major safety event, a long enrollment pause, or a change that affects the procedure or data workflow. Routine monitoring can determine when a full review is unnecessary.

    For a broader view of how early feasibility data can support downstream decisions, see this related MedTech evidence framework. The same discipline—defining the question, capturing the right measures, and documenting context—strengthens both clinical execution and future market-access discussions.

  • FIH Protocol Amendments in Latin America: A Control Plan to Reduce Regulatory Rework

    FIH Protocol Amendments in Latin America: A Control Plan to Reduce Regulatory Rework

    FIH protocol amendments in Latin America are not simply document updates. In an early-stage medical device study, a change to an endpoint, eligibility rule, procedure, or safety assessment can affect the ethics submission, regulatory package, informed consent, site workflow, import documents, and training plan at the same time. When each team reviews the change in isolation, sponsors can lose weeks reconciling versions that were technically correct but operationally inconsistent.

    A controlled amendment process gives a leading MedTech startup a safer way to learn quickly without creating avoidable submission cycles. The goal is not to prevent every change. It is to make the rationale, impact, approvals, and implementation sequence visible before a revised protocol reaches a Latin American authority or study site.

    Why FIH protocol amendments create disproportionate risk

    FIH studies generate new information while the protocol is still proving its assumptions. Early observations may lead a sponsor to clarify a stopping rule, narrow a population, change a follow-up visit, or add a safety measurement. Each decision can be reasonable on its own, yet the combined effect may change the study’s risk profile or the way a site performs a procedure.

    Latin America adds a coordination layer because country and institutional reviews do not always move in the same sequence. Colombia’s clinical-investigation framework, for example, places emphasis on the investigational plan, participant protection, and institutional oversight through its national regulator and participating institutions. Brazil’s evolving clinical-research framework also reinforces the importance of a complete, internally consistent package. A sponsor should therefore treat the amendment as a cross-functional change-control event, not as a new version of a Word file.

    The first decision is classification. Is the change administrative, operational, scientific, or safety-related? Does it alter the primary objective, participant exposure, procedure burden, inclusion and exclusion criteria, statistical assumptions, or the information presented during consent? A short impact statement answering these questions becomes the anchor for every downstream reviewer.

    A five-step control plan for FIH protocol amendments Latin America

    1. Open one amendment record. Assign a unique internal change number, an owner, a decision date, and a short rationale. Record the current approved version and list every affected artifact: protocol, investigator materials, consent form, case-report forms, safety plans, device accountability records, import documentation, and site training. This prevents the common failure mode in which the protocol is updated but a supporting document still describes the previous procedure.

    2. Map the evidence and risk impact. Explain what new information triggered the change and whether it reduces, increases, or leaves unchanged the foreseeable risk to participants. For a procedure change, identify new equipment, staffing, emergency coverage, or competency requirements. For an eligibility change, review recruitment feasibility and whether the consent discussion needs new language. Keep the analysis proportional, but do not skip it because the amendment appears minor.

    3. Run a country and institution matrix. Create a row for each Latin American country and each participating institution. For every row, identify the authority or ethics body that must review the change, whether the amendment can be submitted in parallel, which documents require local language updates, and what must happen before implementation. The matrix should distinguish approval, acknowledgement, notification, and site activation. Those are different milestones and should never be collapsed into one “approved” status.

    4. Freeze the release package. Use a single source package with a clean protocol, tracked-changes version, amendment summary, revised consent language, updated supporting documents, and a version crosswalk. Add a release checklist requiring clinical, regulatory, quality, medical, data, and site-operations sign-off. A simple rule helps: no site receives an operational instruction until the effective version and the applicable local approval status are confirmed.

    5. Close the loop after approval. Record the effective date for each country and site, then confirm retraining, re-consent, database updates, document replacement, and audit-trail completion. The amendment is not implemented when a letter arrives; it is implemented when the right participants, investigators, and systems are operating from the same approved instructions. A short post-implementation review can capture whether the change produced the intended safety or data-quality benefit.

    Designing an amendment dossier reviewers can follow

    A reviewer should be able to understand the change without comparing every line of two long documents. Start with a one-page executive summary: what changed, why it changed, which participants are affected, which risks were reassessed, and what approvals are requested. Follow with a table showing old language, new language, rationale, and affected documents. Add the supporting evidence that informed the decision, but keep unrelated background out of the core package.

    Use consistent terminology across the protocol, consent form, investigator brochure or device information, and site instructions. If the amendment changes a visit window, the schedule of assessments and case-report form should use the same definition. If it changes a safety threshold, the monitoring plan and escalation pathway should repeat the same threshold. Consistency is a practical signal that the sponsor understands its own risk controls.

    For country execution, prepare a local annex rather than rewriting the global rationale several times. The annex can identify the applicable authority, institutional sequence, language needs, local contact, and implementation date. This approach protects the scientific core of the amendment while giving each country team the detail needed for compliant execution.

    FAQ: FIH protocol amendments in Latin America

    When should a sponsor notify sites about a planned amendment?

    Share a controlled planning notice when sites need to prepare, but do not authorize the changed procedure until the applicable review and implementation conditions are met. Early communication can reserve training time and prevent avoidable scheduling disruption.

    Should an amendment be submitted in every Latin American country?

    Not automatically. The decision depends on the change, the local rules, and the status of the study in each country. A country matrix should document whether the action is approval, acknowledgement, notification, or no filing, with a clear rationale and owner.

    How can sponsors reduce amendment-related delays?

    Reduce avoidable delay by classifying the change early, using one evidence-based impact assessment, freezing a complete release package, and tracking country and site implementation separately. The cross-functional readiness gate for FIH submissions provides a related framework for aligning teams before filing.

    For regulatory context, sponsors can consult INVIMA’s clinical-investigation information and Brazil’s Law No. 14.874/2024. Requirements should be confirmed with local regulatory and ethics experts before a submission is made.

  • 510k vs PMA: Which FDA Pathway Should Your Medical Device Pursue?

    510k vs PMA: Which FDA Pathway Should Your Medical Device Pursue?

    Choosing between a 510(k) and a Premarket Approval (PMA) is one of the most consequential decisions a medical device founder makes. Get it right early, and your clinical strategy, budget, and investor timeline all line up. Get it wrong, and you may spend 18 months collecting data that doesn't satisfy the evidentiary standard your pathway actually requires.

    This article breaks down the core differences between the two pathways, how to determine which applies to your device, and what that choice means for your first-in-human trial design.


    What the FDA Is Actually Asking

    Both pathways exist to answer the same fundamental question: is this device safe and effective enough to be on the US market? The difference lies in how much evidence the FDA needs to reach that answer — and that requirement flows directly from how your device is classified.

    The FDA assigns every medical device to one of three classes based on patient risk.

    • Class I devices carry low risk. Most are exempt from premarket review entirely.
    • Class II devices carry moderate risk. Most reach market through the 510(k) pathway.
    • Class III devices carry the highest risk — typically because they sustain or support life, are implanted, or present an unreasonable risk of illness or injury. These require PMA.

    Your device's classification is the starting point for everything else.


    The 510(k) Pathway: Substantial Equivalence

    A 510(k) submission asks the FDA to clear your device by demonstrating substantial equivalence to a legally marketed predicate. You're not proving safety and effectiveness in isolation — you're showing your device performs comparably to something already on the market.

    What “substantially equivalent” means in practice

    Your device must share the same intended use as the predicate and either the same technological characteristics, or different characteristics that don't raise new safety or effectiveness questions. That framing matters because it shapes what kind of clinical data — if any — you actually need to collect.

    Many 510(k) submissions rely primarily on bench testing, biocompatibility data, and performance testing. When clinical data is required, it's typically a focused study rather than a full pivotal trial.

    Timeline and workload

    The FDA's standard review period for a 510(k) is 90 days from acceptance, though total elapsed time often runs longer when the agency issues additional information requests. For a device with a clear predicate and strong bench data, the 510(k) can be a relatively fast path to market.

    The risk is predicate selection. A weak or distant predicate invites a Not Substantially Equivalent determination — which can push you toward De Novo or PMA territory without warning.


    The PMA Pathway: Valid Scientific Evidence

    A PMA requires you to demonstrate reasonable assurance of safety and effectiveness through valid scientific evidence. There's no predicate to point to. The FDA evaluates your device on its own merits, which means your clinical dataset needs to stand alone.

    This is the pathway for Class III devices: implantable cardiac devices, certain neurological implants, high-risk diagnostics, and others where failure could cause serious harm.

    What a PMA clinical program looks like

    A PMA typically requires at least one well-controlled pivotal trial — often with a statistically powered sample size, defined primary endpoints, and a comparator arm. The FDA's review of that data is rigorous, and the agency may convene an advisory panel for high-profile submissions.

    The IDE (Investigational Device Exemption) is the mechanism that allows you to collect pivotal data in the first place. Before you enroll a single patient in a significant-risk device study, you need an approved IDE. That application itself requires preliminary safety data — which is exactly where a first-in-human or early feasibility study fits in.

    Timeline and investment

    PMA is a longer, more expensive process than 510(k). Total development timelines from first-in-human to PMA approval can run five to ten years for complex devices. The clinical program alone typically spans multiple phases: an early feasibility study to establish safety signals, followed by a pivotal trial to generate primary effectiveness data.

    For a startup, that timeline has direct implications for how you structure your FIH study and what evidence you need before your next funding round.


    Key Differences at a Glance

    Factor 510(k) PMA
    Device class Primarily Class II Class III
    Standard of review Substantial equivalence to a predicate Valid scientific evidence of safety and effectiveness
    Clinical data requirement Often limited or none Required; typically a pivotal trial
    IDE required Only for significant-risk studies Yes, for pivotal and often for early feasibility
    FDA review timeline ~90 days (standard) 180 days (after filing acceptance)
    Post-approval requirements Generally lighter Ongoing post-approval studies common

    The De Novo Pathway: A Third Option Worth Knowing

    If your device is genuinely novel, poses low to moderate risk, and has no valid predicate, De Novo is worth serious consideration. It creates a new device classification and, once granted, establishes your device as a predicate for future 510(k) submissions.

    De Novo is not a shortcut. It requires more documentation than a standard 510(k), and the FDA's review period is longer. But for a first-of-kind device that doesn't belong in Class III, it's the appropriate route — and it avoids the burden of a full PMA.


    How Pathway Choice Shapes Your FIH Study

    Your regulatory pathway determines the evidentiary standard your clinical data must meet. That standard, in turn, determines what your first-in-human study actually needs to accomplish.

    For a 510(k) device, your FIH study is often a relatively small early feasibility study designed to confirm safety signals and support predicate comparisons. Endpoints are narrower, enrollment targets are smaller, and the study can typically be completed faster.

    For a PMA device, your FIH study is the first step in a longer clinical program. The FDA will evaluate it as part of the overall evidence package, and the data needs to be structured to support the IDE application for your pivotal trial. Endpoints, patient population, and follow-up duration all have to be designed with that pivotal study in mind from day one.

    This is why FDA strategy alignment can't be an afterthought. Design your FIH study without anchoring it to your intended pathway, and you risk collecting data that doesn't move your program forward.


    Aligning FIH Trial Design to Your Pathway

    At bioaccess®, every study in the FIH-12™ program begins with FDA strategy alignment as the first of nine workstreams. The protocol is built around the sponsor's intended pathway — whether that's IDE, 510(k), De Novo, PMA, or HDE — so the clinical evidence package that comes out of the program is structured for the submission it needs to support.

    Trials run in Panama, Colombia, El Salvador, Chile, and the Dominican Republic, where ethics and regulatory approvals are observed in 30 to 90 days, compared to 6 to 12 months in the US or EU. That speed matters when your runway is finite and your next funding milestone depends on having human data in hand.

    The FIH-12™ program delivers a submission-ready evidence package within 12 months. All data is structured for FDA acceptance under 21 CFR 812.28, which governs the use of foreign clinical data in US submissions.


    Practical Questions to Ask Before You Choose

    Before committing to a pathway, work through these with your regulatory team:

    What is your device's intended use, and does it match an existing predicate? If yes, 510(k) is likely your starting point. If no, you're looking at De Novo or PMA.

    What risk class does the FDA assign to devices with your intended use? The FDA's product classification database is the first place to check. If your device type is consistently Class III, PMA is your pathway regardless of predicate availability.

    Have you had a Pre-Submission (Q-Sub) meeting with the FDA? A Pre-Sub is the most direct way to get the agency's early read on your classification and pathway. It's not binding, but it significantly reduces the risk of a wrong-pathway investment.

    What does your clinical evidence need to show? For 510(k), you need to demonstrate comparability. For PMA, you need to demonstrate safety and effectiveness. These are different evidentiary standards that require different study designs.

    What is your funding timeline? If you have 18 months of runway and need human data before a Series B closes, a PMA pivotal trial isn't achievable in that window. But a well-designed early feasibility study that supports your IDE application can be.


    When Founders Get This Wrong

    The most common mistake is assuming a 510(k) pathway because a similar device exists on the market. Predicate selection is more nuanced than it looks. A device with the same intended use but meaningfully different technology may not qualify as substantially equivalent — and a Not Substantially Equivalent determination late in the process is expensive.

    The second common mistake is under-designing the FIH study for a PMA pathway. Founders sometimes treat the early feasibility study as a standalone safety check rather than as the foundation for a pivotal trial. When the pivotal trial IDE application reaches the FDA, gaps in the early data create delays that could have been avoided.

    Both mistakes come down to the same root cause: regulatory strategy that starts too late.


    FAQs

    What is the main difference between a 510(k) and a PMA?
    A 510(k) clears a device by showing it is substantially equivalent to a legally marketed predicate. A PMA approves a device based on valid scientific evidence of safety and effectiveness, without relying on a predicate. PMA applies to Class III devices and requires a full clinical program; 510(k) applies primarily to Class II devices and often requires limited or no clinical data.

    Does a 510(k) device need clinical trials?
    Not always. Many 510(k) submissions rely on bench testing, biocompatibility data, and performance testing. Clinical data is required when bench testing alone can't establish substantial equivalence, or when the device's intended use involves a clinical performance claim that needs human data to support it.

    What is an IDE and when do you need one?
    An Investigational Device Exemption (IDE) is FDA authorization to use an investigational device in a clinical study. You need an IDE for any significant-risk device study conducted in the United States. For PMA devices, the IDE is the mechanism that allows you to collect the pivotal trial data the FDA requires for approval.

    Can a Class II device require PMA?
    In rare cases, yes. The FDA can require a Class II device to go through PMA if it determines that general and special controls aren't sufficient to provide reasonable assurance of safety and effectiveness. This is uncommon but worth confirming for novel device types.

    What is the De Novo pathway and how does it differ from 510(k) and PMA?
    De Novo is a classification pathway for novel, low-to-moderate-risk devices with no valid predicate. It creates a new device type and establishes the device as a predicate for future 510(k) submissions. It requires more documentation than a standard 510(k) but is less burdensome than PMA — making it the right route for genuinely first-of-kind devices that don't pose Class III risk.

    How does my FDA pathway choice affect my first-in-human study design?
    Your pathway determines the evidentiary standard your clinical data must meet. A 510(k) FIH study typically needs to confirm safety and support predicate comparisons, with narrower endpoints and smaller enrollment. A PMA FIH study is the first step in a longer clinical program and must be designed with the pivotal trial in mind from the start — including endpoints, patient population, and follow-up duration.

    How long does PMA approval typically take compared to 510(k)?
    The FDA's standard review period for a 510(k) is 90 days from acceptance, though total elapsed time is often longer. For PMA, the FDA has 180 days from filing acceptance to act, but the full development timeline from first-in-human to PMA approval for complex devices can span several years — including the time required to complete a pivotal trial.


    Pathway selection is a regulatory decision with clinical, financial, and strategic consequences. The earlier you align your FIH study design to your intended submission, the less time and capital you spend collecting data that doesn't move your program forward.

    If you're mapping your device's regulatory strategy and want to understand how a structured FIH program fits into that plan, learn more at bioaccessla.com.

  • Best Practices for First in Human Biopharma Trials in El Salvador

    Best Practices for First in Human Biopharma Trials in El Salvador

    Introduction

    El Salvador presents a unique opportunity for biopharma trials, boasting a regulatory landscape that allows for rapid approvals and significant cost efficiencies. With the potential for 30% lower per-patient costs compared to US and EU benchmarks, sponsors can leverage this strategic advantage to expedite their clinical research. Yet, navigating local regulations and patient recruitment can be daunting for sponsors.

    What strategies can sponsors employ to navigate these challenges and secure successful trial outcomes?

    Understand the Regulatory Landscape for FIH Trials in El Salvador

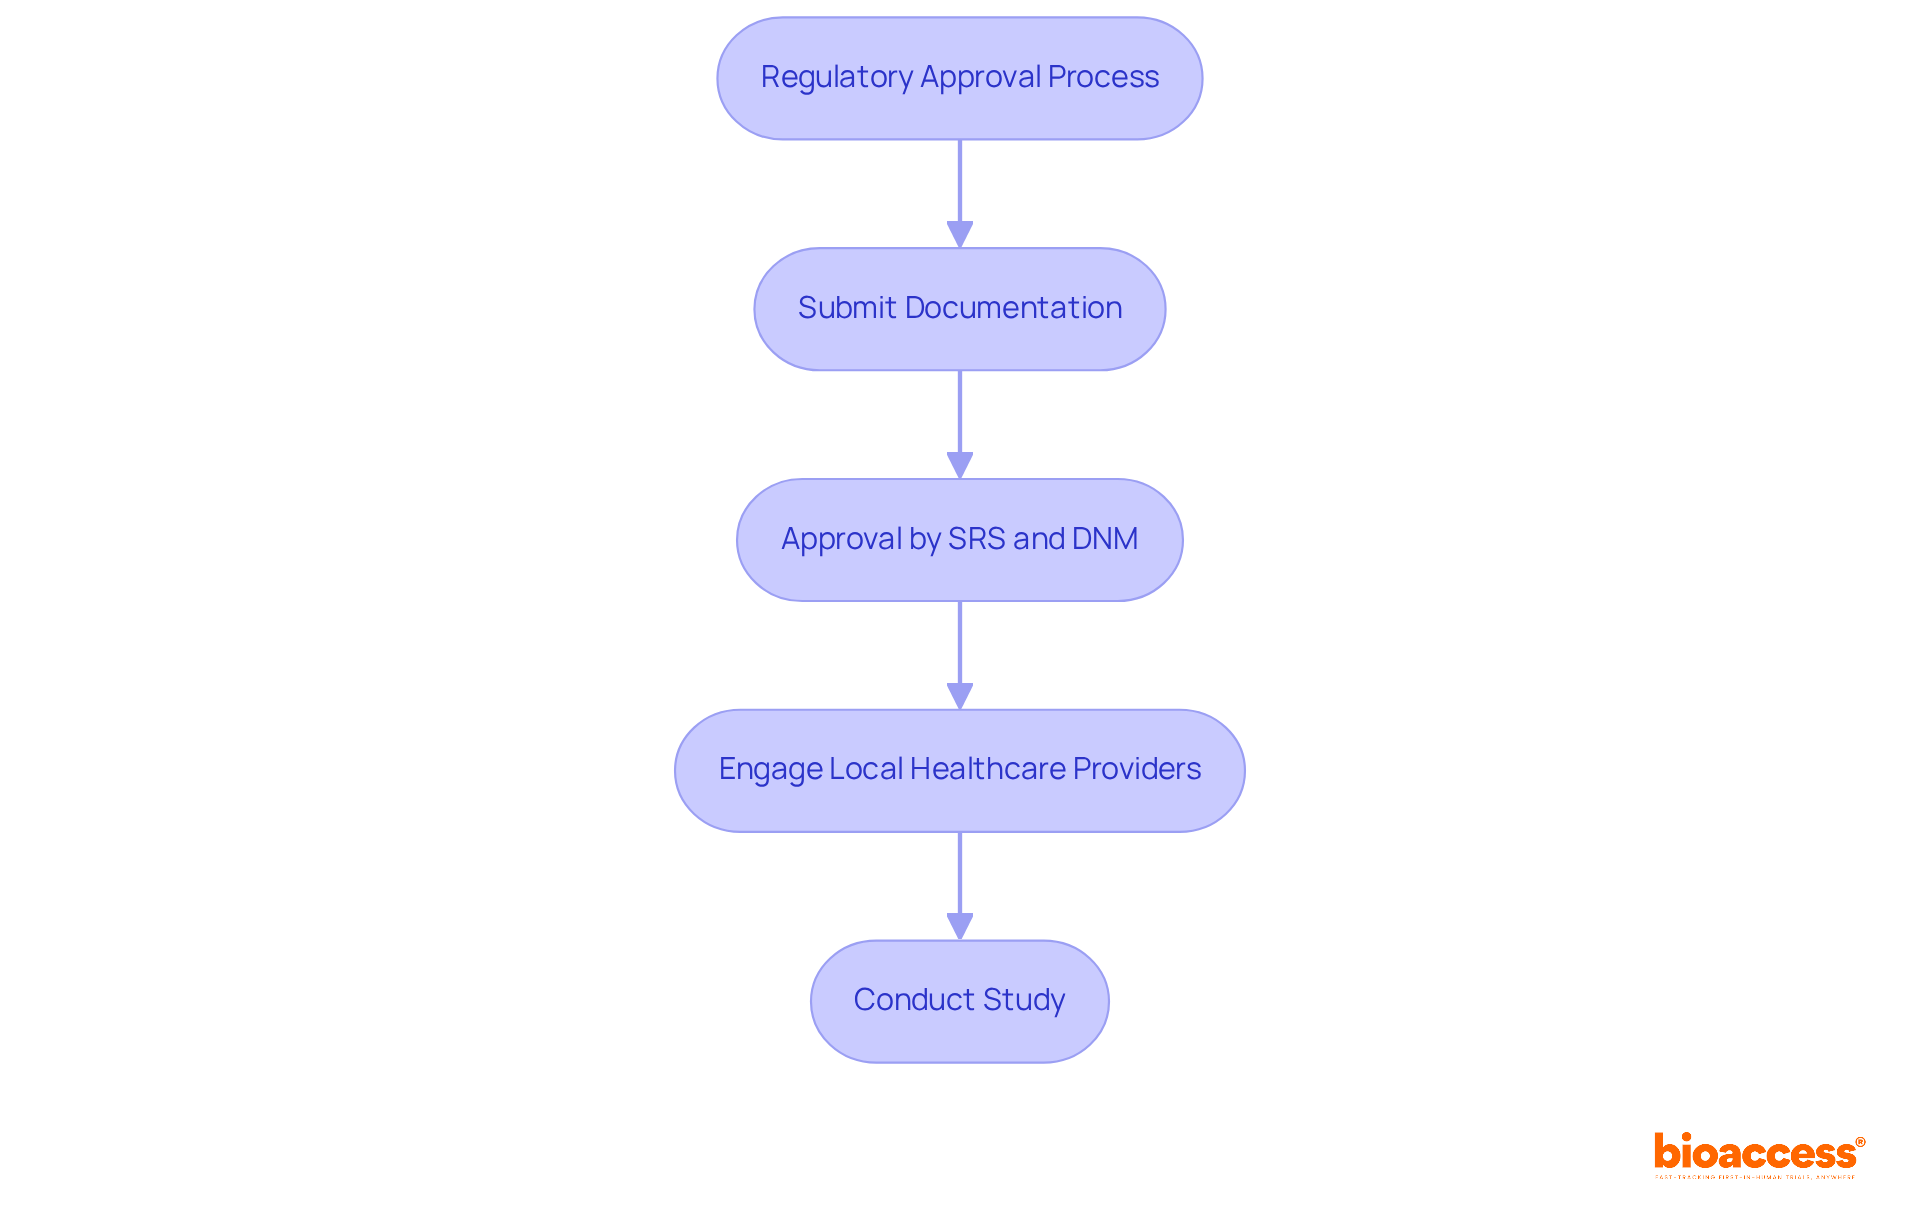
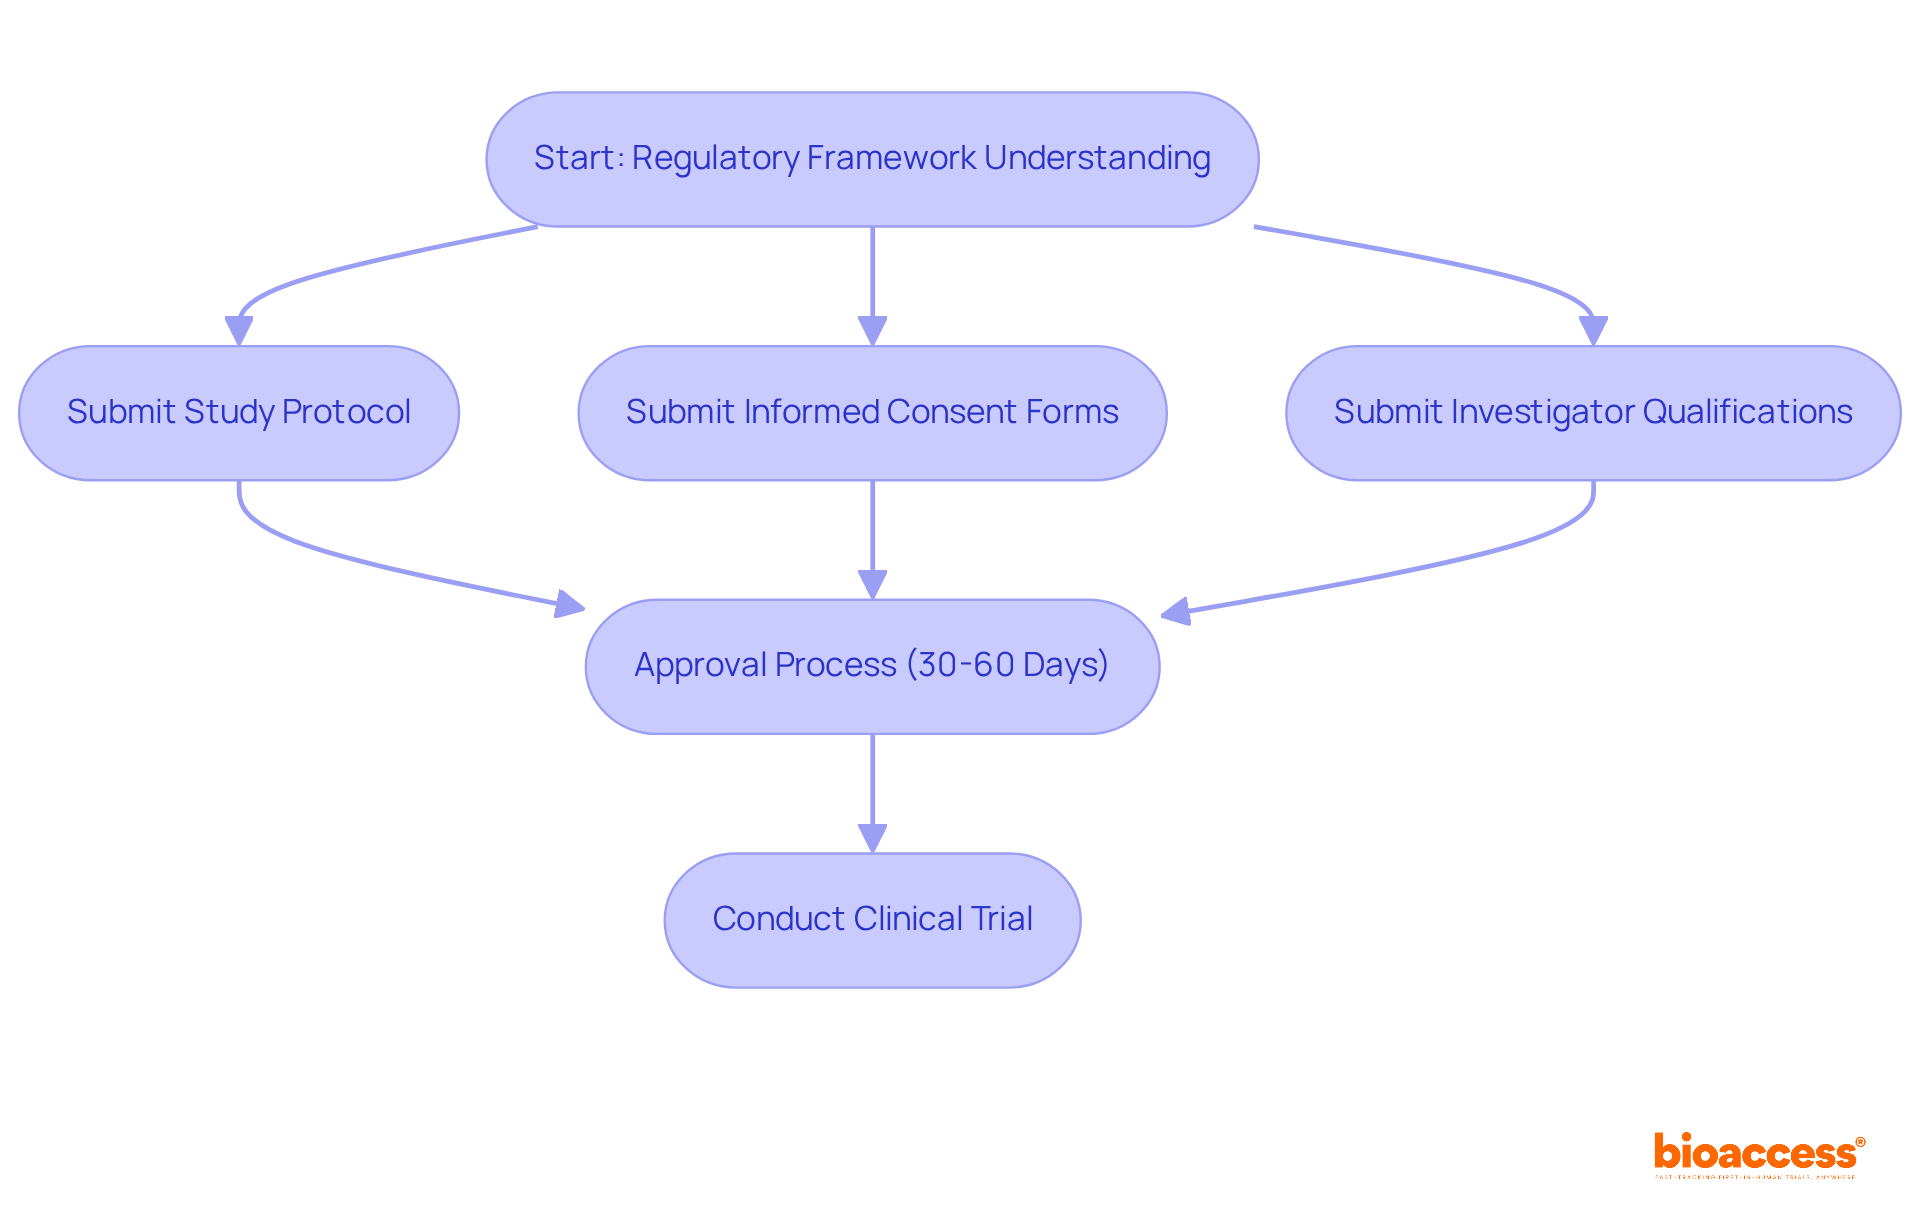
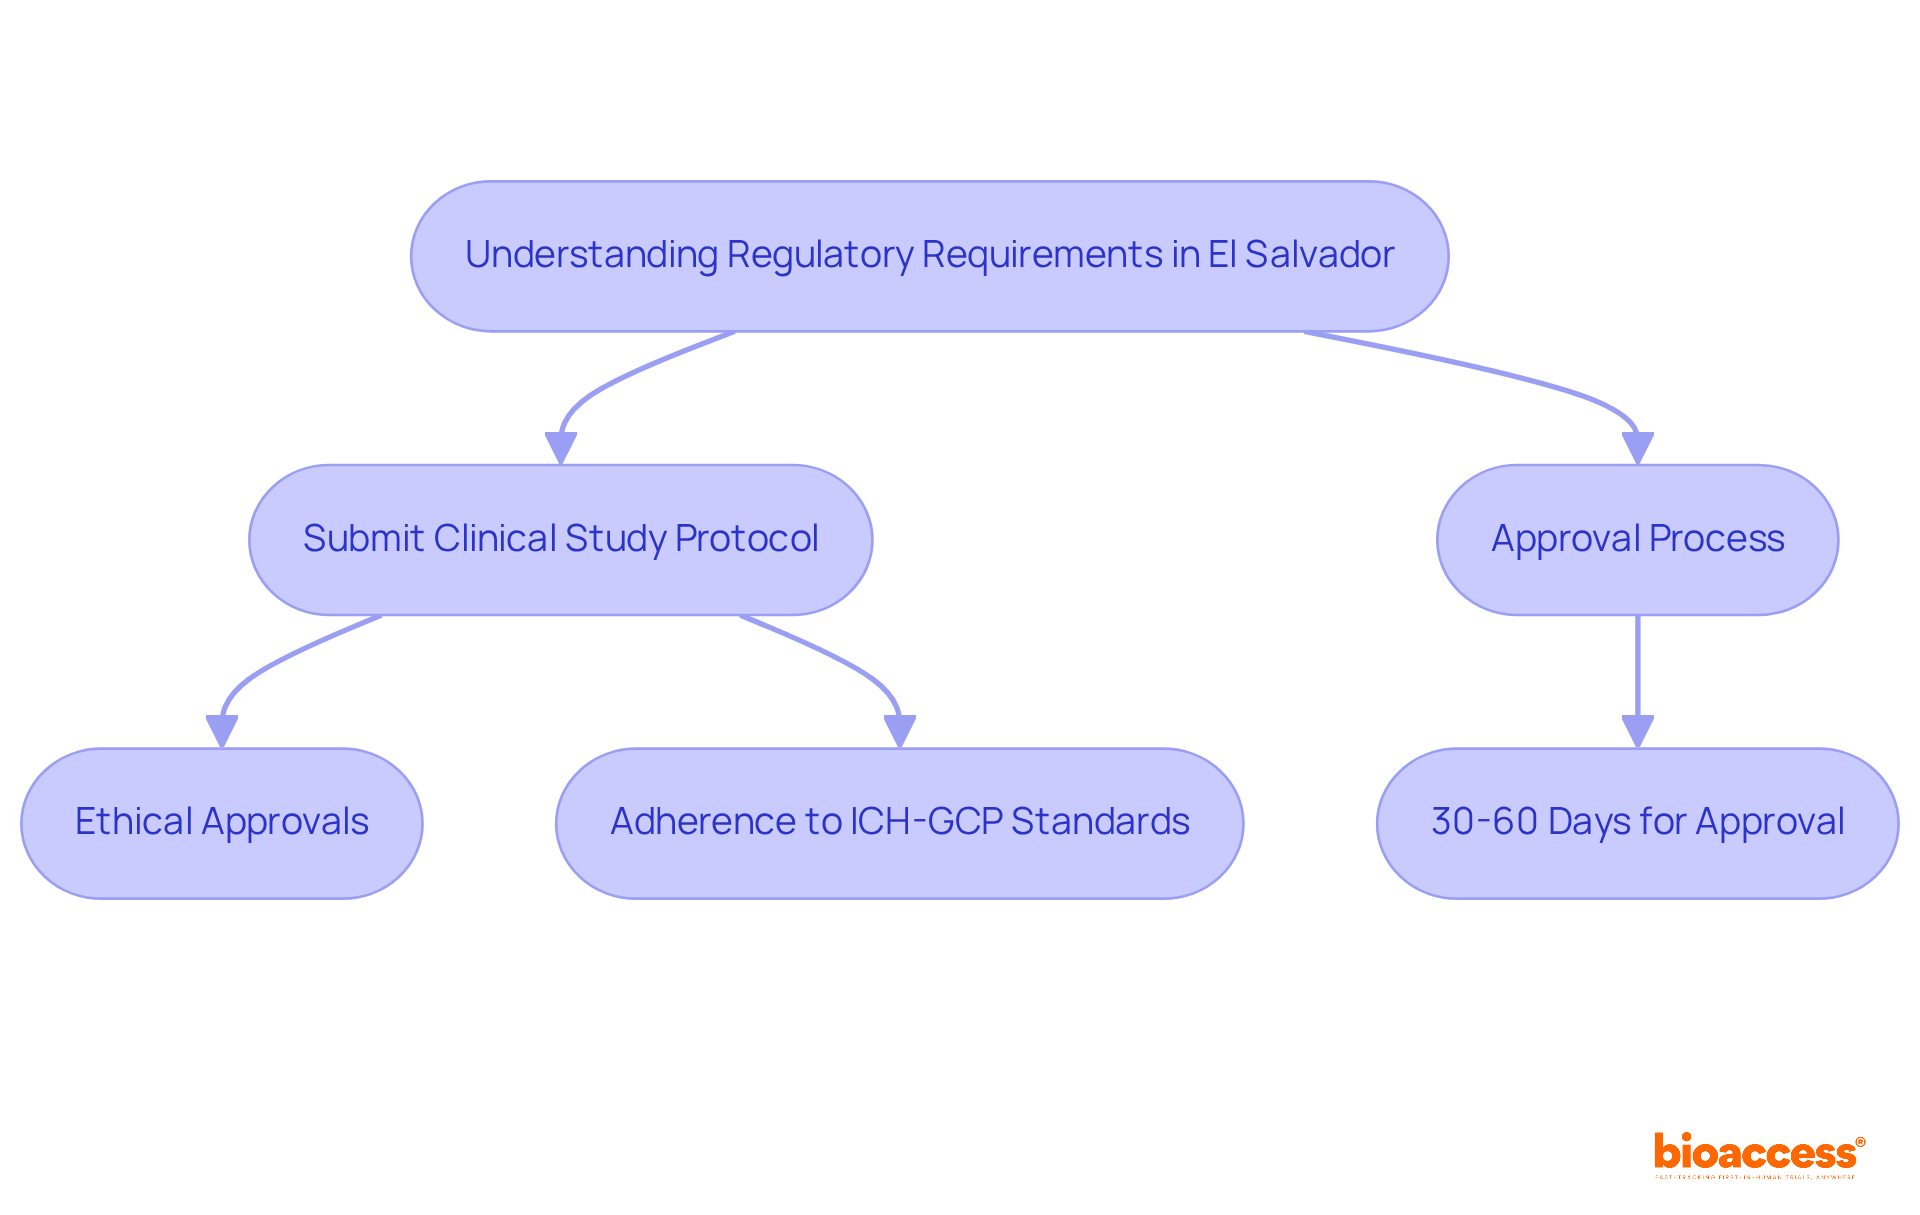
    El Salvador’s regulatory framework for first in human biopharma studies offers a unique opportunity for clinical researchers. Supervised by the Superintendencia de Regulación Sanitaria (SRS) and the National Directorate of Medicines (DNM), the approval process typically takes only 30 to 60 days. This speed offers a significant advantage compared to many other regions. Adherence to ICH-GCP standards is crucial, ensuring ethical conduct and data integrity throughout the study process. Sponsors must prepare thorough documentation, including:

    1. The study protocol
    2. Investigator’s Brochure
    3. Informed consent forms

    All of which need to be submitted electronically through the SRS-CNEIS-ES platform. Additionally, all documentation must be prepared in Spanish to comply with local regulations.

    To recruit participants effectively, it’s crucial to engage with local healthcare providers and community organizations, which increases the chances of successful outcomes in research studies. Moreover, conducting studies in the region can result in cost reductions of about 30% lower per-patient expenses compared to US/EU benchmarks, making it a strategic option for early-stage clinical investigations. By navigating these regulations effectively, sponsors can expedite their research timelines. Understanding these regulatory pathways, along with the importance of local adherence and community participation, is key to speeding up study initiation and ensuring compliance.

    This flowchart outlines the steps involved in conducting first in human trials in El Salvador. Each box represents a key stage in the process, and the arrows show how each step leads to the next. Follow the flow to understand how to navigate the regulatory landscape effectively.

    Prepare Essential Documentation and Compliance Requirements

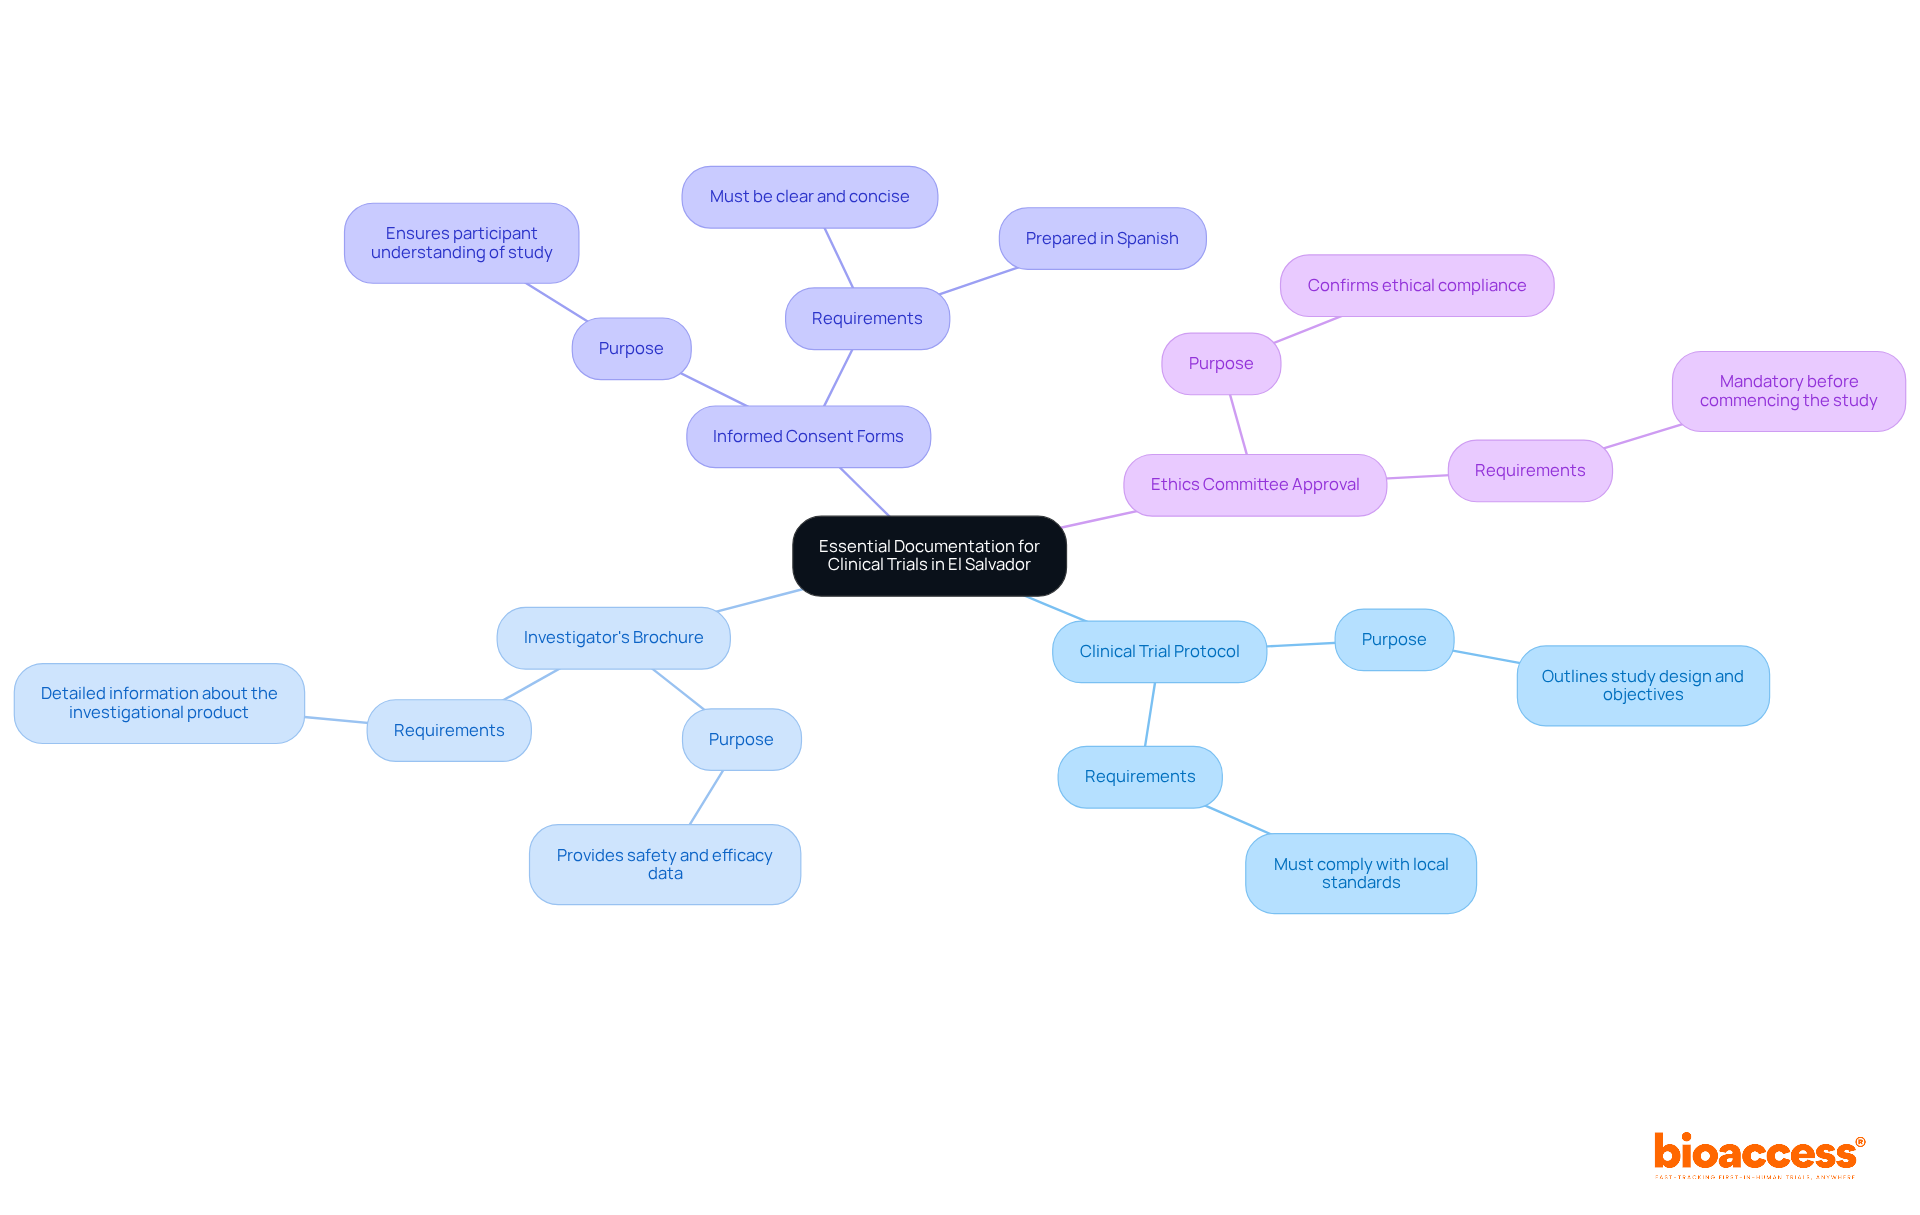
    To thrive in the regulatory landscape of El Salvador, sponsors must meticulously prepare key documents for submission to the Superintendencia de Regulación Sanitaria (SRS). These include:

    • Clinical Trial Protocol: This document outlines the study design, objectives, and methodology, serving as the foundation for the trial.
    • Investigator’s Brochure: This provides detailed information about the investigational product, including its safety and efficacy data.
    • Informed Consent Forms: These ensure that participants are fully informed about the study’s purpose, procedures, risks, and benefits, and must be clear and concise.
    • Ethics Committee Approval: Documentation from an Institutional Review Board (IRB) confirming ethical compliance is mandatory before commencing the study.

    All documents must be prepared in Spanish and adhere to local standards. The approval timeline for phase 1 trials in the region typically ranges from 30 to 60 days, making it one of the quickest options in Latin America. The bioaccess® sample budget puts a first-in-human study in Latin America at about $430K for 20 subjects with a minimally invasive device and about $1.32M for 10 subjects with a surgical implant (illustrative, not a quote; see bioaccessla.com/sample-budget-fih-trial-latin-america). Employing templates and checklists is essential for streamlining this process, guaranteeing that all necessary information is included and minimizing the risk of delays. Acquainting oneself with the regulatory framework and ensuring proper documentation is essential for the success of clinical studies in the region. As noted by the SRS, “Compliance with these details is critical to avoiding submission delays and ensuring the SRS can review applications efficiently.” With bioaccess®, sponsors can also benefit from accelerated timelines, initiating first in human biopharma El Salvador studies within 6-8 weeks and achieving FDA-bridgeable data approximately 40% faster than the pathways in the US/EU. With the right preparation and support, sponsors can navigate these challenges and accelerate their clinical research efforts in El Salvador.

    This mindmap starts with the main topic in the center and branches out to show the key documents needed for clinical trials. Each branch represents a different document, and the sub-branches provide important details about what each document entails. This visual helps you see how everything connects and what you need to prepare.

    Implement Effective Patient Recruitment Strategies

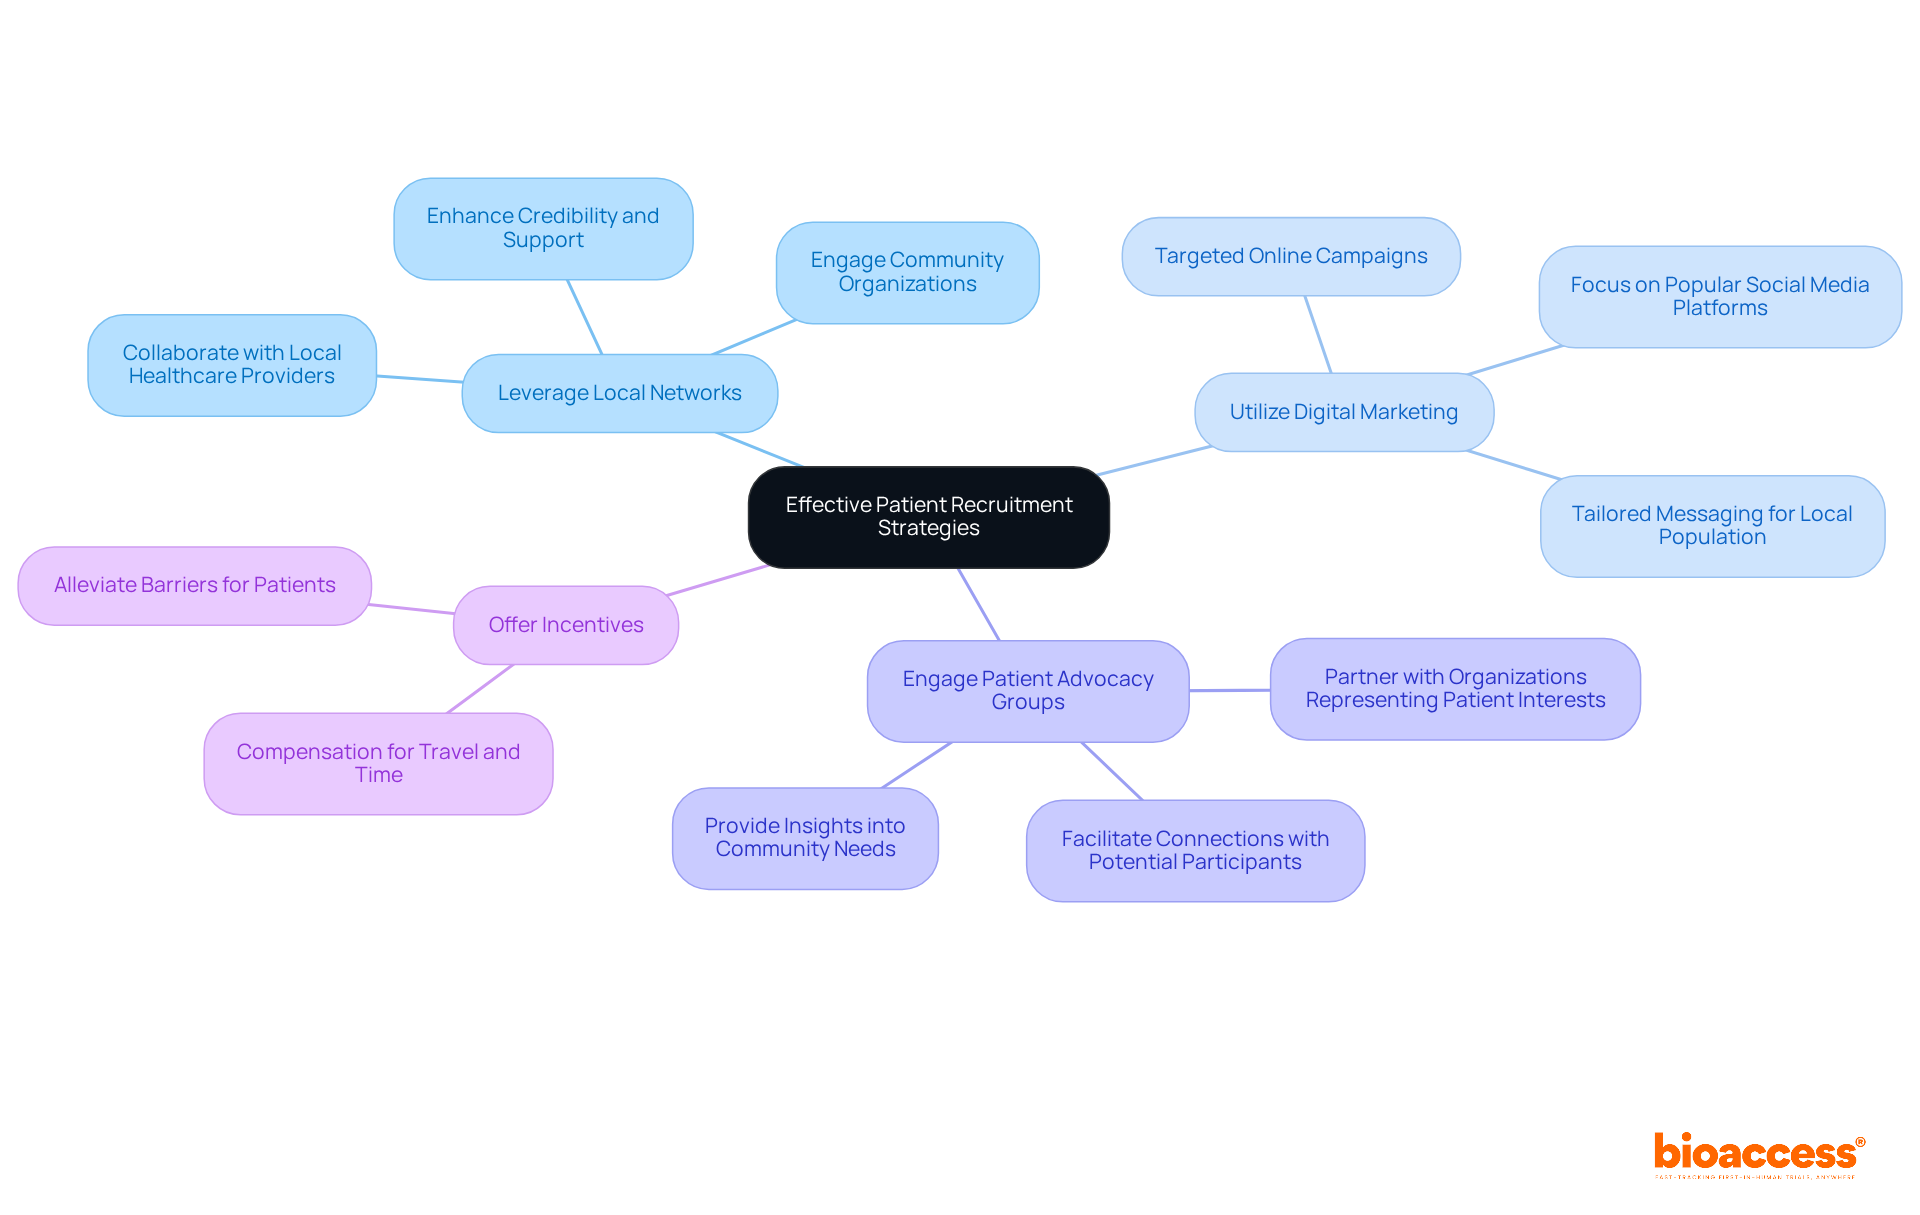
    In El Salvador, the success of first in human biopharma El Salvador studies relies on effective patient recruitment strategies. Sponsors should consider the following approaches:

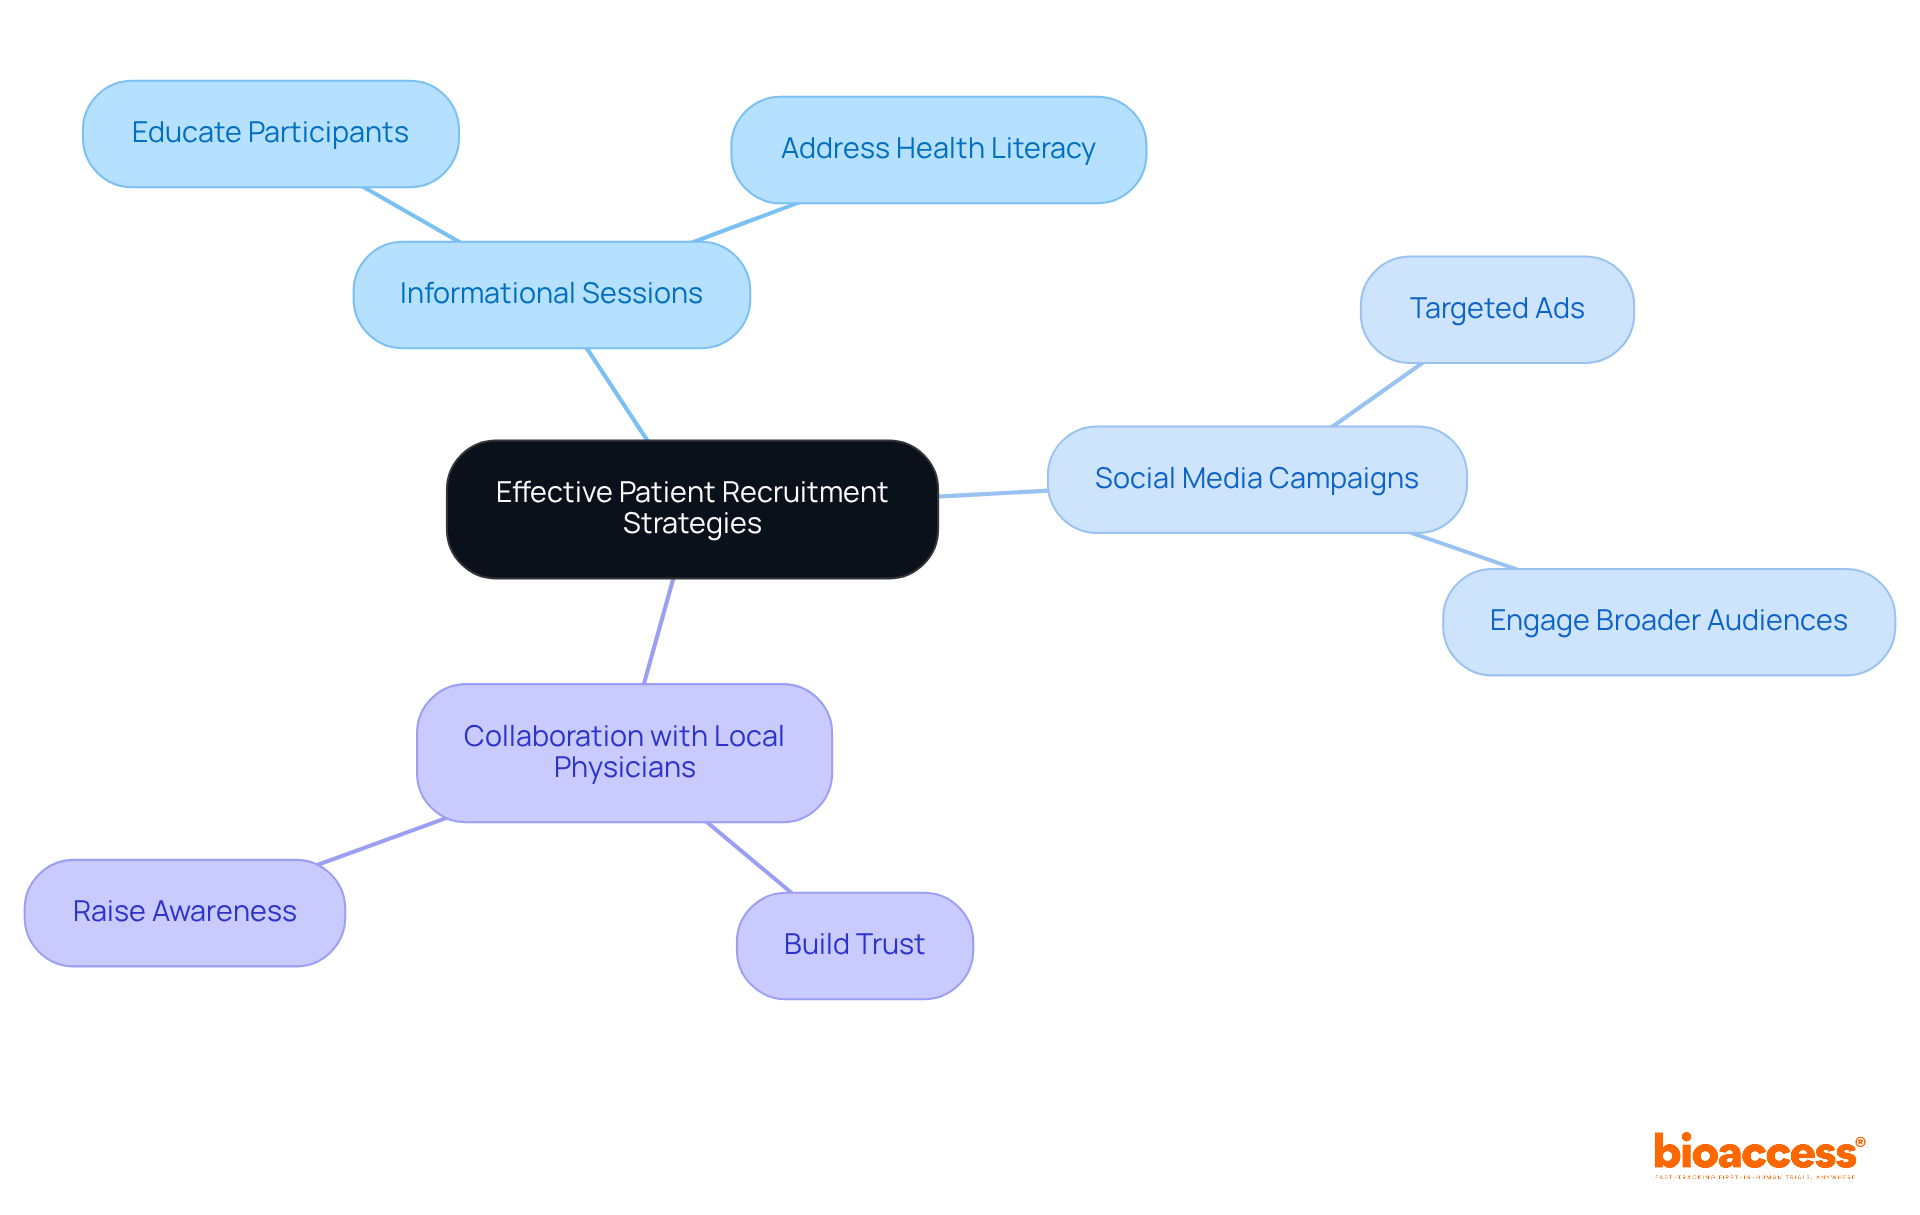
    • Leverage Local Networks: Collaborate with local healthcare providers and community organizations to raise awareness about the trial. Engaging with trusted local entities can enhance credibility and foster community support, a strategy that bioaccess® has successfully implemented in its projects across Latin America.
    • Utilize Digital Marketing: Implement targeted online campaigns to reach potential participants, focusing on popular social media platforms in the region. Tailored messaging that resonates with the local population can significantly improve outreach efforts, as demonstrated by bioaccess®’s effective communication strategies.
    • Engage Patient Advocacy Groups: Partner with organizations that represent patient interests to enhance trust and credibility. These groups can facilitate connections with potential participants and provide valuable insights into community needs, aligning with bioaccess®’s commitment to understanding local patient populations.
    • Offer Incentives: Think about offering compensation for travel and time to encourage participation. Financial support can alleviate barriers for patients, particularly those with limited mobility or resources.

    By utilizing these approaches, sponsors can improve enrollment rates and ensure a diverse participant pool. This ultimately leads to more comprehensive data and favorable study outcomes. With only 36.32% of trials meeting their recruitment goals, the challenge of effective patient recruitment is clear. As the FDA indicates, ‘Patient recruitment remains the single largest bottleneck in development of trials.’ Additionally, compliance with local regulatory authorities such as INVIMA and adherence to ICH-GCP standards are essential to ensure operational success as we strive to be first in human biopharma El Salvador. Addressing common pitfalls, such as overcomplicating recruitment processes, can further improve outcomes. Implementing these strategies not only boosts enrollment but also enhances data quality, leading to successful study execution. With the expertise of bioaccess®’s founders, Dr. Martinez-Clark and Dr. O’Neill, sponsors can navigate the complexities of the regulatory landscape and expedite their clinical studies in Latin America. Moreover, carrying out studies in Latin America can result in about 30% reduced per-patient expenses compared to US/EU benchmarks, making it a financially efficient choice for sponsors.

    The central node represents the overall goal of improving patient recruitment. Each branch shows a different strategy, and the sub-branches provide more details on how to implement these strategies effectively. This layout helps visualize the connections and importance of each approach.

    Leverage Technology for Efficient Trial Management

    In the rapidly evolving landscape of clinical research, the integration of technology is no longer optional; it’s essential for success in first in human biopharma El Salvador trials. Sponsors should consider the following tools:

    • Electronic Data Capture (EDC): This technology streamlines data collection and management, significantly reducing errors associated with manual entry. EDC systems support adherence to ICH-GCP standards and ensure that information is readily available for regulatory submissions.
    • Remote Monitoring Tools: These instruments facilitate real-time supervision of study sites, ensuring adherence and information integrity. By allowing sponsors to monitor study progress remotely, they can address issues promptly and maintain high-quality data standards.
    • Telemedicine Solutions: Telemedicine facilitates patient consultations and follow-ups, enhancing participant engagement and retention. This method is especially advantageous in El Salvador, where obtaining healthcare can be difficult, ensuring that patients stay connected throughout the study.
    • Trial Management Software: Utilizing comprehensive platforms helps manage documentation, track progress, and ensure compliance with regulatory requirements. These systems can integrate various functions, offering a cohesive approach to management that enhances operational efficiency.

    By embracing these technologies, sponsors not only streamline operations but also position themselves to lead in the competitive field of clinical research, paving the way for innovative solutions and improved patient outcomes.

    This mindmap illustrates how different technologies contribute to efficient trial management. Start at the center with the main idea, then explore each branch to see the specific tools and their benefits. Each color-coded branch helps you quickly identify the different areas of technology being discussed.

    Conclusion

    El Salvador stands out as a prime location for first-in-human biopharma trials, offering unique advantages that can significantly enhance clinical research outcomes. With expedited regulatory processes and significant cost efficiencies, sponsors can initiate studies faster than in many other regions. By leveraging the swift approval timelines of 30 to 60 days from the Superintendencia de Regulación Sanitaria (SRS) and the National Directorate of Medicines (DNM), they can gain a strategic edge. This advantage, combined with the potential for 30% lower per-patient costs compared to US and EU benchmarks, positions El Salvador as an attractive option for early-stage clinical investigations.

    What strategies can sponsors employ to succeed in this environment? Thorough preparation of essential documentation, effective patient recruitment, and the integration of advanced technology are crucial. Sponsors must ensure compliance with ICH-GCP standards and local regulations while engaging local healthcare providers and utilizing digital marketing to enhance recruitment efforts. Additionally, employing electronic data capture and remote monitoring tools can streamline trial management, ensuring high-quality data and operational efficiency.

    Conducting first-in-human trials in El Salvador is a game-changer for many sponsors. By embracing the unique advantages offered by the region, they can not only accelerate their clinical research timelines but also achieve better patient engagement and data quality. Successfully addressing these challenges not only accelerates timelines but also enhances the quality of data collected. The decision to conduct trials in El Salvador could redefine success for MedTech and Biopharma companies, paving the way for groundbreaking innovations.

    Frequently Asked Questions

    What is the regulatory authority overseeing first-in-human trials in El Salvador?

    The regulatory framework for first-in-human trials in El Salvador is supervised by the Superintendencia de Regulación Sanitaria (SRS) and the National Directorate of Medicines (DNM).

    How long does the approval process for clinical trials typically take in El Salvador?

    The approval process for clinical trials in El Salvador typically takes only 30 to 60 days, which is significantly faster than many other regions.

    What standards must be adhered to during clinical trials in El Salvador?

    Adherence to ICH-GCP (International Council for Harmonisation – Good Clinical Practice) standards is crucial to ensure ethical conduct and data integrity throughout the study process.

    What documentation is required for submitting a clinical trial application in El Salvador?

    Sponsors must prepare thorough documentation, including the study protocol, Investigator’s Brochure, and informed consent forms, which need to be submitted electronically through the SRS-CNEIS-ES platform.

    In what language must the documentation be prepared for clinical trials in El Salvador?

    All documentation must be prepared in Spanish to comply with local regulations.

    How can sponsors effectively recruit participants for clinical trials in El Salvador?

    To recruit participants effectively, it is crucial to engage with local healthcare providers and community organizations, which increases the chances of successful outcomes in research studies.

    What are the cost advantages of conducting clinical trials in El Salvador?

    Conducting studies in El Salvador can result in cost reductions of about 30% lower per-patient expenses compared to US/EU benchmarks.

    What is the strategic advantage of conducting early-stage clinical investigations in El Salvador?

    The combination of expedited regulatory approvals, lower costs, and the ability to engage with treatment-naïve patient populations makes El Salvador a strategic option for early-stage clinical investigations.

    List of Sources

    1. Understand the Regulatory Landscape for FIH Trials in El Salvador
      • 9 Affordable Clinical Trial Options in El Salvador for Startups | bioaccess® (https://bioaccessla.com/blog/9-affordable-clinical-trial-options-in-el-salvador-for-startups)
      • Conduct a First-in-Human Study in El Salvador: A Step-by-Step Guide | bioaccess® (https://bioaccessla.com/blog/conduct-a-first-in-human-study-in-el-salvador-a-step-by-step-guide)
      • The Landscape Of Medtech Clinical Research In El Salvador | Julio G. Martinez-Clark (https://linkedin.com/posts/juliomartinezclark_the-landscape-of-medtech-clinical-research-activity-7297985823382142977-ChNJ)
      • How to Conduct a First-in-Human Clinical Trial in El Salvador | bioaccess® (https://bioaccessla.com/blog/how-to-conduct-a-first-in-human-clinical-trial-in-el-salvador)
    2. Prepare Essential Documentation and Compliance Requirements
      • 4 Key Strategies for Phase 1 Clinical Trials in El Salvador | bioaccess® (https://bioaccessla.com/blog/4-key-strategies-for-phase-1-clinical-trials-in-el-salvador)
      • Conduct FIH Clinical Trials in El Salvador: A Step-by-Step Guide | bioaccess® (https://bioaccessla.com/blog/conduct-fih-clinical-trials-in-el-salvador-a-step-by-step-guide)
      • El Salvador Clinical Trial Submission Guide Released | RegDesk posted on the topic | LinkedIn (https://linkedin.com/posts/regdesk_regulatoryupdateswithregdesk-elsalvadore-activity-7402391264018604033-tpSy)
      • How to Conduct a First-in-Human Clinical Trial in El Salvador | bioaccess® (https://bioaccessla.com/blog/how-to-conduct-a-first-in-human-clinical-trial-in-el-salvador)
      • User Guide for Clinical Trial Submissions on the SRS–CNEIS-ES Platform: El Salvador 2025 (https://regdesk.co/blog/user-guide-for-clinical-trial-submissions-on-the-srs-cneis-es-platform-el-salvador-2025)
    3. Implement Effective Patient Recruitment Strategies
      • Patient Recruitment for Clinical Trials: Strategies That Actually Work (https://kapsuletech.com/blog/patient-recruitment-clinical-trials)
      • 25+ useful clinical trial recruitment statistics for better results (https://antidote.me/blog/25-useful-clinical-trial-recruitment-statistics-for-better-results)
      • Methods and perceptions of success for patient recruitment in decentralized clinical studies – PMC (https://pmc.ncbi.nlm.nih.gov/articles/PMC10643920)
      • Evaluation of factors associated with recruitment rates in early phase clinical trials based on the European Clinical Trials Register data – PMC (https://pmc.ncbi.nlm.nih.gov/articles/PMC10719455)
      • Clinical Trials Patient Recruitment in Latin America | H Clinical (https://hclinical.com/patient-recruitment)
    4. Leverage Technology for Efficient Trial Management
      • Clinical Trial Technology And Services Market Size Report, 2025-2030 (https://grandviewresearch.com/industry-analysis/clinical-trial-technology-services-market-report)
      • Clinical Trial Management System Market Statistics – 2034 (https://factmr.com/report/832/clinical-trial-management-systems-market)
      • Electronic Data Capture in Clinical Trials | Applied Clinical Trials Online (https://appliedclinicaltrialsonline.com/view/electronic-data-capture-clinical-trials)
      • AI in Clinical Trials Market Report 2024-2030, By Function, Phase, and Geo (https://marketsandmarkets.com/Market-Reports/ai-in-clinical-trials-market-42687548.html)
      • 8 key benefits of electronic data capture for clinical trials | Viedoc (https://viedoc.com/blog/key-benefits-electronic-data-capture-clinical-trials)

  • INVIMA Colombia Clinical Trial Approval: Timeline, Documents, and Common Delays

    INVIMA Colombia Clinical Trial Approval: Timeline, Documents, and Common Delays

    Colombia is one of the most frequently considered Latin American markets for clinical trial expansion. It has a large patient population, established academic medical centers, and a reasonably mature research infrastructure. But for MedTech and biopharma sponsors evaluating where to run a first-in-human or early-feasibility study, INVIMA's approval process carries a reputation worth examining honestly before you commit budget and timeline to it.

    This article covers how INVIMA clinical trial approvals actually work, what documents you need, how long the process takes, and where sponsors most often lose weeks or months to delays that could have been avoided.


    What Is INVIMA and What Does It Regulate?

    INVIMA (Instituto Nacional de Vigilancia de Medicamentos y Alimentos) is Colombia's national health regulatory authority. It oversees clinical trial authorization for drugs, biologics, and medical devices conducted on Colombian territory.

    For clinical research, INVIMA operates under Decree 2378 of 2008 and Resolution 8430 of 1993, which establish the ethical and scientific framework for human research in Colombia. Device trials also intersect with INVIMA's medical device registration framework, adding a classification review layer depending on the investigational product.

    INVIMA is not a passive registry. It conducts substantive scientific review of protocols — which is one reason timelines run longer than sponsors sometimes expect when they first look at Colombia as a LATAM option.


    INVIMA Clinical Trial Approval Timeline

    INVIMA's official review window is 30 to 60 business days from the date of an accepted submission. In practice, sponsors should plan for 4 to 9 months total elapsed time — from initial submission to authorization — once you account for document preparation, parallel institutional ethics committee (IEC) review, query resolution, and any resubmission cycles.

    Here is how the timeline typically breaks down:

    Pre-Submission and Document Preparation

    Assembling the dossier usually takes 4 to 8 weeks before submission. This phase is consistently underestimated. Missing or incorrectly formatted documents are the single most common source of delay, and INVIMA will not begin its substantive review until the submission passes an administrative completeness check.

    Institutional Ethics Committee (IEC) Review

    Colombia requires IEC approval from a recognized ethics committee at each participating site before INVIMA will issue final authorization. IEC timelines vary by institution but typically run 4 to 8 weeks. Some sponsors submit to both IEC and INVIMA simultaneously to compress the overall timeline; others wait for IEC approval first. Running them in parallel is more efficient, but it requires your protocol and consent forms to be finalized before either submission goes in.

    INVIMA Scientific Review

    Once the submission is accepted, INVIMA's scientific review team evaluates the protocol, investigator qualifications, site suitability, and the study's risk-benefit profile. This phase generates formal queries — called requerimientos — that the sponsor must respond to within a defined window. A single query round can add 4 to 8 weeks, and complex protocols sometimes generate two rounds.

    Authorization Issuance

    After satisfactory responses to all queries, INVIMA issues the clinical trial authorization. No subjects can be enrolled until this document is in hand.


    Required Documents for INVIMA Clinical Trial Submission

    The exact document list varies depending on whether the study involves a drug, biologic, or medical device, but the core dossier for most clinical trials includes:

    • Clinical study protocol (in Spanish or with a certified Spanish translation)
    • Investigator's Brochure (IB) or equivalent device description document
    • Informed consent form(s) in Spanish, compliant with Resolution 8430
    • Investigator CVs for principal investigators at each site
    • Site qualification documentation (infrastructure, equipment, staff)
    • Ethics committee approval letter from the IEC at each participating site
    • Sponsor authorization letter and legal representation documentation for the sponsor's local representative or CRO
    • Product dossier including manufacturing information, quality data, and preclinical safety summary
    • Insurance or indemnification documentation covering trial participants
    • INVIMA application form completed in the required format

    For medical device trials specifically, INVIMA may also request the device's risk classification under Colombian regulation and, in some cases, prior regulatory clearance or CE/FDA status as supporting context.

    All documents must be submitted through INVIMA's digital platform (VUE, Ventanilla Única Empresarial) in the required format. Paper submissions are no longer accepted for most trial types.


    Common Causes of Delay in INVIMA Approvals

    Knowing where approvals stall is more useful than knowing the official timeline. These are the delays sponsors run into most often:

    Incomplete or Incorrectly Formatted Submissions

    INVIMA's administrative completeness check is strict. A missing document, an incorrectly formatted file, or a translation that does not meet certification standards will result in the submission being returned. The review clock does not start until the submission clears this check.

    Protocol Language and Translation Quality

    The protocol and consent forms must be in Spanish. Machine-translated documents or low-quality translations regularly generate queries during scientific review — and errors in technical terminology can raise substantive scientific questions that take multiple rounds to resolve.

    Ethics Committee Timing Misalignment

    If IEC review at a site is delayed, INVIMA will not issue final authorization even if its own review is complete. Sponsors who treat IEC review as a sequential step after INVIMA review, rather than a parallel track, routinely add 6 to 10 weeks to their overall timeline.

    Query Response Delays

    INVIMA's formal queries must be answered within a specified window. Sponsors who are not organized to respond quickly — or who need to revise the protocol to address a query — can lose significant time. Each query round resets a portion of the review clock.

    Investigator and Site Documentation Gaps

    INVIMA scrutinizes investigator qualifications carefully. CVs that do not reflect relevant therapeutic area experience, or sites that lack documented GCP training records, frequently generate queries or requests for additional information.

    Regulatory Classification Uncertainty for Devices

    For medical device trials, INVIMA's classification of the investigational device under Colombian regulation can introduce uncertainty. If the device does not map cleanly to an existing Colombian classification, INVIMA may request additional technical documentation before proceeding with clinical trial review.


    How Colombia Compares to Other LATAM Jurisdictions

    For sponsors evaluating where to run a first-in-human or early-feasibility study, the INVIMA timeline is a meaningful planning input. The realistic 4 to 9 month window for clinical trial authorization in Colombia is significantly longer than what sponsors can achieve in certain other Latin American jurisdictions.

    In Panama, El Salvador, Chile, and the Dominican Republic, ethics and regulatory approvals are typically observed in 30 to 90 days. That gap matters when your runway is tied to a Series A milestone or a board deadline. A 6-month difference in regulatory approval timing can determine whether you have data in hand before your next funding round closes.

    This is one reason sponsors working with bioaccess® on FIH programs operate in those four jurisdictions rather than Colombia. The faster approval windows are not a workaround — Panama, El Salvador, Chile, and the Dominican Republic are established regulatory environments with qualified sites and data structured for FDA acceptance under 21 CFR 812.28 for foreign clinical data.


    What to Do If Colombia Is Still the Right Fit

    Some sponsors have specific reasons to run in Colombia: existing investigator relationships, a patient population with particular disease prevalence, or a market access strategy that makes Colombian data valuable beyond the FIH milestone. If that describes your situation, the practical steps to minimize delay are:

    1. Start document preparation 3 to 4 months before your target submission date. Certified translations and site qualification packages take longer than most teams expect.
    2. Run IEC and INVIMA submissions in parallel. Coordinate with your sites so ethics committee submissions go in at the same time as your INVIMA dossier.
    3. Engage a local regulatory affairs consultant or CRO with active INVIMA experience. Familiarity with current query patterns and administrative requirements is worth more than general LATAM regulatory knowledge.
    4. Finalize your protocol before submission. Amendments after submission restart portions of the review process.
    5. Build query response capacity into your team. Assign a dedicated person to monitor INVIMA communications and coordinate responses within the required window.

    FAQs

    What is the official INVIMA review timeline for clinical trial authorization?
    INVIMA's official review window is 30 to 60 business days from the date of accepted submission. In practice, total elapsed time from initial submission to authorization is typically 4 to 9 months when accounting for document preparation, IEC review, and query resolution rounds.

    Does Colombia require ethics committee approval before INVIMA authorization?
    Yes. INVIMA requires IEC approval from a recognized institutional committee at each participating site as part of the authorization process. Running IEC and INVIMA submissions in parallel is the most efficient way to manage overall timeline.

    What language must clinical trial documents be submitted in for INVIMA?
    The protocol, informed consent forms, and most supporting documents must be in Spanish. Certified translations are required for documents originally prepared in other languages. Low-quality translations are a common source of queries and delays.

    Can a foreign sponsor submit directly to INVIMA without a local representative?
    No. Foreign sponsors must designate a local legal representative in Colombia or engage a CRO with local legal standing to submit and manage the application on their behalf.

    What is the most common reason INVIMA submissions are delayed?
    Incomplete or incorrectly formatted submissions that fail the administrative completeness check are the most frequent cause. This prevents the substantive review clock from starting and can add weeks to the process before the sponsor receives any feedback.

    How does INVIMA's timeline compare to other Latin American jurisdictions?
    Colombia's realistic 4 to 9 month window is longer than what is achievable in jurisdictions like Panama, El Salvador, Chile, and the Dominican Republic, where ethics and regulatory approvals are typically observed in 30 to 90 days for clinical trials in those markets.

    Is INVIMA clinical trial data accepted by the FDA?
    Foreign clinical data submitted to the FDA must meet the requirements of 21 CFR 812.28 for investigational devices, or equivalent standards for drugs and biologics. Whether INVIMA-authorized Colombian trial data satisfies those requirements depends on study design, ICH-GCP compliance, and the specific submission context. Sponsors should confirm FDA alignment before initiating any study intended to support a US regulatory pathway.


    Plan Your Timeline Around the Approval Process, Not After It

    INVIMA is a capable regulatory authority, and Colombia is a legitimate clinical research market. But the approval timeline is not forgiving of late starts or incomplete submissions. If you are managing a startup runway, a 4 to 9 month regulatory approval window needs to be factored into your FIH planning from the moment you begin site selection — not after your protocol is finalized.

    If your primary goal is getting first human data within a timeline that works for your next funding round, it is worth understanding all your jurisdiction options in Latin America before defaulting to Colombia. Learn more at bioaccessla.com.


    WordPress category: Navigating Regulatory Landscapes in Latin America

  • Best Practices for Biopharma Clinical Trials in El Salvador

    Best Practices for Biopharma Clinical Trials in El Salvador

    Introduction

    While El Salvador presents a promising landscape for biopharma clinical trials, the path to success is fraught with challenges that require careful navigation. This country offers a unique blend of rapid regulatory approvals and cost efficiencies that can significantly enhance the trial process.

    With approval timelines averaging just 30 to 60 days and per-patient costs approximately 30% lower than US and EU benchmarks, sponsors can capitalize on these advantages to accelerate their research initiatives. Yet, sponsors often find themselves grappling with local regulations and patient recruitment hurdles.

    To truly harness El Salvador’s potential, sponsors must strategically address these challenges to ensure compliance and optimize enrollment.

    Understand Regulatory Frameworks for Clinical Trials in El Salvador

    In the fast-paced world of biopharma clinical trial El Salvador, understanding the regulatory framework is crucial for success. The regulatory framework for medical studies in the country is mainly supervised by the National Directorate of Medicines (DNM) and the Ministry of Health. This framework is efficient. The approval process for a biopharma clinical trial in El Salvador typically lasts only 30 to 60 days, establishing the country as one of the quickest nations in Latin America for initiating clinical studies.

    To ensure compliance, sponsors must adhere to the International Council for Harmonisation Good Clinical Practice (ICH-GCP) guidelines. This includes submitting comprehensive documentation such as:

    • The study protocol
    • Informed consent forms
    • Qualifications of the investigator

    Understanding these requirements can really speed up the approval process and ensure that all studies are conducted ethically and legally. Have you considered how collaborating with local regulatory specialists could enhance your chances of success? They can offer valuable perspectives on navigating the intricacies of the submission process, increasing the chances of a successful execution.

    Furthermore, conducting a biopharma clinical trial El Salvador can provide substantial cost reductions, with per-patient expenses roughly 30% lower than US/EU standards, making it an appealing choice for sponsors. Utilizing insights and market access strategies from bioaccess® can significantly enhance your understanding of the regulatory environment and optimize your operations in the region. Ignoring these insights could mean missed opportunities and costly delays in your clinical trials.

    This flowchart outlines the steps needed to navigate the regulatory framework for clinical trials in El Salvador. Start at the top and follow the arrows to see how each step leads to the next, culminating in the ability to conduct your clinical trial.

    Implement Effective Site Selection Strategies for Optimal Recruitment

    Many sponsors face challenges in patient enrollment, making the choice of research locations for the biopharma clinical trial in El Salvador a critical factor for success. Sponsors should concentrate on assessing historical performance metrics, patient demographics, and facility capabilities, particularly concerning INVIMA regulations and compliance requirements such as ICH-GCP.

    By leveraging the insights offered by bioaccess® through its Global Trial Accelerators™, sponsors can obtain crucial study insights and market access strategies tailored for the Latin American environment. By concentrating on locations with a proven track record in patient recruitment, sponsors can significantly boost their enrollment rates, especially considering that 80% of research studies do not meet their enrollment deadlines.

    Involving local investigators who have established connections within the community can further enhance recruitment efforts while also reducing the risks linked to high staff turnover that can disrupt study continuity. Additionally, leveraging a network of pre-qualified clinical research locations streamlines the selection process, ensuring that chosen sites are adequately equipped to meet the specific requirements of the study.

    Regular communication with site staff, coupled with ongoing training, can optimize site performance and enhance patient engagement. Moreover, conducting studies in Latin America can lead to cost reductions of about 30% lower per-patient expenses compared to US/EU benchmarks, providing a strategic edge for sponsors.

    By implementing these approaches, sponsors can navigate the complexities of research studies in the region effectively, capitalizing on the unique advantages of conducting research in Latin America.

    This flowchart outlines the steps sponsors should take for effective site selection in clinical trials. Each box represents a key factor or action, and the arrows show how they connect to create a comprehensive strategy for boosting patient enrollment.

    Develop Targeted Patient Recruitment Strategies for Local Populations

    To successfully recruit participants for the biopharma clinical trial El Salvador, sponsors must adopt culturally sensitive strategies that resonate with local communities. Involving local healthcare providers is crucial for increasing awareness about the biopharma clinical trial El Salvador and its benefits. Organizing informational sessions and utilizing popular social media platforms can significantly enhance outreach efforts.

    Trust is essential for recruitment. Collaborating with local organizations and patient advocacy groups can help build trust and encourage participation in the biopharma clinical trial El Salvador. Additionally, tailoring recruitment materials to reflect the cultural context of the target population can further improve engagement and enrollment rates. This approach respects local traditions and addresses potential barriers to participation, ultimately resulting in more favorable outcomes for studies.

    Have you considered how culturally sensitive strategies can impact recruitment rates? Studies show a remarkable increase in Hispanic recruitment from 7.0% to 39.1% (p < 0.001) when these strategies are applied. As Lindsey Ross from Cedars-Sinai Medical Center emphasizes, integrating cultural safety into recruitment materials is crucial for enhancing participation rates.

    Furthermore, employing Community-Based Participatory Research (CBPR) methods can lead to higher engagement and participation rates, ensuring that studies are relevant to community needs. Acknowledging and addressing historical mistrust can transform recruitment efforts, paving the way for more inclusive and effective studies.

    This flowchart shows the steps to effectively recruit participants for clinical trials. Each box represents a strategy, and the arrows indicate how these strategies connect and lead to better recruitment outcomes. Follow the flow to see how each step builds on the previous one!

    Leverage Technology for Efficient Clinical Trial Management

    Incorporating advanced technology into the management of research studies is not just beneficial; it’s essential for enhancing efficiency and data integrity in clinical research. Electronic data capture (EDC) systems streamline data collection. They minimize errors associated with manual entry and ensure compliance with regulatory standards such as ICH-GCP and local regulations enforced by INVIMA. These systems provide real-time data access. This allows sponsors to monitor patient progress and track adverse events instantly, which is crucial for timely interventions. Have you considered how quickly first-in-human trials can start? In El Salvador, the biopharma clinical trial el salvador can begin within just 6-8 weeks, making it a prime location for early-stage clinical trials.

    Remote monitoring tools further improve oversight of study progress, decreasing the need for frequent visits and related expenses. By enabling centralized data management, EDC systems enhance collaboration among research teams, sponsors, and sites, ensuring that all parties have access to the same up-to-date information. Furthermore, bioaccess® collaborates with Greenlight Guru for a cloud-based quality management system (QMS) and EDC integration, enhancing the credibility of these technological claims.

    Utilizing patient engagement platforms can enhance communication and boost retention rates, which is crucial for the success of research studies. Analytics tools can evaluate recruitment strategies and site performance, enabling data-driven decisions that enhance the execution of studies. Automated reporting features in EDC systems save time and reduce the risk of errors in data analysis, further illustrating the efficiency gains from using these systems. This technological integration accelerates study timelines. It also supports the goal of achieving regulatory approval efficiently, reinforcing El Salvador’s appeal for biopharma clinical trial el salvador. By embracing these technological advancements, stakeholders can significantly improve their chances of success in the competitive landscape of clinical trials.

    This flowchart shows how different technologies improve clinical trial management. Each box represents a technology or tool, and the arrows indicate how they contribute to better efficiency and data integrity in clinical research.

    Conclusion

    El Salvador is emerging as a pivotal hub for biopharma clinical trials, especially for first-in-human studies. Rapid regulatory approval processes, cost efficiency, and effective patient recruitment strategies make El Salvador an attractive option for sponsors aiming to expedite their clinical research. By leveraging the unique advantages of conducting trials in this region, stakeholders can significantly enhance their operational efficiency and overall success.

    Key insights from the article highlight the importance of understanding the regulatory frameworks governed by INVIMA and the Ministry of Health, which facilitate swift approvals within 30 to 60 days. Additionally, implementing targeted site selection and culturally sensitive patient recruitment strategies can dramatically improve enrollment rates, addressing the common challenges faced in clinical trials. The integration of advanced technology, such as electronic data capture systems and remote monitoring tools, further streamlines trial management, ensuring compliance and enhancing data integrity.

    In conclusion, embracing the opportunities presented by El Salvador for biopharma clinical trials can lead to substantial benefits, including reduced costs and accelerated timelines. Focusing on local engagement and using technology can help sponsors tackle the complexities of clinical research more smoothly. The strategic advantages of conducting trials in El Salvador could redefine success for sponsors in the biopharma sector.

    Frequently Asked Questions

    What is the regulatory authority overseeing clinical trials in El Salvador?

    The regulatory framework for medical studies in El Salvador is mainly supervised by the National Directorate of Medicines (DNM) and the Ministry of Health.

    How long does the approval process for a biopharma clinical trial typically take in El Salvador?

    The approval process for a biopharma clinical trial in El Salvador typically lasts only 30 to 60 days, making it one of the quickest nations in Latin America for initiating clinical studies.

    What guidelines must sponsors adhere to for compliance in clinical trials in El Salvador?

    Sponsors must adhere to the International Council for Harmonisation Good Clinical Practice (ICH-GCP) guidelines.

    What documentation is required for submitting a clinical trial in El Salvador?

    Required documentation includes the study protocol, informed consent forms, and qualifications of the investigator.

    How can local regulatory specialists assist sponsors in El Salvador?

    Collaborating with local regulatory specialists can enhance the chances of success by providing valuable perspectives on navigating the intricacies of the submission process.

    What are the cost benefits of conducting biopharma clinical trials in El Salvador?

    Conducting a biopharma clinical trial in El Salvador can provide substantial cost reductions, with per-patient expenses roughly 30% lower than US/EU standards.

    How can bioaccess® help sponsors optimize their operations in El Salvador?

    Utilizing insights and market access strategies from bioaccess® can significantly enhance understanding of the regulatory environment and optimize operations in the region.

    List of Sources

    1. Understand Regulatory Frameworks for Clinical Trials in El Salvador
      • 4 Key Strategies for Phase 1 Clinical Trials in El Salvador | bioaccess® (https://bioaccessla.com/blog/4-key-strategies-for-phase-1-clinical-trials-in-el-salvador)
      • 9 Affordable Clinical Trial Options in El Salvador for Startups | bioaccess® (https://bioaccessla.com/blog/9-affordable-clinical-trial-options-in-el-salvador-for-startups)
      • User Guide for Clinical Trial Submissions on the SRS–CNEIS-ES Platform: El Salvador 2025 (https://regdesk.co/blog/user-guide-for-clinical-trial-submissions-on-the-srs-cneis-es-platform-el-salvador-2025)
      • Conducting clinical trials in El Salvador: ethical considerations and opportunities. | Julio G. Martinez-Clark posted on the topic | LinkedIn (https://linkedin.com/posts/juliomartinezclark_the-untapped-potential-of-clinical-trials-activity-7307430545007759361-jdhR)
      • Achieve Fast Clinical Trial Approval in El Salvador: A Step-by-Step Guide | bioaccess® (https://bioaccessla.com/blog/achieve-fast-clinical-trial-approval-in-el-salvador-a-step-by-step-guide)
    2. Implement Effective Site Selection Strategies for Optimal Recruitment
      • Clinical Trial Site Selection: The Essential Guide for Sponsors (https://clinvigilant.com/blog/clinical-trial-site-selection-essential-guide-sponsors)
      • Strategies for Successful Site Selection in Clinical Trials (https://advarra.com/blog/strategies-for-successful-site-selection-in-clinical-trials)
      • Optimizing Site Selection and Management for Clinical Trial Success (https://studypages.com/blog/optimizing-site-selection-and-management-for-clinical-trial-success)
      • Portfolio Approach to Optimize Site Selection | Applied Clinical Trials Online (https://appliedclinicaltrialsonline.com/view/portfolio-approach-optimize-site-selection-0)
    3. Develop Targeted Patient Recruitment Strategies for Local Populations
      • How cultural safety boosts clinical trial patient recruitment  – COUCH Health (https://couch.health/how-cultural-safety-boosts-clinical-trial-patient-recruitment)
      • Bridging the Gap: Culturally Responsive Strategies for NIH Trial Recruitment – PMC (https://pmc.ncbi.nlm.nih.gov/articles/PMC12644225)
      • Enrollment in Clinical Trials: Statistics and Patient Recruitment Strategies | Power (https://withpower.com/guides/enrollment-in-clinical-trials-statistics-and-patient-recruitment-strategies)
      • 7 Effective Enrollment Strategies for Global Patient Recruitment – Splash Clinical (https://splashclinical.com/global-patient-recruitment-strategies)
    4. Leverage Technology for Efficient Clinical Trial Management
      • Benefits of Using an Electronic Data Capture (EDC) System in Clinical Trials (https://minervaresearchsolutions.com/blogs/electronic-data-capture-system-in-clinical-trials)
      • Clinical Trial Technology And Services Market Size Report, 2025-2030 (https://grandviewresearch.com/industry-analysis/clinical-trial-technology-services-market-report)
      • Benefits of Electronic Data Capture in Clinical Trials (https://clincapture.com/benefits-of-electronic-data-capture)
      • 8 key benefits of electronic data capture for clinical trials | Viedoc (https://viedoc.com/blog/key-benefits-electronic-data-capture-clinical-trials)
      • Clinical Trial Management System Market Statistics – 2034 (https://factmr.com/report/832/clinical-trial-management-systems-market)

  • 10 Key Insights for Your Medical Device Study in El Salvador

    10 Key Insights for Your Medical Device Study in El Salvador

    Introduction

    As the landscape of clinical research evolves, El Salvador stands out as a game-changer for medical device studies. This country offers a unique blend of regulatory efficiency and cost-effectiveness that can significantly enhance clinical trial outcomes. With approval timelines as short as 30 to 60 days and per-patient costs approximately 30% lower than in the U.S. and EU, researchers can capitalize on the region’s advantages while navigating local regulations, which can be a daunting task.

    What strategies can researchers adopt to thrive in this evolving landscape? This article will outline ten essential strategies that can empower researchers to conduct effective medical device studies in El Salvador, providing actionable insights that can streamline processes and optimize results.

    Understand Regulatory Requirements in El Salvador

    Understanding the regulatory landscape in El Salvador is crucial for researchers aiming to conduct a medical device study in El Salvador efficiently. El Salvador’s regulatory structure for medical research is supervised by the Dirección Nacional de Medicamentos (DNM). Sponsors must submit a comprehensive clinical study protocol that includes:

    1. Ethical approvals
    2. Adherence to ICH-GCP standards

    The approval process is efficient. It typically takes between 30 to 60 days, making El Salvador an attractive option for researchers looking to conduct a medical device study in El Salvador. Navigating local regulations can be daunting for researchers, yet it is vital for compliance and timely study initiation. Furthermore, conducting studies in Latin America can lead to cost reductions of about 30% lower per-patient expenses compared to US/EU benchmarks, making it a financially beneficial option. By utilizing bioaccess®’s Global Trial Accelerators™, researchers can transform potential regulatory hurdles into streamlined pathways for their medical device study in El Salvador and throughout Latin America. Embracing these insights can significantly enhance the success of clinical trials in El Salvador and beyond.

    This flowchart outlines the steps researchers need to take to navigate the regulatory landscape in El Salvador. Start at the top with understanding the requirements, then follow the arrows to see what needs to be submitted and the expected timeline for approval.

    Select Optimal Clinical Trial Sites for Efficiency

    Navigating the complexities of site selection can be daunting for organizations, especially in a dynamic landscape like El Salvador, particularly for a medical device study in El Salvador. Choosing optimal research sites necessitates a comprehensive assessment of several crucial factors, including:

    1. Investigator expertise
    2. Patient demographics
    3. Site infrastructure

    With a network of over 50 pre-qualified clinical research sites, bioaccess® is well-positioned to assist organizations in identifying locations in El Salvador that meet their specific medical device study requirements. Historical performance data of sites should be a primary consideration, as it provides insights into their past success rates and operational capabilities.

    Furthermore, access to target patient groups is essential for ensuring effective study execution, as it directly influences recruitment timelines and overall research efficiency. Logistical capabilities, including the site’s ability to manage patient travel and retention, should also be assessed to mitigate potential delays in recruitment.

    Ryan Monte, Director of Marketing, emphasizes that “Travel can be a perceived burden for patients, potentially delaying recruitment.” By concentrating on these aspects, organizations can significantly enhance their chances of success in clinical trials.

    This mindmap starts with the main idea of selecting clinical trial sites at the center. Each branch represents a key factor to consider, and the sub-branches provide more details about what to look for in each area. It's a visual guide to help you understand how these factors connect and contribute to successful clinical trials.

    Implement Effective Patient Recruitment Strategies

    To enhance patient recruitment in El Salvador, sponsors must navigate significant geographical barriers and engage local communities effectively. Effective strategies include:

    1. Hosting informational sessions to educate potential participants about the study.
    2. Utilizing targeted social media campaigns to reach broader audiences.
    3. Collaborating with local physicians to raise awareness and trust in the research.

    With many potential participants living far from research centers, how can sponsors effectively bridge this gap? Significantly, around 70% of potential clinical study participants reside more than two hours from a research center, emphasizing the necessity of local engagement strategies.

    Employing culturally sensitive materials can address potential barriers to participation. How can this approach foster a diverse patient population in the study? Addressing low health literacy is also essential, as it ensures that potential participants comprehend the study and feel at ease engaging with it. This approach fosters community involvement and meets the compliance standards set by INVIMA, enabling a more seamless route to study execution.

    Thanks to bioaccess®’s expertise, sponsors can effectively navigate the complexities of clinical studies in Latin America, benefiting from expedited timelines and cost efficiencies that are approximately 30% lower per patient compared to US/EU benchmarks. Furthermore, comprehending the distinctions between First-in-Human (FIH) and Early Feasibility Studies (EFS) is crucial, as FIH assessments evaluate a medical device or drug in humans for the first time, while EFS examines design concepts in a limited number of subjects. Understanding these dynamics not only streamlines recruitment but also fosters a more inclusive approach to clinical research.

    This mindmap starts with the central idea of patient recruitment strategies and branches out into specific methods. Each branch represents a different strategy, and the sub-branches provide more detail on how to implement these strategies effectively. Follow the branches to see how each strategy connects to the overall goal of enhancing patient recruitment.

    Ensure Compliance with ICH-GCP Standards

    Navigating the complexities of clinical research in El Salvador requires unwavering commitment to ICH-GCP guidelines. All clinical studies conducted here must comply with the International Council for Harmonisation Good Clinical Practice (ICH-GCP) standards. This compliance encompasses critical aspects such as:

    Adhering to these standards safeguards participant rights and boosts the credibility of your data, paving the way for smoother submissions and approvals.

    INVIMA, the national authority, mandates strict adherence to ICH-GCP, which is vital for upholding high standards in research. By emphasizing ICH-GCP adherence, organizations can enhance the efficiency of their clinical studies and increase the chances of favorable outcomes. However, without strict adherence to these guidelines, organizations risk jeopardizing their research integrity and future opportunities.

    The central node represents the main focus on ICH-GCP compliance. Each branch shows a critical aspect of compliance, and the sub-branches provide more details on what needs to be done to adhere to these standards. This visual helps you see how each part contributes to the overall goal of maintaining high research standards.

    Leverage bioaccess® for Streamlined Trial Execution

    In the fast-evolving landscape of clinical research, the need for efficient and compliant trial execution has never been more critical. Bioaccess® offers an extensive range of services specifically crafted for first-in-human studies, including:

    Collaborating with bioaccess® allows organizations to streamline their trial execution process. They can achieve activation timelines that are typically 40% faster than in traditional markets. With deep local knowledge, the CRO ensures that compliance obligations are met, allowing clients to focus on what truly matters.

    This efficiency is particularly evident in the medical device study El Salvador, where regulatory approval timelines can be as short as 1-3 months, significantly enhancing the feasibility of studies compared to the 12-18 months often seen in the U.S. and EU. Furthermore, the cost advantages in Latin America are notable, with ethics committee fees ranging from $500 to $3,000, which are significantly lower than the $5,000 to $25,000 fees in the U.S. and EU. Additionally, backers can benefit from roughly 30% reduced per-patient expenses in Latin America, which enhances the feasibility of the medical device study El Salvador.

    By utilizing bioaccess®’s capabilities, sponsors can not only save time and costs but also ensure high-quality, regulatory-grade evidence that supports their strategic goals. As highlighted by Martine Dehlinger-Kremer, PhD, “CROs play a crucial role in delivering the essential expertise, resources, and support to conduct research and introduce new drugs to the market,” emphasizing the important function bioaccess® serves in enabling successful studies.

    By leveraging bioaccess®’s expertise, organizations can transform their clinical research approach, ensuring they remain competitive in a rapidly changing market.

    This mindmap shows how bioaccess® services connect to improve clinical trial execution. Each branch represents a key service, and the sub-branches detail specific aspects or benefits. Follow the branches to understand how these services work together to enhance efficiency and compliance.

    Analyze Local Market Dynamics and Healthcare Infrastructure

    El Salvador‘s healthcare system presents a unique opportunity for clinical research, blending public and private sectors to support innovative studies. With a population of approximately 6.4 million, the country boasts a significant urban demographic, which is crucial for patient recruitment. To design effective trials, it’s crucial to understand local market dynamics. This includes the prevalence of target conditions and healthcare access. Sponsors should evaluate the availability of medical facilities and the overall healthcare infrastructure to optimize patient recruitment and ensure robust data collection.

    Navigating the evolving regulatory landscape can be a challenge for sponsors, as frameworks are aligning more closely with international standards. Compliance with ICH-GCP guidelines and oversight from regulatory authorities such as the Ministry of Health are essential. With these insights, stakeholders can refine their strategies for conducting successful medical device studies in El Salvador.

    Significantly, with bioaccess®, trial approvals can be obtained in just 4-8 weeks, much quicker than the 6+ months usually needed in the US and EU. This accelerated timeline not only enables faster access to medical data for investor meetings or FDA Pre-Submissions but also results in significant cost reductions of around $25K per patient. This allows organizations to reinvest those savings into R&D or other funding milestones. By leveraging bioaccess®’s expertise, sponsors can improve their research strategies and take advantage of the cost-effective opportunities available in El Salvador. Embracing bioaccess® not only streamlines trial approvals but also positions sponsors to capitalize on the burgeoning opportunities within El Salvador’s healthcare landscape.

    This mindmap starts with the central theme of healthcare dynamics in El Salvador. Each branch represents a key area of focus, and the sub-branches provide more detailed insights. Follow the branches to explore how these elements interact and contribute to the opportunities in clinical research.

    Build Relationships with Local Regulatory Authorities

    In the fast-paced world of clinical research, establishing strong ties with local regulatory bodies is essential for success in the medical device study El Salvador. Building robust connections with local oversight bodies, such as the Superintendencia de Regulación Sanitaria (SRS) and the Dirección Nacional de Medicamentos (DNM), is crucial for the successful implementation of the medical device study El Salvador. Sponsors should engage in proactive communication by attending oversight meetings and seeking feedback on study protocols.

    How can a collaborative approach foster trust and lead to expedited approvals through the fast-track review process? This approach can allow for approvals in specific countries within 55 working days.

    Importantly, approvals for the medical device study El Salvador can be finalized within 30-60 days, greatly improving the pace of study initiation while also gaining from cost efficiencies, as research can be carried out at roughly 30% lower expenses compared to the U.S. and EU. Without these connections, sponsors risk delays that could hinder study initiation and increase costs. By prioritizing these connections, sponsors can navigate the compliance environment more effectively, ensuring adherence to International Council for Harmonisation Good Clinical Practice (ICH-GCP) guidelines and optimizing their study outcomes. It’s wise to schedule regular meetings with local oversight bodies to keep up with any changes in requirements.

    Utilizing insights from bioaccess®’s Global Trial Accelerators™ can further improve your comprehension of market access strategies and compliance updates, positioning your studies for success in the dynamic landscape of Latin America. For instance, leveraging bioaccess®’s expertise can help streamline the submission process and ensure that all necessary documentation is in order, ultimately reducing delays and enhancing the likelihood of timely approvals. By leveraging local insights and expertise, sponsors can not only enhance their approval timelines but also position their studies for greater success in a competitive market.

    This flowchart shows the steps to successfully engage with local regulatory bodies. Follow the arrows to see how each action leads to either expedited approvals or potential delays. The green steps indicate positive actions that can speed up the process, while the red step highlights the risks of not engaging effectively.

    Implement Robust Data Management and Monitoring Practices

    In the competitive landscape of clinical research, effective data management is a pillar of integrity and quality in the medical device study El Salvador. Sponsors should adopt standardized data collection protocols and leverage electronic data capture (EDC) systems to streamline processes. Regular audits play a crucial role in spotting discrepancies and ensuring compliance with ICH-GCP standards and local laws enforced by INVIMA. Ongoing assessment of data quality improves the dependability of study outcomes and facilitates successful regulatory submissions, achievable in as little as 30-90 days.

    Imagine reducing your study costs while ensuring high-quality data. Implementing these practices can help control study costs. For budgeting, bioaccess® publishes sample first-in-human budgets of about $430K for a 20-subject minimally invasive device study and about $1.32M for a 10-subject surgical implant study (illustrative, not a quote; see bioaccessla.com/sample-budget-fih-trial-latin-america). That makes the medical device study El Salvador an attractive option for early-stage studies.

    Additionally, bioaccess® simplifies the entire process, allowing studies to start within 6-8 weeks and deliver FDA-bridgeable data about 40% faster than traditional methods. Embracing these strategies not only enhances data quality but also positions sponsors for success in a rapidly evolving market.

    This flowchart illustrates the steps to implement effective data management in clinical research. Start with robust practices, follow through with standardized protocols and audits, and see how these lead to better data quality and compliance, ultimately benefiting your study outcomes.

    Invest in Training for Clinical Research Staff

    Investing in training for clinical research personnel is not just beneficial; it’s essential for the successful execution of medical device study El Salvador and throughout Latin America. It is imperative to provide continuous education and resources to keep staff informed about best practices and compliance changes, especially in navigating the compliance landscapes of Colombia and Mexico.

    Navigating the complex compliance landscapes of Colombia and Mexico presents significant challenges for clinical research personnel. Mastering these processes significantly enhances study efficiency and reduces expenses, with per-patient costs in Latin America being roughly 30% less than US/EU standards. An impressive 96.1% of technical personnel actively pursue courses related to their profession, demonstrating a strong commitment to continuous learning.

    Personnel who receive thorough training are empowered to manage studies with greater effectiveness and precision, leading to enhanced data quality and participant safety throughout the research. In El Salvador, where regulatory pathways are streamlined through agencies like COFEPRIS, prioritizing staff training can significantly enhance the medical device study El Salvador outcomes and expedite the route to market.

    As W. Edwards Deming aptly stated, “Without data, you’re just another person with an opinion,” underscoring the necessity of informed training practices. To implement effective training programs, sponsors should consider developing tailored resources that address the specific needs of their staff, ensuring compliance with local regulations and enhancing overall study success. By prioritizing tailored training programs, sponsors can ensure compliance and drive the success of their studies in a competitive market.

    The central node represents the main focus on training. Each branch highlights a key area related to training, and the sub-branches provide more detailed insights. This structure helps visualize how training impacts various aspects of clinical research.

    Collaborate with Local Universities and Research Institutions

    In the realm of clinical research, collaboration with local universities and research institutions in El Salvador is essential for the success of the medical device study El Salvador. Collaborating with local universities and research institutions grants access to invaluable resources and specialized knowledge, enhancing the quality of research studies. As noted by Dinma Okorie, effective collaboration unites diverse perspectives, fostering innovative solutions in research.

    By incorporating insights from academic research, funding entities can promote innovation and enhance study design and execution. By aligning partnerships with trial objectives, sponsors can harness the strengths of local institutions, resulting in more efficient and effective clinical research outcomes.

    This mindmap illustrates how collaborating with local universities and research institutions can enhance clinical research. Each branch represents a key benefit or insight, showing how they connect back to the central theme of collaboration.

    Conclusion

    El Salvador stands out as a prime location for medical device studies, offering a unique blend of regulatory efficiency and cost-effectiveness that can transform clinical research outcomes. Sponsors who grasp local regulatory requirements and collaborate with specialized organizations like bioaccess® will master the complexities of clinical trials. The streamlined approval timelines, often ranging from 30 to 60 days, coupled with the opportunity for substantial cost savings – up to 30% less per patient than US and EU benchmarks – cannot be overlooked.

    It’s clear that selecting the right clinical trial sites and implementing effective patient recruitment strategies are crucial for success. Engaging with local regulatory authorities and investing in training for clinical research staff further enhance the likelihood of successful outcomes. Collaborations with local universities and research institutions can also provide invaluable resources and insights, fostering innovation and improving study design.

    In conclusion, embracing the unique opportunities in El Salvador will elevate the success of your medical device studies. By prioritizing local engagement, compliance, and strategic partnerships, sponsors can not only expedite their clinical trials but also position themselves advantageously in a competitive market. The strategic advantages of conducting trials in El Salvador could redefine your approach to clinical research, ensuring you stay ahead in the rapidly evolving MedTech landscape.

    Frequently Asked Questions

    What is the regulatory authority overseeing medical device studies in El Salvador?

    The regulatory authority overseeing medical device studies in El Salvador is the Dirección Nacional de Medicamentos (DNM).

    What are the key requirements for submitting a clinical study protocol in El Salvador?

    Sponsors must submit a comprehensive clinical study protocol that includes ethical approvals and adherence to ICH-GCP standards.

    How long does the approval process typically take for clinical studies in El Salvador?

    The approval process typically takes between 30 to 60 days.

    What are the financial benefits of conducting clinical trials in El Salvador compared to the US/EU?

    Conducting studies in El Salvador can lead to cost reductions of about 30% lower per-patient expenses compared to US/EU benchmarks.

    How can bioaccess® assist researchers in navigating regulatory requirements in El Salvador?

    Bioaccess® offers Global Trial Accelerators™ to help researchers transform potential regulatory hurdles into streamlined pathways for their medical device studies.

    What factors should organizations consider when selecting clinical trial sites in El Salvador?

    Organizations should consider investigator expertise, patient demographics, and site infrastructure when selecting clinical trial sites.

    How many pre-qualified clinical research sites does bioaccess® have in El Salvador?

    Bioaccess® has a network of over 50 pre-qualified clinical research sites in El Salvador.

    Why is access to target patient groups important for clinical trials?

    Access to target patient groups is essential for ensuring effective study execution, as it directly influences recruitment timelines and overall research efficiency.

    What strategies can sponsors use to enhance patient recruitment in El Salvador?

    Sponsors can enhance patient recruitment by hosting informational sessions, utilizing targeted social media campaigns, and collaborating with local physicians.

    What percentage of potential clinical study participants in El Salvador live more than two hours from a research center?

    Approximately 70% of potential clinical study participants reside more than two hours from a research center.

    How can culturally sensitive materials improve patient recruitment?

    Culturally sensitive materials can address potential barriers to participation and foster a diverse patient population in the study.

    What is the difference between First-in-Human (FIH) studies and Early Feasibility Studies (EFS)?

    FIH studies evaluate a medical device or drug in humans for the first time, while EFS examines design concepts in a limited number of subjects.

    List of Sources

    1. Understand Regulatory Requirements in El Salvador
      • Master Early Feasibility Study in El Salvador: A Step-by-Step Guide | bioaccess® (https://bioaccessla.com/blog/master-early-feasibility-study-in-el-salvador-a-step-by-step-guide)
      • User Guide for Clinical Trial Submissions on the SRS–CNEIS-ES Platform: El Salvador 2025 (https://regdesk.co/blog/user-guide-for-clinical-trial-submissions-on-the-srs-cneis-es-platform-el-salvador-2025)
      • 9 Affordable Clinical Trial Options in El Salvador for Startups | bioaccess® (https://bioaccessla.com/blog/9-affordable-clinical-trial-options-in-el-salvador-for-startups)
      • Changes in the Latin American Clinical Trial Regulatory Environment | PPD Inc (https://ppd.com/blog/positive-changes-in-the-latin-american-clinical-trial-regulatory-environment)
      • Achieve Fast Clinical Trial Approval in El Salvador: A Step-by-Step Guide | bioaccess® (https://bioaccessla.com/blog/achieve-fast-clinical-trial-approval-in-el-salvador-a-step-by-step-guide)
    2. Select Optimal Clinical Trial Sites for Efficiency
      • Site-Driven Metrics: Operational Data To Improve Research (https://advarra.com/blog/site-driven-metrics-operational-data-to-improve-research)
      • How Sponsors Can Use Clinical Trial Performance Metrics When Collaborating with Sites | OneStudyTeam (https://onestudyteam.com/blog/sponsors-use-clinical-trial-performance-metrics-collaborating-sites)
      • Clinical Trial Site Selection: Process & Best Practices (https://syncora.com/blogs/clinical-trial-site-selection)
    3. Implement Effective Patient Recruitment Strategies
      • 25+ useful clinical trial recruitment statistics for better results (https://antidote.me/blog/25-useful-clinical-trial-recruitment-statistics-for-better-results)
      • Clinical studies: the challenge of patient recruitment (https://servier.com/en/newsroom/clinical-studies-patient-recruitment)
      • 10 Inspiring Patient Experience Quotes | Relias (https://relias.com/blog/patient-experience-quotes)
      • Enrollment in Clinical Trials: Statistics and Patient Recruitment Strategies | Power (https://withpower.com/guides/enrollment-in-clinical-trials-statistics-and-patient-recruitment-strategies)
      • Patient Engagement Quotes: For Every Purpose & Audience (https://nclusiv.co.uk/edi-consulting/f/patient-engagement-quotes-for-every-purpose-audience)
    4. Ensure Compliance with ICH-GCP Standards
      • Master ICH-GCP Compliance for Clinical Trials in Colombia | bioaccess® (https://bioaccessla.com/blog/master-ich-gcp-compliance-for-clinical-trials-in-colombia)
      • The Effects the ICH E6(R3) Updates Will Have on Good Clinical Practice (https://quanticate.com/blog/ich-e6-r3-good-clinical-practice-updates)
      • El Salvador Clinical Trial Submission Guide Released | RegDesk posted on the topic | LinkedIn (https://linkedin.com/posts/regdesk_regulatoryupdateswithregdesk-elsalvadore-activity-7402391264018604033-tpSy)
      • ICH E6 Good clinical practice – Scientific guideline | European Medicines Agency (EMA) (https://ema.europa.eu/en/ich-e6-good-clinical-practice-scientific-guideline)
    5. Leverage bioaccess® for Streamlined Trial Execution
      • Turbocharging Clinical Trial Activation Timelines (https://advarra.com/resources/turbocharging-clinical-trial-activation-timelines)
      • Ways to Lower Costs of Clinical Trials and How CROs Help (https://americanpharmaceuticalreview.com/Featured-Articles/185929-Ways-to-Lower-Costs-of-Clinical-Trials-and-How-CROs-Help)
      • COVID-19 Pandemic Exemplifies the Benefits of CROs | Applied Clinical Trials Online (https://appliedclinicaltrialsonline.com/view/covid-19-pandemic-exemplifies-the-benefits-of-cros)
      • Full Service CRO: Complete Guide for Sponsors| Cromos Pharma (https://cromospharma.com/full-service-cros-in-2026)
      • Costs & Timelines | bioaccess® (https://bioaccessla.com/costs-and-timelines)
    6. Analyze Local Market Dynamics and Healthcare Infrastructure
      • Conducting clinical trials in El Salvador: ethical considerations and opportunities. | Julio G. Martinez-Clark posted on the topic | LinkedIn (https://linkedin.com/posts/juliomartinezclark_the-untapped-potential-of-clinical-trials-activity-7307430545007759361-jdhR)
      • Sage Reference – Health Care Systems Around the World: A Comparative Guide – El Salvador (https://sk.sagepub.com/book/mono/healthcare-systems-around-the-world/chpt/el-salvador)
      • Healthcare Resource Guide – El Salvador (https://trade.gov/healthcare-resource-guide-el-salvador)
      • El Salvador (https://data.who.int/countries/222)
    7. Build Relationships with Local Regulatory Authorities
      • Navigate Clinical Trials: Choose the Right CRO in El Salvador | bioaccess® (https://bioaccessla.com/blog/navigate-clinical-trials-choose-the-right-cro-in-el-salvador)
      • Clinical Trial Regulatory Approval Latin America: 4 Proven Timelines (https://fomatmedical.com/blogs-updates/clinical-trial-regulatory-approval-latin-america)
      • Changes in the Latin American Clinical Trial Regulatory Environment | PPD Inc (https://ppd.com/blog/positive-changes-in-the-latin-american-clinical-trial-regulatory-environment)
      • Best Practices for Building Strong Regulatory Relationships white paper | PPD (https://ppd.com/resource/best-practices-for-building-strong-regulatory-relationships-white-paper)
    8. Implement Robust Data Management and Monitoring Practices
      • Importance of Clinical Data Management in Clinical Trials (https://sofpromed.com/importance-of-clinical-data-management-in-clinical-trials)
      • Quantifying Data Quality for Clinical Trials Using Electronic Data Capture – PMC (https://pmc.ncbi.nlm.nih.gov/articles/PMC2516178)
      • The Role of Data Management in Clinical Trials | ICON news and blogs (https://careers.iconplc.com/blogs/2024-4/the-role-of-data-management-in-clinical-trials)
      • The Ultimate Guide to Electronic Data Capture for Clinical Trials (https://quanticate.com/blog/electronic-data-capture-systems-in-clinical-trials)
    9. Invest in Training for Clinical Research Staff
      • Famous Quotes on Research and Well-Being – Center for the Advancement of Well-Being (https://wellbeing.gmu.edu/famous-quotes-on-research-and-well-being)
      • 70 Research Quotes to Inspire Your Work – Qualtrics (https://qualtrics.com/articles/strategy-research/research-quotes)
      • Web-based training and certification of clinical staff during the randomised clinical trial SafeBoosC-III – Trials (https://link.springer.com/article/10.1186/s13063-024-08530-x)
      • Training needs of health personnel in El Salvador and perceived barriers: keys to strengthening regional virtual training | Pan American Journal of Public Health (https://journal.paho.org/en/articles/training-needs-health-personnel-salvador-and-perceived-barriers-keys-strengthening)
    10. Collaborate with Local Universities and Research Institutions
    • The Importance of Effective Collaboration in Clinical Research and How Probe Facilitates It (https://infiuss.com/insights/the-importance-of-effective-collaboration-in-clinical-research-and-how-probe-facilitates-it)
    • Current State and Needs of Clinical Laboratories in Latin America: A Cross-Country Assessment (https://academic.oup.com/jalm/article/11/4/927/8513316)
    • The Pros and Cons of Academic Partnerships in Clinical Research (https://clinicaltrialsarena.com/news/the-pros-and-cons-of-academic-partnerships-in-clinical-research-4988891-2)