Tag: Mexico

  • The legal architecture of Latin American post-trial access: SDEA, DPA, product liability, sponsor accession

    A Latin American post-trial access (PTA) program is a regulatory filing wrapped in four contracts. The filing is the visible part — an ANMAT import expediente, an ANVISA ofício, a DIGEMID authorization. The four contracts are what determine who answers to a regulator, who answers to a patient, and who answers to a plaintiff’s lawyer three years after the last shipment.

    Those four instruments are a Safety Data Exchange Agreement, a country-specific Data Processing Agreement, a product-liability allocation, and — the one most often missing — a sponsor accession mechanism that binds the marketing-authorization holder to the same schedules the operator signed. This piece sets out how we paper each of them and the five architectural mistakes that recur in draft PTA agreements we review.

    Why the paperwork carries more weight than the filing

    In nine Latin American jurisdictions the continued-supply duty is statutory and sits on the sponsor. Brazil’s Lei nº 14.874/2024 Art. 31 §4 states that “o fornecimento do medicamento será de responsabilidade do patrocinador,” and Art. 33 inciso VI releases the sponsor only five years after commercial availability in Brazil. Chile’s Código Sanitario Art. 111 C, inserted by Art. 34 of Ley 20.850, attaches the free-supply duty to the holder of the provisional-use authorization and then to the sanitary-registration holder — including a successor that acquired the registration later. Peru’s DS 021-2017-SA Art. 40(p) and Art. 89 put both the access duty and the funding on the sponsor. Panama’s Decreto Ejecutivo 21/2026 Art. 68 (Gaceta Oficial Digital 30510-C, 23 April 2026, which reglamentates Titles III and IV of Ley 84 de 14 de mayo de 2019) names investigadores y patrocinadores as co-obligors.

    None of those statutes names an operator, an importadora, or a managed-access vendor. The obligation is the sponsor’s by law. Everything the operator does — the import authorization under Disposición ANMAT 12792/2016 Art. 4, the cold-chain leg, the pharmacovigilance intake — is performed on behalf of an obligor that remains the obligor. If the contract does not say so with precision, the operator has effectively assumed a statutory duty it has no legal standing to discharge.

    Pillar 1: the Safety Data Exchange Agreement

    The SDEA is the instrument that connects local adverse-event intake to the sponsor’s global pharmacovigilance system. It should be executed within 30 days of the Work Order, not left to a later “PV annex to follow.”

    Three ICH guidelines set the substance. ICH E2A fixes the expedited-reporting clock: fatal or life-threatening unexpected adverse drug reactions require notification “as soon as possible but no later than 7 calendar days after first knowledge by the sponsor,” followed by a fuller report “within 8 additional calendar days” (§III.B.1), while all other serious unexpected ADRs run on a 15-calendar-day clock (§III.B.2). Because the clock starts on sponsor knowledge, the SDEA must set an internal onward-transmission deadline for the local operator that is materially shorter — otherwise the sponsor’s regulatory clock is being consumed by the operator’s intake queue. ICH E2F governs periodic reporting: the DSUR is an annual report with a data lock point on “the last day of the one-year reporting period” and submission “no later than 60 calendar days after the DSUR data lock point” (§2.2), so the SDEA must specify who supplies PTA-cohort line listings into that cycle and by when. ICH E3 §12 sets the safety-evaluation structure the underlying trial report already follows, which is the format PTA safety data should feed into rather than a parallel one.

    Practical drafting points: name the sponsor’s global PV mailbox and the operator’s PV contact by role, define the reconciliation cadence, and state expressly that regulatory reporting to the local authority is the sponsor’s obligation performed through the operator as agent, with the operator’s duty limited to timely, accurate onward transmission.

    Pillar 2: the Data Processing Agreement — country by country

    There is no single Latin American data-protection instrument, so there is no single DPA. The controlling article set changes by jurisdiction:

    Jurisdiction Instrument Transfer article Notes for PTA drafting
    Argentina Ley 25.326 Art. 12(1)–(2) Transfer to countries without adequate protection is prohibited; Art. 12(2)(b) carves out medical-data exchange where the affected person’s treatment requires it. Art. 11(4) makes the transferee subject to the transferor’s obligations and imposes joint liability.
    Argentina (clauses) AAIP Resolución 198/2023 Anexo I Approves two model clause sets: responsable–responsable and responsable–encargado. Use the latter where the operator processes only on sponsor instruction (Cláusula 6.1).
    Brazil Lei nº 13.709/2018 (LGPD) Arts. 33–36 Art. 33 II(a)–(b) permits transfer on specific or standard contractual clauses; Art. 33 VIII permits it on specific, highlighted consent distinguished from other purposes.
    Mexico LFPDPPP (DOF 20 March 2025) Arts. 35–36 Health data is sensitive (Art. 2 fr. VI) and requires express written consent (Art. 8). Art. 36 fr. II exempts transfers necessary for medical treatment or health-service management.
    Chile Ley 19.628Ley 21.719 Art. 10 → Arts. 27–29 Ley 21.719 was published 13 December 2024 and enters into force 1 December 2026. Any Chilean PTA DPA signed now should be drafted to the Arts. 27–29 transfer regime, not only to Ley 19.628 Art. 10.
    Peru DS 016-2024-JUS (Reglamento, Ley 29733) Arts. 18–20 In force 120 calendar days after publication (31 March 2025). Art. 20.1 permits model contractual clauses imposing “cuando menos las mismas obligaciones” on the importer.
    Colombia Ley Estatutaria 1581 de 2012 Art. 26 Health data is sensitive (Art. 5); Art. 26(b) carves out medical-data exchange required by the data subject’s treatment. Otherwise the SIC issues a declaración de conformidad (Art. 26, par. 1).

    The operator-side drafting position is the same everywhere: the sponsor is responsable/controller, the operator is encargado/operator, processing is limited to documented instructions, sub-processing requires prior written consent, and the operator returns or deletes on termination subject to statutory retention. Where the destination country has no adequacy finding, attach the applicable model clauses as a schedule rather than describing them in the body.

    The Argentina adequacy mistake

    The most common error in Argentine PTA drafting is treating Commission Decision 2003/490/EC as if it authorised outbound transfers from Argentina. Article 1 reads: “Argentina is regarded as providing an adequate level of protection for personal data transferred from the Community.” Article 2 confines the decision to adequacy in Argentina “with a view to meeting the requirements of Article 25(1) of Directive 95/46/EC.” The instrument is unidirectional — EU to Argentina.

    A PTA data flow from Argentine sites to a sponsor in the United States, or to an access vendor in the Netherlands, is an Argentine outbound transfer governed by Ley 25.326 Art. 12, and the correct instrument is the AAIP responsable–encargado model agreement under Resolución 198/2023, not a citation to the 2003 decision. Treating the adequacy finding as reciprocal is a defect that survives review because it looks like a considered legal position.

    Pillar 3: product liability sits with the sponsor

    The operator is not the manufacturer, does not hold the marketing authorization, and cannot practically bear product-liability risk for the product itself. A managed-access or expanded-access vendor is in the same position. Neither controls design, manufacture, batch release, labelling content, or the safety profile — so neither can defend a product claim on the merits or insure it economically.

    Our drafting position, and the position we recommend to any operator in this role:

    • The sponsor or titular defends and indemnifies the operator against third-party claims arising from the product itself, including design, manufacture, and labelling defects.
    • The sponsor maintains product-liability insurance covering the PTA territories for the duration of the program plus a tail, and provides certificates on request.
    • The operator’s liability cap covers operator services only. Product liability sits outside the cap.
    • Carve-outs outside the cap in both directions: gross negligence, wilful misconduct, breach of confidentiality, intellectual-property infringement, and breach of data-protection obligations.

    The cap itself is negotiable, usually expressed against fees paid under the Work Order over a defined lookback. Its composition is not: a cap that silently absorbs product liability converts a services agreement into an uninsured product warranty.

    Pillar 4: sponsor accession as a condition precedent

    Because the sponsor holds the statutory supply duty, the product liability, the marketing authorization, and the primary pharmacovigilance obligation, an operator’s Work Order should be conditioned on sponsor accession. Two mechanisms work:

    1. Direct accession — the sponsor executes a short accession instrument to the schedules that allocate safety data exchange, data processing, and liability (in our template set, schedules C, E and F).
    2. Tripartite side letter — the sponsor, the access vendor or intermediary, and the operator sign a single side letter confirming the sponsor’s indemnity, insurance, PV ownership, and patient-continuity funding, with the underlying Work Order otherwise unchanged.

    Either way the Work Order should not become effective until accession is signed. Without it, the operator holds a services contract with a counterparty that cannot deliver the indemnity the contract assumes, and the patient-continuity commitment has no funded obligor behind it.

    Five architectural mistakes we see repeatedly

    1. No sponsor accession condition. The operator signs with an intermediary and inherits an unfunded, uninsurable duty.
    2. Product liability inside the operator’s cap. Structurally wrong for a non-manufacturer.
    3. The reciprocal-adequacy error. Argentina→US or Argentina→NL flows papered as if Decision 2003/490/EC covered them.
    4. No patient-continuity run-off. Termination should trigger a defined run-off — our default is 90 days — during which supply, PV intake, and cold-chain continue at the sponsor’s cost.
    5. No sponsor-funded continuity trigger. If the sponsor terminates the program or the access vendor disengages, the continuity obligation must be expressly sponsor-funded, or patients absorb the commercial dispute.

    Governing law, dispute resolution, and pre-send gates

    For cross-border PTA services agreements with a US-headquartered operator, Delaware law with AAA-ICDR arbitration seated in New York is a sensible default: neutral to the LATAM performance jurisdictions, familiar to sponsor counsel, and enforceable across the region under the New York Convention. Local-law carve-outs remain necessary for the statutory duties themselves, which are not contractible away.

    Before any PTA agreement leaves our desk it passes four gates: (1) a counsel memo verifying the regulatory framework and article citations for each performance jurisdiction; (2) named performing entities, including the habilitada local entity and the importadora of record; (3) sponsor accession path agreed in principle, in writing, before signature; and (4) harmonized statutory-obligation language, so that the same duty is not described one way in the recitals and another way in the schedules.

    Frequently asked questions

    What legal architecture does a LATAM post-trial access program require?
    Four instruments beyond the services agreement itself: a Safety Data Exchange Agreement connecting local adverse-event intake to the sponsor’s global pharmacovigilance system; a country-specific Data Processing Agreement built on the applicable transfer article (Argentina Ley 25.326 Art. 12, Brazil LGPD Arts. 33–36, Colombia Ley 1581 Art. 26, and so on); a product-liability allocation placing defence, indemnity, and insurance on the sponsor or titular; and a sponsor accession mechanism binding the marketing-authorization holder to those schedules. The regulatory filing — import authorization, ethics submission — is separate and downstream.

    What is a Safety Data Exchange Agreement (SDEA) in PTA?
    An SDEA is the bilateral agreement that defines how safety information moves from the PTA site and local operator into the sponsor’s global pharmacovigilance system. It should be executed within 30 days of the Work Order and built on ICH principles: ICH E2A §III.B for the 7-day and 15-calendar-day expedited-reporting clocks, ICH E2F §2.2 for annual DSUR periodicity and the 60-day post-data-lock-point submission window, and ICH E3 §12 for the safety-evaluation structure the data must fit. It names PV contacts, sets onward-transmission deadlines shorter than the sponsor’s regulatory clock, and fixes a reconciliation cadence.

    What is a Data Processing Agreement (DPA) in Argentine PTA?
    It is the instrument that makes an Argentine PTA data flow lawful under Ley 25.326. Art. 12(1) prohibits transfer to countries or organisations that do not provide adequate protection levels, and Art. 11(4) makes the transferee subject to the transferor’s obligations with joint liability. Where the sponsor sits in a country without an Argentine adequacy finding, the practical route is the responsable–encargado model agreement approved by AAIP Resolución 198/2023, attached as a schedule. Cláusula 6.1 limits the importer to the exporter’s documented instructions, with no decision-making power over scope or content.

    Does EU Commission Decision 2003/490/EC cover Argentina→US or Argentina→EU data flows?
    No. Article 1 of Decision 2003/490/EC regards Argentina as adequate for “personal data transferred from the Community,” and Article 2 limits the decision to adequacy in Argentina for the purposes of Article 25(1) of Directive 95/46/EC. The decision is unidirectional: EU to Argentina. An outbound transfer from Argentine sites to a US sponsor or a Dutch access vendor is governed by Ley 25.326 Art. 12 and requires its own adequacy basis, statutory exception, or model clauses. Article 3 of the decision, in fact, gives EU authorities power to suspend flows to recipients in Argentina — the opposite of a reciprocal permission.

    Who bears product liability in a PTA program — the sponsor, the manufacturer, or the operator?
    The sponsor or the titular of the marketing authorization. The operator is not the manufacturer, does not hold the authorization, and does not control design, manufacture, batch release, or labelling — so it cannot defend a product claim on the merits or insure it at a rational price. The correct architecture has the sponsor defend and indemnify the operator for product-related third-party claims, maintain product-liability insurance covering the PTA territories for the program term plus a tail, and accept that product liability sits outside the operator’s services liability cap.

    Why should PTA operators condition the Work Order on sponsor accession?
    Because the sponsor holds every obligation the Work Order depends on: the statutory continued-supply duty, the marketing authorization, primary pharmacovigilance responsibility, product liability, and the funding for patient continuity. An operator that contracts only with an intermediary holds an indemnity from a party that does not control the product and a continuity commitment with no funded obligor. Making accession a condition precedent — rather than a post-signature action item — is the only reliable way to ensure the risk allocation in the schedules is enforceable against the party that can actually perform it.

    What is a tripartite side letter in LATAM PTA?
    A single short instrument signed by the sponsor, the access vendor or intermediary, and the local operator, used where the sponsor will not accede directly to the operator’s schedules. It confirms four things: the sponsor’s defence and indemnity for product-related claims; the sponsor’s product-liability insurance covering the PTA territories; sponsor ownership of primary pharmacovigilance and regulatory reporting; and sponsor funding of patient continuity, including any run-off period. It leaves the underlying Work Order commercial terms untouched, which is usually why it is the faster path to signature.

    What is the standard liability cap in a LATAM PTA Work Order?
    There is no single market standard, and any figure quoted as one should be treated with suspicion. Caps are typically expressed as a ceiling tied to fees paid under the Work Order over a defined lookback period. The more consequential negotiation is not the number but the composition — what the cap covers and what sits outside it. A cap that quietly includes product liability turns a services agreement into an uninsured product warranty, which is a worse outcome for the operator than a low number with clean carve-outs.

    What carve-outs should sit outside the liability cap?
    Five, in both directions: gross negligence, wilful misconduct, breach of confidentiality, intellectual-property infringement, and breach of data-protection obligations. Product liability should also sit outside the operator’s cap, because the operator is not the manufacturer. Data-protection breach deserves particular attention in Latin America: Argentina’s Ley 25.326 Art. 11(4) imposes joint liability between transferor and transferee, and Mexico’s LFPDPPP Art. 59 fr. IV allows sanctions for sensitive-data infractions to be increased up to twofold, so capped data-protection exposure can be materially lower than actual statutory exposure.

    What is the standard patient-continuity run-off period?
    Our default drafting position is 90 days from the effective date of termination. During that window, product supply, pharmacovigilance intake, and cold-chain and importation services continue at the sponsor’s cost while the sponsor arranges an alternative route — a successor operator, an extension study, or transition into commercial or public-system supply. The reason to fix a defined period rather than “a reasonable transition” is that the statutory obligations do not pause: Brazil’s Lei 14.874/2024 Art. 33 lists exhaustive interruption grounds, and contract termination between a sponsor and its operator is not one of them.

    Should managed-access-program specialists require sponsor accession too?
    Yes, and for the same structural reason. A managed-access or expanded-access specialist occupies the same position as a regional operator: it is not the manufacturer, does not hold the marketing authorization, and cannot bear product-liability risk for the product. Whether the intermediary is a global access platform, a specialty distributor, or a regional CRO, the party with the statutory supply duty and the insurable product risk is the sponsor. Any access architecture that leaves the sponsor outside the contractual chain has a gap at exactly the point where a patient-harm claim would land.

    Working on a LATAM post-trial access program? bioaccess® is a US-headquartered, LATAM-native operator running regulatory, importadora, and 2–8 °C GDP cold-chain functions directly across the region. If you’re evaluating PTA feasibility in Argentina, Brazil, Chile, Peru, Panama, Mexico or Colombia, contact Julio Martinez-Clark, Co-Founder & CEO, at jmclark@bioaccessla.com or +1 (954) 903-7210. More at bioaccessla.com/roadmap.

    Sources

    • ICH E2A, Clinical Safety Data Management: Definitions and Standards for Expedited Reporting — https://database.ich.org/sites/default/files/E2A_Guideline.pdf
    • ICH E2F, Development Safety Update Report — https://database.ich.org/sites/default/files/E2F_Guideline.pdf
    • ICH E3, Structure and Content of Clinical Study Reports — https://database.ich.org/sites/default/files/E3_Guideline.pdf
    • Commission Decision 2003/490/EC of 30 June 2003 (Argentina adequacy) — https://eur-lex.europa.eu/legal-content/EN/TXT/HTML/?uri=CELEX:32003D0490
    • Argentina, Ley 25.326 (Protección de los Datos Personales) — https://servicios.infoleg.gob.ar/infolegInternet/anexos/60000-64999/64790/texact.htm
    • Argentina, AAIP Resolución 198/2023 (RESOL-2023-198-APN-AAIP, BO 18/10/2023), model international-transfer clauses — https://servicios.infoleg.gob.ar/infolegInternet/anexos/390000-394999/391538/norma.htm
    • Argentina, AAIP Resolución 198/2023 Anexo I (IF-2023-108581614-APN-DNPDP#AAIP) — https://servicios.infoleg.gob.ar/infolegInternet/anexos/390000-394999/391538/res198.pdf
    • Argentina, Disposición ANMAT 12792/2016 (post-study import procedure) — https://www.boletinoficial.gob.ar/detalleAviso/primera/154162/20161117
    • Argentina, Disposición ANMAT 7516/2025 (GCP, in force 1 December 2025) — https://www.boletinoficial.gob.ar/detalleAviso/primera/332695/20251009
    • Brazil, Lei nº 13.709/2018 (LGPD) — https://www.planalto.gov.br/ccivil_03/_ato2015-2018/2018/lei/l13709.htm
    • Brazil, Lei nº 14.874/2024, Arts. 30–37 — https://www.planalto.gov.br/ccivil_03/_ato2023-2026/2024/lei/l14874.htm
    • Brazil, Decreto nº 12.651/2025, Art. 31 — https://www2.camara.leg.br/legin/fed/decret/2025/decreto-12651-7-outubro-2025-798105-publicacaooriginal-176652-pe.html
    • Mexico, Ley Federal de Protección de Datos Personales en Posesión de los Particulares (DOF 20 March 2025; last reform DOF 14 November 2025) — https://www.diputados.gob.mx/LeyesBiblio/pdf/LFPDPPP.pdf
    • Chile, Ley 19.628 sobre Protección de la Vida Privada — https://www.bcn.cl/leychile/navegar?idNorma=141599
    • Chile, Ley 21.719 (published 13 December 2024; in force 1 December 2026) — https://www.bcn.cl/leychile/navegar?idNorma=1209272
    • Chile, Ley 20.850 and Código Sanitario Art. 111 C — https://www.bcn.cl/leychile/navegar?idNorma=1078148
    • Peru, Decreto Supremo N° 016-2024-JUS (Reglamento de la Ley 29733) — https://www.gob.pe/institucion/anpd/normas-legales/6554453-16-2024-jus
    • Peru, Reglamento de Ensayos Clínicos, DS 021-2017-SA, Arts. 115–118 — https://ensayosclinicos-repec.ins.gob.pe/images/Reglamento_de_EC.pdf
    • Colombia, Ley Estatutaria 1581 de 2012 — https://www.funcionpublica.gov.co/eva/gestornormativo/norma.php?i=49981
    • Panama, Decreto Ejecutivo No. 21 de 23 de abril de 2026, Art. 68, Gaceta Oficial Digital No. 30510-C (primary-source Gaceta PDF, read 6 September 2026)

  • Post-trial access in Latin America: the operator’s map

    Ten Latin American countries legally require a trial sponsor to keep supplying the investigational product after the study closes. Three more address post-trial continuation in binding instruments with weak or unassigned duties. Seven impose nothing. If your Phase 3 has LATAM sites, that distinction is a line item, not an ethics footnote.

    We built this map because the region is now diverging fast. Brazil enacted a statute in 2024 and its regulation in 2025. Honduras went from zero to a mandate in February 2026. Panama replaced its research decree in April 2026. Meanwhile most global vendor and law-firm summaries still cite instruments that have been repealed, and several repeat citation errors that a regulator would catch on the first review cycle.

    Where the mandates actually are

    Across 20 jurisdictions, the classification breaks down as follows.

    Binding statutory mandate (10): Argentina, Brazil, Chile, Peru, Ecuador, Costa Rica, Guatemala, Honduras, Nicaragua, Panama. Each has a law, decree, resolution or ministerial normativa that obliges continued provision of the investigational product after the trial ends.

    Binding instrument, weak or unassigned duty (3): Uruguay, Bolivia, Venezuela. Venezuela’s Buenas Prácticas Clínicas §6.12.1 requires the sponsor only to “procurar… la provisión del tratamiento” after the trial — endeavour, not provide (INHRR). Uruguay’s Decreto 158/019 Anexo numeral 24 says participants “deben tener la certeza de que contarán con los beneficios demostrados” but names no obligor at all (IMPO). Bolivia’s Art. 99 routes continuation entirely into the compassionate-use chapter, requiring per-patient DINAMED authorization (AGEMED).

    No mandate (7): Mexico, Colombia, Paraguay, El Salvador, Dominican Republic, Cuba, Puerto Rico. In each case we read the operative clinical-trial instrument and it contains no post-trial supply obligation.

    The comparative matrix

    Country Mandate status Primary instrument Cost allocation Import mechanism
    Argentina Binding statute Disp. ANMAT 12792/2016; GCP base reset by Disp. 7516/2025 Sponsor, free to participant, site and payer (Art. 3(g)) Dedicated PTA import expediente to ANMAT–DERM, valid 12 months (Art. 4); physical import via INAME (Art. 5)
    Brazil Binding statute Lei 14.874/2024 Arts. 30–37 + Decreto 12.651/2025 Art. 31 Sponsor (Lei Art. 31 §4); free supply (Decreto Art. 31) ANVISA authorization + import licence under RDC 38/2013
    Chile Binding statute Ley 20.850 Art. 17; Cód. Sanitario Art. 111 C “Sin costo para el paciente”; duty on provisional-authorization holder, then registration holder ISP special provisional-use authorization (Art. 111 A); CENABAST exceptional import
    Peru Binding statute DS 021-2017-SA Arts. 115–118 Sponsor-funded, provided free (Arts. 40(p), 89) OGITT extension trial or case-by-case ANM/DIGEMID authorization (Art. 116) with a seven-document set (Art. 117)
    Panama Binding statute Decreto Ejecutivo 21/2026 Art. 68, Gaceta Oficial 30510-C, 23 Apr 2026 Investigators and sponsors co-obligated to ensure access; cost not stated verbatim Extension of the trial import permit for exclusive participant use (Art. 68); RESEGIS registration + DNFD authorization (Art. 99)
    Ecuador Binding statute AM 00069-2024 Arts. 80–81, 95(c) Sponsor or legal representative, “entrega gratuita” (Art. 80) No PTA-specific route; general ARCSA import authorization
    Costa Rica Binding statute Ley 9234 Arts. 28, 53(k) Sponsor, free, “mientras lo requieran” None identified in the statute for post-trial product
    Guatemala Binding statute (instrument version unconfirmed) AM 82-2019 Art. 64; MSPAS index lists AM 206-2021 Supply “podrá ser solicitada al patrocinador” — request-driven, not automatic Compassionate-use authorization by the DRCPFA (Art. 65)
    Honduras Binding statute (new) Acuerdo 0256-ARSA-2025 Art. 63 Sponsor or legal representative, “sin costo” (Art. 63) Extension trial or compassionate use (Art. 63); special ARSA import authorization (Art. 86)
    Nicaragua Binding statute Normativa-166 Cap. VI num. 16 Sponsor obliged; free-of-charge stated for the trial phase only General trial import rules; no PTA route
    Uruguay Binding guidance Decreto 158/019 Anexo num. 24 No obligor named n.a.
    Bolivia Binding guidance Norma para Estudios Clínicos Art. 99 → Arts. 74–76 Not allocated post-trial Per-patient DINAMED compassionate-use authorization
    Venezuela Binding guidance Normas de BPC §§5.4.5, 6.12.1 Free during trial only; post-trial duty is “procurar” None described
    Mexico No mandate for product supply NOM-012-SSA3-2012 §11.2.2 Investigator must arrange continued “tratamiento y cuidados” — not IP supply n.a.
    Colombia No mandate Res. 2378/2008 n.a. n.a.
    Paraguay No mandate Resol. DINAVISA 238/2024 n.a. n.a.
    El Salvador No mandate Lineamientos Técnicos, Ac. Ejec. 1530 (2025) n.a. n.a.
    Dominican Republic No mandate Manual CONABIOS, 2ª ed. n.a. — §7.1 gives an information right only n.a.
    Cuba No mandate BPC en Cuba (CECMED) n.a. — §4.3.2 covers adverse-event medical care only n.a.
    Puerto Rico (US) No mandate 21 CFR 312 Subpart I n.a. — permissive expanded-access framework n.a. (US customs territory)

    Why this is a closing cost, not an ethics footnote

    A sponsor that runs sites in Brazil, Chile, Peru, Panama and Argentina and then closes the study has, in five jurisdictions, a legally enforceable duty to keep shipping product to responders — free of charge, under separate authorizations, for a period the sponsor does not control.

    Brazil’s Ministry of Health states the position without hedging: continued post-study treatment “não é uma expectativa, mas um dever legal, aplicável desde o planejamento da pesquisa até o período pós-estudo” (INAEP FAQ). That duty is priced nowhere in a standard Phase 3 budget. It requires a cohort-scale filing distinct from the trial dossier, an import authorization with its own clock, GDP-compliant cold chain for as long as the cohort persists, and pharmacovigilance reporting after database lock.

    The obligation also survives corporate events. Chile’s Código Sanitario Art. 111 C states the duty “afectará al titular del registro sanitario, aun cuando no haya sido el titular de la autorización provisional o haya adquirido con posterioridad el registro sanitario” (BCN). Buy a Chilean registration and you buy the free-supply obligation attached to it. That belongs in diligence, not in a site-activation checklist.

    The five strongest sponsor obligations

    Brazil. Lei 14.874/2024 Art. 30 requires the sponsor and investigator to file a post-study access plan with the CEP before the trial starts. Art. 31 §4 puts the cost on the sponsor. Art. 33 permits interruption only on listed grounds, including the “transcurso do prazo de 5 (cinco) anos, contado da disponibilidade comercial do medicamento experimental no País.” Decreto 12.651/2025 Art. 31 restates the free-supply duty whenever the investigator judges the product the best therapeutic alternative. Full detail in our Brazil post-trial access pillar.

    Chile. Art. 111 C obliges continuity “sin costo para el paciente… por todo el tiempo que persista su utilidad terapéutica” — no commercialization endpoint, no five-year cap. See the Chile Ley 20.850 analysis.

    Panama. Article 68 of Decreto Ejecutivo 21/2026 (Gaceta Oficial 30510-C, 23 April 2026) reads: “Los investigadores y patrocinadores deben asegurar a todos los participantes el acceso al producto, siempre que se haya comprobado el beneficio clínico o de salud pública de la intervención durante el estudio; hasta su comercialización en el país.” It then requires the sponsor to apply for “una extensión del permiso de importación del producto utilizado durante la investigación para uso exclusivo de los participantes.” The decree entered into force on promulgation under Art. 105. Detail in the Panama Decreto 21/2026 pillar.

    Argentina. Disposición ANMAT 12792/2016 is the only instrument in the region that is purely a post-trial access import procedure. Art. 3(g) requires a sworn sponsor declaration that supply will be “sin costo alguno para el participante, el establecimiento asistencial o su cobertura de salud” — note that the site and the payer are named, not just the patient. Art. 4 gives the DERM authorization a 12-month validity. Art. 2 excludes authorized extension studies, which run on a different track. See the Argentina Disposición 12792 pillar.

    Peru. DS 021-2017-SA is the best-drafted operational regime in the region: Art. 115 defines the obligation and its trigger conditions, Art. 116 names two authorization routes (OGITT extension trial or case-by-case ANM/DIGEMID authorization), Art. 117 lists the documents, Art. 118 assigns post-access pharmacovigilance. Art. 40(p) makes it a sponsor duty. See the Peru DS 021-2017-SA pillar.

    Where the duty reaches devices

    Most LATAM post-trial provisions were drafted for medicines. Four jurisdictions reach hardware textually.

    Costa Rica is the clearest. Ley 9234 Art. 53(k) obliges the sponsor to provide, free of charge and after the study concludes, “el medicamento, dispositivo o procedimiento que ha sido objeto de investigación,” with four exhaustive exits — including a reasoned treating-physician resolution filed in the record and communicated to the CEC within three working days. Art. 28 sets the duration at “mientras lo requieran.”

    Brazil reaches devices through Lei 14.874/2024 Art. 37: “Aplicar-se-ão aos produtos e dispositivos médicos e aos produtos de terapias avançadas experimentais… as disposições deste Capítulo, no que couber.” Chile reaches them through Código Sanitario Art. 111 A, which covers “los productos farmacéuticos y los elementos de uso médico.” Peru reaches them through the definition of producto en investigación in Art. 2.1.36.

    Ecuador does not. AM 00069-2024 is a reglamento for medicines and processed natural medicinal products, so a device sponsor’s Ecuadorian exposure runs through ethics-committee expectations and the informed consent, not through Arts. 80–81.

    What changed between 2024 and 2026

    Honduras added a mandate. Acuerdo 0256-ARSA-2025 Art. 63 defines post-trial access as “la entrega sin costo por parte del patrocinador o su representante legal,” even where the product has no Honduran sanitary registration, subject to three cumulative conditions. Published in La Gaceta on 28 January 2026, in force 30 days later. The predecessor Acuerdo 041-2020 had no post-trial provision at all. Read Art. 63 alongside Art. 18 numeral 5, which softens the duty to facilitating access “cuando el patrocinador lo considere” — a real internal tension, and a reason not to treat Honduras as equivalent to Brazil.

    Panama replaced its research decree. Decreto Ejecutivo 21/2026 reglamenta Titles III and IV of Ley 84 de 14 de mayo de 2019 and entered into force on promulgation, 23 April 2026. Its Art. 104 repeals Decreto Ejecutivo 1843 of 2014, Decreto Ejecutivo 6 of 2015 and Resolución 390 of 2003.

    Ecuador deleted its endpoint. AM 00069-2024 Art. 80 states the free-supply duty with no termination point. The repealed AM 0075-2017 had capped it: Art. 39(w) ran only “hasta que el producto se comercialice en el país” (MSP Ecuador). Art. 81 narrowed the trigger to three cumulative conditions while the duration became open-ended. Almost nobody has flagged that trade.

    Brazil completed a two-step build. Statute in 2024, regulation in 2025, with further INAEP guidance promised by Decreto 12.651/2025 Art. 31 §2.

    Argentina reset its GCP base. Disposición 7516/2025 took effect 1 December 2025 (Art. 8). Its Art. 7 repealed Disposiciones 6677/10, 4008/17, 9929/19 and 2172/25 plus Circulares 0001/11 and 004/18. Disp. 12792/2016 is absent from that repeal list, so the post-trial import procedure stands — but the substantive continuity duty moved into the new GCP annex, and sponsors are filing against instruments that no longer exist. The legal architecture of LATAM PTA piece works through how the obligation layer and the import layer interact.

    Colombia: no binding post-trial access statute

    We read Resolución 2378 de 2008 and Resolución 8430 de 1993 in full, checking expressly for post-trial supply language. Neither contains any. Res. 8430/1993 allocates only harm-related costs — Art. 13 medical care for research-related injury, Art. 15(j) treatment availability and indemnification, Art. 15(k) additional costs against the research budget.

    That makes Colombia a cost-certainty jurisdiction: no statutory tail obligation, no separate post-trial filing, no open-ended supply exposure. It does not make post-trial access impossible. A sponsor that wants to continue supplying responders in Colombia can run a voluntary continuity program on its own initiative, handled through the ethics committee, the informed consent and the general product import rules. The exposure is contractual and reputational rather than statutory, which means it has to be allocated in the CRO and site agreements rather than assumed away.

    Mexico sits in an adjacent position and is routinely misdescribed. NOM-012-SSA3-2012 §11.2.2 obliges “el investigador principal” to arrange continuation of “el tratamiento y cuidados” to prevent withdrawal effects. That is an investigator duty about care, not a sponsor duty to supply the investigational product.

    What sponsors get wrong

    Citing repealed instruments. Argentina’s Disp. 6677/2010, which historically carried the continuity obligation, is repealed. Ecuador’s AM 0075-2017 is repealed. Honduras’s Acuerdo 041-2020 is revoked in its entirety. Panama’s Decreto Ejecutivo 1843/2014 and 6/2015 are repealed. Filings and legal memos still quote all of them.

    The “Ley 419/2023” error. Panama’s medicines statute is Ley 419 of 1 February 2024, not 2023 — and it is a commercial-medicines law, not the post-trial access instrument. The binding post-trial duty sits in Decreto Ejecutivo 21/2026 Art. 68, under Ley 84 of 2019. Getting this wrong signals to a Panamanian reviewer that the filer has not read the current framework.

    Treating Argentina’s RAEM as post-trial access. Disposición 4616/2019 approves the Régimen de Accesibilidad de Excepción a Medicamentos: an individual-patient exceptional import route with 90-day, 180-day and one-year quantity windows (Boletín Oficial). It contains no reference to clinical trials or post-trial access. Filing a trial cohort through RAEM means one expediente per patient, per renewal, on the wrong legal basis. Cohort post-trial access in Argentina runs on Disp. 12792/2016.

    Assuming an obligation implies a pathway. Costa Rica mandates continued free provision of the device or medicine under Art. 53(k), but Art. 55 addresses importation only before an approved study begins. No post-trial import route is identified in the statute. Ecuador and Nicaragua have the same shape. The obligation is real; the mechanism has to be constructed.

    The fastest route to compliance

    For a sponsor closing a multi-country LATAM Phase 3, the sequence that works is: classify each participating country into mandate / soft / none using the operative current instrument; identify which mandate countries require a filing distinct from the trial dossier (Argentina, Brazil, Panama, Peru at minimum); confirm whether your product class is textually in scope, which matters most for devices; establish who the legal importer of record will be in each country, since the trial import authorization frequently expires with the trial; and only then estimate cohort size, duration and cold-chain cost. Countries with no mandate still need a documented position, because the ethics committee and the informed consent will ask.

    Working on a LATAM post-trial access program? bioaccess® is a US-headquartered, LATAM-native operator running regulatory, importadora, and 2–8 °C GDP cold-chain functions directly across the region. If you’re evaluating PTA feasibility in Argentina, Brazil, Chile, Peru, Panama, Costa Rica or elsewhere in Latin America, contact Julio Martinez-Clark, Co-Founder & CEO, at jmclark@bioaccessla.com or +1 (954) 903-7210. More at bioaccessla.com/roadmap.

    Frequently Asked Questions

    Which Latin American countries require post-trial access?
    Ten jurisdictions impose a binding statutory duty: Argentina, Brazil, Chile, Peru, Ecuador, Costa Rica, Guatemala, Honduras, Nicaragua and Panama. Three more — Uruguay, Bolivia and Venezuela — address post-trial continuation in binding instruments but with weak verbs, no named obligor, or routing into per-patient compassionate use. Seven impose nothing: Mexico, Colombia, Paraguay, El Salvador, the Dominican Republic, Cuba and Puerto Rico. The classification depends on reading the operative current instrument, not a secondary summary, because five of these countries changed their framework between 2024 and 2026.

    Which LATAM country has the strongest post-trial access mandate?
    Brazil. Lei 14.874/2024 Art. 30 requires a post-study access plan to be filed with the ethics committee before the trial begins, Art. 31 §4 assigns the cost to the sponsor, and Art. 33 permits interruption only on listed grounds — one of which is the passage of five years from the product’s commercial availability in Brazil. Decreto 12.651/2025 Art. 31 restates the free-supply duty. Brazil’s Ministry of Health describes this as a legal duty rather than an expectation. Chile is the closest runner-up because Art. 111 C has no endpoint at all and the obligation follows the sanitary registration to any subsequent holder.

    Does post-trial access in LATAM apply to medical devices or only drugs?
    Both, in four jurisdictions. Costa Rica’s Ley 9234 Art. 53(k) is the most explicit, obliging free post-study provision of “el medicamento, dispositivo o procedimiento.” Brazil extends its post-trial chapter to devices and advanced therapies through Lei 14.874/2024 Art. 37. Chile’s Código Sanitario Art. 111 A covers “elementos de uso médico.” Peru’s definition of producto en investigación in DS 021-2017-SA Art. 2.1.36 includes devices. Ecuador’s AM 00069-2024 does not cover devices. Argentina’s Disp. 12792/2016 covers products and “materiales” without using the word dispositivo médico, so device coverage there is inferential.

    Which LATAM countries do NOT require post-trial access?
    Mexico, Colombia, Paraguay, El Salvador, the Dominican Republic, Cuba and Puerto Rico. Colombia’s Resoluciones 2378/2008 and 8430/1993 contain no post-trial supply obligation; Res. 8430/1993 allocates only harm-related costs. Mexico’s NOM-012-SSA3-2012 §11.2.2 imposes a continuity duty on the principal investigator covering treatment and care, not on the sponsor to supply the investigational product. Notably, both Paraguay (2024) and El Salvador (2025) rewrote their research frameworks in this window and declined to add a post-trial provision, which cuts against the assumption that the whole region is converging on mandatory access.

    What changed in LATAM post-trial access regulation in 2024-2026?
    Five substantive moves. Brazil completed a two-step build with Lei 14.874/2024 and Decreto 12.651/2025. Ecuador’s AM 00069-2024 repealed AM 0075-2017 and deleted the “until commercialized in the country” endpoint, converting a bounded duty into an open-ended one. Argentina’s Disposición 7516/2025 took effect 1 December 2025 and repealed Disp. 6677/10 among others, resetting the GCP base while leaving the 2016 post-trial import procedure standing. Honduras moved from no mandate to a binding mandate via Acuerdo 0256-ARSA-2025 Art. 63, in force from late February 2026. Panama’s Decreto Ejecutivo 21/2026 entered into force 23 April 2026 with a binding post-trial duty in Art. 68.

    What is the difference between cohort PTA (Argentina) and individual expanded access (RAEM)?
    They are separate legal regimes with separate instruments. Post-trial access under Disposición ANMAT 12792/2016 is a cohort-level procedure: one expediente covering the named participants from an ANMAT-authorized trial, approved by the ethics committee, filed with the Dirección de Evaluación y Registro de Medicamentos, with a 12-month import authorization under Art. 4. The Régimen de Accesibilidad de Excepción a Medicamentos under Disposición 4616/2019 is an individual-patient exceptional import route with 90-day, 180-day and one-year quantity limits, and it makes no reference to clinical trials. Using RAEM for a trial cohort produces per-patient filings on the wrong basis.

    Who pays for post-trial access in Latin America?
    The sponsor, in every country where the duty is clearly allocated. Brazil’s Lei 14.874/2024 Art. 31 §4 puts the supply on the sponsor. Peru’s DS 021-2017-SA Art. 89 requires products to be sponsor-financed and provided free. Costa Rica’s Ley 9234 Art. 53(k) and Ecuador’s AM 00069-2024 Art. 80 both name the sponsor. Chile’s Art. 111 C places the duty on the provisional-authorization holder and then the registration holder. Argentina goes furthest: Disp. 12792/2016 Art. 3(g) requires a sworn declaration that supply carries no cost to the participant, the treating institution or the health coverage. Uruguay, Bolivia, Nicaragua and Honduras leave the cost-bearer partly or wholly unstated.

    How does a sponsor find a qualified PTA operator in Latin America?
    Test three capabilities separately. First, regulatory: can the operator file the country-specific post-trial authorization itself, naming the correct current instrument and article, rather than subcontracting it blind. Second, importation: can it act as legal importer of record after the trial import authorization lapses, which it does in several countries. Third, distribution: can it hold and ship the product under 2–8 °C GDP conditions for the life of the cohort, with pharmacovigilance reporting after database lock. Global post-trial supply vendors market the service regionally without naming Latin American countries or local filing capability on their public pages, so ask for the specific article and the specific authorizing office.

    What is the fastest route to compliance for a sponsor closing a multi-country LATAM Phase 3?
    Start from the operative instrument in each participating country, not from a regional summary. Classify each country as binding mandate, weak instrument or no mandate; determine which mandate countries require a filing distinct from the trial dossier — Argentina, Brazil, Panama and Peru at minimum; confirm your product class is textually in scope, which is the decisive question for devices; appoint a legal importer of record in each country because trial import authorizations frequently expire with the trial; then size the cohort, the duration and the cold chain. Countries with no mandate still need a documented, defensible position for the ethics committee.

    Sources

    • Argentina — Disposición ANMAT 12792/2016: https://www.boletinoficial.gob.ar/detalleAviso/primera/154162/20161117
    • Argentina — Disposición ANMAT 7516/2025: https://www.boletinoficial.gob.ar/detalleAviso/primera/332695/20251009
    • Argentina — Disposición ANMAT 4616/2019 (RAEM): https://www.boletinoficial.gob.ar/detalleAviso/primera/208794/20190604
    • Brazil — Lei nº 14.874/2024: https://www.planalto.gov.br/ccivil_03/_ato2023-2026/2024/lei/l14874.htm
    • Brazil — Decreto nº 12.651/2025: https://www2.camara.leg.br/legin/fed/decret/2025/decreto-12651-7-outubro-2025-798105-publicacaooriginal-176652-pe.html
    • Brazil — ANVISA RDC nº 38/2013: https://anvisalegis.datalegis.net/action/ActionDatalegis.php?acao=abrirTextoAto&tipo=RDC&numeroAto=00000038&seqAto=000&valorAno=2013&orgao=RDC/DC/ANVISA/MS&codTipo=&desItem=&desItemFim=&cod_menu=1696&cod_modulo=134&pesquisa=true
    • Brazil — Ministério da Saúde / INAEP FAQ on acesso pós-estudo: https://www.gov.br/saude/pt-br/composicao/orgaos-colegiados/inaep/faq/faq/acesso-pos-estudo/o-acesso-fornecimento-pos-estudo-e
    • Chile — Ley 20.850 and Código Sanitario Arts. 111 A–111 C: https://www.bcn.cl/leychile/navegar?idNorma=1078148
    • Peru — Reglamento de Ensayos Clínicos, DS 021-2017-SA: https://ensayosclinicos-repec.ins.gob.pe/images/Reglamento_de_EC.pdf
    • Panama — Decreto Ejecutivo No. 21 de 23 de abril de 2026, Gaceta Oficial Digital No. 30510-C (Arts. 68, 99, 104, 105); primary text read from the Gaceta Oficial PDF
    • Panama — Ley 419 de 1 de febrero de 2024 (medicamentos): https://www.minsa.gob.pa/sites/default/files/normatividad/ley-419-de-2024-ley-de-medicamentos.pdf
    • Ecuador — Acuerdo Ministerial 00069-2024: https://www.espoch.edu.ec/wp-content/uploads/2025/10/ac-00069-2024_dic_31_compressed_1-1.pdf
    • Ecuador — Acuerdo Ministerial 0075-2017 (repealed): https://www.salud.gob.ec/wp-content/uploads/2022/09/A.M.-0075-REGLAMENTO-ENSAYOS-CLINICOS-1.pdf
    • Costa Rica — Ley N.º 9234, Ley Reguladora de Investigación Biomédica: https://documentos.una.ac.cr/bitstream/handle/unadocs/5670/Texto%20Completo%20Norma%209234.pdf?sequence=1&isAllowed=y
    • Guatemala — Acuerdo Ministerial 82-2019: https://medicamentos.mspas.gob.gt/phocadownload/Acuerdo%20Ministerial%2082-2019.pdf
    • Guatemala — MSPAS legislación vigente index (AM 206-2021): https://medicamentos.mspas.gob.gt/index.php/legislacion-vigente/acuerdos
    • Honduras — Acuerdo No. 0256-ARSA-2025: https://www.tsc.gob.hn/web/leyes/Acuerdo-0256-ARSA-2025.pdf
    • Nicaragua — Normativa-166, Norma para la Regulación de Ensayos Clínicos: https://www.minsa.gob.ni/sites/default/files/2022-10/Norma%20de%20Ensayos%20Clinicos.11833.pdf
    • Uruguay — Decreto N° 158/019, Anexo: https://www.impo.com.uy/bases/decretos-originales/158-2019/8
    • Bolivia — Norma para Estudios Clínicos (AGEMED): https://www.agemed.gob.bo/archivos_agemed/ensayosclinicos/001-2021.pdf
    • Venezuela — Normas de Buena Práctica Clínica (INHRR): https://inhrr.gob.ve/pdf/pdf_jr/JR-1311-2013.pdf
    • Mexico — NOM-012-SSA3-2012: https://sidof.segob.gob.mx/notas/docFuente/5284148
    • Colombia — Resolución 2378 de 2008: https://www.ins.gov.co/Normatividad/Resoluciones/RESOLUCION%202378%20DE%202008.pdf
    • Colombia — Resolución 8430 de 1993: https://www.minsalud.gov.co/sites/rid/Lists/BibliotecaDigital/RIDE/de/dij/resolucion-8430-DE-1993.PDF
    • Paraguay — Resolución DINAVISA 238/2024: https://dinavisa.gov.py/wp-content/uploads/2024/10/2.-Requisitos-de-Ensayos-Clinicos.-Resol.-238_2024.pdf
    • El Salvador — Lineamientos Técnicos para la Investigación en Salud, Acuerdo Ejecutivo 1530 (2025): https://asp.salud.gob.sv/regulacion/pdf/lineamientos/lineamientostecnicosparalainvestigacionensalud-Acuerdo-Ejecutivo-1530-29052025_v1.pdf
    • Dominican Republic — Manual de Normas y Procedimientos Operativos, CONABIOS: https://conabios.gob.do/wp-content/uploads/2025/02/1.Manual-de-Normas-y-Procedimientos-Operativos-V2-13-02.pdf
    • Cuba — Buenas Prácticas Clínicas en Cuba (CECMED): https://www.cecmed.cu/sites/default/files/adjuntos/Reglamentacion/Dir_BPC.pdf
    • United States / Puerto Rico — 21 CFR 312.310 (Expanded Access, Subpart I): https://www.ecfr.gov/current/title-21/chapter-I/subchapter-D/part-312/subpart-I/section-312.310
    • FDA — Expanded Access training materials: https://www.fda.gov/media/193381/download

  • COFEPRIS Medical Device Registration Checklist (Mexico): MRH, Abbreviated Pathway, and Spanish Dossier

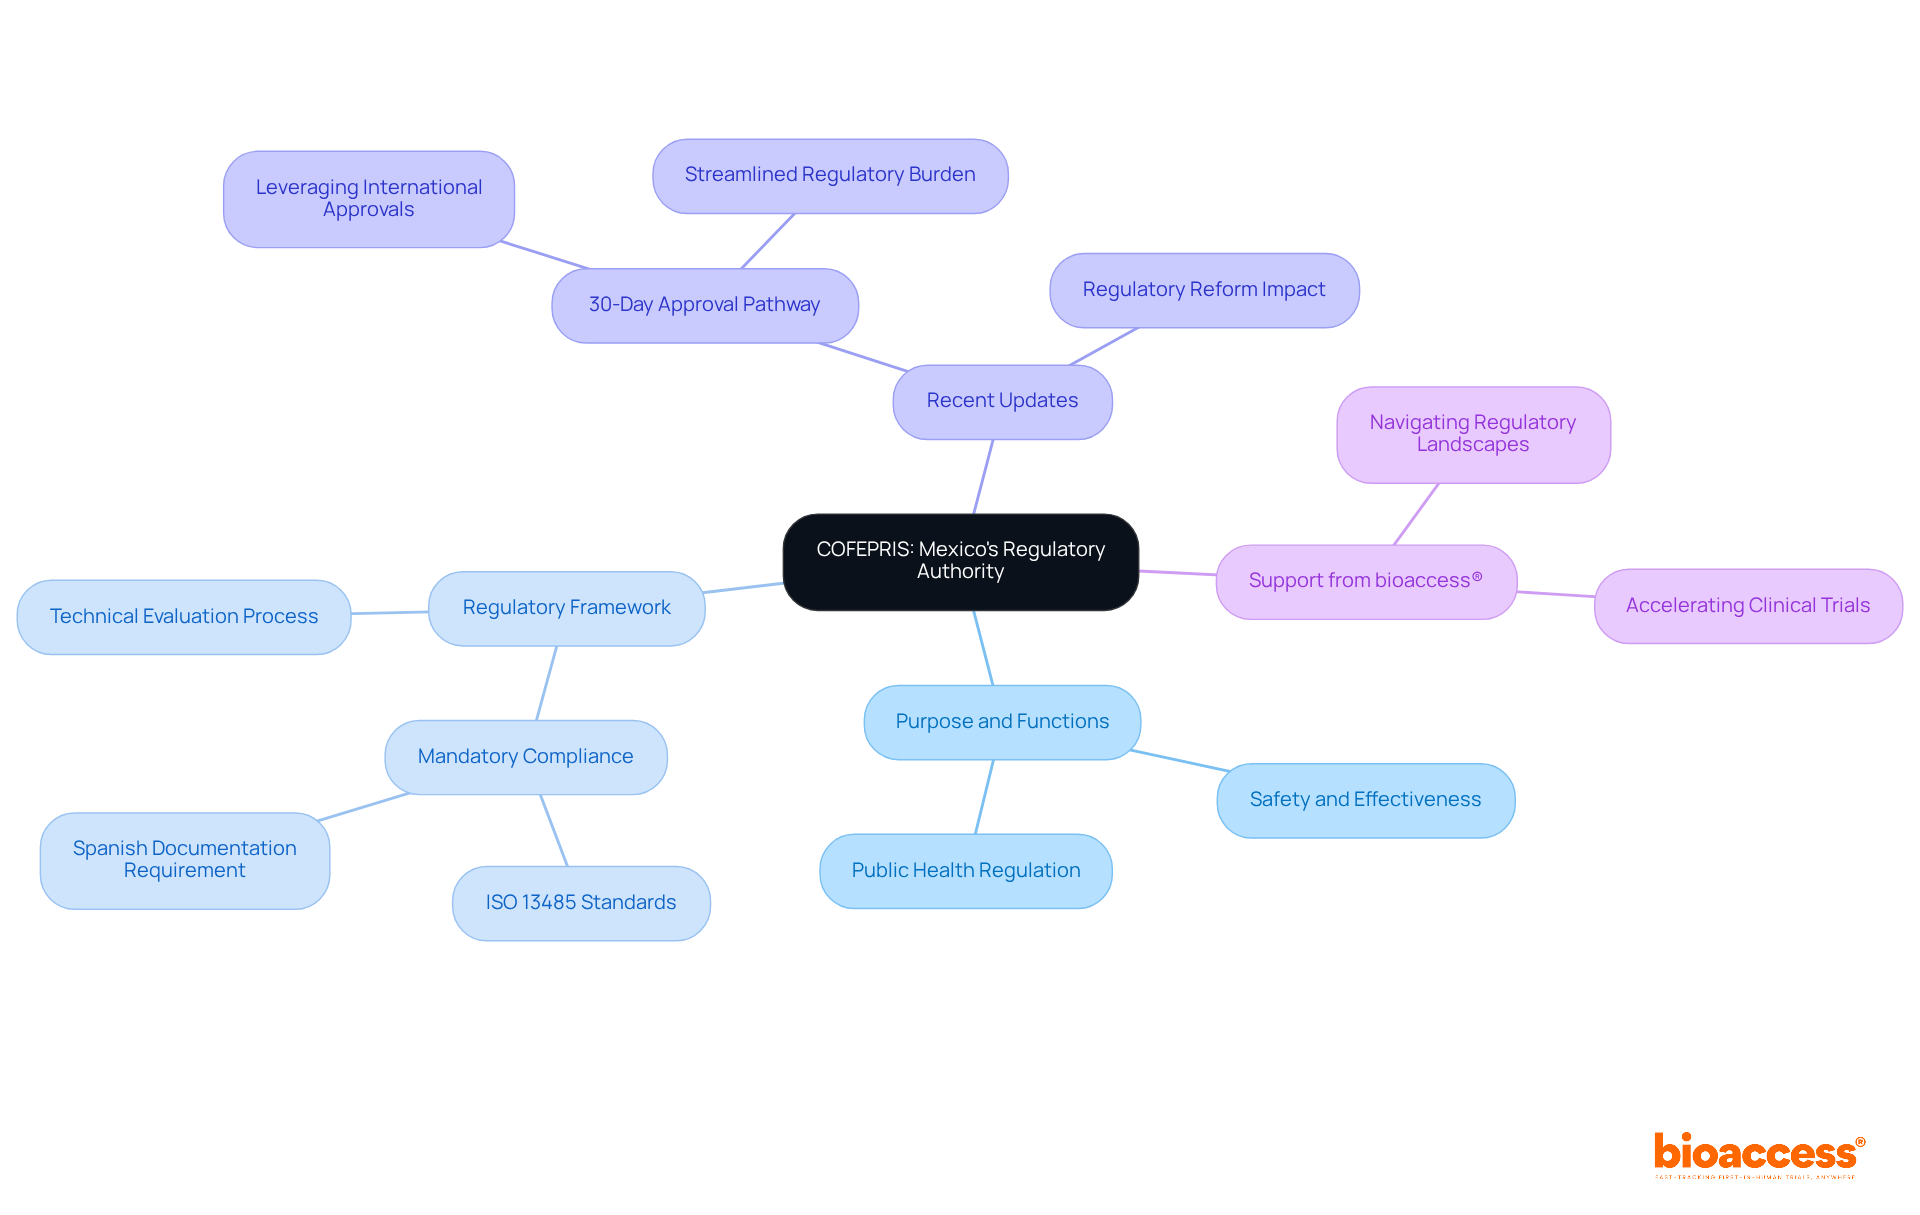
    COFEPRIS medical device registration is the ranking laggard for a reason: most English pages either recycle a generic “LATAM registration” outline or talk about manufacturing in Mexico. U.S. RA leads need a holder checklist — who owns the registro sanitario, which pathway you actually qualify for in 2026, and what must be in Spanish before DIGIPRIS will take the fee.

    bioaccess® works from Miami with U.S. MedTech sponsors and keeps trial plus market-access coverage across 19 Latin American and Caribbean markets. Mexico is one market in that footprint, not the only one. Timelines below are experience-based planning ranges for 2026, not COFEPRIS SLAs.

    What COFEPRIS registration is

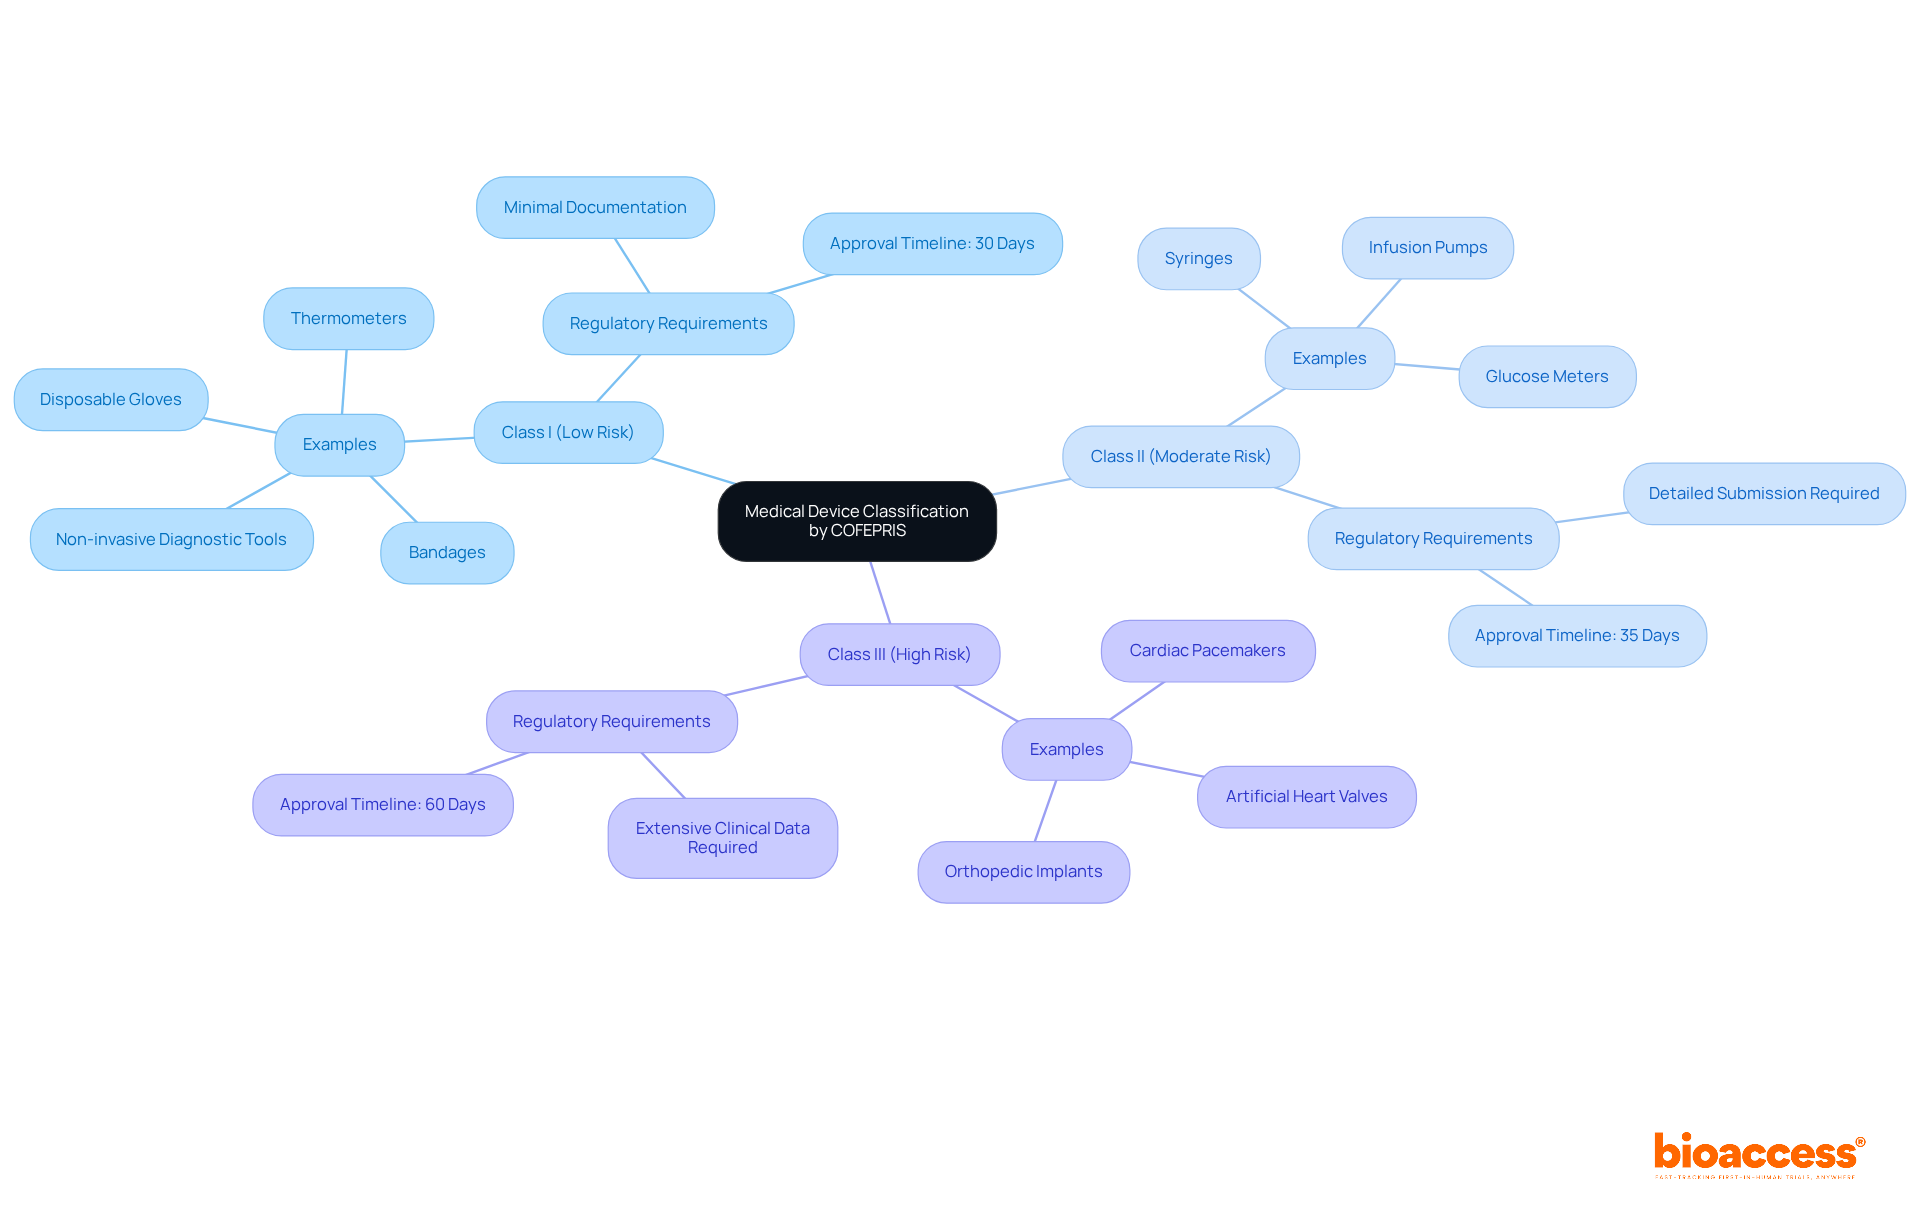
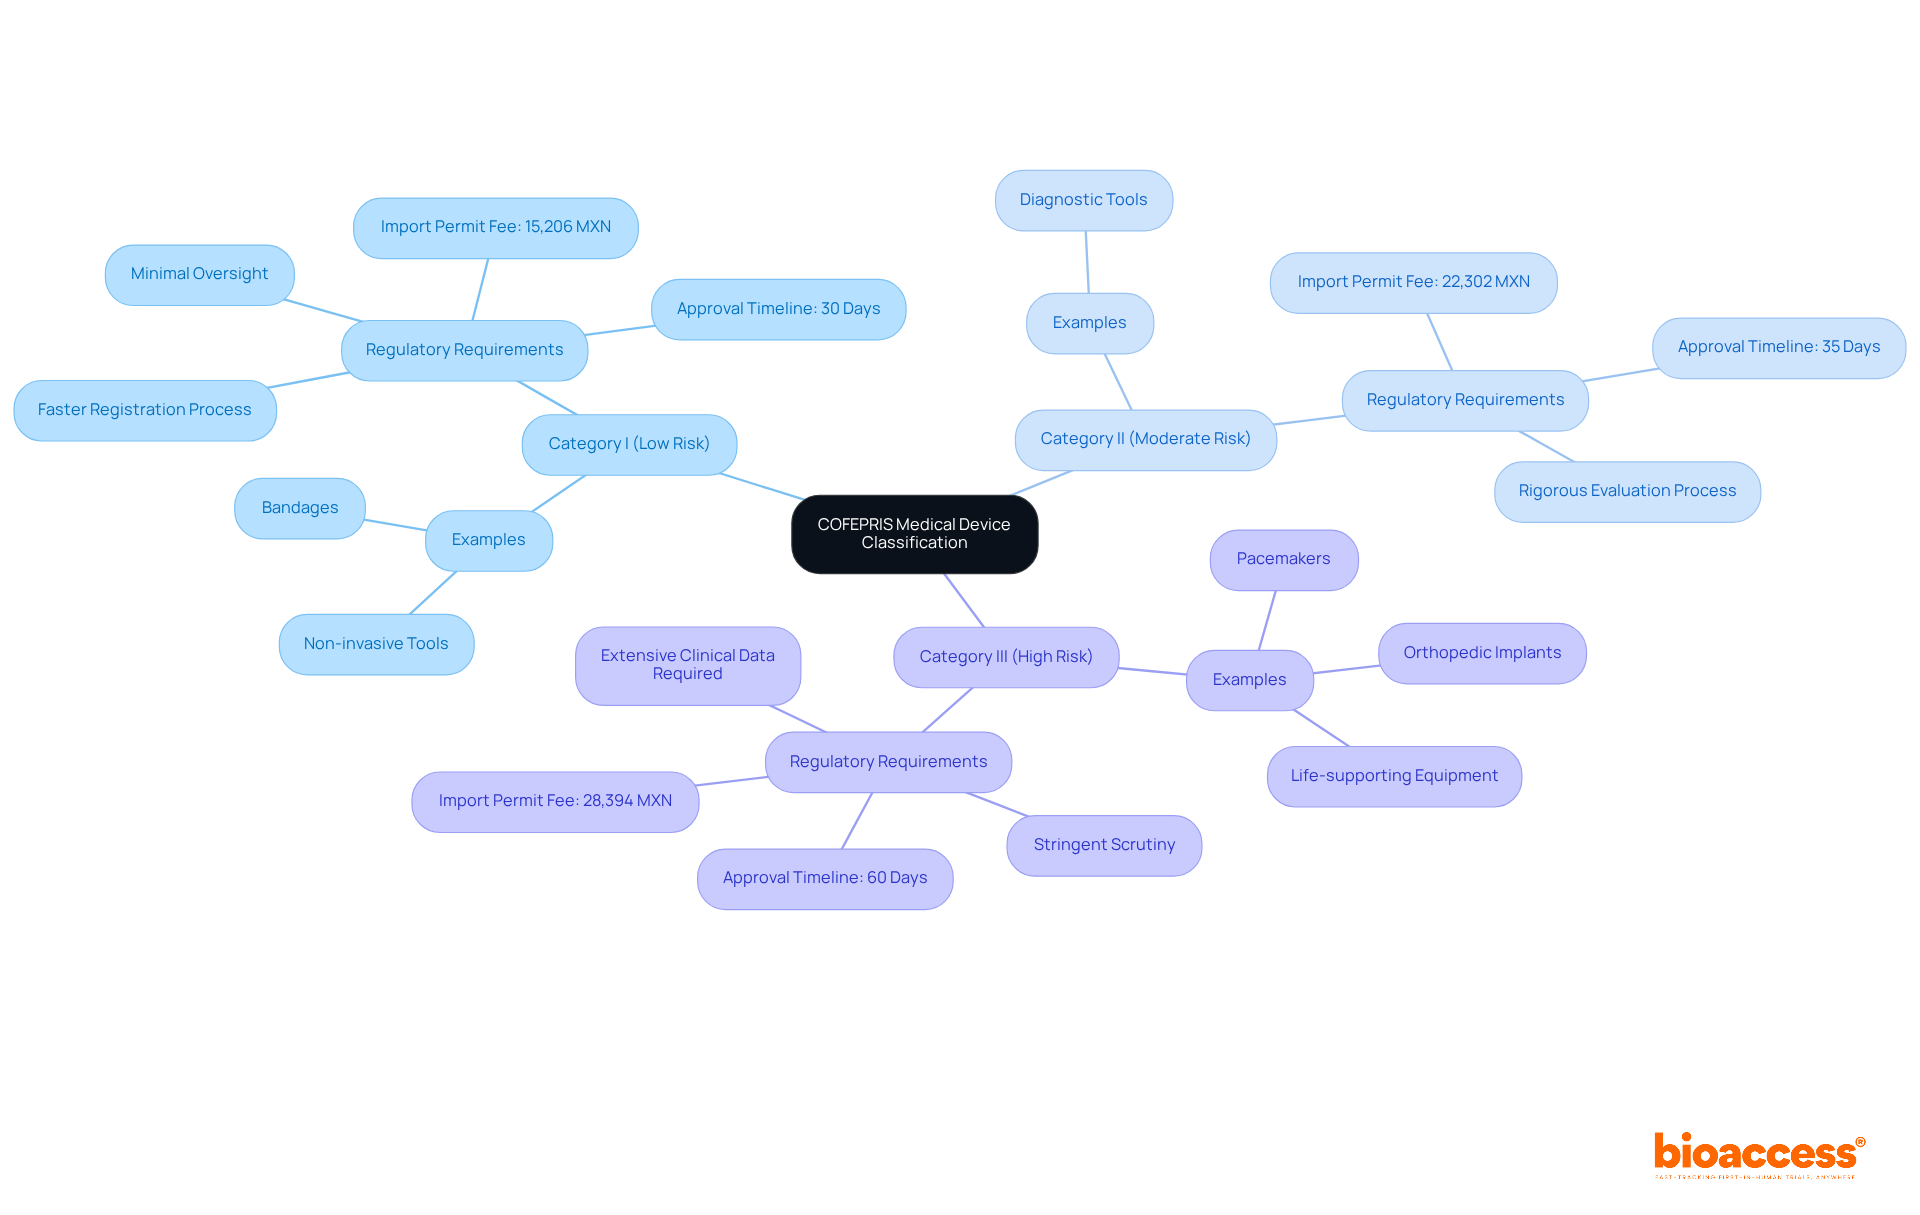
    COFEPRIS (Comisión Federal para la Protección contra Riesgos Sanitarios) issues the sanitary registration that must appear on Mexican labeling before you commercially import and sell a device. The legal spine is the Ley General de Salud plus the device reglamento and the applicable NOMs — especially NOM-137-SSA1 (labeling) and NOM-241-SSA1 (GMP / good manufacturing and quality practices for devices). Classification is risk-based Class I / II / III (with IIa/IIb language used in some COFEPRIS materials). Classification drives dossier depth and the standard-route calendar.

    A 510(k), De Novo, PMA, or CE certificate is not a Mexican registration. Since September 2025 it can be the ticket onto the abbreviated / equivalence pathway if the authorization comes from an IMDRF- or MDSAP-recognized authority (FDA is the usual U.S. case; Health Canada, TGA, and EU MDR authorizations are the other names reviewers expect). That pathway is a summary dossier plus reliance — not a copy-paste of the FDA decision summary into a Spanish folder with no Mexican holder.

    The Mexico Registration Holder is the asset

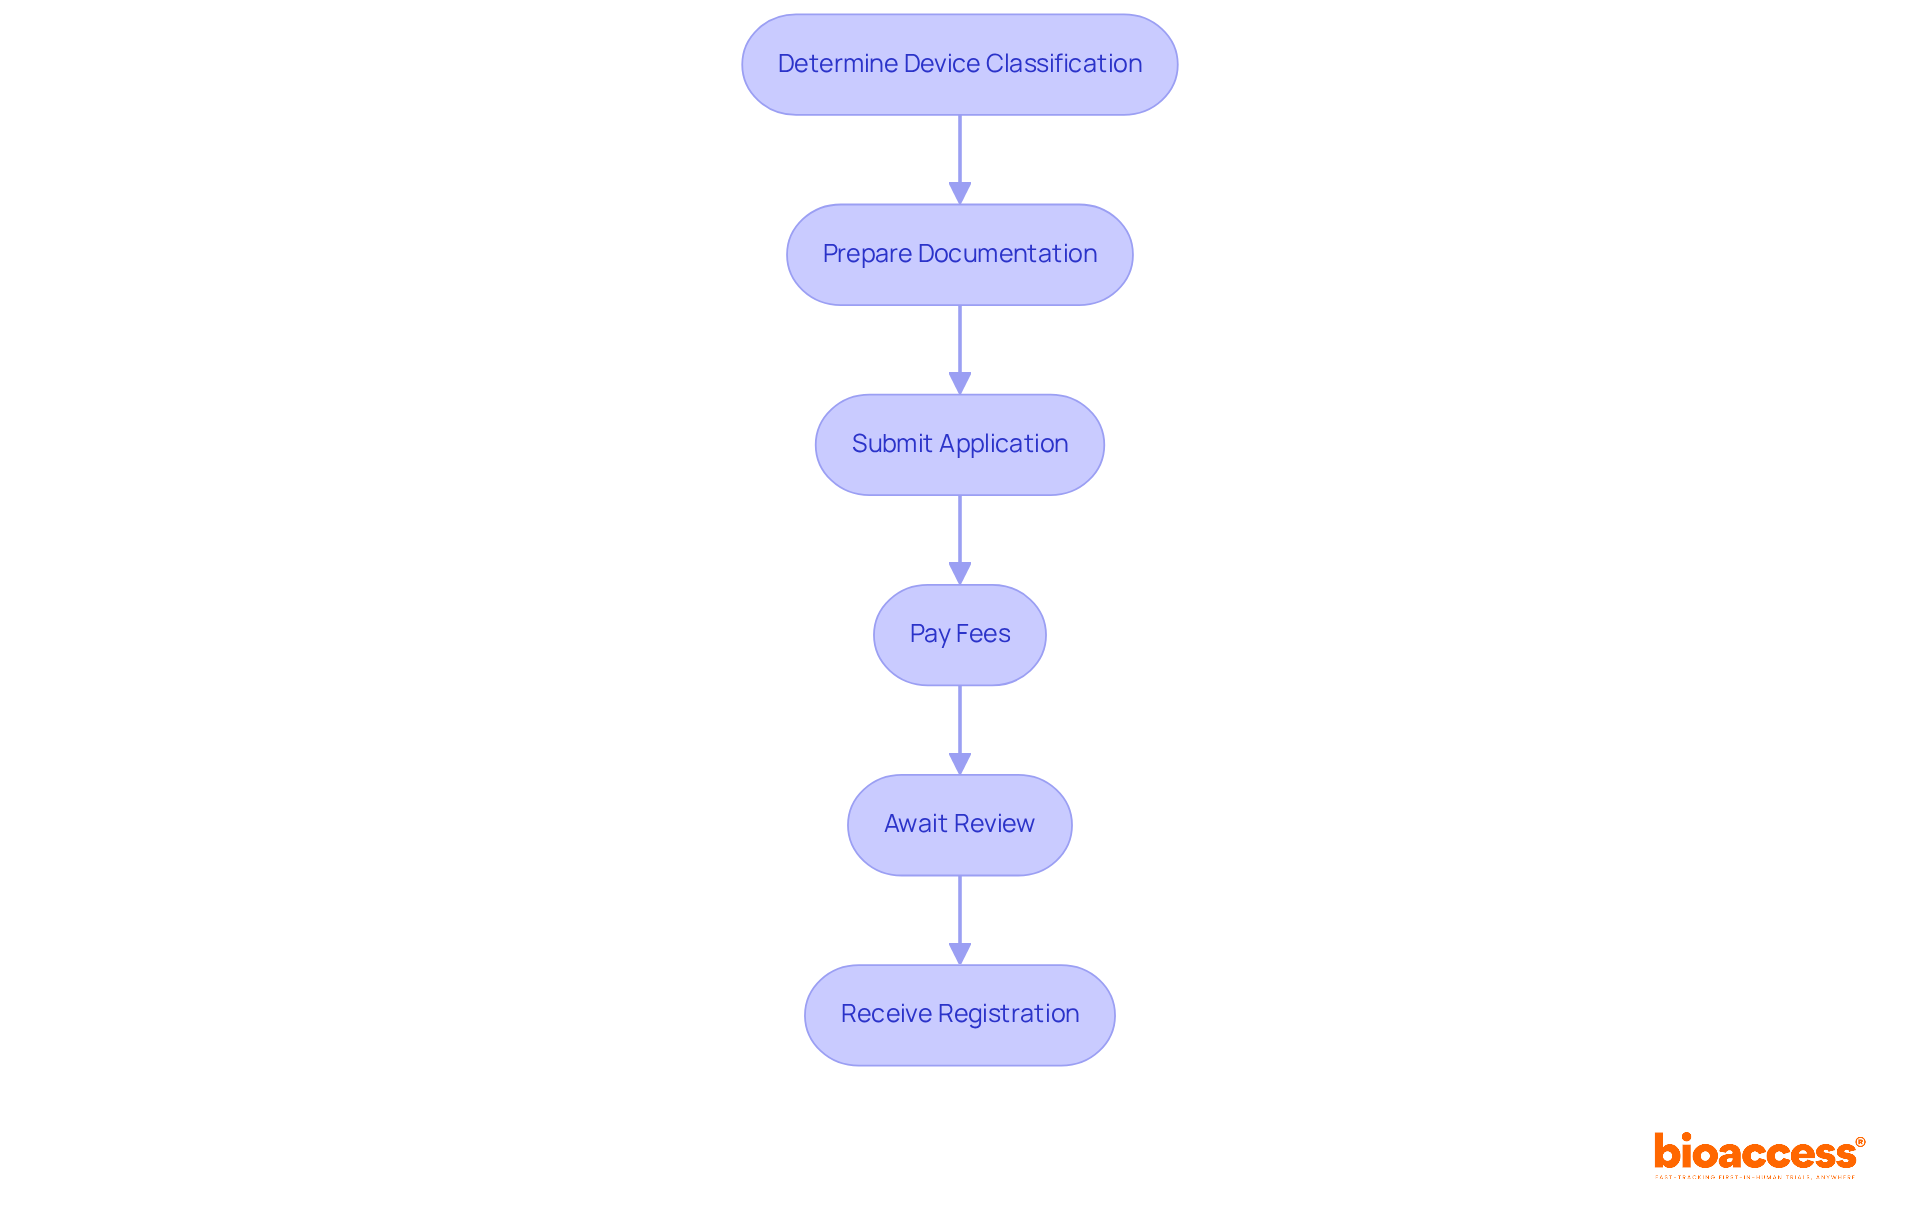
    Foreign manufacturers do not hold the registro sanitario. A Mexico Registration Holder (MRH) — a legally constituted Mexican entity, sometimes still called the authorized representative or sanitary correspondent — files, pays the government fee, and typically owns the number in its name. Transfers are possible and slow. If your exclusive distributor is the MRH, a breakup is a regulatory project.

    • Notarized, apostilled letter of representation / power of attorney that states exactly what the MRH may file, modify, renew, and report.
    • MRH corporate standing and, where applicable, the establishment notices COFEPRIS expects for the activities they perform.
    • A written plan for who is importer of record vs. who is MRH vs. who is distributor. One company can wear two hats. Three hats on a thin distributor is how import permits stall when a person leaves.
    • Exit language: how you will transfer the registration if the commercial deal ends. Put it in the appointment, not in a slide.

    Pathways and a hedged calendar

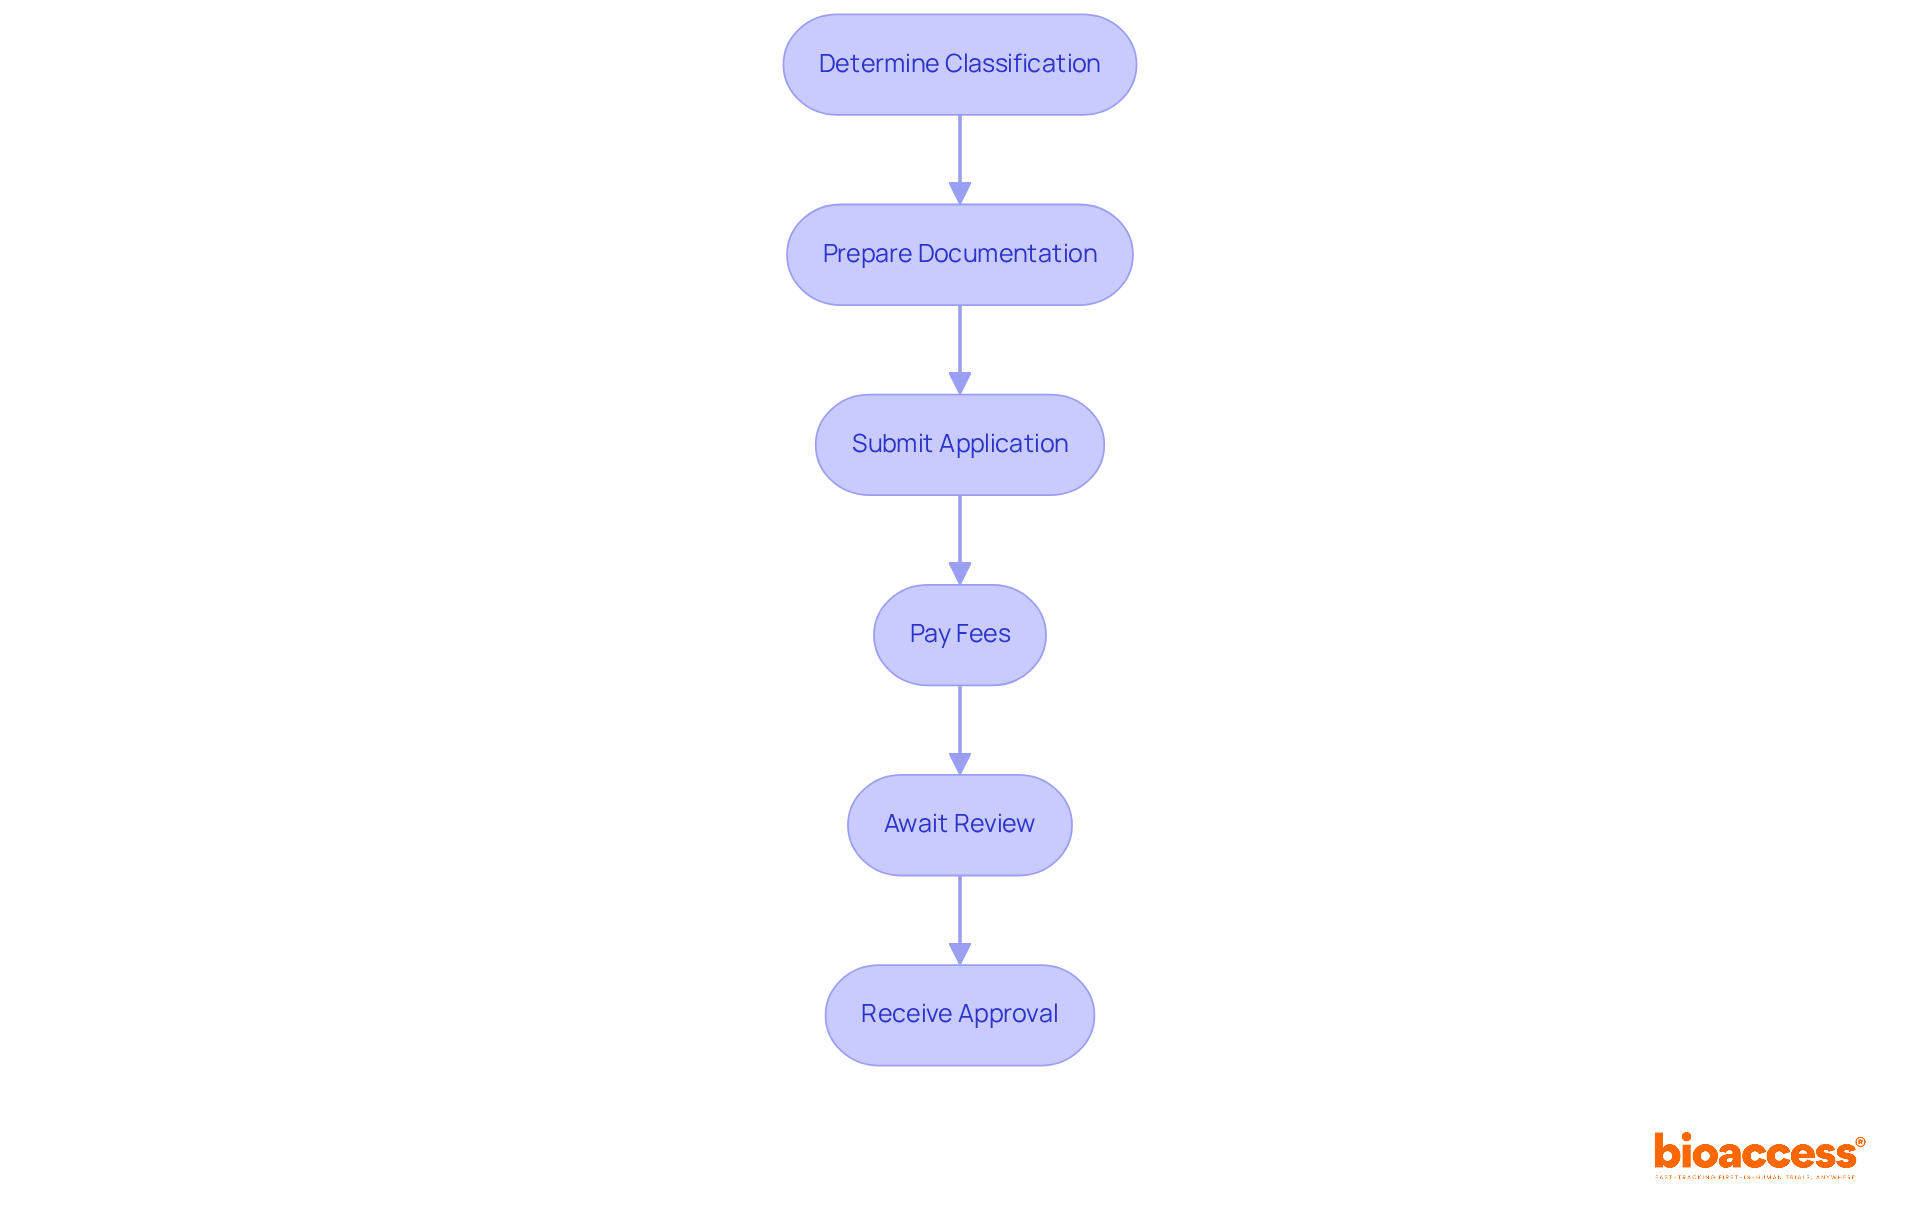
    • Standard route. Full technical dossier. Published planning windows you will hear in 2026: on the order of 20–30 days for many Class I files, 30–60 for Class II, 60–180 for Class III — after a complete filing. Deficiency letters and workload stretch those numbers. Class III implants should not be promised as a 60-day launch.
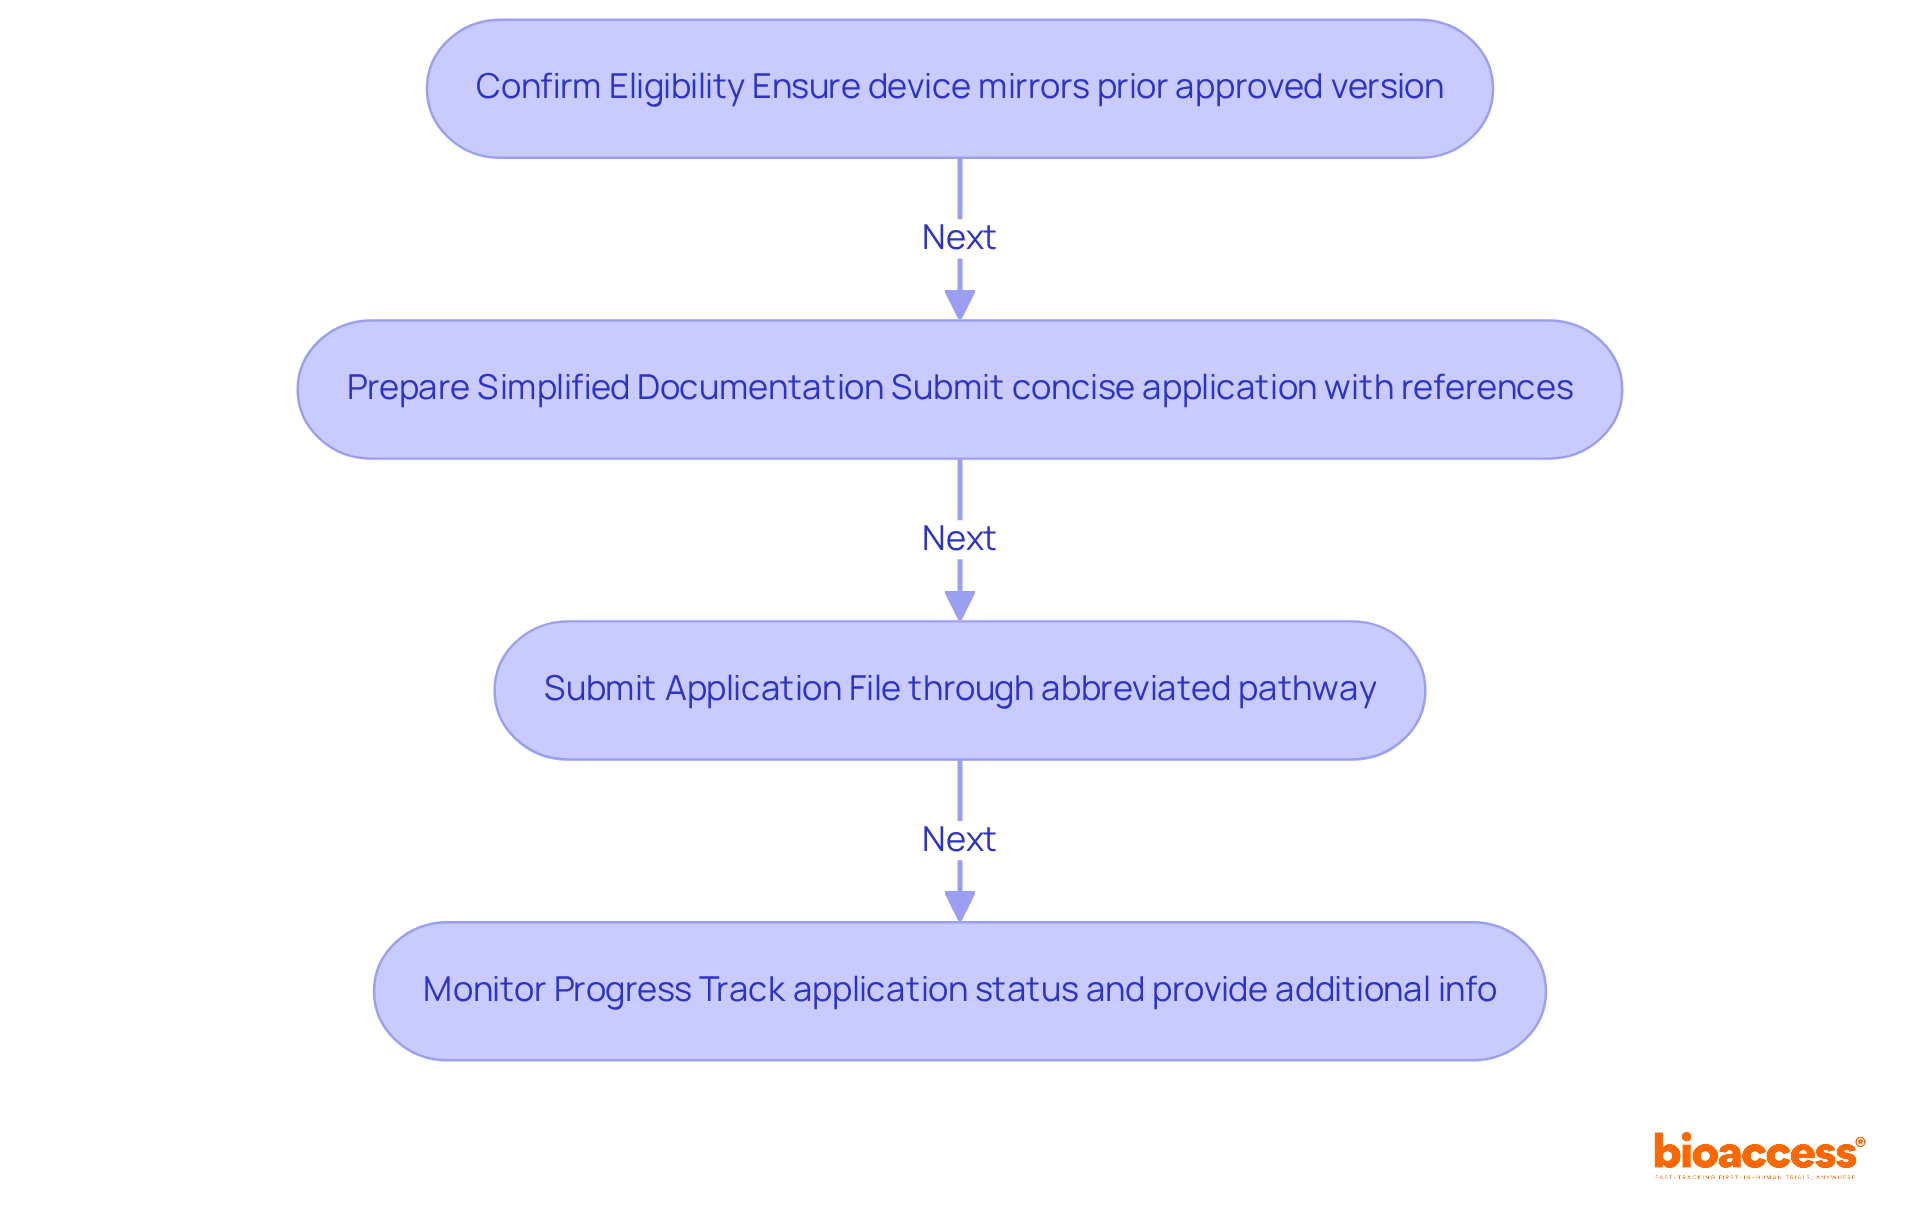
    • Abbreviated / equivalence route (from 1 September 2025). Summary dossier that leans on a valid FDA or other recognized-market authorization. COFEPRIS has socialized a ~30-day target review across classes. Treat 30 days as a target after completeness, not as door-to-door from the day you hire counsel. Spanish labeling, the MRH pack, and “same device” identity (indications, design, manufacturer) are where abbreviated files die.

    March 2025 simplification measures trimmed some administrative steps and compressed certain low-risk reviews. They did not delete the holder requirement.

    Dossier checklist

    Every pathway

    • Device identity: generic and brand names, models, accessories, intended use, and the Mexican class you are claiming.
    • MRH letter of representation, apostilled; manufacturer corporate documents as required.
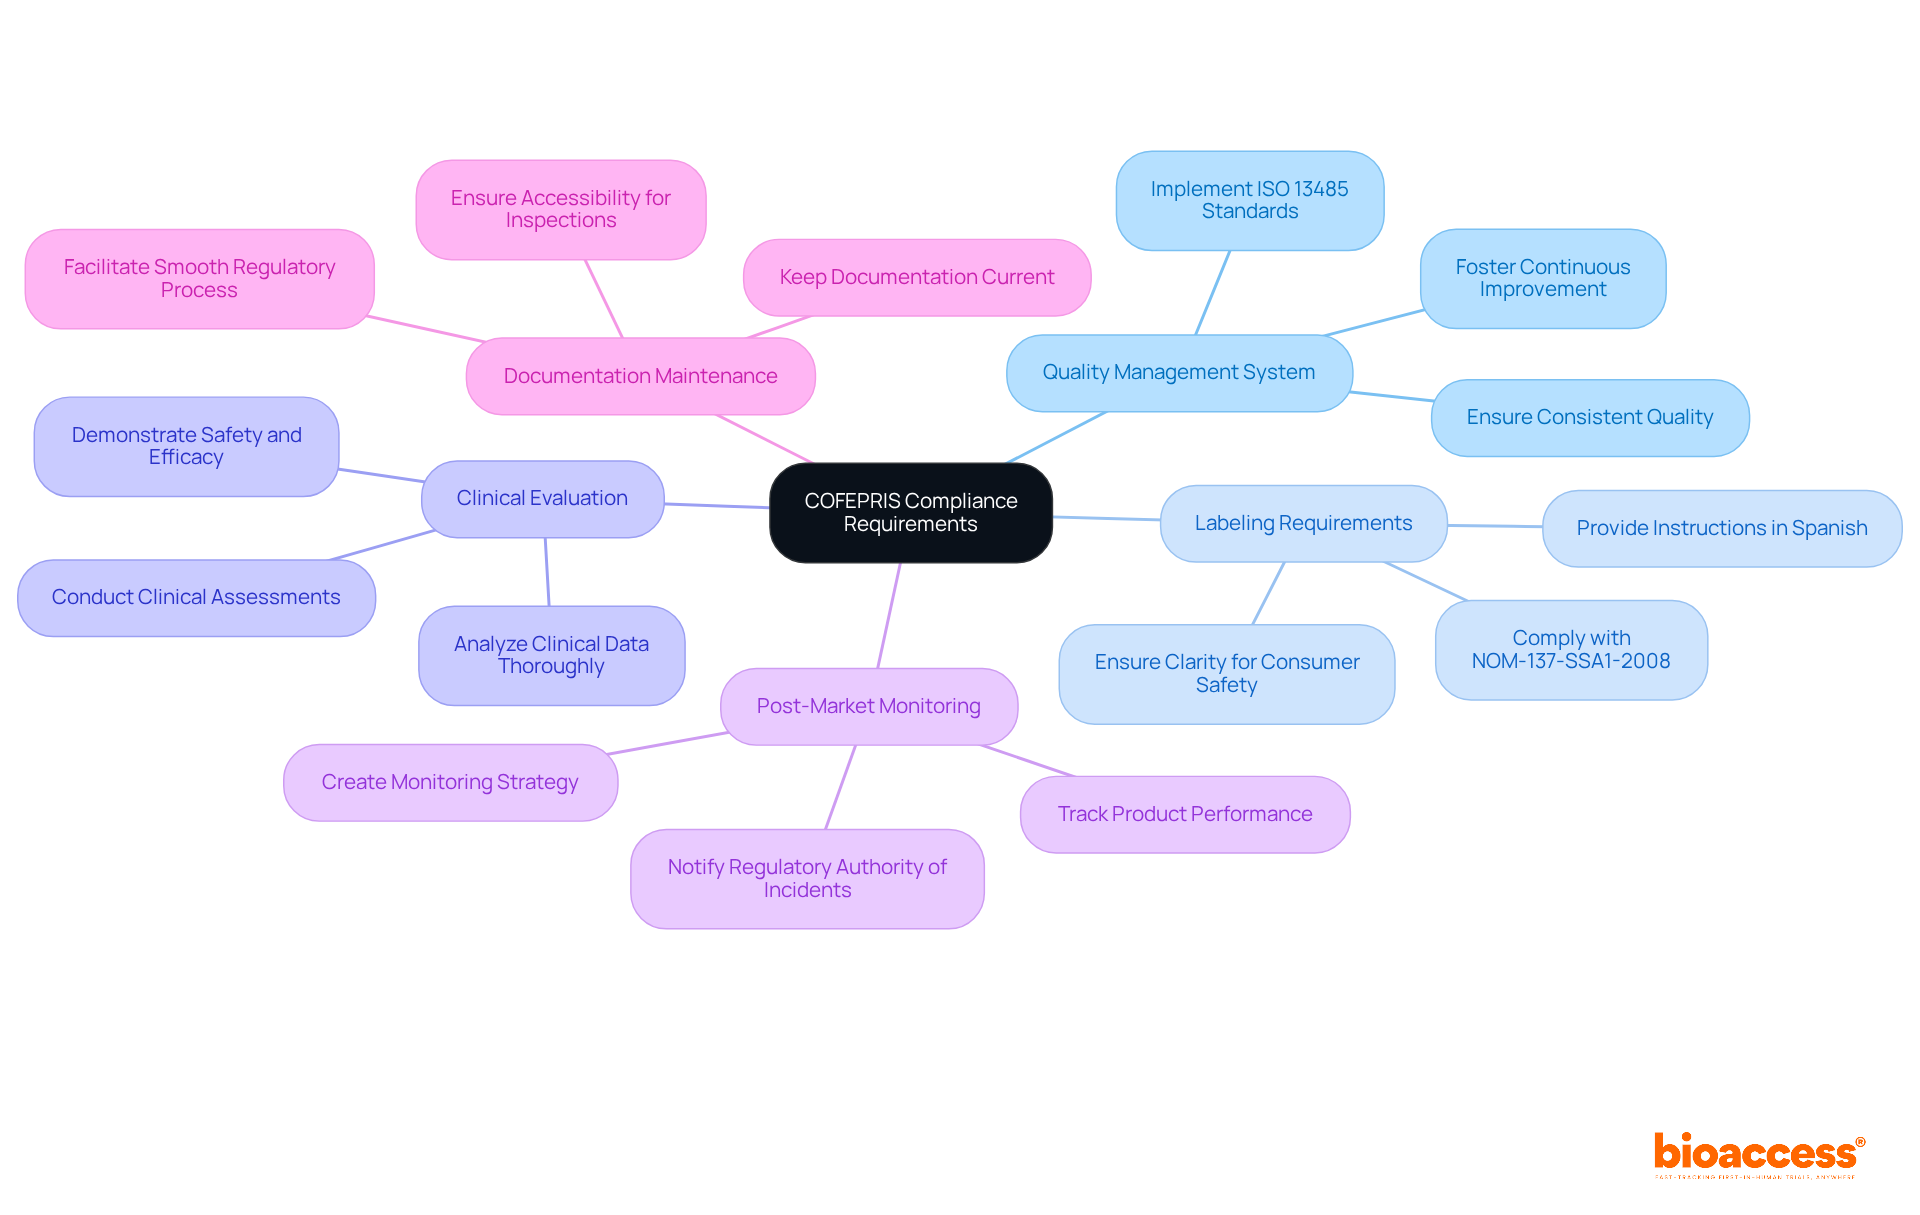
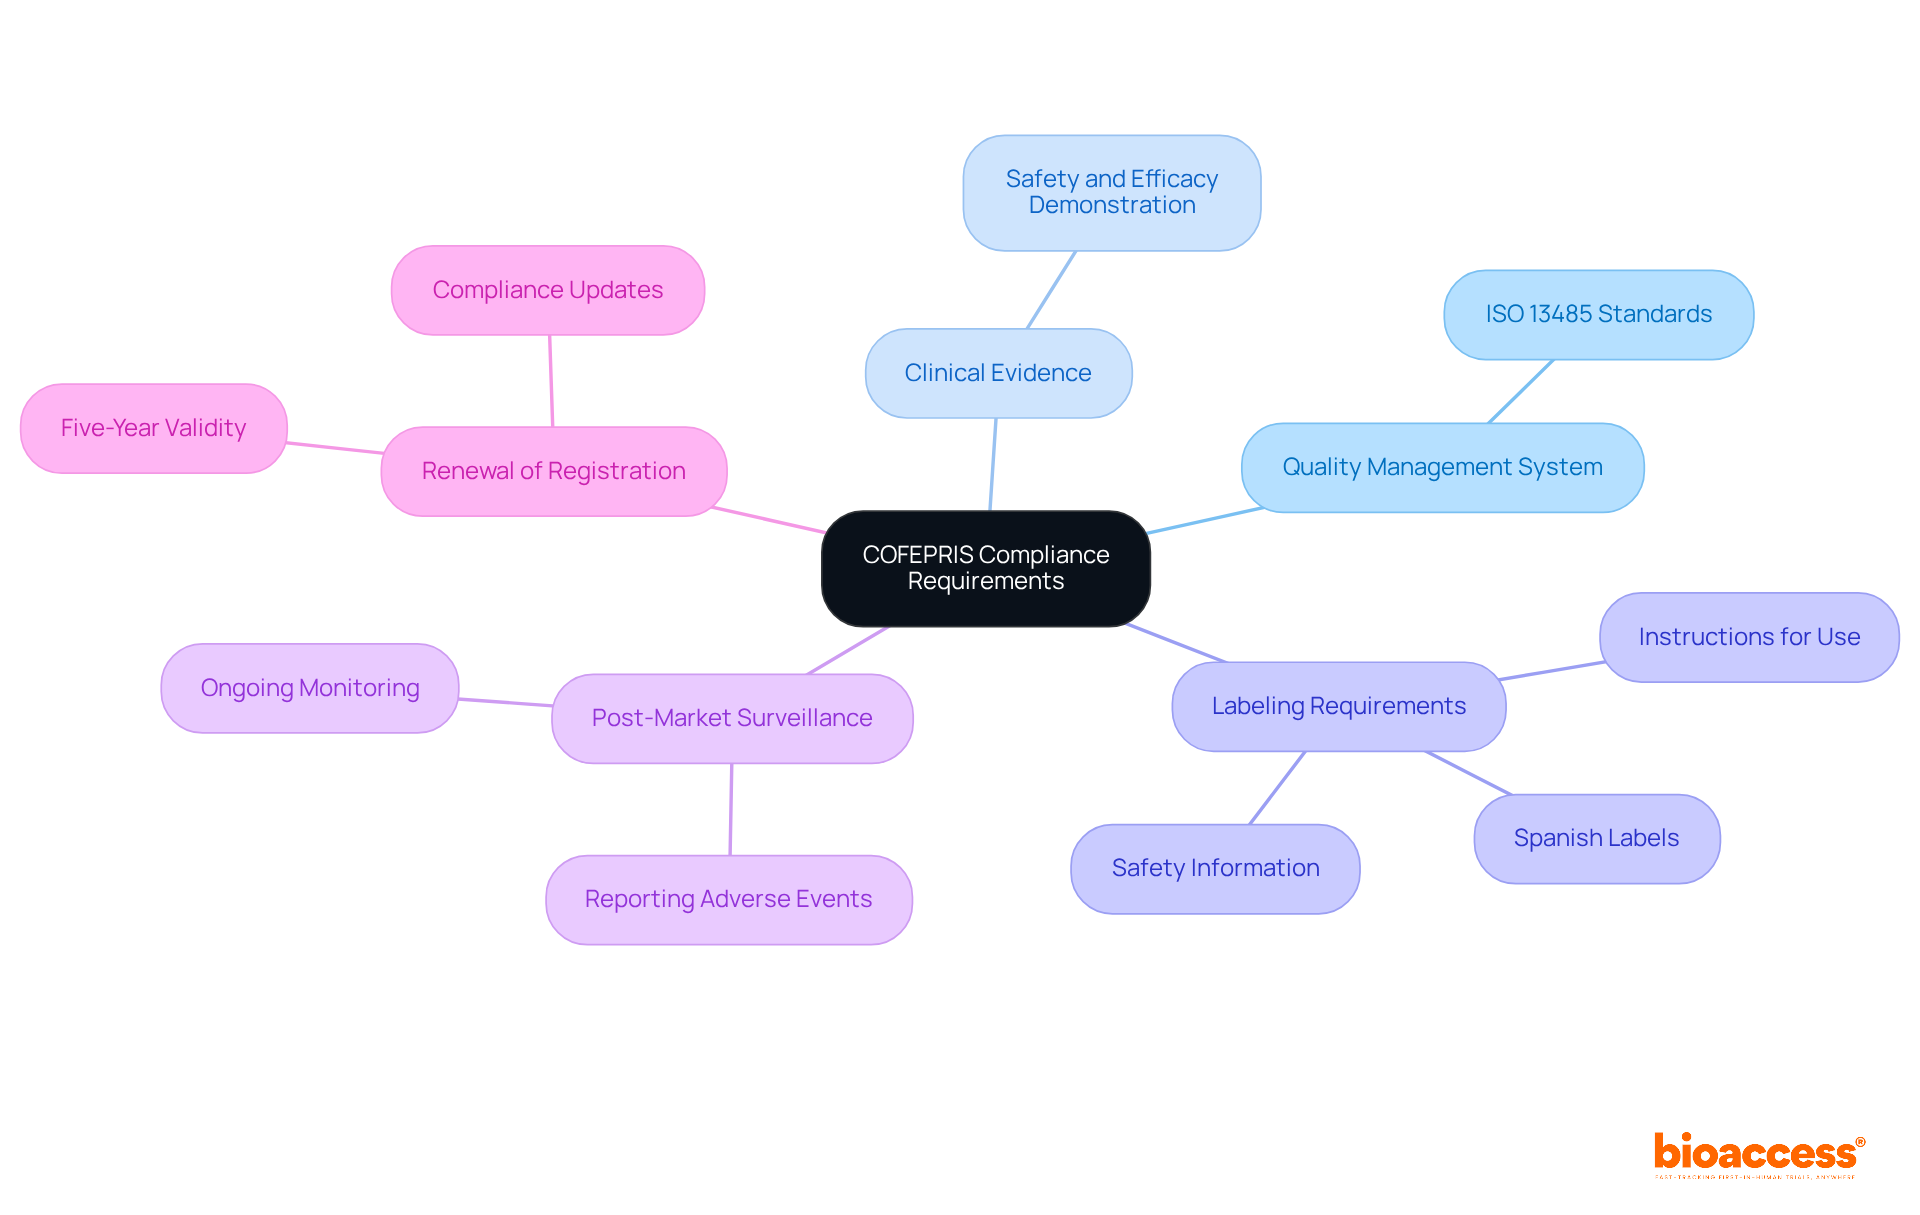
    • QMS evidence — ISO 13485 is the practical standard and is the usual way to speak to NOM-241 expectations. MDSAP or a recognized GMP certificate helps; “we are FDA-registered” alone is a thin story.
    • Spanish labels and IFU per NOM-137: generic name, origin, lot/serial, expiry if applicable, manufacturer, importer/MRH, and a reserved field for the registration number.
    • Proof of payment of the COFEPRIS government fee for the correct clave / modality. Fees are published in MXN and change. Do not freeze a USD “all-in” number from a 2023 blog post.

    Standard route extras

    • Full technical description, drawings, materials, and specifications.
    • Risk analysis (ISO 14971 or equivalent).
    • Biocompatibility, electrical, software, and sterility evidence that matches how the device is sold.
    • Clinical evidence appropriate to Class III and to novel Class II claims.

    Abbreviated route extras

    • Certified evidence of the foreign marketing authorization (FDA clearance/approval letter and current listing story, or the equivalent CE/MDR, Health Canada, TGA pack).
    • A “sameness” memo: indications, design, labeling claims, and legal manufacturer must match what the reference authority approved. A Mexico-only indication is not an abbreviated file.
    • Spanish summary of the foreign review story — not 400 pages of untranslated FDA correspondence.

    Validity, renewals, and technovigilance

    First registrations remain a five-year instrument in normal practice. As of January 2026, subsequent renewals can be granted for periods of up to ten years — useful if you are already on the market and your holder is stable. Technovigilance reporting stays with the MRH. If your U.S. complaint system does not forward Mexico-reportable events to the MRH on a defined clock, you have a regulatory gap, not a “local admin” task.

    FAQ-style close

    Can a U.S. company be the registration holder? Not without a Mexican legal entity acting as MRH. Plan the holder before you book the DIGIPRIS slot.

    Does the abbreviated pathway replace the MRH? No. It shortens the technical review when the foreign authorization is real and the device is the same. The holder still files.

    Is this the same as a COFEPRIS clinical-trial authorization? No. Research ethics and trial import of investigational units are a different authorization. Do not send a 510(k) equivalence pack to a trial desk and expect a sanitary registration number.

    How should we budget? Government fees are only the clave. Translations, apostilles, MRH retainers, and one likely deficiency cycle are the project. Hedge the calendar; do not sell the board a single flat USD fee.

    Where does a multi-country register-and-hold model live? If the devices are already FDA-cleared (510(k)/PMA) or CE-marked and you want an independent holder rather than a distributor-owned number, bioaccess® describes that separately on the LATAM Launch Subscription market-access page. Mexico is usually sequenced with the abbreviated pack and a holder who is not also your only commercial bet.

  • Choosing a Local Comparator for MedTech Reimbursement Dossiers in Brazil, Colombia, and Mexico

    Choosing a Local Comparator for MedTech Reimbursement Dossiers in Brazil, Colombia, and Mexico

    For a MedTech company entering Latin America, the local comparator is more than a line in a clinical-evidence table. It is the reference point that lets a payer, hospital, or health technology assessment (HTA) team judge whether a new device changes outcomes, workflow, resource use, or total cost. A comparator that is scientifically convenient but disconnected from local practice can weaken a reimbursement dossier even when the device performs well.

    The right approach is to choose a comparator by country and care pathway, then build a bridge back to the evidence collected during early clinical development. Brazil, Colombia, and Mexico each have distinct institutions and decision contexts. A common evidence core can support all three, but the comparator rationale and resource-use assumptions should be localized.

    Why comparator choice determines payer credibility

    A comparator should represent the decision a local clinician or purchaser would make if the new technology were not available. That may be an established device, a procedure, a diagnostic pathway, watchful waiting, or a combination of services. The relevant question is not “What is the closest product?” It is “What happens to this patient in this health system today?”

    This distinction matters because HTA considers more than technical performance. Brazil’s CONITEC describes technology assessment in terms that include clinical evidence, economic evaluation, and budget impact. Colombia’s IETS defines HTA as a systematic, multidisciplinary examination of effectiveness, safety, and social, economic, and ethical consequences. Mexico’s CENETEC publishes guidance for the economic evaluation of medical devices. These official frameworks point to the same practical lesson: the comparator must make the consequences of adoption measurable.

    Brazil: anchor the dossier in SUS practice and budget impact

    For a public-system strategy in Brazil, begin by describing the current SUS pathway for the target patient: who provides care, what procedure or technology is used, what resources are consumed, and where delays or complications arise. The comparator should be the realistic alternative within that pathway, not merely the device with the closest engineering specifications.

    Build the evidence package around three layers. First, show comparative clinical outcomes that matter to the patient and provider. Second, quantify resource use, including procedure time, staff, consumables, repeat visits, training, maintenance, and downstream events. Third, model the eligible population and adoption scenarios so the decision maker can see the budget effect under conservative and expanded use.

    Use the current CONITEC HTA materials and methodological guidance to confirm the applicable submission expectations. For an early-stage sponsor, the immediate goal is not to claim a final cost-effectiveness result from a small FIH study. It is to capture the baseline workflow and resource variables that a later model will need.

    Colombia: make the local care pathway explicit

    In Colombia, the comparator should reflect how the service is delivered through the relevant network and what the decision maker can actually change. A global standard of care may not be the operational baseline if local hospitals use a different procedure, staffing model, referral pattern, or purchasing arrangement.

    Start with a pathway map: entry point, diagnostic work-up, treatment or intervention, follow-up, complications, and referral. For each step, document who performs it, how long it takes, what equipment and supplies are required, and which outcomes are visible to the payer or hospital. Then explain why the selected comparator is the appropriate reference for that pathway.

    IETS materials emphasize clinical effectiveness, safety, and the economic and social implications of health technologies. Translate that multidimensional view into a dossier structure: comparative outcomes, adverse events, quality-of-life or functional measures where relevant, staff and infrastructure requirements, and costs that are material to the Colombian setting. The IETS overview of HTA is a useful official reference when defining the scope of the evidence plan.

    Mexico: connect the comparator to implementation and economics

    For Mexico, a credible comparator must fit the institution and service context in which the device would be adopted. Ask whether the alternative is delivered in public hospitals, private facilities, or both; whether the required equipment is already installed; and whether the new technology changes training, staffing, maintenance, or referral patterns.

    Separate acquisition price from total implementation cost. A device can appear inexpensive while requiring new imaging, specialized staff, software, service contracts, or additional visits. Conversely, a higher purchase price may be offset by shorter procedure time or fewer repeat interventions. Record these variables prospectively during early studies so that a later economic model can compare like with like.

    Review the Mexican CENETEC guidance for economic evaluation of medical devices and adapt the evidence plan to the intended decision setting. Current institutional requirements should be confirmed before a formal submission, especially when the product will be evaluated by more than one payer or hospital network.

    Build one comparator matrix across three countries

    A sponsor can reduce rework by maintaining a master comparator matrix with country-specific annexes. Capture at least:

    • Clinical baseline: the patient population, indication, current intervention, and relevant outcomes.
    • Workflow baseline: procedure steps, care setting, staff time, equipment, and referral pattern.
    • Safety baseline: complications, repeat procedures, contraindications, and follow-up burden.
    • Economic baseline: acquisition, consumables, personnel, maintenance, admissions, and downstream resource use.
    • Adoption baseline: training, infrastructure, procurement, and implementation constraints.
    • Decision use: the payer, hospital, or HTA question the comparison is intended to answer.

    Do not wait for a pivotal trial to collect these fields. Even a small early-feasibility program can record procedure duration, staff mix, consumables, unplanned visits, technical failures, and patient-reported measures using a prespecified template. Those observations will not replace comparative evidence, but they can reveal which assumptions need validation and which outcomes matter locally.

    Frequently asked questions

    Should the comparator be the cheapest available option?
    No. It should be the realistic alternative used in the target care pathway. The lowest purchase price may not be the lowest-cost or most relevant option after staff time, complications, maintenance, and follow-up are included.

    Can one comparator serve Brazil, Colombia, and Mexico?
    Sometimes the clinical concept is shared, but the service pathway, staffing, infrastructure, and purchasing context may differ. Use a common evidence core with country-specific comparator definitions and assumptions.

    Is comparator planning relevant during an FIH study?
    Yes. FIH studies are not designed to prove final reimbursement value, but they can capture baseline workflow, safety, resource use, and patient-centered measures that prevent avoidable evidence gaps later.

    A locally credible comparator turns a MedTech dossier from a product description into a decision analysis. By defining the reference pathway early and documenting how it differs across Brazil, Colombia, and Mexico, sponsors can make later regulatory, HTA, and reimbursement conversations more focused and more defensible.

  • COFEPRIS Just Made Clinical Research Approval Simpler In Mexico. Here’s What Changed.

    COFEPRIS Just Made Clinical Research Approval Simpler in Mexico. Here’s What Changed.

    COFEPRIS Just Made Clinical Research Approval Simpler in Mexico. Here’s What Changed.

    Published: May 18, 2026 | bioaccess® Research and Regulatory Team

    The Acuerdo and Its Limits

    On May 4, 2026, Mexico’s Comisión Federal para la Protección contra Riesgos Sanitarios published a Diario Oficial de la Federación Acuerdo that took effect two days later, on May 6. The Acuerdo formalized mandatory digital submission of all clinical research protocols through DIGIPRiS — COFEPRIS’s electronic platform — and introduced an exemption category that removes the authorization requirement entirely for a defined class of low-risk studies. The headline reads as regulatory modernization. For a first-in-human founder evaluating Mexico as a clinical site, the reality is more textured than the headline suggests.

    Mexico has long held structural advantages for clinical research that its regulatory timeline has historically undercut. It is the second-largest pharmaceutical market in Latin America. Its urban research sites in Mexico City and Monterrey are well-staffed and experienced. The patient population for therapeutic categories ranging from urology to metabolic disease is large. What founders and regulatory directors have historically encountered is a submission process that, by COFEPRIS’s own published data, averaged up to 400 days for clinical trial approval before the current modernization wave began.

    The May 4 Acuerdo does not eliminate that history overnight. It signals a directional change — one that is already showing measurable effects in the data — and it introduces two specific operational shifts that matter more than the general narrative of “faster approvals”: a mandatory digital platform with concrete submission requirements, and an exemption classification that most non-Mexico-specialist CROs do not surface for their clients. Understanding both is how founders use this moment rather than simply noting it.

    bioaccess® has operated across 10 Latin American countries since 2010, supporting 58 client companies through first-in-human programs. This post draws on that operational context to translate the Acuerdo from regulatory text into a practical framework for founders and regulatory affairs directors building or revising their LATAM clinical strategy.

    What the Acuerdo Actually Changed

    The May 4 DOF Acuerdo, published at sidof.segob.gob.mx/notas/5786604, mandates three operational shifts:

    • DIGIPRiS is now the mandatory submission channel for all new clinical research protocols. Sponsors and CROs must submit new protocols, amendments, and technical reports exclusively through the DIGIPRiS portal. Legacy paper-based filing pathways are no longer accepted for new submissions. This applies regardless of study phase, therapeutic category, or sponsor geography. An active institutional account with delegated user roles — authorizer, editor, viewer — must be established before any submission clock starts. First-time submitters without existing platform credentials should allow 2–4 weeks for account setup and role delegation before protocol review begins.
    • “Investigación sin riesgo” studies are fully exempt from COFEPRIS authorization. Mexico’s health research regulatory framework (Reglamento de la Ley General de Salud en Materia de Investigación para la Salud) classifies research into risk tiers. “Investigación sin riesgo” — no-risk research — covers studies that use documentary techniques, structured interviews, observation, and non-invasive physiological measurement without procedures that exceed standard clinical contact. Studies in this category do not require COFEPRIS authorization under the Acuerdo and do not submit through DIGIPRiS for authorization purposes. Device sponsors developing companion diagnostics, observational registries, or instrument-only studies should determine whether their study qualifies before assuming full COFEPRIS submission overhead. Misclassification in either direction costs time.
    • Single-opportunity prevention and immediate resolution schemes. The Acuerdo introduces a single-opportunity rule for submission completeness — incomplete dossiers are flagged at intake rather than returned weeks into the review cycle. For defined categories, immediate resolution pathways are introduced. Both changes are designed to reduce the back-and-forth that historically inflated review timelines well beyond regulatory normatives.

    Prior to the Acuerdo, DIGIPRiS had been in partial rollout since 2025. As of May 2026, the platform manages 90% of protocol amendment workflows. The transition to mandatory full-protocol submission through the same channel completes that digital migration. For CROs and sponsors with established accounts, this is an efficiency gain. For those entering Mexico for the first time, platform credentialing is now a prerequisite step, not a parallel task.

    The 400-Day Baseline: What the Data Actually Says

    Any accurate assessment of the Acuerdo’s significance requires anchoring in the numbers COFEPRIS itself has published. The agency’s Digitalización 2026 Plan — a 60-million-peso initiative with a December 2026 completion target, surfaced in mid-May 2026 — explicitly acknowledges that historical clinical trial approval times averaged up to 400 days prior to the current modernization wave. That number is not an advocacy figure. It is the baseline COFEPRIS used to set its own performance improvement targets.

    Against that baseline, the 2025 DIGIPRiS implementation data is meaningful: average protocol approval times dropped from 90 to 45 calendar days between January and April 2025 as the platform was progressively deployed. Amendment reviews averaged 57 days — a 37% improvement over prior normatives. By May 2026, the platform manages 90% of amendment workflows. These numbers reflect a partial rollout; the full mandatory deployment that began May 6 will produce new performance data over the coming quarters.

    The honest framing for a founder: the Acuerdo signals structural intent backed by published data. It does not transform Mexico’s regulatory environment overnight. Budget conservatively on timeline while treating the directional improvement as real. For programs that can align protocol submission with a Mexico study start, the compression from 90 to 45 days — let alone from 400 — is structurally significant.

    The Fastest Route: COFEPRIS Reliance for Reference-Authority Protocols

    For sponsors whose protocols have already received authorization from a WHO-recognized high-level regulatory authority — including the FDA, EMA, or MHRA — the fastest Mexico submission route is not the standard DIGIPRiS pathway. It is the COFEPRIS reliance mechanism published in the Diario Oficial de la Federación on March 24, 2025, as analyzed by Global Regulatory Partners.

    Under the reliance framework, protocols already authorized by reference regulators receive an abbreviated COFEPRIS review with target timelines of:

    • 30 business days for medical devices
    • 45 business days for drugs and biologics

    These timelines are not guarantees — they are regulatory normatives. But for a device sponsor who has already completed an FDA Early Feasibility Study, or whose protocol carries CE mark approval, the reliance pathway represents a materially faster entry than standard review. DIGIPRiS makes the submission process for reliance applications cleaner and more trackable than the legacy paper system.

    The practical implication: device founders should confirm whether their existing FDA or EMA documentation qualifies their Mexico protocol for the reliance pathway before defaulting to standard submission. The 30-business-day target for devices under reliance — approximately six calendar weeks — positions Mexico competitively with other LATAM FIH markets when this pathway applies.

    For sponsors evaluating Mexico as part of a U.S.-plus-LATAM clinical strategy, the reliance pathway and the standard DIGIPRiS route serve different program types. Reliance is the right tool for sponsors with prior reference-authority approval. DIGIPRiS standard review is the route for novel protocols. Knowing which applies to your study at the outset determines whether Mexico belongs in your Year 1 clinical plan or your Year 2.

    Where Mexico Fits in a LATAM Clinical Portfolio

    Mexico’s regulatory position in the LATAM FIH landscape is distinct from its regional peers. A direct comparison helps founders understand where Mexico fits in a multi-country program design.

    Country Regulatory Authority Target Review Timeline Fastest Ethics Timeline Key Pathway Feature
    Colombia INVIMA ~30 days (authority) ~15–18 days (targeted, experience-based) Fastest FIH ethics timeline in LATAM; strong site density
    Mexico COFEPRIS 30 BD (devices, reliance) / 45 BD (drugs, reliance) / 45 CD (standard DIGIPRiS) 4–8 weeks (typical) Reliance pathway for FDA/EMA-approved protocols; second-largest LATAM pharma market
    Brazil ANVISA 90 days (parallel review, RDC 945/2024) Concurrent with ANVISA review Parallel ethics and authority review; largest LATAM market by patient volume
    Argentina ANMAT 62 days (Disposición 7516/2025) Concurrent with ANMAT review Streamlined 62-day normative; strong oncology and metabolic disease site base

    Colombia remains the fastest LATAM jurisdiction for first-in-human medical device studies on a combined authority-plus-ethics basis. For sponsors whose primary objective is speed to FIH data, Colombia typically anchors the program.

    Mexico’s distinct value is patient population size, strong research sites in Mexico City and Monterrey, and — post-Acuerdo — a materially improved submission process for both standard and reliance pathways. It is not the fastest LATAM market, but it is increasingly competitive for sponsors requiring large patient pools, FDA/EMA-eligible reliance, or a Mexico regulatory track record for commercial purposes. For a multi-country program — Colombia for FIH speed, Mexico for expanded cohort enrollment — the post-Acuerdo improvement changes the sequencing calculus.

    What Founders Should Do Now

    If Mexico is in your clinical plan for 2026 or 2027, three actions should happen before your next protocol submission discussion:

    • Establish DIGIPRiS credentialing immediately. The platform requires institutional account setup, user role delegation, and CRO authorization documentation. This is not a same-day process. For sponsors working with a CRO that already holds active DIGIPRiS credentials, this step is absorbed into existing infrastructure. For sponsors engaging a CRO for the first time, confirm credential status before the contract is signed. A CRO without an active account adds 2–4 weeks before your protocol review clock starts — time that has nothing to do with the regulatory review itself.
    • Determine if your study qualifies as “investigación sin riesgo.” Sponsors developing observational registries, companion diagnostics, or non-invasive measurement instruments should review their study design against the risk classification framework before assuming full COFEPRIS submission overhead. A regulatory classification confirmation at protocol design stage is a 2–3 day exercise. Misclassification costs 4–8 weeks.
    • Confirm your protocol’s reliance eligibility. If your study has received FDA or EMA authorization, the reliance pathway targets 30 business days for devices and 45 business days for drugs. This is the fastest available COFEPRIS review track and requires specific documentation at submission. DIGIPRiS submission under the reliance pathway follows the same platform process as standard review but with a different regulatory dossier structure. Confirm reliance eligibility and documentation requirements with your CRO before drafting the submission package.

    Navigating DIGIPRiS requires an institutional account with established COFEPRIS relationships, documented sponsor delegation, and a track record of dossier completeness under the single-opportunity rule. A first-time submitter absorbs the platform learning curve on your protocol’s timeline. A CRO with active Mexico credentials absorbs it before your protocol arrives.

    Three Questions to Determine Whether Mexico Belongs in Your 2026 Clinical Plan

    The Acuerdo doesn’t change the fundamental logic of LATAM site selection for FIH programs. It changes one variable — submission timeline and process — in a direction that favors Mexico more than the previous two years did. The three questions that determine whether that change is material for your program:

    1. Does your protocol have FDA, EMA, or MHRA authorization? If yes, the COFEPRIS reliance pathway positions Mexico’s device review at 30 business days — competitive with Colombia on a combined basis for sponsors who don’t need ultra-fast ethics timelines. If no, standard DIGIPRiS review timelines apply and Colombia likely leads on speed.
    2. Does your primary endpoint require a large patient pool that a single Colombia site cannot support? Mexico’s site density in Mexico City and Monterrey, combined with the post-Acuerdo submission improvement, makes Mexico a natural partner for expanded cohort enrollment in programs that opened in Colombia. For sponsors needing 30–50+ patients in a single FIH program, a Colombia-plus-Mexico multi-site design may be the right structure.
    3. Is Mexico a target commercial market? If your device’s commercial path includes Mexico — a market of 130 million people with a growing private healthcare sector — building a Mexico regulatory track record at FIH stage is not just a trial design question. It is a commercial infrastructure question. The DIGIPRiS improvement makes it less costly to establish that track record early.

    If you answer yes to any of these three questions, Mexico belongs in your 2026–2027 clinical planning discussion. The Acuerdo gave it a better position on the board than it held twelve months ago.

    Next Steps

    If you are evaluating Mexico as part of a LATAM FIH or multi-country clinical program, the time to establish DIGIPRiS infrastructure and confirm your study’s regulatory classification is before your protocol is finalized — not after. The window where Mexico’s post-Acuerdo momentum aligns with available site capacity and a CRO team already credentialed on the platform is now.

    Book a meeting to discuss where Mexico fits in your clinical strategy, or use the clinical trial cost calculator to model per-patient and total program costs across LATAM jurisdictions.

    Sources

  • Master the Mexico Public Tender Process for Medical Devices

    Master the Mexico Public Tender Process for Medical Devices

    Introduction

    Navigating the Mexico public tender process for medical devices offers a significant opportunity for stakeholders in the healthcare sector. Recent reforms have transformed the landscape, introducing greater transparency and efficiency. By understanding the intricacies of this process, businesses can strategically position themselves for success, tapping into a rapidly growing market. However, with various types of tenders and strict eligibility criteria, how can companies ensure they not only meet the requirements but also distinguish themselves in a competitive bidding environment?

    Understand the Mexico Public Tender Landscape

    Navigating the for healthcare equipment is crucial for stakeholders aiming to thrive in a rapidly evolving landscape. Recent reforms by the Mexican government have significantly transformed the , resulting in enhanced transparency and efficiency. A new now consolidates procurement processes under the Ministry of Health, emphasizing the necessity for compliance with updated laws and regulations regarding . Key players, such as the , are pivotal in the , influencing the future of .

    To develop an effective , staying informed about – the official government portal for public procurement – is essential. This platform serves as a vital resource for stakeholders, enabling them to position themselves advantageously in the competitive tendering landscape. Familiarity with these dynamics not only empowers stakeholders but also enhances their ability to navigate challenges effectively. By understanding the intricacies of the bidding process, stakeholders can seize opportunities that align with their strategic goals.

    The central node represents the overall landscape, while branches show important aspects like reforms and strategies. Each color-coded branch helps you see how these elements relate to the tender process.

    Identify the Types of Tenders Available

    In Mexico, proposals for can be classified into several distinct types, each possessing unique characteristics that influence . Understanding these classifications is crucial for navigating the competitive landscape effectively.

    1. Open Tenders: These publicly announced bids allow any qualified supplier to submit a proposal. As the most common type of bid, they are particularly advantageous for companies aiming to enter the market. In 2026, are expected to constitute a significant portion of the procurement environment, reflecting a commitment to transparency and competition.
    2. : This format invites only selected suppliers to bid, often based on pre-qualification criteria. For companies with established market relationships, this can provide a strategic advantage in securing contracts.
    3. : This method enables government entities to award contracts without a competitive bidding process, typically in urgent situations or for specialized products. While this approach can expedite procurement, it may limit opportunities for broader participation.
    4. : Aimed at , this bid type maximizes competition and includes two proposals: one for Drugs and another for .
    5. : Initiated when the Yearly Tender fails to meet supply needs, s can be organized by public health institutions with adequate budgets.

    Grasping these types will empower you to tailor your approach and enhance your chances of success in the bidding process. As the market evolves, staying informed about the dynamics of versus , including recent changes in the , will be essential for navigating this competitive environment.

    The central node represents the main topic of tender types. Each branch shows a specific type of tender, with additional details about its characteristics. This layout helps you see how each type differs and what strategies might be best for each.

    Meet Eligibility Criteria and Requirements

    To effectively engage in the for healthcare products, businesses must meet . These key requirements are crucial for success in the :

    1. Registration: Companies must register in the CompraNet system, a prerequisite for all bidders. As of 2026, approximately 75% of companies have successfully fulfilled these registration requirements, underscoring the significance of this step in the .
    2. Legal Compliance: Proof of is essential, including adherence to tax obligations and labor regulations. Engaging a local representative can facilitate this process, ensuring that all are met. Experts like Ana Criado emphasize that understanding the is crucial for navigating these complexities.
    3. : Bidders must submit comprehensive technical documents that validate the quality and safety of their . This includes obtaining necessary certifications from COFEPRIS, Mexico’s regulatory authority for health products. Insights from industry leaders highlight the importance of thorough documentation to meet these standards.
    4. Financial Stability: Some bids may require to showcase the company’s stability and ability to meet contractual obligations. This aspect is vital for building trust with procurement authorities.

    It is essential to thoroughly examine the proposal documents for any additional requirements specific to each submission, as these can vary significantly. Expert advice suggests that maintaining proactive transparency and compliance with local regulations can greatly enhance a bidder’s competitive position in the for devices.

    The central node represents the overall eligibility criteria, while the branches show the specific requirements needed to participate in the tender process. Each branch contains important details that explain what businesses need to do to qualify.

    Follow the Step-by-Step Bidding Process

    To effectively bid on , follow this structured process:

    1. Monitor : Regularly access the to stay updated on new that align with your product offerings. This platform is crucial for tracking opportunities in real-time.
    2. Prepare Documentation: Compile all necessary documentation, including , , and . The typical duration to prepare these documents can differ, but it generally requires about 15 to 30 days, depending on the intricacy of the proposal.
    3. Submit Your Bid: Complete the online submission through CompraNet, ensuring that all required documents are uploaded accurately and submitted before the specified deadline. Attention to detail is critical, as incomplete submissions can lead to disqualification.
    4. Attend Bid Opening: Engage in the . This provides valuable insights into the and the evaluation criteria used by the committee, allowing you to gauge your standing among other bidders.
    5. Follow Up: After submission, actively monitor the status of your bid. Be prepared to provide additional information or clarification if requested by the evaluation committee, as responsiveness can enhance your credibility.

    By diligently following these steps, you can significantly enhance your chances of obtaining a contract through the Mexico public tender process devices in the .

    Each box represents a crucial step in the bidding process. Follow the arrows to see how each step leads to the next, ensuring you don't miss any important actions.

    Understand Evaluation Criteria for Successful Bids

    In Mexico’s public tender process for medical devices, the evaluation of bids hinges on several critical criteria:

    1. : The primary factor is the quality and adherence of the proposed healthcare instruments to established regulatory standards. Submissions must clearly articulate how products align with these standards, as this is essential for gaining approval. The influence of improves by showcasing the effectiveness and safety of equipment, which is essential for fulfilling regulatory expectations.
    2. Cost: Although price plays a significant role, it is not the sole determinant. Bids are assessed based on the overall value they present, which includes quality, service, and long-term benefits.
    3. Experience and Track Record: A proven history of successful projects in the can significantly bolster a bidder’s credibility. Demonstrating relevant experience reassures evaluators of the bidder’s capability to deliver.
    4. : The Mexican government promotes local economic growth, frequently preferring proposals that include . This aligns with the national strategy to enhance domestic production capabilities. Notably, certain tenders may be limited to national participants if products have at least 50% national content. can strengthen bids by showcasing commitment to local economic growth.

    , reaching around US$800 billion by 2030. This growth is driven by increasing demand for , making it crucial for bidders to understand and leverage these effectively.

    Successful examples of bids based on include , which underscore the importance of compliance and innovation in securing contracts. By tailoring submissions to meet these evaluation standards, bidders can significantly enhance their chances of success in the Mexico public tender process devices within the competitive procurement landscape.

    The central node represents the overall evaluation criteria, while the branches show the key factors that influence bid success. Each sub-branch provides additional details about what evaluators look for in each criterion.

    Conclusion

    Navigating the Mexico public tender process for medical devices is not just a task; it’s a strategic imperative. With the evolving landscape shaped by recent reforms and regulatory changes, stakeholders must be well-equipped to thrive in this competitive environment. Understanding the nuances of compliance with updated laws and leveraging strategic insights can significantly enhance bidding success.

    Key aspects to consider include familiarizing oneself with various types of tenders – open tenders, restricted invitations, and direct awards – each requiring tailored strategies. Meeting eligibility criteria, such as registration in CompraNet and providing comprehensive technical documentation, is essential for participation. Moreover, adhering to a structured bidding process and grasping evaluation criteria – like technical merit, cost, and local content – can profoundly influence bid outcomes.

    As the healthcare device market in Mexico continues to expand, staying informed about the latest trends and regulations is increasingly vital. Actively engaging in the public tender process not only opens doors to lucrative opportunities but also fosters growth and innovation within the medical technology sector. Stakeholders are encouraged to embrace these insights and take proactive steps toward mastering the tender process, ensuring they remain competitive in this dynamic procurement landscape.

    Frequently Asked Questions

    What is the significance of understanding the Mexico public tender landscape for healthcare equipment?

    Understanding the Mexico public tender landscape is crucial for stakeholders as it helps them navigate the evolving procurement process, which has been transformed by recent government reforms aimed at enhancing transparency and efficiency.

    What recent changes have impacted the Mexico public tender process?

    Recent reforms have consolidated procurement processes under the Ministry of Health, emphasizing compliance with updated laws and regulations concerning public tender processes for healthcare devices.

    Who are the key players in the Mexico public tender process?

    Key players include the Ministry of Health and COFEPRIS, which play pivotal roles in influencing healthcare procurement in Mexico.

    How can stakeholders stay informed about upcoming tender opportunities?

    Stakeholders can stay informed by using CompraNet, the official government portal for public procurement, which provides vital information on upcoming opportunities.

    What are the different types of tenders available for medical devices in Mexico?

    The types of tenders available include: Open Tenders: Publicly announced bids open to any qualified supplier. Restricted Invitations: Bids that invite only selected suppliers based on pre-qualification criteria. Direct Awards: Contracts awarded without competitive bidding, typically in urgent situations. Yearly Bid: Aimed at supplying government healthcare institutions, including proposals for Drugs and Medical Devices. Small Tender: Organized by public health institutions when the Yearly Tender fails to meet supply needs.

    Why is it important to understand the classifications of tenders?

    Understanding the classifications of tenders is crucial for tailoring bidding strategies and enhancing the chances of success in the competitive landscape of healthcare procurement.

    What is the expected trend for open bids in the future?

    Open bids are expected to constitute a significant portion of the procurement environment by 2026, reflecting a commitment to transparency and competition.

    List of Sources

    1. Understand the Mexico Public Tender Landscape
      • fitchsolutions.com (https://fitchsolutions.com/bmi/region/mexico)
      • lexology.com (https://lexology.com/library/detail.aspx?g=141557d3-d54c-47d5-9ca5-101ada618138)
      • linkedin.com (https://linkedin.com/pulse/mexico-procurement-services-market-growth-outlook-ai-strategy-qsm7f)
      • state.gov (https://state.gov/reports/2025-investment-climate-statements/mexico)
    2. Identify the Types of Tenders Available
      • chameleon-pharma.com (https://chameleon-pharma.com/curious-about-the-pharma-tenders-procedure-in-mexico)
      • trade.gov (https://trade.gov/country-commercial-guides/mexico-selling-public-sector)
      • mexiconewsdaily.com (https://mexiconewsdaily.com/news/contracts-without-tenders-hit-record-numbers)
    3. Meet Eligibility Criteria and Requirements
      • openopps.com (https://openopps.com/blog/how-to-win-government-contracts-and-tenders-in-mexico)
      • chameleon-pharma.com (https://chameleon-pharma.com/curious-about-the-pharma-tenders-procedure-in-mexico)
      • trade.gov (https://trade.gov/country-commercial-guides/mexico-selling-public-sector)
      • veraqueconsulting.com (https://veraqueconsulting.com/mx/ultimate-guide-for-regulatory-affairs-in-mexico)
      • practiceguides.chambers.com (https://practiceguides.chambers.com/practice-guides/public-procurement-2025/mexico/trends-and-developments)
    4. Follow the Step-by-Step Bidding Process
      • openopps.com (https://openopps.com/blog/how-to-win-government-contracts-and-tenders-in-mexico)
      • indexbox.io (https://indexbox.io/blog/tenders-2026-02-21-procurement-research-brief)
      • linkedin.com (https://linkedin.com/posts/ilion-labs_how-to-navigate-public-tenders-in-mexico-activity-7383885018798026755-DPqQ)
      • indexbox.io (https://indexbox.io/blog/tenders-2026-02-11-tender-analytics-goods)
    5. Understand Evaluation Criteria for Successful Bids
      • statista.com (https://statista.com/outlook/hmo/medical-technology/medical-devices/mexico?srsltid=AfmBOoqxbKba-kvspyfw_NpErRthy95SRowBx51VVF9B_IkOlmhRl9oI)
      • ivemsa.com (https://ivemsa.com/medical-device-manufacturing-mexico-overview)
      • practiceguides.chambers.com (https://practiceguides.chambers.com/practice-guides/public-procurement-2025/mexico)
      • mexicobusiness.news (https://mexicobusiness.news/health/news/mexico-acquire-816-high-tech-medical-devices-2026)

  • Master Mexico Price Controls for Medical Devices: A Complete Guide

    Master Mexico Price Controls for Medical Devices: A Complete Guide

    Introduction

    Understanding the complexities of price controls in Mexico is crucial for anyone engaged in the medical device industry. These government-imposed guidelines are designed to balance affordability for consumers with profitability for manufacturers, ultimately shaping healthcare accessibility. As the Mexican government continues to refine its approach to these regulations, stakeholders are confronted with a pressing question: how can they effectively navigate the intricacies of compliance and market entry without stifling innovation? This guide explores the fundamentals of Mexico’s price controls for medical devices, providing insights into:

    1. Regulatory frameworks
    2. Market access strategies
    3. The broader implications for research and development

    Explore the Fundamentals of Price Controls in Mexico

    Price controls in Mexico serve as government-imposed guidelines that dictate the maximum prices for medical devices and pharmaceuticals. The implementation of is designed to ensure that healthcare products remain affordable and accessible to the population. Understanding these fundamentals is crucial for manufacturers, as they significantly impact , , and overall business operations, particularly in relation to .

    Types of Price Controls: Mexico employs various mechanisms, including , which limit the maximum allowable price based on international benchmarks. This approach helps maintain competitive pricing while ensuring that remain accessible under .

    Objectives: The primary goal is to make accessible to the public while balancing affordability for consumers with profitability for manufacturers. The establishment of the in 2008 has been pivotal in negotiating costs for patented medications, similar to how enhance the effectiveness of cost regulations.

    Recent Developments: The Mexican government has been actively revising its approach to , focusing on dialogue with industry stakeholders to refine strategies without imposing strict caps. Recent initiatives have aimed to reduce medicine costs, as and designates around 30% of its health budget for the acquisition of medicines, which is anticipated to improve access to essential products. Furthermore, the Coordinating Commission for Negotiating the Cost of Medicines and Other Inputs (CCNPM) reported savings of $355 million USD from 2008 to 2011, emphasizing the effectiveness of negotiations in Mexico.

    that while can enhance affordability, they may also result in unintended consequences, such as diminished innovation and supply shortages. As one economist stated, “Price regulations can create a paradox where the intention to make healthcare more affordable inadvertently stifles innovation.” The continuous conversation between the government and industry is essential for addressing these challenges and ensuring that effectively serve the public interest without hindering market growth. Legal precedents have also emerged requiring insurers to provide drugs not listed in formularies, illustrating the complexities in the healthcare system related to price controls.

    The center represents the main topic of price controls, with branches showing different aspects like types, goals, and recent changes. Each branch helps you understand how these elements connect to the overall theme.

    Understand the Regulatory Framework for Medical Device Pricing

    The regulatory framework in and is fundamentally shaped by the and enforced by COFEPRIS (Federal Commission for Protection against Sanitary Risk). This framework is crucial for ensuring that meet before they can enter the market.

    • Regulatory Oversight: COFEPRIS plays a pivotal role in the approval and pricing of . It ensures that all products comply with established , which is essential for protecting public health.

    Manufacturers must submit that align with the on . These guidelines often include reference pricing based on global market conditions. This process demands comprehensive documentation and justification for the proposed costs, ensuring .

    • : Adhering to is not just advisable; it is essential. Non-compliance can lead to significant delays in market access or even financial penalties. To navigate these complexities effectively, manufacturers should stay updated on and consider collaborating with local experts for guidance.

    The central node represents the overall regulatory framework, while the branches show key areas of focus. Each sub-branch provides more detail on specific aspects, helping you understand how they connect to the main topic.

    Successfully navigating access to the economy under the requires a strategic approach that is both informed and adaptable. Here are essential strategies to consider:

    • Market Research: Conduct to understand competitive pricing, consumer demand, and regulatory expectations. This data is vital for establishing a compliant and competitive price point. Notably, the Mexican is projected to reach approximately USD 8.41 billion by 2025, underscoring the importance of understanding industry dynamics, particularly in relation to , to guide effective .
    • Engagement with Stakeholders: Building strong relationships with is crucial. Proactive communication with entities like COFEPRIS can provide valuable insights into upcoming , facilitating a smoother navigation through the approval process.
    • Adjustment of : Develop flexible cost approaches that can adapt to potential regulatory changes or economic conditions. Implementing tiered pricing models or can enhance acceptance within the industry, aligning the interests of manufacturers and healthcare providers while ensuring patient access to innovative technologies.
    • Utilize Local Knowledge: Partner with regional advisors or CROs such as bioaccess® to effectively and expedite entry into the industry. bioaccess® offers a range of , including feasibility studies, site selection, compliance reviews, trial setup, import permits, project management, and reporting, ensuring a streamlined process for startups aiming for accelerated clinical study results.

    The central node represents the overall theme, while each branch highlights a key strategy. Follow the branches to explore specific actions and insights related to each strategy.

    Assess the Impact of Price Controls on Clinical Research and Development

    Mexico price controls on exert a profound influence on clinical within the medical device sector. Understanding this impact is crucial for stakeholders aiming to .

    • Funding Constraints: , directly impacting their capacity to invest in . This limitation frequently leads to a reduced number of innovations reaching consumers, as companies may prioritize existing products over new developments.
    • Development Timelines: . Manufacturers must navigate additional regulatory scrutiny, which can delay the introduction of new devices and prolong the time to market.
    • Market Dynamics: The implementation of can alter competitive dynamics within the industry. Reduced competition may stifle innovation, compelling manufacturers to adjust their R&D strategies to focus on cost-effective solutions that meet regulatory expectations rather than pioneering advancements.
    • Long-term Sustainability: It is crucial for manufacturers to grasp the of cost controls. is essential for ensuring ongoing innovation and market presence. Understanding these dynamics will enable companies to better navigate the challenges posed by Mexico price controls on while continuing to deliver valuable medical solutions.

    The central node represents the main topic, while the branches illustrate different impacts of price controls. Each branch can be explored for more detailed insights into how these factors affect the medical device sector.

    Conclusion

    Understanding the complexities of price controls for medical devices in Mexico is crucial for manufacturers and stakeholders aiming for success in this regulated market. These controls ensure that healthcare products remain affordable and accessible while balancing the interests of consumers and manufacturers. By effectively navigating pricing regulations, businesses can strategically position themselves for market entry and growth.

    This article has explored key aspects such as:

    1. The types of price controls
    2. The regulatory framework enforced by COFEPRIS
    3. The impact of these controls on clinical research and development

    Engaging with stakeholders, conducting thorough market research, and adapting cost strategies in response to regulatory changes are essential. These insights provide a comprehensive understanding of how to operate effectively within the constraints of Mexico’s price control system.

    As the medical device sector in Mexico evolves, it is imperative for manufacturers to stay proactive and informed. Embracing flexible strategies and fostering communication with regulatory bodies will facilitate compliance and enhance opportunities for innovation and market success. By prioritizing these approaches, stakeholders can contribute to a healthcare landscape that balances affordability with the ongoing advancement of medical technologies.

    Frequently Asked Questions

    What are price controls in Mexico?

    Price controls in Mexico are government-imposed guidelines that dictate the maximum prices for medical devices and pharmaceuticals, aimed at ensuring these products remain affordable and accessible to the population.

    What types of price controls are implemented in Mexico?

    Mexico employs various mechanisms for price controls, including price ceilings and reference pricing, which limit the maximum allowable price based on international benchmarks.

    What is the primary objective of price controls for medical devices in Mexico?

    The primary objective is to make essential medical products accessible to the public while balancing affordability for consumers with profitability for manufacturers.

    What role does the Committee for the Negotiation of Drug Costs (CNDP) play in Mexico?

    Established in 2008, the CNDP is pivotal in negotiating costs for patented medications, enhancing the effectiveness of cost regulations similar to those for medical devices.

    How has the Mexican government recently approached cost controls?

    The government has been revising its approach by focusing on dialogue with industry stakeholders to refine strategies without imposing strict price caps, while also aiming to reduce medicine costs.

    What budget allocation does Mexico designate for the acquisition of medicines?

    Mexico designates around 30% of its health budget for the acquisition of medicines, which is expected to improve access to essential products.

    What savings were reported by the Coordinating Commission for Negotiating the Cost of Medicines and Other Inputs (CCNPM)?

    The CCNPM reported savings of $355 million USD from 2008 to 2011, highlighting the effectiveness of negotiations in reducing costs.

    What are some unintended consequences of price controls noted by healthcare economists?

    While price controls can enhance affordability, they may also lead to diminished innovation and supply shortages in the healthcare sector.

    Why is continuous dialogue between the government and industry important?

    Continuous conversation is essential for addressing challenges related to price controls and ensuring they effectively serve the public interest without hindering market growth.

    What legal precedents have emerged regarding insurers and price controls in Mexico?

    Legal precedents have emerged requiring insurers to provide drugs not listed in formularies, illustrating the complexities of the healthcare system related to price controls.

    List of Sources

    1. Explore the Fundamentals of Price Controls in Mexico
      • lexology.com (https://lexology.com/library/detail.aspx?g=4ae967b9-e758-40f2-99c4-15df6bcd1e33)
      • tandfonline.com (https://tandfonline.com/doi/full/10.1080/23288604.2022.2084221)
      • emergobyul.com (https://emergobyul.com/resources/mexico-overview-medical-device-industry-and-healthcare-statistics)
    2. Understand the Regulatory Framework for Medical Device Pricing
      • veraqueconsulting.com (https://veraqueconsulting.com/mx/understanding-cofepris-fees-for-medical-device-registrations-in-mexico)
      • Medical Device Classification Under COFEPRIS: A Comprehensive Guide | bioaccess® (https://bioaccessla.com/blog/medical-device-classification-under-cofepris-a-comprehensive-guide)
      • 9 Key Class II Device Rules COFEPRIS for Successful Registration | bioaccess® (https://bioaccessla.com/blog/9-key-class-ii-device-rules-cofepris-for-successful-registration)
      • mddionline.com (https://mddionline.com/medical-device-regulations/mexico-s-shortened-regulatory-timetable-attracts-medical-device-manufacturers)
      • emergobyul.com (https://emergobyul.com/resources/mexico-overview-medical-device-industry-and-healthcare-statistics)
    3. Navigate Market Access Strategies Under Price Controls
      • definitivehc.com (https://definitivehc.com/blog/medtech-pricing-strategies)
      • emergobyul.com (https://emergobyul.com/resources/mexico-overview-medical-device-industry-and-healthcare-statistics)
      • Achieve Medical Device Market Access in Latin America: A Step-by-Step Guide | bioaccess® (https://bioaccessla.com/blog/achieve-medical-device-market-access-in-latin-america-a-step-by-step-guide)
      • grandviewresearch.com (https://grandviewresearch.com/horizon/outlook/smart-medical-devices-market/mexico)
      • expertmarketresearch.com (https://expertmarketresearch.com/reports/mexico-medical-devices-market)
    4. Assess the Impact of Price Controls on Clinical Research and Development
      • uschamber.com (https://uschamber.com/intellectual-property/impact-of-government-price-controls-on-patients)
      • pmc.ncbi.nlm.nih.gov (https://pmc.ncbi.nlm.nih.gov/articles/PMC7902591)
      • nber.org (https://nber.org/digest/may05/effect-price-controls-pharmaceutical-research)
      • itif.org (https://itif.org/publications/2023/07/17/hidden-toll-of-drug-price-controls-fewer-new-treatments-higher-medical-costs-for-world)
      • digitalcommons.ursinus.edu (https://digitalcommons.ursinus.edu/bus_econ_fac/5)

  • Navigate COFEPRIS: Your Mexico FDA Equivalent for Medical Devices

    Navigate COFEPRIS: Your Mexico FDA Equivalent for Medical Devices

    Introduction

    Navigating the complex landscape of medical device regulation in Mexico demands a thorough understanding of COFEPRIS, the country’s counterpart to the FDA. This regulatory body is crucial in ensuring the safety and efficacy of health-related products, making it imperative for manufacturers to become well-acquainted with its guidelines. As the market evolves, new reforms and compliance requirements present both opportunities and challenges for MedTech companies.

    How can manufacturers effectively navigate these complexities to ensure successful product launches and enhance patient access to innovative technologies?

    Understand COFEPRIS and Its Role in Medical Device Regulation

    The Federal Commission for the Protection against Sanitary Risks is recognized as the , overseeing the safety and effectiveness of , medications, and pharmaceuticals. Operating under the Ministry of Health, this regulatory agency enforces stringent safety standards that all medical devices must meet before entering the Mexican market. For manufacturers, grasping the is essential, as it delineates the necessary documentation, , and approval processes vital for .

    In January 2026, the agency introduced a reform allowing subsequent renewals for periods of up to ten years. This change underscores the importance of a proactive compliance strategy to navigate the complexities of the Mexican market effectively. Additionally, adherence to Article 376 is crucial for manufacturers to ensure compliance with local regulations. Bioaccess® specializes in facilitating this process, leveraging its expertise to help navigate the regulatory and efficiently meet ANMAT registration requirements.

    As the regulatory authority states, “The agency must approve your regulatory application before you can sell your healthcare product in Mexico, in accordance with the .” Understanding the not only simplifies market entry but also . This ultimately leads to successful approvals for and improved patient access to innovative technologies.

    Identify Medical Devices Regulated by COFEPRIS

    into three primary categories based on risk levels:

    1. Class I (low risk)
    2. Class II (moderate risk)
    3. Class III ()

    Understanding these classifications is essential for navigating the effectively. Each class comes with .

    , require minimal documentation and typically undergo a streamlined approval process, often completed within 30 days. In contrast, , which include syringes and infusion pumps, involve moderate risk and necessitate a more detailed submission, with an approval timeline of approximately 35 days.

    , are considered and demand extensive . This leads to a more stringent review process that can take up to 60 days. Grasping the categorization of your equipment is crucial for effectively .

    The center shows the main topic of medical device classification, with branches leading to each risk class. Each class has examples and requirements, helping you understand what is needed for regulatory compliance.

    Follow the COFEPRIS Medical Device Registration Process

    To successfully register a medical product with the health authority, follow these essential steps:

    1. Determine : Identify your device’s risk class, as this will dictate the you must meet.
    2. : Compile essential documents, including a technical dossier, , and proof of compliance with applicable standards. Precise translation of all documentation into Spanish is crucial for evaluation by the health authority. Additionally, ensure compliance with ANMAT requirements where applicable.
    3. Submit Application: File your application with the health regulatory authority, ensuring that all documents are complete and correctly formatted.
    4. : Pay the necessary registration charges, which differ by classification. For instance, Class II categories generally incur fees ranging from $3,000 to $8,000, while Class III categories can exceed $15,000.
    5. Await Review: , with a decision usually provided within 30 business days for low-risk items, due to the accelerated 30-day approval process. However, the complete approval process can take up to 30 months depending on the complexity of the item.
    6. Receive Registration: Upon approval, you will obtain a , which permits you to market your device in Mexico. It’s important to note that the Mexico FDA equivalent has a rejection rate of approximately 20% for applications, emphasizing the need for thorough preparation and compliance with all requirements. Furthermore, it is advised to initiate the approval process 12-18 months prior to your planned market entry to account for any unforeseen delays. For a comprehensive understanding, consider the as well.

    Each box represents a step in the registration journey. Follow the arrows to see how to move from one step to the next, ensuring you complete each task in order.

    Meet Key Compliance Requirements for COFEPRIS

    To comply with COFEPRIS regulations, manufacturers must adhere to several key requirements:

    1. : Implement a (QMS) that meets . This is essential for ensuring consistent quality in . ISO 13485 establishes a framework for effective quality management, enhancing compliance with regulatory requirements and fostering continuous improvement in processes.
    2. : Ensure that all product labeling complies with NOM-137-SSA1-2008, which mandates that . This is crucial for consumer safety and clarity, as proper labeling assists users in comprehending the product’s intended use and any associated risks.
    3. : Conduct a to demonstrate the safety and efficacy of the apparatus, particularly for higher-risk classifications. This evaluation must encompass a thorough examination of available clinical data, ensuring that the product meets the necessary safety standards before it can be marketed.
    4. : Create a strategy to track the performance of the product and notify the regulatory authority of any negative incidents. This ongoing monitoring is vital for maintaining product safety and efficacy after the device has been introduced to the market.
    5. Documentation Maintenance: Ensure all documentation is current and easily accessible for inspections or audits. Proper and facilitating a smooth regulatory process.

    In 2026, revisions to ISO 13485 compliance requirements will further align with regulatory standards, reflecting the changing landscape of healthcare product regulation in Mexico. Following these guidelines not only guarantees conformity but also boosts the trustworthiness and appeal of healthcare products in a competitive landscape.

    The central node represents the overall compliance requirements, while each branch shows a specific area of focus. Follow the branches to see the detailed actions needed for each compliance requirement.

    Utilize Mexico’s Abbreviated Regulatory Pathway for Faster Approvals

    has unveiled a streamlined approval process, enabling producers to register medical products based on prior endorsements from recognized regulatory bodies, similar to the . This initiative is crucial for enhancing in Mexico. To effectively navigate this pathway, follow these :

    1. Confirm Eligibility: Ensure your device mirrors one previously approved by a recognized authority, maintaining the same formulation, intended use, and manufacturing process.
    2. Prepare Simplified Documentation: Submit a concise application that references the existing approval, along with any additional required documentation, which may include translations and administrative formalities.
    3. Submit Application: File your application through the , typically resulting in a decision within a target review period of just .
    4. Monitor Progress: Keep track of your application status and be prepared to provide any additional information requested by COFEPRIS.

    This new pathway significantly reduces the , with estimates indicating a 70-80% decrease in the paperwork required for international healthcare product manufacturers. By leveraging existing approvals, manufacturers can expedite their entry into the Mexican market, ultimately improving access to essential medical devices through the for both patients and providers. Industry leaders emphasize that if the 30-day timeline is consistently upheld, it will represent a transformative shift in efficiency, facilitating quicker access to vital medical technologies. Furthermore, as part of bioaccess’s Global Trial Accelerators™, we offer critical and market access strategies that empower medtech startups to successfully .

    Each box represents a step in the approval process. Follow the arrows to see the order of actions needed to successfully register medical products in Mexico.

    Conclusion

    Understanding COFEPRIS and its role as Mexico’s counterpart to the FDA is essential for any manufacturer looking to introduce medical devices into this growing market. The agency’s stringent oversight guarantees that all health-related products adhere to rigorous safety and efficacy standards, fostering trust and credibility among consumers and healthcare providers alike.

    This article highlights crucial aspects of navigating COFEPRIS, including:

    • The classification of medical devices into risk categories
    • The comprehensive registration process
    • The compliance requirements that manufacturers must follow

    By outlining the necessary steps for successful registration and underscoring the significance of quality management and post-market monitoring, it becomes evident that thorough preparation is vital for securing approval and maintaining product integrity.

    In conclusion, engaging with COFEPRIS not only opens avenues to the Mexican market but also elevates the overall quality of healthcare products available to patients. Manufacturers are urged to take advantage of the newly introduced abbreviated regulatory pathway to expedite approvals, ultimately enhancing access to innovative medical technologies. By prioritizing compliance and grasping the regulatory landscape, stakeholders can contribute to a healthier future for all, ensuring that safe and effective medical devices reach those who need them.

    Frequently Asked Questions

    What is COFEPRIS and what is its role in medical device regulation?

    COFEPRIS, the Federal Commission for the Protection against Sanitary Risks, is Mexico’s equivalent of the FDA. It oversees the safety and effectiveness of health-related products, medications, and pharmaceuticals, enforcing stringent safety standards for medical devices before they enter the Mexican market.

    What should manufacturers understand about COFEPRIS?

    Manufacturers need to grasp the regulatory framework established by COFEPRIS, which includes necessary documentation, compliance requirements, and approval processes essential for successful product launches in Mexico.

    What recent reform did COFEPRIS introduce in January 2026?

    COFEPRIS introduced a reform allowing subsequent renewals of medical device approvals for periods of up to ten years, highlighting the importance of a proactive compliance strategy.

    How does Article 376 relate to manufacturers?

    Adherence to Article 376 is crucial for manufacturers to ensure compliance with local regulations set forth by COFEPRIS.

    What is the significance of understanding COFEPRIS for market entry?

    Understanding COFEPRIS simplifies market entry and enhances the credibility of producers, leading to successful approvals for health-related products and improved patient access to innovative technologies.

    How does COFEPRIS classify medical devices?

    COFEPRIS classifies medical devices into three categories based on risk levels: Class I (low risk), Class II (moderate risk), and Class III (high risk).

    What are the approval requirements for Class I medical devices?

    Class I devices, such as bandages and non-invasive diagnostic tools, require minimal documentation and typically undergo a streamlined approval process, often completed within 30 days.

    What is the approval process for Class II medical devices?

    Class II devices, including syringes and infusion pumps, involve moderate risk and necessitate a more detailed submission, with an approval timeline of approximately 35 days.

    What is required for Class III medical devices?

    Class III devices, such as cardiac pacemakers and artificial heart valves, are considered high risk and require extensive clinical data, leading to a more stringent review process that can take up to 60 days.

    Why is it important to understand the classification of medical devices?

    Grasping the categorization of medical devices is crucial for effectively navigating the registration and compliance landscape with COFEPRIS.

    List of Sources

    1. Understand COFEPRIS and Its Role in Medical Device Regulation
      • Master COFEPRIS Guidelines for Medical Devices Compliance | bioaccess® (https://bioaccessla.com/blog/master-cofepris-guidelines-for-medical-devices-compliance)
      • mddionline.com (https://mddionline.com/medical-device-regulations/mexico-s-shortened-regulatory-timetable-attracts-medical-device-manufacturers)
      • mexicobusiness.news (https://mexicobusiness.news/health/news/mexicos-cofepris-rolls-out-anti-counterfeit-plan)
      • medenvoyglobal.com (https://medenvoyglobal.com/blog/what-is-cofepris-for-medical-devices)
      • COFEPRIS Mexico Medical Device Regulations | Pure Global (https://pureglobal.com/markets/mexico/cofepris-medical-device-regulations)
    2. Identify Medical Devices Regulated by COFEPRIS
      • emergobyul.com (https://emergobyul.com/services/classification-medical-devices-mexico)
      • regdesk.co (https://regdesk.co/regulations-library/mexico)
      • emergobyul.com (https://emergobyul.com/services/cofepris-medical-device-and-ivd-registration-and-approval-mexico)
      • pureglobal.com (https://pureglobal.com/markets/mexico/cofepris-medical-device-and-ivd-classification)
    3. Follow the COFEPRIS Medical Device Registration Process
      • medenvoyglobal.com (https://medenvoyglobal.com/blog/do-i-need-cofepris-approval-to-sell-in-mexico)
      • artixio.com (https://artixio.com/post/case-study-ensuring-cofepris-regulatory-compliance-for-health-supplements-in-mexico)
      • chameleon-pharma.com (https://chameleon-pharma.com/cofepris-now-offers-drugs-and-medical-devices-registration-in-30-45-days-what-to-expect-from-the-new-digipris-platform)
      • artixio.com (https://artixio.com/post/mexico-cofepris-regulations-for-medical-device-registration)
      • linkedin.com (https://linkedin.com/posts/bennyarazy_medicaldevices-ivd-regulatoryupdates-activity-7429673864135118849-XqtI)
    4. Meet Key Compliance Requirements for COFEPRIS
      • ivemsa.com (https://ivemsa.com/medical-device-manufacturing-mexico-overview)
      • veraqueconsulting.com (https://veraqueconsulting.com/mx/clinical-evaluation-studies-for-medical-device-approval-in-mexico)
      • Get Quote Authorized Representative Mexico Devices: Steps to Compliance | bioaccess® (https://bioaccessla.com/blog/get-quote-authorized-representative-mexico-devices-steps-to-compliance)
      • artixio.com (https://artixio.com/blog/cofepris-compliance)
      • emergobyul.com (https://emergobyul.com/resources/mexico-overview-medical-device-industry-and-healthcare-statistics)
    5. Utilize Mexico’s Abbreviated Regulatory Pathway for Faster Approvals
      • pureglobal.com (https://pureglobal.com/news/mexico-cofepris-2025-abbreviated-pathway-for-medical-devices)
      • mddionline.com (https://mddionline.com/medical-device-regulations/mexico-s-shortened-regulatory-timetable-attracts-medical-device-manufacturers)
      • globalregulatorypartners.com (https://globalregulatorypartners.com/cofepris-introduces-abbreviated-regulatory-pathway-reliance-to-accelerate-health-product-approvals-in-mexico)
      • pureglobal.com (https://pureglobal.com/blog-posts/mexicos-abbreviated-regulatory-pathway-is-a-game-changer-for-medical-device-market-access)

  • How Clinical Trials Support Market Entry in Mexico: Key Strategies

    How Clinical Trials Support Market Entry in Mexico: Key Strategies

    Introduction

    Clinical trials are the cornerstone of the medical product approval process, especially in rapidly evolving markets such as Mexico, where regulatory frameworks are in flux. These studies not only validate the safety and efficacy of new medical innovations but also bolster their credibility among healthcare providers and patients. However, the complexities of clinical trials can present substantial challenges for companies seeking to penetrate this dynamic market.

    What strategies can organizations implement to harness the benefits of clinical trials and secure a successful market entry in Mexico?

    Explore the Role of Clinical Trials in Market Entry

    of new medical products, highlighting how . In Mexico, these evaluations not only aid in gathering essential information for compliance submissions but also enhance the product’s credibility among healthcare providers and potential patients. By conducting , companies can leverage the nation’s diverse patient population, resulting in faster recruitment and more comprehensive data collection. This process ultimately facilitates a smoother market entry by demonstrating how , ensuring that products are thoroughly tested and compliant with local regulations.

    Moreover, successful medical trials can significantly reduce the time to market, illustrating how by providing the necessary evidence to satisfy the requirements of authorities such as COFEPRIS (Federal Commission for Protection against Sanitary Risk). With bioaccess®‘s , , Pilot Studies, Pivotal Studies, and Post-Market Follow-Up Studies, companies can navigate the complexities of research more effectively. Achieving official approval is a critical milestone for any company seeking to understand how for new medical devices or pharmaceuticals. Bioaccess® is dedicated to expediting this process, ultimately contributing to economic growth and healthcare improvement in the region.

    This flowchart shows the journey of conducting clinical trials, starting from initial trials, moving through various study types, and culminating in market entry. Each box represents a critical stage in the process.

    Understand Mexico’s Regulatory Framework for Clinical Trials

    Mexico’s health research framework is primarily governed by the General Health Law and the Health Research Secondary Regulations, with COFEPRIS serving as the principal authority overseeing research activities in the health sector. Companies must submit comprehensive study protocols, informed consent forms, and other essential documentation for approval prior to initiating any .

    Recent regulatory updates have focused on streamlining the approval process, enhancing efficiency for sponsors. For instance, COFEPRIS has introduced reliance criteria that allow for the acceptance of data from international studies, thereby expediting the approval of local experiments.

    At bioaccess, we are dedicated to optimizing this process through our extensive . These include:

    • Feasibility assessments
    • Site selection
    • Setup
    • Import permits
    • Project oversight
    • Reporting

    Our are crucial for ensuring compliance across all aspects of a study, from participant recruitment to data management, significantly reducing the risk of . Leveraging our expertise, we assist Medtech, Biopharma, and Radiopharma startups in navigating these challenges and accelerating their research processes, which demonstrates how in Mexico.

    Each box represents a step in the regulatory process. Follow the arrows to see how the steps connect, and note the services offered to assist at each stage.

    Implement Effective Strategies for Conducting Clinical Trials in Mexico

    To conduct successful clinical trials in Mexico, organizations should adopt the following strategies:

    1. Leverage Local Expertise: Collaborating with is essential, as they possess a profound understanding of the regulatory landscape and patient demographics. Their expertise can significantly improve the execution of tests, ensuring compliance with local regulations and ethical standards, which is crucial for understanding how . Notably, , highlighting the efficiency of local partnerships and the potential for significant cost savings of $25K per patient with FDA-ready data.
    2. : Mexico’s rich demographic diversity offers a unique opportunity to recruit a wide range of participants. This diversity not only enhances the generalizability of study results but also fosters improved patient engagement, which is crucial for understanding how . Understanding the socioeconomic factors, such as the challenges posed by poverty and illiteracy, is vital for effective recruitment strategies.
    3. : Implementing efficient project management practices is vital for meeting timelines. Consistent communication with all parties involved, including regulatory organizations such as COFEPRIS, can assist in resolving any issues quickly, which is essential for understanding how . The recent Resolution published by , further enhancing operational efficiency.
    4. Training and compliance are critical, as they ensure that all team members are well-trained in and local regulations, which is vital for understanding how . This training is crucial for upholding compliance and ensuring the integrity of study information, which ultimately affects how and influences the credibility of the research results. As cultural factors influence patient participation, training should also encompass local customs and practices.
    5. is essential in through the incorporation of digital tools for information collection and monitoring, which can greatly enhance the precision of details. Electronic data capture systems enable real-time monitoring of study progress, enhancing overall efficiency and data integrity. can also assist in tackling the linguistic diversity present in Mexico, highlighting how by ensuring clear communication among all participants.
    6. Specialized Study Types: bioaccess® specializes in various types of studies, including Early-Feasibility Studies, , Pilot Studies, Pivotal Studies, and Post-Market Clinical Follow-Up Studies. This expertise enables customized methods that satisfy the particular requirements of each study, further increasing the chances of successful results.

    The center represents the main goal of effective clinical trials. Each branch shows a strategy, and the sub-branches give more details about how to implement it. Different colors help you easily distinguish between strategies.

    Once clinical studies are successfully completed and approval from authorities is secured, understanding how clinical trials support market entry in Mexico is the next crucial step for navigating and commercialization. Here are key considerations:

    1. : Ensure that all necessary approvals from COFEPRIS are secured. This encompasses not only the testing outcomes but also the marketing approval for the product. In Colombia, the National Food and Drug Surveillance Institute (INVIMA) plays a crucial role in this process, acting as a Level 4 health authority recognized by PAHO/WHO, overseeing medical device regulation and classification.
    2. : Develop a comprehensive market entry strategy that includes pricing, distribution channels, and promotional activities. Understanding the competitive landscape is crucial for positioning the product effectively. Utilizing the knowledge of experts such as Katherine Ruiz, who focuses on compliance matters for medical devices and in vitro diagnostics, can offer valuable insights into market dynamics.
    3. : Engage with healthcare professionals, payers, and patients early in the commercialization process. Building relationships with key stakeholders can facilitate smoother market entry and enhance product adoption. Bioaccess highlights the significance of in its trial management services, ensuring that all parties are informed and involved.
    4. : Implement a robust plan to monitor the product’s performance and safety in the real world. This is not only a compliance necessity but also vital for preserving trust with healthcare providers and patients. Ongoing monitoring aligns with bioaccess’s dedication to compliance excellence and innovation in clinical research.
    5. Continuous Compliance: Stay informed about policy changes and ensure ongoing adherence to COFEPRIS guidelines. This vigilance is necessary to avoid any disruptions in and to maintain the product’s market position. The expertise of bioaccess’s , led by Ana Criado, ensures that clients are well-prepared to navigate these complexities.

    Each box represents a step in the process you need to take after clinical trials. Follow the arrows to see how one step leads to the next, ensuring a smooth market entry for your product.

    Conclusion

    The role of clinical trials in supporting market entry in Mexico is pivotal; they not only ensure the safety and effectiveness of medical products but also enhance credibility among healthcare providers and potential patients. By leveraging Mexico’s diverse patient population and streamlining regulatory processes, companies can navigate the complexities of research and accelerate their path to market.

    This article highlights key strategies for conducting successful clinical trials in Mexico, including:

    1. Collaboration with local experts
    2. Diverse patient recruitment
    3. Implementation of efficient project management practices

    It emphasizes the importance of compliance with regulatory frameworks and the necessity of engaging stakeholders throughout the commercialization process. These insights collectively demonstrate how clinical trials facilitate a smoother market entry, ultimately contributing to economic growth and healthcare improvement in the region.

    In conclusion, organizations looking to enter the Mexican market must recognize the strategic importance of clinical trials as a foundational step. By adopting best practices and remaining vigilant in compliance, companies can position themselves for success in a competitive landscape. Embracing these strategies enhances the likelihood of regulatory approval and fosters trust and engagement within the healthcare community, ensuring that new medical products can make a meaningful impact on patient care.

    Frequently Asked Questions

    What is the role of clinical trials in market entry in Mexico?

    Clinical trials are essential for confirming the safety and effectiveness of new medical products, aiding in compliance submissions, and enhancing product credibility among healthcare providers and patients.

    How do clinical trials benefit companies looking to enter the Mexican market?

    By conducting clinical studies in Mexico, companies can utilize the diverse patient population for faster recruitment and more comprehensive data collection, facilitating smoother market entry.

    What regulatory body must companies satisfy for market entry in Mexico?

    Companies must provide necessary evidence to satisfy the requirements of COFEPRIS (Federal Commission for Protection against Sanitary Risk).

    How can successful medical trials impact the time to market for new products?

    Successful medical trials can significantly reduce the time to market by providing the necessary evidence required for regulatory approval.

    What types of studies does bioaccess® manage to support clinical trials?

    Bioaccess® manages Early-Feasibility Studies, First-In-Human Studies, Pilot Studies, Pivotal Studies, and Post-Market Follow-Up Studies.

    What is the overall goal of conducting clinical trials in Mexico?

    The overall goal is to achieve official approval for new medical devices or pharmaceuticals, contributing to economic growth and healthcare improvement in the region.

    List of Sources

    1. Implement Effective Strategies for Conducting Clinical Trials in Mexico
      • COFEPRIS Simplifies Authorization of Clinical Trials in Mexico – Opportunity for International Investment | Pérez-Llorca, Law Firm (https://perezllorca.com/en-mx/news/legal-briefing/cofepris-simplifies-authorization-of-clinical-trials-in-mexico-opportunity-for-international-investment)
      • linkedin.com (https://linkedin.com/posts/cohortias_big-news-for-clinical-research-in-mexico-activity-7310064680805257216-BoJ2)
      • languageconnections.com (https://languageconnections.com/clinical-trials-in-mexico-addressing-the-challenges)
      • pmlive.com (https://pmlive.com/intelligence/clinical_trial_regulation_in_mexico_477081)
      • qualtrics.com (https://qualtrics.com/blog/research-quotes)

  • Navigate COFEPRIS: Your Guide to the FDA Equivalent in Mexico

    Navigate COFEPRIS: Your Guide to the FDA Equivalent in Mexico

    Introduction

    Navigating the complex landscape of medical device regulation in Mexico demands a thorough understanding of COFEPRIS, the country’s counterpart to the FDA. This regulatory authority is crucial in ensuring the safety and efficacy of medical products. For manufacturers looking to penetrate the Mexican market, grasping COFEPRIS’s processes and requirements is essential. Recent updates have streamlined the approval pathways, raising an important question: how can producers effectively leverage these changes to expedite their market entry while ensuring compliance with rigorous safety standards?

    Explore COFEPRIS: Mexico’s Regulatory Authority for Medical Devices

    The Federal Commission for Protection against Sanitary Risks serves as Mexico’s primary regulatory authority, dedicated to . Established under the Ministry of Health, this agency serves as the , focusing on public health safety through the , pharmaceuticals, and other health products. In 2025, the agency granted 292 authorizations for medicines, medical instruments, and , underscoring its commitment to and fostering innovation.

    For producers looking to enter the Mexican market, understanding the agency’s is crucial. Compliance with its rigorous safety standards is not just recommended; it’s mandatory for legal sales. The agency insists that all authorizations stem from thorough technical processes rooted in scientific evaluation and risk analysis. This unwavering commitment to safety and quality is essential for manufacturers navigating the complexities of the Mexican healthcare landscape.

    Recent updates to health authority regulations have streamlined the approval process, positioning Mexico as a prime launch site for high-value medical products. The introduction of a , leveraging existing approvals from the U.S., U.K., and EU, aims to significantly alleviate regulatory burdens and enhance entry efficiency. By recognizing assessments from reputable global regulatory bodies, the agency allows foreign producers to expedite their entry into the Mexican economy, making it an attractive destination for cutting-edge medical technologies that are considered .

    bioaccess® excels in throughout Latin America, offering vital insights and support for . With expertise in securing swift approvals and access strategies, bioaccess® accelerates and regulatory processes, ensuring that innovative medical technologies reach consumers efficiently.

    Start at the center with COFEPRIS, then explore each branch to understand its purpose, regulatory requirements, recent changes, and how bioaccess® can help navigate these processes.

    Identify Medical Devices Regulated by COFEPRIS

    :

    1. I (low risk)
    2. II (moderate risk)
    3. III (high risk)

    , such as bandages and non-invasive tools, typically require minimal regulatory oversight, making their market introduction straightforward. In contrast, , which include diagnostic tools, undergo a more rigorous evaluation process to ensure safety and effectiveness. Class III devices, encompassing implants and life-supporting equipment, face the most stringent scrutiny due to their significant impact on patient health.

    , reflecting a commitment to align with international standards. For example, the updated classification rules now feature ten distinct criteria for in vitro diagnostics (IVDs), an increase from the previous four. This change highlights the critical nature of precise categorization in the , especially for looking to navigate the market with the support of Global Trial Accelerators™.

    As of 2025, COFEPRIS has registered a substantial number of medical instruments across these categories, with Category I items leading the count, followed by Category II and Category III items. Authorized Category I instruments include basic surgical tools, while often feature more complex diagnostic equipment. , such as pacemakers and orthopedic implants, necessitate extensive clinical data to validate their safety and effectiveness.

    Understanding these classifications is vital for manufacturers aiming to effectively and ensure compliance with COFEPRIS regulations. As regulatory specialists emphasize, “Navigating the intricacies of classification is essential for successful entry into Mexico.” This insight underscores the need for thorough preparation and comprehension of the regulatory landscape. Here, bioaccess can assist startups in leveraging and market access strategies to enhance their chances of success.

    The central node represents the overall classification system, while the branches show the different risk categories. Each sub-branch provides examples of devices within those categories, helping you understand the regulatory requirements associated with each type.

    Registering a with the health authority is a crucial process that involves several key steps:

    1. Determine Classification: First, identify whether the apparatus falls under Class I, II, or III. This classification significantly impacts the and timelines.
    2. : Next, compile essential documents, including technical specifications, , and labeling information. Ensure these documents are well-structured and up-to-date to facilitate a smoother approval process.
    3. : After preparing the documentation, file the application through the relevant online platform. It’s vital to ensure all documents are complete and translated into Spanish.
    4. : Pay the relevant registration charges, which vary depending on the classification of the equipment.
    5. Await Review: COFEPRIS will assess the application, with . , potentially reducing review times significantly.
    6. Receive Approval: Upon authorization, the item will be assigned a , allowing it to be marketed in Mexico. Notably, approximately 70% to 80% of the necessary work for approval can be fulfilled by previous assessments from reliable international regulators. This can accelerate the process for producers with existing endorsements from the FDA, Health Canada, or the FDA equivalent in Mexico.

    Each box represents a step in the registration journey - follow the arrows to see how to navigate through the process from classification to receiving approval.

    Understand Key Compliance Requirements for COFEPRIS

    Compliance with COFEPRIS regulations entails several essential requirements:

    1. : Manufacturers must establish a QMS that adheres to ISO 13485 standards. This ensures consistent quality in medical product production, which is crucial for maintaining compliance and enhancing market reputation.
    2. : For Class II and III instruments, providing robust that demonstrates both safety and efficacy is essential. This requirement is vital for gaining approval and ensuring patient safety.
    3. : All medical products must feature labels in Spanish, including comprehensive instructions for use and safety information. This ensures clarity and compliance with local regulations.
    4. : Manufacturers are obligated to conduct ongoing monitoring of their products post-approval. This includes notifying the regulatory authority of any negative occurrences, which is crucial for upholding compliance and guaranteeing the safety of medical products available.
    5. : Medical equipment registrations are valid for five years and must be renewed to maintain access to the marketplace. This process requires manufacturers to stay updated on and maintain compliance throughout the product lifecycle.

    Start at the center with COFEPRIS compliance, then explore each branch to see the essential requirements and their specific details.

    Leverage Mexico’s Abbreviated Regulatory Pathway for Faster Market Access

    Effective September 1, 2025, COFEPRIS has introduced an abbreviated that allows manufacturers to register based on prior approvals from recognized authorities like the FDA or the FDA equivalent in Mexico. This , with approvals expected within for qualifying items.

    To leverage this pathway, manufacturers must:

    1. Confirm Eligibility: Ensure that their equipment has received prior approval from a recognized authority.
    2. Prepare a Simplified Dossier: Submit a that references the existing approval, minimizing redundant documentation.
    3. Engage a Local Representative: Appoint a (MRH) to facilitate the submission process and ensure compliance with local regulations.

    Moreover, producers should be aware of the , which are crucial for adherence in the Mexican sector. As noted by Giulia Guerreschi, a regulatory affairs specialist at Pure Global, “approximately 70% to 80% of the requisite work is already satisfied, with only limited supplementary requirements, such as translations and administrative formalities, remaining to achieve compliance with Mexico’s national law.”

    By utilizing this expedited route, manufacturers can gain , significantly enhancing their competitive edge and aligning with COFEPRIS’s goal of streamlining and expediting the registration process for medicines and medical devices. Furthermore, subscribing to bioaccess’s Global Trial Accelerators™ can provide essential and , helping medtech startups navigate the complexities of the Latin American regulatory landscape effectively.

    Each box represents a step in the process to gain faster market access in Mexico. Follow the arrows to see how each step leads to the next, ultimately helping manufacturers navigate the regulatory landscape.

    Conclusion

    Understanding COFEPRIS is crucial for anyone aiming to navigate the medical device landscape in Mexico. As the country’s counterpart to the FDA, COFEPRIS plays a vital role in ensuring that medical products are safe, effective, and compliant with stringent health standards. The agency’s dedication to public health not only enhances access to innovative medical technologies but also cultivates a thriving environment for manufacturers looking to enter the Mexican market.

    This guide has outlined key aspects of COFEPRIS’s regulatory framework, including:

    1. The classification of medical devices
    2. The registration process
    3. Compliance requirements

    The introduction of an abbreviated regulatory pathway highlights Mexico’s commitment to streamlining market entry for foreign producers, enabling quicker approvals based on existing assessments from recognized international bodies. These developments emphasize the necessity of understanding the regulatory landscape to ensure successful product launches.

    As the medical technology sector evolves, leveraging resources like bioaccess® can provide invaluable support in navigating COFEPRIS’s complex regulations. Manufacturers are urged to stay informed about updates and utilize expedited pathways for faster market access. By doing so, they not only enhance their competitive advantage but also contribute to improving healthcare outcomes in Mexico.

    Frequently Asked Questions

    What is COFEPRIS and what role does it play in Mexico?

    COFEPRIS, or the Federal Commission for Protection against Sanitary Risks, is Mexico’s primary regulatory authority responsible for ensuring the safety and effectiveness of medical instruments, pharmaceuticals, and other health products. It serves a role similar to the FDA in the United States.

    How many authorizations did COFEPRIS grant in 2025?

    In 2025, COFEPRIS granted 292 authorizations for medicines, medical instruments, and clinical trials.

    What is required for producers looking to enter the Mexican market?

    Producers must understand COFEPRIS’s regulatory framework and comply with its rigorous safety standards, which are mandatory for legal sales in Mexico.

    What updates have been made to COFEPRIS regulations?

    Recent updates have streamlined the approval process, including a new 30-day approval pathway for medical devices that recognizes existing approvals from the U.S., U.K., and EU, thus alleviating regulatory burdens for foreign producers.

    How does COFEPRIS categorize medical devices?

    COFEPRIS categorizes medical devices into three groups based on risk: Category I (low risk), Category II (moderate risk), and Category III (high risk).

    What types of products fall under each category?

    Category I includes low-risk items like bandages and non-invasive tools. Category II includes moderate-risk items such as diagnostic tools, while Category III encompasses high-risk devices like implants and life-supporting equipment.

    What recent changes have been made to the classification rules?

    The updated classification rules have broadened definitions and requirements, including an increase in criteria for in vitro diagnostics (IVDs) from four to ten, aligning with international standards.

    Why is understanding these classifications important for manufacturers?

    Understanding COFEPRIS classifications is crucial for manufacturers to navigate the registration process effectively and ensure compliance with regulatory requirements, which is essential for successful market entry.

    How can bioaccess® assist companies in navigating COFEPRIS regulations?

    Bioaccess® offers insights and support for MedTech and Biopharma companies, helping them secure swift approvals and access strategies to accelerate clinical trials and regulatory processes in Latin America.

    List of Sources

    1. Explore COFEPRIS: Mexico’s Regulatory Authority for Medical Devices
      • Master COFEPRIS Guidelines for Medical Devices Compliance | bioaccess® (https://bioaccessla.com/blog/master-cofepris-guidelines-for-medical-devices-compliance)
      • mddionline.com (https://mddionline.com/medical-device-regulations/mexico-s-shortened-regulatory-timetable-attracts-medical-device-manufacturers)
      • medenvoyglobal.com (https://medenvoyglobal.com/blog/what-is-cofepris-for-medical-devices)
      • chameleon-pharma.com (https://chameleon-pharma.com/cofepris-now-offers-drugs-and-medical-devices-registration-in-30-45-days-what-to-expect-from-the-new-digipris-platform)
      • linkedin.com (https://linkedin.com/pulse/cofepris-grants-292-health-authorizations-expands-availability-4mqqc)
    2. Identify Medical Devices Regulated by COFEPRIS
      • regdesk.co (https://regdesk.co/regulations-library/mexico)
      • medenvoyglobal.com (https://medenvoyglobal.com/blog/what-is-cofepris-for-medical-devices)
      • pureglobal.com (https://pureglobal.com/markets/mexico/cofepris-medical-device-and-ivd-classification)
    3. Navigate the COFEPRIS Medical Device Registration Process
      • chameleon-pharma.com (https://chameleon-pharma.com/cofepris-now-offers-drugs-and-medical-devices-registration-in-30-45-days-what-to-expect-from-the-new-digipris-platform)
      • omcmedical.com (https://omcmedical.com/mexico-medical-device-registration)
      • mddionline.com (https://mddionline.com/medical-device-regulations/mexico-s-shortened-regulatory-timetable-attracts-medical-device-manufacturers)
      • insights.tetakawi.com (https://insights.tetakawi.com/cofepris-medical-device-registration-mexico)
      • emergobyul.com (https://emergobyul.com/services/cofepris-medical-device-and-ivd-registration-and-approval-mexico)
    4. Understand Key Compliance Requirements for COFEPRIS
      • bioaccessla.com (https://bioaccessla.com/es/blog/achieve-cofepris-medical-device-approval-in-4-simple-steps)
      • Master COFEPRIS Guidelines for Medical Devices Compliance | bioaccess® (https://bioaccessla.com/blog/master-cofepris-guidelines-for-medical-devices-compliance)
      • mexicobusiness.news (https://mexicobusiness.news/health/news/quality-management-systems-are-key-develop-medical-devices)
      • artixio.com (https://artixio.com/blog/cofepris-compliance)
      • emergobyul.com (https://emergobyul.com/resources/mexico-overview-medical-device-industry-and-healthcare-statistics)
    5. Leverage Mexico’s Abbreviated Regulatory Pathway for Faster Market Access
      • globalregulatorypartners.com (https://globalregulatorypartners.com/cofepris-introduces-abbreviated-regulatory-pathway-reliance-to-accelerate-health-product-approvals-in-mexico)
      • pureglobal.com (https://pureglobal.com/blog-posts/mexicos-abbreviated-regulatory-pathway-is-a-game-changer-for-medical-device-market-access)
      • mddionline.com (https://mddionline.com/medical-device-regulations/mexico-s-shortened-regulatory-timetable-attracts-medical-device-manufacturers)
      • linkedin.com (https://linkedin.com/pulse/breaking-news-medical-device-manufacturers-lukne)