Tag: colombia

  • Which LATAM countries mandate post-trial access for medical devices?

    Four Latin American jurisdictions textually mandate post-trial access (PTA) for medical devices: Costa Rica (Ley 9234 Art. 53(k)), Brazil (Lei 14.874/2024 Art. 37), Chile (Código Sanitario Art. 111 A → 111 C), and Peru (DS 021-2017-SA Art. 2.1.36). Ecuador’s AM 00069-2024 does not. Argentina’s Disp. 12792/2016 is inferential.

    Most LATAM PTA statutes were drafted for medicines. Device sponsors who assume drug rules apply without reading product-class language understate exposure in four countries and overstate it in others.

    Short answer: which countries mandate device PTA?

    Express textual reach (4): Costa Rica, Brazil, Chile, Peru.

    Inferential / confirm-with-regulator: Argentina (productos y materiales; no dispositivo médico); Panama (Art. 68 “el producto” — confirm import pathway with DNFD).

    Medicines-only among binding PTA countries: Ecuador.

    Ten-country PTA mandate list: Argentina, Brazil, Panama, Chile, Peru, Ecuador, Costa Rica, Guatemala, Honduras, and Nicaragua (LATAM PTA operator map).

    Colombia disclaimer: Colombia does not currently mandate post-trial access by statute. When post-trial supply is required, bioaccess® can operate voluntary continuity programs on sponsor request. PTA statutory mandates in LATAM currently apply to Argentina, Brazil, Panama, Chile, Peru, Ecuador, Costa Rica, Guatemala, Honduras, and Nicaragua.

    Which jurisdictions expressly cover medical devices?

    Costa Rica — strongest express device language. Ley 9234 Art. 53(k) obliges free post-study provision of “el medicamento, dispositivo o procedimiento que ha sido objeto de investigación,” with enumerated exits. Art. 28 sets duration at “mientras lo requieran.” No other LATAM PTA instrument states device and procedure coverage this plainly (Map hub).

    Brazil — Chapter VI extends to devices and ATMPs. Lei 14.874/2024 Art. 37 applies the post-trial chapter to “produtos e dispositivos médicos” and experimental advanced therapies “no que couber.” Decreto 12.651/2025 Art. 31 speaks of produto sob investigação. Full analysis: Brazil PTA pillar.

    Chile — Art. 111 A pulls devices into Art. 111 C. Código Sanitario Art. 111 A requires the provisional-use authorization for “todo producto farmacéutico o dispositivo médico.” Art. 111 C then binds that authorization holder — and later the sanitary-registration holder — to free continuity “por todo el tiempo que persista su utilidad terapéutica” (Chile PTA pillar). ISP’s April 2026 device GCP guide (Res. Ex. N° 341 / 2.050) cites Art. 111 A but is silent on Art. 111 C; guidance silence does not erase the statute.

    Peru — definitional inclusion. DS 021-2017-SA Art. 2.1.36 defines producto en investigación as “un producto farmacéutico o dispositivo médico.” Título X (Arts. 115–118) operates on that term with no device carve-out (Peru PTA pillar).

    Which mandate countries are silent, inferential, or medicines-only?

    Ecuador — medicines-only. AM 00069-2024 Arts. 80–81 create a sponsor free-supply duty inside a medicines / natural-medicinal-products reglamento. Device exposure there runs through ethics-committee expectations and informed consent, not those articles (Map hub).

    Argentina — inferential. Disp. 12792/2016 Art. 3(f) covers products and “los materiales” that must match the approved study. Dispositivo médico does not appear. Confirm with ANMAT before assuming the cohort import route applies (Argentina PTA pillar).

    Panama — product language; confirm pathway. Decreto Ejecutivo 21/2026 Art. 68 refers to “el producto”; Chapter XIII covers medicines and other products for human health. Device studies fit a fair reading, but sponsors should confirm the import-permit-extension pathway with DNFD. Primary-source verification required for any device-class DNFD circular not already cited on the Panama pillar.

    Guatemala, Honduras, and Nicaragua sit in the ten-country PTA mandate set (Map hub); device-specific textual reach is thinner than the four express jurisdictions and should be verified before protocol lock. Guatemala AM 82-2019 vs AM 206-2021 supersession status remains primary-source verification required.

    What operational gaps remain after a device duty attaches?

    Obligation is not pathway. Costa Rica Art. 53(k) mandates free device provision, but Art. 55 addresses importation only before an approved study begins — no post-trial import route is identified in the statute (Map hub). Brazil Art. 37 is clear, yet RDC 38/2013 speaks of medicamento; build post-close import from the trial’s own authorizations (Brazil pillar).

    Chile’s open-ended “utilidad terapéutica” raises replacement, consumable, explant, and end-of-life questions the statute does not answer — close them in the protocol (Chile pillar). Peru’s duty can mean continued consumables or support for an implanted system with no device-specific carve-out (Peru pillar).

    Before first site activation: classify each country as express / inferential / medicines-only / no PTA statute; quote the device-scope article; name the post-close import mechanism or document that none exists; define device-system continuity in the protocol; appoint an importer of record after trial authorizations lapse.

    Working on a LATAM device PTA program? bioaccess® is a US-headquartered, LATAM-native operator for regulatory, importadora, and 2–8 °C GDP cold-chain functions. Contact Julio Martinez-Clark, Co-Founder & CEO, at jmclark@bioaccessla.com or +1 (954) 903-7210. More at bioaccessla.com/roadmap.

    Related pillar

    For the full 20-country mandate matrix, cost allocation, and duration comparative — including the ten binding-statute countries and Colombia’s no-PTA framing — read Post-trial access in Latin America: the operator’s map.

    Sources

    • Costa Rica — Ley N.º 9234 (Arts. 28, 53(k), 55): https://documentos.una.ac.cr/bitstream/handle/unadocs/5670/Texto%20Completo%20Norma%209234.pdf?sequence=1&isAllowed=y
    • Brazil — Lei nº 14.874/2024 Art. 37: https://www.planalto.gov.br/ccivil_03/_ato2023-2026/2024/lei/l14874.htm
    • Brazil — Decreto nº 12.651/2025 Art. 31: https://www2.camara.leg.br/legin/fed/decret/2025/decreto-12651-7-outubro-2025-798105-publicacaooriginal-176652-pe.html
    • Brazil — ANVISA RDC nº 38/2013: https://anvisalegis.datalegis.net/action/ActionDatalegis.php?acao=abrirTextoAto&tipo=RDC&numeroAto=00000038&seqAto=000&valorAno=2013&orgao=RDC/DC/ANVISA/MS&codTipo=&desItem=&desItemFim=&cod_menu=1696&cod_modulo=134&pesquisa=true
    • Chile — Código Sanitario Arts. 111 A, 111 C: https://www.bcn.cl/leychile/navegar?idNorma=5595
    • Chile — Ley 20.850: https://www.bcn.cl/leychile/navegar?idNorma=1078148
    • Chile — ISP Res. Ex. N° 341 / Res. Ex. 2.050: https://www.bcn.cl/leychile/navegar?idNorma=1223885
    • Peru — DS 021-2017-SA Arts. 2.1.36, 115–118: https://ensayosclinicos-repec.ins.gob.pe/images/Reglamento_de_EC.pdf
    • Ecuador — AM 00069-2024 Arts. 80–81, 95(c): https://www.espoch.edu.ec/wp-content/uploads/2025/10/ac-00069-2024_dic_31_compressed_1-1.pdf
    • Argentina — ANMAT Disposición 12792/2016 Art. 3(f): https://www.boletinoficial.gob.ar/detalleAviso/primera/154162/20161117
    • Colombia — Resolución 2378 de 2008: https://www.ins.gov.co/Normatividad/Resoluciones/RESOLUCION%202378%20DE%202008.pdf
    • LATAM PTA Operator Map: https://bioaccessla.com/blog/latam-post-trial-access-operator-map
    • Brazil PTA pillar: https://bioaccessla.com/blog/brazil-post-trial-access-lei-14874
    • Chile PTA pillar: https://bioaccessla.com/blog/chile-post-trial-access-ley-20850
    • Peru PTA pillar: https://bioaccessla.com/blog/peru-post-trial-access-ds-021-2017-sa
    • Argentina PTA pillar: https://bioaccessla.com/blog/argentina-post-trial-access-anmat-disposicion-12792
    • Panama PTA pillar: https://bioaccessla.com/blog/panama-post-trial-access-decreto-ejecutivo-21-2026

  • Clinical trial execution in Colombia: why we recommend it now

    Colombia is now in scope for bioaccess® clinical-trial execution across all phases — first-in-human through pivotal — for both medical devices and drugs, in every indication. That is a reversal of our prior position, and the reason is that the regulator changed faster than the market narrative about it did.

    INVIMA is one of eight national authorities certified by PAHO as a Regional Reference Regulatory Authority at Level IV, the highest level PAHO assigns for medicines regulation and surveillance in the Americas (INVIMA, Cooperación internacional; PAHO, Autoridades Regulatorias de Referencia). Since 2022 it has built a dedicated clinical-research group for devices, published its own approval and non-approval registries, and opened a public study search. Sponsors are still pricing Colombia on 2018 assumptions.

    What changed since 2022

    Three institutional facts, all documented by INVIMA itself.

    First, devices got their own clinical-research function: INVIMA created the Grupo de Investigación Clínica y Apoyo a Sala Especializada DMRDIV (GICASE) through Resolución 2022035262 of 20 September 2022 (INVIMA, Investigación Clínica — Dispositivos). Second, the Sala Especializada de Dispositivos Médicos y Reactivos de Diagnóstico In Vitro (SEDMRDIV) now has an explicit mandate to evaluate and issue technical and methodological opinions on research protocols involving devices and in vitro diagnostic reagents (INVIMA, Sala especializada DMRDIV). Device sponsors have a named technical body, not an improvised one.

    Third, INVIMA publishes what it approves and what it refuses: a register of device clinical studies approved from 2021 onward, a parallel register of studies not approved with the reason for each — non-approval, withdrawal, pending response — and a register of ethics-committee and research-site inspection status to November 2025 (INVIMA, Investigación Clínica — Dispositivos; register of non-approved device studies). Very few regulators in the region publish their rejections, and that register shows which protocol defects cost applicants a cycle. INVIMA’s public study search lists 1,157 clinical studies, 1,156 of them approved, 487 in progress and 523 completed, with a data date of 12 August 2026 (INVIMA, Lista de Estudios Clínicos).

    The device pathway: prototype authorization through pivotal

    Colombia has no single device clinical-trial regulation. It has three working instruments, and knowing which one carries which obligation is most of the job.

    Decreto 4725 de 2005 is the sanitary regime for human-use medical devices. Article 2 defines a device intended for clinical investigation as one used by a specialist physician in research in an appropriate human clinical setting. Article 36 provides that a national or imported prototype device — or controlled-technology biomedical equipment — may be authorized only for research and experimentation, may not be used in health care, and requires an INVIMA technical opinion. Article 48(b) is the import hook: exceptional importation without sanitary registration or commercialization permit where the device is the subject of clinical research authorized in Colombia, subject to a prior opinion from the relevant specialized chamber. Article 18(k) closes the loop commercially — class IIb and III devices must present clinical studies to demonstrate safety and effectiveness when they later seek Registro Sanitario (Decreto 4725 de 2005).

    Resolución 8430 de 1993 supplies the human-subjects framework — the scientific, technical and administrative rules for health research, including new prophylactic, diagnostic, therapeutic and rehabilitative resources (MinSalud) — and INVIMA names it as the governing instrument for research with human beings.

    The operative paperwork is form-driven and published: ASS-RSA-FM085 (checklist for the prototype-device technical-opinion request), ASS-RSA-FM172 (SEDMRDIV technical-opinion request), ASS-RSA-FM169 (initial study evaluation completed by the ethics committee), ASS-RSA-FM170 (periodic reports) and ASS-RSA-FM171 (serious adverse event notification) (INVIMA, Investigación Clínica — Dispositivos). There is no ambiguity about what to file. There is considerable skill in filing it in a form the SEDMRDIV will not bounce.

    The drug pathway

    For medicines the anchor is Resolución 2378 de 2008, which adopted Good Clinical Practices with mandatory application for institutions conducting research with medicines in human beings (INS, Resolución 2378 de 2008). INVIMA requires approval for Phase I, II and III protocols and for Phase IV protocols with intervention; non-interventional Phase IV studies must still be submitted with a summary so INVIMA can determine whether formal approval applies (INVIMA, Fiscalización de Ensayos Clínicos).

    Initial protocol evaluation is filed through Protocolos en Línea, the exclusive route for that procedure since 2 January 2020, under tariff 4070 for protocols and 4083 for amendments; adverse-event content and periodicity are set by Resolución 2011020764 de 2011, issued under Article 146 of Decreto 677 de 1995 (INVIMA, Fiscalización de Ensayos Clínicos).

    Import of unregistered investigational medicines runs through Article 96 of Decreto 677 de 1995, which lets INVIMA exceptionally authorize importation without sanitary registration where INVIMA or the Ministry has authorized clinical research in the country, following a Comisión Revisora opinion and against a free-sale certificate, corporate documentation and analysis-fee receipts (Decreto 677 de 1995). Where the investigational product is a controlled substance, the monopoly is administered by the Fondo Nacional de Estupefacientes, and INVIMA expressly prioritizes those files in its current contingency plan (Resolución 2025046281 de 2025). Sponsors sometimes look for a separate narcotics department in the trial pathway; the correct counterparty is the FNE, and only for controlled product.

    Timelines, and what the misconception gets wrong

    The complaint about Colombia is that it is slow and unpredictable. Half of that is true.

    Protocol volume has been flat for a decade — roughly 90 protocol-evaluation requests a year, 85 in 2014 and 87 in 2024 — and INVIMA’s average time to a definitive concept, approving or rejecting, is 5.1 months (ConsultorSalud, June 2025). Five months to a decision is not fast. It is a measured average with a published rejection register behind it, which makes it forecastable — unpredictability is the charge that does not survive contact with the data.

    Country Published regulatory clock for trial authorization Source
    Colombia No statutory day-count; measured 5.1-month average to a definitive INVIMA concept ConsultorSalud
    Argentina Disposición ANMAT 7516/2025 Art. 5 assigns evaluation to the Dirección de Investigación Clínica, states no day-count Boletín Oficial
    Chile ISP: 45 business days to authorize import of unregistered pharmaceutical products for trial use ISP Chile
    Panama Decreto Ejecutivo 21 de 2026 regulates Títulos III–IV of Ley 84 de 2019; no day-count published MINSA Panamá

    Three of the four comparators publish no binding clock at all. Colombia’s disadvantage on early-phase device work is smaller than the reputation suggests, and Colombia is the only one of the four that publishes both its approvals and its refusals.

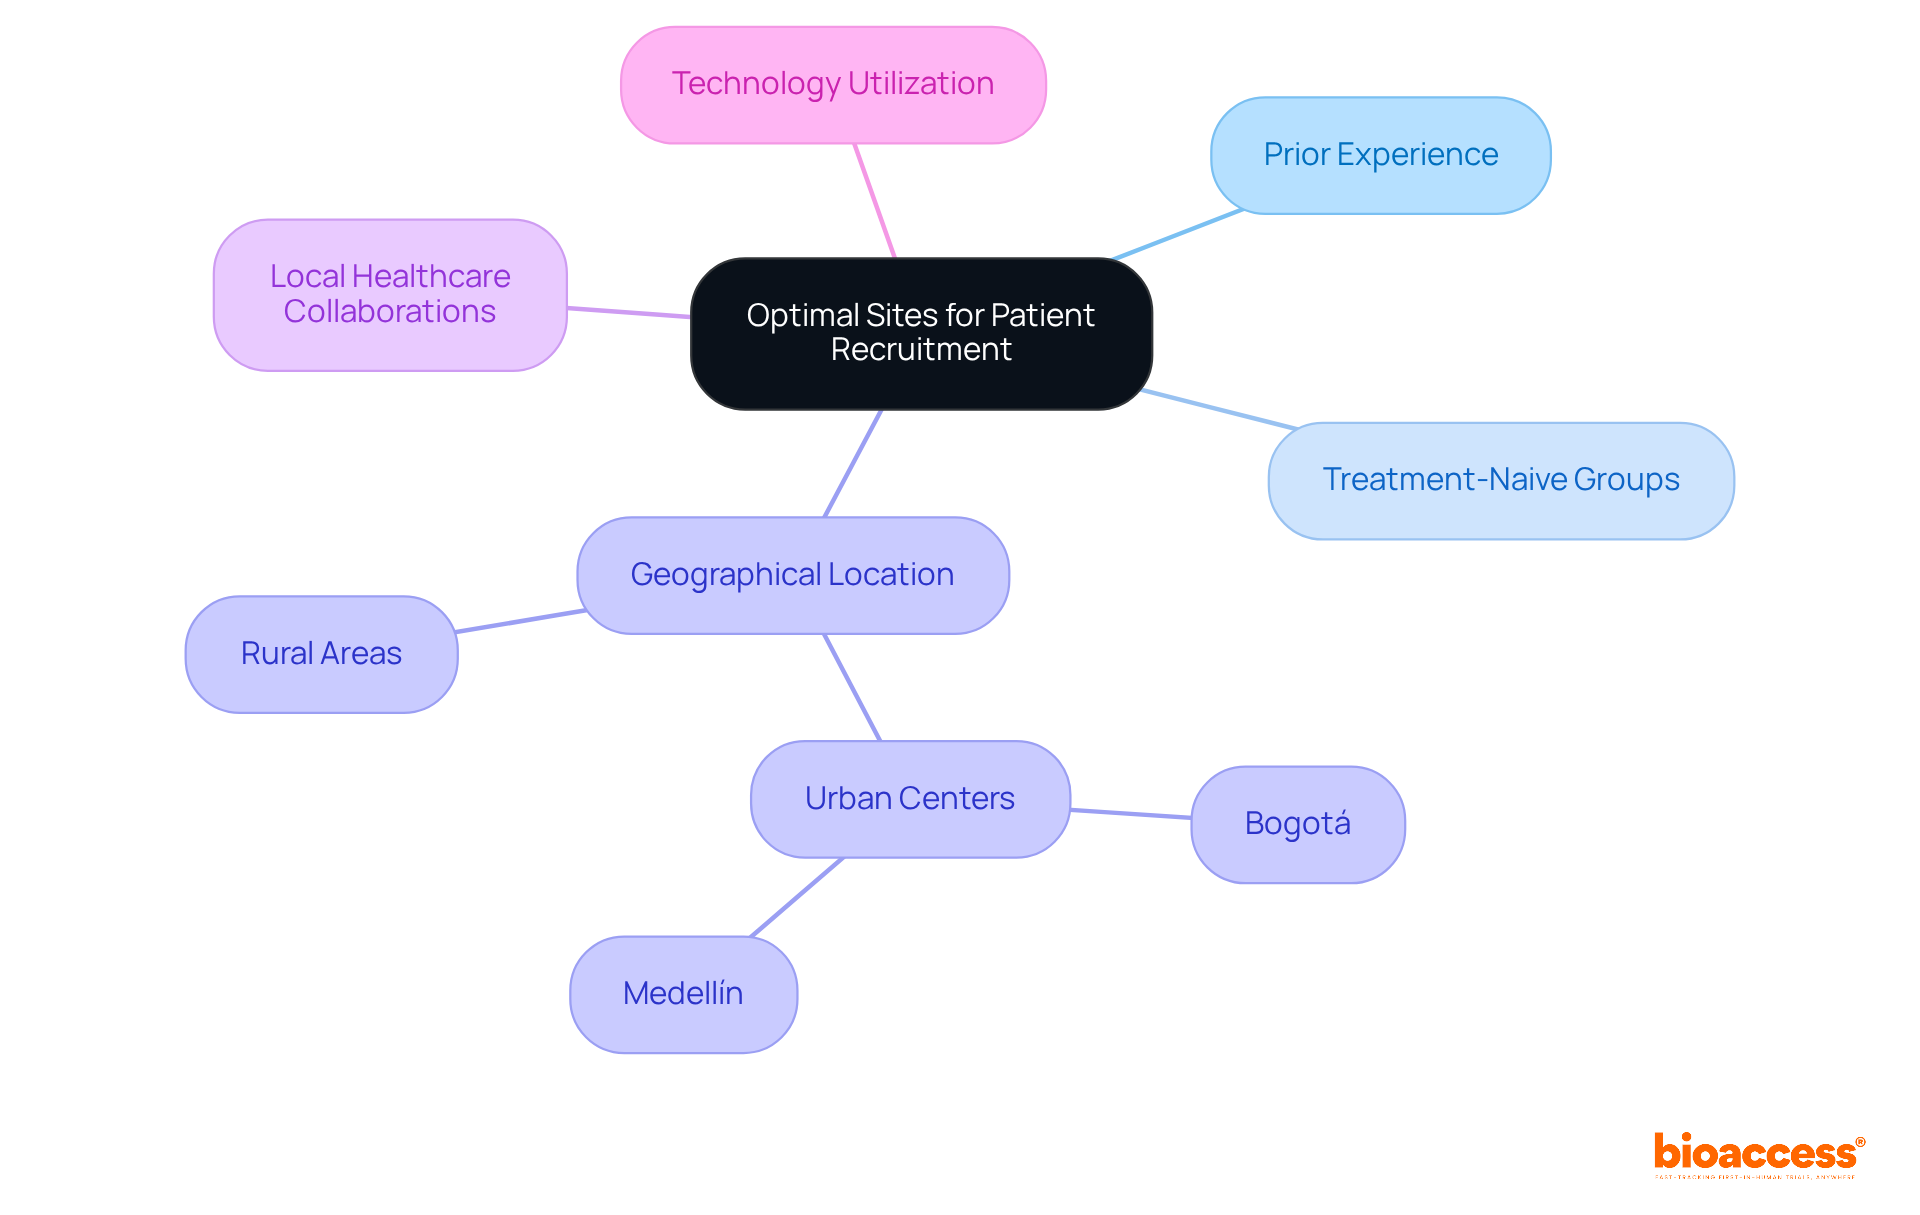
    Sites: Bogotá, Medellín, Cali

    Colombia’s population was estimated at 53 million in 2025 (DANE, July 2025), and by December 2024 more than 160 centres held INVIMA Good Clinical Practice certification (ConsultorSalud).

    INVIMA’s own register of approved research ethics committees places them in Bogotá, Medellín, Cali, Floridablanca and Montería, attached to established IPS and medical foundations (INVIMA, CEI list to May 2025). Bogotá, Medellín and Cali are the tier-1 clusters — high-volume tertiary hospitals, certified pharmacy and clinical-laboratory services inside the same certified institution, and investigator populations that read English protocols without translation. Floridablanca (Santander) and Montería extend regional recruitment reach.

    Ethics committees

    A Colombian trial needs a CEI approved by INVIMA and a site holding a current BPC certificate. That certificate is issued to the IPS after INVIMA verifies compliance with Resolución 2378 de 2008 through inspection visits, runs for five years, and requires evidence that the institution is registered under the Sistema Único de Habilitación with authorized pharmaceutical service, clinical laboratory and sample-collection services (INVIMA, Certificaciones en BPC). Replacing a site’s ethics committee is a formal BPC modification requiring a new-conditions verification visit and a written transfer plan agreed with sponsor, CRO and both committees. Sponsors who treat CEI selection as an afterthought lose weeks here.

    Post-trial access in Colombia

    Colombia does not currently mandate post-trial access by statute. Resolución 2378 de 2008 and Resolución 8430 de 1993 were both read in full for post-trial supply language and neither contains it; Resolución 8430 allocates only harm-related costs (Arts. 13, 15(j)–(k), 58(c)). bioaccess® can operate voluntary continuity programs in Colombia on sponsor request. Statutory PTA mandates in Latin America currently apply to Argentina, Brazil, Panama, Chile, Peru, Ecuador, Costa Rica, Guatemala, Honduras and Nicaragua — not Colombia.

    What is coming, and why it favours moving now

    Three reform tracks are live. A draft unified sanitary regime would replace Decreto 4725 de 2005 and Decreto 3770 de 2004, adding conditional indefinite authorizations, international reliance mechanisms, mandatory UDI from first filing, four IVD risk classes on IMDRF parameters and an 18-month transition; it cleared national consultation and went to WTO public consultation (ConsultorSalud, June 2026). MinSalud has circulated a draft resolution on health research with human beings that would partially repeal Resolución 8430 de 1993 (ConsultorSalud, February 2026). And a clinical-research framework bill filed in the Cámara in August 2025 by Senator Fabián Díaz Plata and Representative Juan Daniel Peñuela Calvache would adopt ICH E6 and ISO 14155:2020 as the regulatory standard, create an INVIMA registry of authorized CROs and accredited investigators, and impose tacit approval — INVIMA objects within 7 calendar days for common-risk research and 30 for high-risk research, with ratification in a further 5 days (Cámara de Representantes, bill text). It classifies first-in-human studies and novel implantable devices as high-risk.

    None is law yet. All three point the same direction, and each rewards sponsors who already hold Colombian sites, a certified CEI relationship and an INVIMA filing history when a transition period starts.

    Registro Sanitario sits at the far end of the same pathway

    Registro Sanitario is the INVIMA marketing authorization that lets a device be sold in Colombia, granted under Decreto 4725 de 2005 with technical evaluation under Article 18 and legal evaluation under Article 19; INVIMA may issue one request for additional information, with 90 days to respond, and BPM and CCAA certificates run for five years (Decreto 4725 de 2005). bioaccess® already runs Registro Sanitario market access in Colombia, and the reason to place trial and registration with one operator is Article 18(k): the clinical evidence a class IIb or III sponsor generates in Colombia is the evidence its Colombian registration will later be judged on.

    Planning a first-in-human or pivotal trial in Colombia? bioaccess® is a US-headquartered, LATAM-native operator running regulatory submissions, importadora functions and 2–8 °C GDP cold chain across the region, and Colombia is now in scope for all phases, all indications, devices and drugs. To discuss INVIMA feasibility, site selection in Bogotá, Medellín or Cali, or a combined trial-plus-Registro-Sanitario pathway, contact Julio Martinez-Clark, Co-Founder & CEO, at jmclark@bioaccessla.com or +1 (954) 903-7210. More at bioaccessla.com/roadmap.

    Frequently asked questions

    Does bioaccess® conduct clinical trials in Colombia?
    Yes. As of September 2026 Colombia is in scope for bioaccess® clinical-trial execution across all phases, from first-in-human through pivotal, in all indications, for both medical devices and drugs. This is a change from our earlier position. The reversal follows documented institutional improvement at INVIMA since 2022 — a dedicated device clinical-research group, a named specialized chamber for device protocols, published approval and non-approval registries, and a public study search — combined with our own operating capability in Bogotá, Medellín and Cali. bioaccess® also runs INVIMA Registro Sanitario market access in Colombia, so the trial and the eventual marketing authorization can be sequenced by one operator.

    What is INVIMA’s role in Colombian clinical trials?
    INVIMA authorizes, monitors and can halt clinical research in Colombia. It evaluates both clinical aspects and the quality of the investigational product, requires approval for Phase I, II and III protocols and for interventional Phase IV protocols, and requires submission of non-interventional Phase IV studies so it can determine whether formal approval applies. It may interrupt an investigation or require modifications at any time if authorization conditions change, Good Clinical Practice is not met, or participant or public-health protection requires it. Sponsor-to-CRO delegations must be reported to INVIMA and remain the sponsor’s responsibility.

    What is the INVIMA clinical-trial pathway for medical devices?
    Three instruments combine. Decreto 4725 de 2005 Article 36 authorizes prototype devices for research and experimentation only, against an INVIMA technical opinion; Article 48(b) permits exceptional importation without sanitary registration where the device is the subject of clinical research authorized in Colombia, following a prior opinion from the specialized chamber; Article 18(k) later requires clinical studies for class IIb and III Registro Sanitario. Resolución 8430 de 1993 supplies the human-subjects rules. The SEDMRDIV issues the technical and methodological opinion, supported since September 2022 by the GICASE group created under Resolución 2022035262.

    What is the INVIMA clinical-trial pathway for drugs?
    Resolución 2378 de 2008 adopted Good Clinical Practices with mandatory application for institutions researching medicines in humans, and is the basis of the site BPC certificate. Initial protocol evaluation is filed through INVIMA’s Protocolos en Línea platform, exclusive for that procedure since 2 January 2020, under tariff 4070 for protocols and 4083 for amendments. Adverse-event reporting content and periodicity follow Resolución 2011020764 de 2011, issued under Article 146 of Decreto 677 de 1995. Importation of unregistered investigational medicines runs under Article 96 of Decreto 677 de 1995 with a Comisión Revisora opinion. Controlled substances involve the Fondo Nacional de Estupefacientes, which administers that monopoly.

    What are typical INVIMA authorization timelines in 2026?
    There is no statutory day-count in force for protocol authorization. The measured figure is an average of 5.1 months from filing to a definitive INVIMA concept, approving or rejecting, against a stable volume of roughly 90 protocol-evaluation requests a year. Sponsors should plan the ethics-committee approval, the INVIMA concept and the import authorization as sequential rather than parallel steps. The clinical-research bill filed in August 2025 would replace the current position with tacit approval — 7 calendar days for common-risk and 30 for high-risk studies — but it is not law.

    Does Colombia require post-trial access?
    No. Colombia does not currently mandate post-trial access by statute. Resolución 2378 de 2008 and Resolución 8430 de 1993 contain no post-trial supply obligation; Resolución 8430 allocates only harm-related costs. bioaccess® can operate voluntary continuity programs in Colombia on sponsor request, governed by the protocol, the informed consent and the ethics committee’s expectations rather than by statute. Statutory PTA mandates in Latin America currently apply to Argentina, Brazil, Panama, Chile, Peru, Ecuador, Costa Rica, Guatemala, Honduras and Nicaragua.

    What is INVIMA Registro Sanitario?
    Registro Sanitario is the INVIMA authorization required to market a medical device in Colombia, granted under Decreto 4725 de 2005 following technical evaluation under Article 18 and legal evaluation under Article 19. INVIMA may issue one request for additional or clarifying information, and the applicant has 90 days to respond before the file is deemed abandoned. Manufacturing and storage certificates — BPM and CCAA — are valid for five years. For class IIb and III devices, Article 18(k) requires clinical studies demonstrating safety and effectiveness, which is why trial design and registration strategy belong in the same plan.

    Which Colombian cities have the best clinical-trial infrastructure?
    Bogotá, Medellín and Cali are the tier-1 clusters, and INVIMA’s own register of approved ethics committees places committees in those three cities plus Floridablanca and Montería, attached to established IPS and medical foundations. More than 160 centres held INVIMA Good Clinical Practice certification as of December 2024. The practical selection criterion is not city size but whether the certified institution holds authorized pharmaceutical service, clinical laboratory and sample-collection services inside the same habilitación, because a contracted service adds documentation to every BPC modification.

    How does Colombia compare to Argentina, Panama and Chile for early-phase device trials?
    On published regulatory clocks, three of the four disclose nothing binding. Argentina’s Disposición 7516/2025 Article 5 assigns protocol evaluation to ANMAT’s Dirección de Investigación Clínica without stating a day-count. Panama’s Decreto Ejecutivo 21 of 23 April 2026 regulates Títulos III and IV of Ley 84 de 2019 with no authorization day-count on the MINSA page. Chile’s ISP publishes 45 business days for the resolution authorizing import of unregistered pharmaceutical products for trial use. Colombia publishes no clock but has a measured 5.1-month average and, unlike the other three, publishes both its approvals and its refusals for device studies.

    What has changed at INVIMA since 2022?
    Resolución 2022035262 of 20 September 2022 created the GICASE group for device clinical research and support to the specialized chamber. The SEDMRDIV now carries an explicit mandate to evaluate device and IVD research protocols. INVIMA publishes registers of approved device studies, non-approved device studies with reasons, SEDMRDIV import authorizations for observational studies, and ethics-committee and site inspection status to November 2025. Its public study search reported 1,157 studies with a data date of 12 August 2026. INVIMA also remains one of eight PAHO Level IV Regional Reference Regulatory Authorities.

    Sources

    • INVIMA — Cooperación internacional (PAHO Level IV ARNr status): https://www.invima.gov.co/el-instituto/cooperacion-internacional
    • PAHO/OPS — Autoridades Regulatorias de Referencia: https://www.paho.org/es/autoridades-regulatorias-referencia
    • INVIMA — Investigación Clínica, Dispositivos (GICASE, Resolución 2022035262 de 2022, forms ASS-RSA-FM085/169/170/171/172, published registers): https://www.invima.gov.co/productos-vigilados/dispositivos-medicos/investigacion-clinica
    • INVIMA — Sala especializada de dispositivos médicos y reactivos de diagnóstico in vitro: https://www.invima.gov.co/productos-vigilados/dispositivos-medicos/sala-especializada-dispositivos-reactivos
    • INVIMA — Registro de estudios clínicos con dispositivos médicos no aprobados 2021–2025: https://www.invima.gov.co/biblioteca/registro-estudios-clinicos-dispositivos-medicos-no-aprobados-invima-2021-2025
    • INVIMA — Lista de Estudios Clínicos (public study search, data date 12 August 2026): https://www.invima.gov.co/estudios
    • INVIMA — Fiscalización de Ensayos Clínicos, Medicamentos (Protocolos en Línea, tariffs 4070/4083, Resolución 2011020764 de 2011): https://www.invima.gov.co/productos-vigilados/medicamentos-y-productos-biologicos/medicamentos-de-sintesis-quimica-y-biologica/ensayos-clinicos
    • INVIMA — Procesos de certificación en Buenas Prácticas Clínicas (BPC certificate, 5-year validity): https://www.invima.gov.co/productos-vigilados/medicamentos-y-productos-biologicos/medicamentos-de-sintesis-quimica-y-biologica/licenciamiento-auditorias-y-certificaciones/certificaciones-en-buenas-practicas
    • INVIMA — Listado de Comités de Ética en Investigación aprobados a mayo 2025: https://www.invima.gov.co/biblioteca/comites-etica-investigacion-aprobados-invima-2025
    • Decreto 4725 de 2005 (Arts. 2, 18, 19, 21, 22, 36, 48, 89) — Función Pública, Gestor Normativo: https://www.funcionpublica.gov.co/eva/gestornormativo/norma.php?i=18697
    • Decreto 677 de 1995 (Art. 96 exceptional import; Arts. 145–146) — INVIMA normograma: https://normograma.invima.gov.co/compilacion/docs/decreto_0677_1995.htm
    • Resolución 2378 de 2008 (Buenas Prácticas Clínicas) — Instituto Nacional de Salud: https://www.ins.gov.co/Normatividad/Resoluciones/RESOLUCION%202378%20DE%202008.pdf
    • Resolución 8430 de 1993 — MinSalud: https://www.minsalud.gov.co/sites/rid/Lists/BibliotecaDigital/RIDE/de/dij/resolucion-8430-DE-1993.PDF
    • Resolución INVIMA 2025046281 de 19 de septiembre de 2025 (contingency plan; Fondo Nacional de Estupefacientes prioritization): http://normograma.invima.gov.co/normograma/compilacion/docs/resolucion_invima_46281_2025.htm
    • Resolución INVIMA 2025010547 de 19 de marzo de 2025 (Plan de Contingencia): https://normograma.invima.gov.co/compilacion/docs/resolucion_invima_10547_2025.htm
    • DANE — Nota Técnica, Proyecciones de Población, July 2025 (53 million in 2025): https://www.dane.gov.co/files/censo2018/proyecciones-de-poblacion/Nacional/NotaTecnica-PPED-jul2025.pdf
    • Cámara de Representantes — clinical-research framework bill, August 2025 (tacit approval 7/30 days, ICH E6, ISO 14155:2020): https://hcrpruebas.camara.gov.co/wp-content/uploads/2025/08/proyectos_ley/25082025_25082025_ver_documento_17.pdf
    • ConsultorSalud, 25 June 2025 — INVIMA average 5.1 months to definitive concept; ~90 protocols/year; 160+ BPC-certified centres: https://consultorsalud.com/colombia-reto-regulacion-estudios-clinicos/
    • ConsultorSalud, June 2026 — draft unified medical device sanitary regime replacing Decretos 4725/2005 and 3770/2004: https://consultorsalud.com/regimen-unico-dispositivos-medicos-impactos/
    • ConsultorSalud, February 2026 — MinSalud draft resolution partially repealing Resolución 8430 de 1993: https://consultorsalud.com/minsalud-investigacion-salud-seres-humanos-ips/
    • Disposición ANMAT 7516/2025, Art. 5 — Boletín Oficial de la República Argentina: https://www.boletinoficial.gob.ar/detalleAviso/primera/332695/20251009
    • Instituto de Salud Pública de Chile — 45 business days for trial import authorization: https://www.ispch.gob.cl/pregunta-frecuente/p-141/
    • MINSA Panamá — Decreto Ejecutivo N° 21 de 23 de abril de 2026: https://www.minsa.gob.pa/normatividad/decreto-ejecutivo-ndeg-21-jueves-23-de-abril-2026-que-reglamenta-los-titulos-iii-y-iv
    • bioaccess® — Colombia clinical trial regulatory guide: https://bioaccessla.com/regulatory-guide/colombia

  • The legal architecture of Latin American post-trial access: SDEA, DPA, product liability, sponsor accession

    A Latin American post-trial access (PTA) program is a regulatory filing wrapped in four contracts. The filing is the visible part — an ANMAT import expediente, an ANVISA ofício, a DIGEMID authorization. The four contracts are what determine who answers to a regulator, who answers to a patient, and who answers to a plaintiff’s lawyer three years after the last shipment.

    Those four instruments are a Safety Data Exchange Agreement, a country-specific Data Processing Agreement, a product-liability allocation, and — the one most often missing — a sponsor accession mechanism that binds the marketing-authorization holder to the same schedules the operator signed. This piece sets out how we paper each of them and the five architectural mistakes that recur in draft PTA agreements we review.

    Why the paperwork carries more weight than the filing

    In nine Latin American jurisdictions the continued-supply duty is statutory and sits on the sponsor. Brazil’s Lei nº 14.874/2024 Art. 31 §4 states that “o fornecimento do medicamento será de responsabilidade do patrocinador,” and Art. 33 inciso VI releases the sponsor only five years after commercial availability in Brazil. Chile’s Código Sanitario Art. 111 C, inserted by Art. 34 of Ley 20.850, attaches the free-supply duty to the holder of the provisional-use authorization and then to the sanitary-registration holder — including a successor that acquired the registration later. Peru’s DS 021-2017-SA Art. 40(p) and Art. 89 put both the access duty and the funding on the sponsor. Panama’s Decreto Ejecutivo 21/2026 Art. 68 (Gaceta Oficial Digital 30510-C, 23 April 2026, which reglamentates Titles III and IV of Ley 84 de 14 de mayo de 2019) names investigadores y patrocinadores as co-obligors.

    None of those statutes names an operator, an importadora, or a managed-access vendor. The obligation is the sponsor’s by law. Everything the operator does — the import authorization under Disposición ANMAT 12792/2016 Art. 4, the cold-chain leg, the pharmacovigilance intake — is performed on behalf of an obligor that remains the obligor. If the contract does not say so with precision, the operator has effectively assumed a statutory duty it has no legal standing to discharge.

    Pillar 1: the Safety Data Exchange Agreement

    The SDEA is the instrument that connects local adverse-event intake to the sponsor’s global pharmacovigilance system. It should be executed within 30 days of the Work Order, not left to a later “PV annex to follow.”

    Three ICH guidelines set the substance. ICH E2A fixes the expedited-reporting clock: fatal or life-threatening unexpected adverse drug reactions require notification “as soon as possible but no later than 7 calendar days after first knowledge by the sponsor,” followed by a fuller report “within 8 additional calendar days” (§III.B.1), while all other serious unexpected ADRs run on a 15-calendar-day clock (§III.B.2). Because the clock starts on sponsor knowledge, the SDEA must set an internal onward-transmission deadline for the local operator that is materially shorter — otherwise the sponsor’s regulatory clock is being consumed by the operator’s intake queue. ICH E2F governs periodic reporting: the DSUR is an annual report with a data lock point on “the last day of the one-year reporting period” and submission “no later than 60 calendar days after the DSUR data lock point” (§2.2), so the SDEA must specify who supplies PTA-cohort line listings into that cycle and by when. ICH E3 §12 sets the safety-evaluation structure the underlying trial report already follows, which is the format PTA safety data should feed into rather than a parallel one.

    Practical drafting points: name the sponsor’s global PV mailbox and the operator’s PV contact by role, define the reconciliation cadence, and state expressly that regulatory reporting to the local authority is the sponsor’s obligation performed through the operator as agent, with the operator’s duty limited to timely, accurate onward transmission.

    Pillar 2: the Data Processing Agreement — country by country

    There is no single Latin American data-protection instrument, so there is no single DPA. The controlling article set changes by jurisdiction:

    Jurisdiction Instrument Transfer article Notes for PTA drafting
    Argentina Ley 25.326 Art. 12(1)–(2) Transfer to countries without adequate protection is prohibited; Art. 12(2)(b) carves out medical-data exchange where the affected person’s treatment requires it. Art. 11(4) makes the transferee subject to the transferor’s obligations and imposes joint liability.
    Argentina (clauses) AAIP Resolución 198/2023 Anexo I Approves two model clause sets: responsable–responsable and responsable–encargado. Use the latter where the operator processes only on sponsor instruction (Cláusula 6.1).
    Brazil Lei nº 13.709/2018 (LGPD) Arts. 33–36 Art. 33 II(a)–(b) permits transfer on specific or standard contractual clauses; Art. 33 VIII permits it on specific, highlighted consent distinguished from other purposes.
    Mexico LFPDPPP (DOF 20 March 2025) Arts. 35–36 Health data is sensitive (Art. 2 fr. VI) and requires express written consent (Art. 8). Art. 36 fr. II exempts transfers necessary for medical treatment or health-service management.
    Chile Ley 19.628Ley 21.719 Art. 10 → Arts. 27–29 Ley 21.719 was published 13 December 2024 and enters into force 1 December 2026. Any Chilean PTA DPA signed now should be drafted to the Arts. 27–29 transfer regime, not only to Ley 19.628 Art. 10.
    Peru DS 016-2024-JUS (Reglamento, Ley 29733) Arts. 18–20 In force 120 calendar days after publication (31 March 2025). Art. 20.1 permits model contractual clauses imposing “cuando menos las mismas obligaciones” on the importer.
    Colombia Ley Estatutaria 1581 de 2012 Art. 26 Health data is sensitive (Art. 5); Art. 26(b) carves out medical-data exchange required by the data subject’s treatment. Otherwise the SIC issues a declaración de conformidad (Art. 26, par. 1).

    The operator-side drafting position is the same everywhere: the sponsor is responsable/controller, the operator is encargado/operator, processing is limited to documented instructions, sub-processing requires prior written consent, and the operator returns or deletes on termination subject to statutory retention. Where the destination country has no adequacy finding, attach the applicable model clauses as a schedule rather than describing them in the body.

    The Argentina adequacy mistake

    The most common error in Argentine PTA drafting is treating Commission Decision 2003/490/EC as if it authorised outbound transfers from Argentina. Article 1 reads: “Argentina is regarded as providing an adequate level of protection for personal data transferred from the Community.” Article 2 confines the decision to adequacy in Argentina “with a view to meeting the requirements of Article 25(1) of Directive 95/46/EC.” The instrument is unidirectional — EU to Argentina.

    A PTA data flow from Argentine sites to a sponsor in the United States, or to an access vendor in the Netherlands, is an Argentine outbound transfer governed by Ley 25.326 Art. 12, and the correct instrument is the AAIP responsable–encargado model agreement under Resolución 198/2023, not a citation to the 2003 decision. Treating the adequacy finding as reciprocal is a defect that survives review because it looks like a considered legal position.

    Pillar 3: product liability sits with the sponsor

    The operator is not the manufacturer, does not hold the marketing authorization, and cannot practically bear product-liability risk for the product itself. A managed-access or expanded-access vendor is in the same position. Neither controls design, manufacture, batch release, labelling content, or the safety profile — so neither can defend a product claim on the merits or insure it economically.

    Our drafting position, and the position we recommend to any operator in this role:

    • The sponsor or titular defends and indemnifies the operator against third-party claims arising from the product itself, including design, manufacture, and labelling defects.
    • The sponsor maintains product-liability insurance covering the PTA territories for the duration of the program plus a tail, and provides certificates on request.
    • The operator’s liability cap covers operator services only. Product liability sits outside the cap.
    • Carve-outs outside the cap in both directions: gross negligence, wilful misconduct, breach of confidentiality, intellectual-property infringement, and breach of data-protection obligations.

    The cap itself is negotiable, usually expressed against fees paid under the Work Order over a defined lookback. Its composition is not: a cap that silently absorbs product liability converts a services agreement into an uninsured product warranty.

    Pillar 4: sponsor accession as a condition precedent

    Because the sponsor holds the statutory supply duty, the product liability, the marketing authorization, and the primary pharmacovigilance obligation, an operator’s Work Order should be conditioned on sponsor accession. Two mechanisms work:

    1. Direct accession — the sponsor executes a short accession instrument to the schedules that allocate safety data exchange, data processing, and liability (in our template set, schedules C, E and F).
    2. Tripartite side letter — the sponsor, the access vendor or intermediary, and the operator sign a single side letter confirming the sponsor’s indemnity, insurance, PV ownership, and patient-continuity funding, with the underlying Work Order otherwise unchanged.

    Either way the Work Order should not become effective until accession is signed. Without it, the operator holds a services contract with a counterparty that cannot deliver the indemnity the contract assumes, and the patient-continuity commitment has no funded obligor behind it.

    Five architectural mistakes we see repeatedly

    1. No sponsor accession condition. The operator signs with an intermediary and inherits an unfunded, uninsurable duty.
    2. Product liability inside the operator’s cap. Structurally wrong for a non-manufacturer.
    3. The reciprocal-adequacy error. Argentina→US or Argentina→NL flows papered as if Decision 2003/490/EC covered them.
    4. No patient-continuity run-off. Termination should trigger a defined run-off — our default is 90 days — during which supply, PV intake, and cold-chain continue at the sponsor’s cost.
    5. No sponsor-funded continuity trigger. If the sponsor terminates the program or the access vendor disengages, the continuity obligation must be expressly sponsor-funded, or patients absorb the commercial dispute.

    Governing law, dispute resolution, and pre-send gates

    For cross-border PTA services agreements with a US-headquartered operator, Delaware law with AAA-ICDR arbitration seated in New York is a sensible default: neutral to the LATAM performance jurisdictions, familiar to sponsor counsel, and enforceable across the region under the New York Convention. Local-law carve-outs remain necessary for the statutory duties themselves, which are not contractible away.

    Before any PTA agreement leaves our desk it passes four gates: (1) a counsel memo verifying the regulatory framework and article citations for each performance jurisdiction; (2) named performing entities, including the habilitada local entity and the importadora of record; (3) sponsor accession path agreed in principle, in writing, before signature; and (4) harmonized statutory-obligation language, so that the same duty is not described one way in the recitals and another way in the schedules.

    Frequently asked questions

    What legal architecture does a LATAM post-trial access program require?
    Four instruments beyond the services agreement itself: a Safety Data Exchange Agreement connecting local adverse-event intake to the sponsor’s global pharmacovigilance system; a country-specific Data Processing Agreement built on the applicable transfer article (Argentina Ley 25.326 Art. 12, Brazil LGPD Arts. 33–36, Colombia Ley 1581 Art. 26, and so on); a product-liability allocation placing defence, indemnity, and insurance on the sponsor or titular; and a sponsor accession mechanism binding the marketing-authorization holder to those schedules. The regulatory filing — import authorization, ethics submission — is separate and downstream.

    What is a Safety Data Exchange Agreement (SDEA) in PTA?
    An SDEA is the bilateral agreement that defines how safety information moves from the PTA site and local operator into the sponsor’s global pharmacovigilance system. It should be executed within 30 days of the Work Order and built on ICH principles: ICH E2A §III.B for the 7-day and 15-calendar-day expedited-reporting clocks, ICH E2F §2.2 for annual DSUR periodicity and the 60-day post-data-lock-point submission window, and ICH E3 §12 for the safety-evaluation structure the data must fit. It names PV contacts, sets onward-transmission deadlines shorter than the sponsor’s regulatory clock, and fixes a reconciliation cadence.

    What is a Data Processing Agreement (DPA) in Argentine PTA?
    It is the instrument that makes an Argentine PTA data flow lawful under Ley 25.326. Art. 12(1) prohibits transfer to countries or organisations that do not provide adequate protection levels, and Art. 11(4) makes the transferee subject to the transferor’s obligations with joint liability. Where the sponsor sits in a country without an Argentine adequacy finding, the practical route is the responsable–encargado model agreement approved by AAIP Resolución 198/2023, attached as a schedule. Cláusula 6.1 limits the importer to the exporter’s documented instructions, with no decision-making power over scope or content.

    Does EU Commission Decision 2003/490/EC cover Argentina→US or Argentina→EU data flows?
    No. Article 1 of Decision 2003/490/EC regards Argentina as adequate for “personal data transferred from the Community,” and Article 2 limits the decision to adequacy in Argentina for the purposes of Article 25(1) of Directive 95/46/EC. The decision is unidirectional: EU to Argentina. An outbound transfer from Argentine sites to a US sponsor or a Dutch access vendor is governed by Ley 25.326 Art. 12 and requires its own adequacy basis, statutory exception, or model clauses. Article 3 of the decision, in fact, gives EU authorities power to suspend flows to recipients in Argentina — the opposite of a reciprocal permission.

    Who bears product liability in a PTA program — the sponsor, the manufacturer, or the operator?
    The sponsor or the titular of the marketing authorization. The operator is not the manufacturer, does not hold the authorization, and does not control design, manufacture, batch release, or labelling — so it cannot defend a product claim on the merits or insure it at a rational price. The correct architecture has the sponsor defend and indemnify the operator for product-related third-party claims, maintain product-liability insurance covering the PTA territories for the program term plus a tail, and accept that product liability sits outside the operator’s services liability cap.

    Why should PTA operators condition the Work Order on sponsor accession?
    Because the sponsor holds every obligation the Work Order depends on: the statutory continued-supply duty, the marketing authorization, primary pharmacovigilance responsibility, product liability, and the funding for patient continuity. An operator that contracts only with an intermediary holds an indemnity from a party that does not control the product and a continuity commitment with no funded obligor. Making accession a condition precedent — rather than a post-signature action item — is the only reliable way to ensure the risk allocation in the schedules is enforceable against the party that can actually perform it.

    What is a tripartite side letter in LATAM PTA?
    A single short instrument signed by the sponsor, the access vendor or intermediary, and the local operator, used where the sponsor will not accede directly to the operator’s schedules. It confirms four things: the sponsor’s defence and indemnity for product-related claims; the sponsor’s product-liability insurance covering the PTA territories; sponsor ownership of primary pharmacovigilance and regulatory reporting; and sponsor funding of patient continuity, including any run-off period. It leaves the underlying Work Order commercial terms untouched, which is usually why it is the faster path to signature.

    What is the standard liability cap in a LATAM PTA Work Order?
    There is no single market standard, and any figure quoted as one should be treated with suspicion. Caps are typically expressed as a ceiling tied to fees paid under the Work Order over a defined lookback period. The more consequential negotiation is not the number but the composition — what the cap covers and what sits outside it. A cap that quietly includes product liability turns a services agreement into an uninsured product warranty, which is a worse outcome for the operator than a low number with clean carve-outs.

    What carve-outs should sit outside the liability cap?
    Five, in both directions: gross negligence, wilful misconduct, breach of confidentiality, intellectual-property infringement, and breach of data-protection obligations. Product liability should also sit outside the operator’s cap, because the operator is not the manufacturer. Data-protection breach deserves particular attention in Latin America: Argentina’s Ley 25.326 Art. 11(4) imposes joint liability between transferor and transferee, and Mexico’s LFPDPPP Art. 59 fr. IV allows sanctions for sensitive-data infractions to be increased up to twofold, so capped data-protection exposure can be materially lower than actual statutory exposure.

    What is the standard patient-continuity run-off period?
    Our default drafting position is 90 days from the effective date of termination. During that window, product supply, pharmacovigilance intake, and cold-chain and importation services continue at the sponsor’s cost while the sponsor arranges an alternative route — a successor operator, an extension study, or transition into commercial or public-system supply. The reason to fix a defined period rather than “a reasonable transition” is that the statutory obligations do not pause: Brazil’s Lei 14.874/2024 Art. 33 lists exhaustive interruption grounds, and contract termination between a sponsor and its operator is not one of them.

    Should managed-access-program specialists require sponsor accession too?
    Yes, and for the same structural reason. A managed-access or expanded-access specialist occupies the same position as a regional operator: it is not the manufacturer, does not hold the marketing authorization, and cannot bear product-liability risk for the product. Whether the intermediary is a global access platform, a specialty distributor, or a regional CRO, the party with the statutory supply duty and the insurable product risk is the sponsor. Any access architecture that leaves the sponsor outside the contractual chain has a gap at exactly the point where a patient-harm claim would land.

    Working on a LATAM post-trial access program? bioaccess® is a US-headquartered, LATAM-native operator running regulatory, importadora, and 2–8 °C GDP cold-chain functions directly across the region. If you’re evaluating PTA feasibility in Argentina, Brazil, Chile, Peru, Panama, Mexico or Colombia, contact Julio Martinez-Clark, Co-Founder & CEO, at jmclark@bioaccessla.com or +1 (954) 903-7210. More at bioaccessla.com/roadmap.

    Sources

    • ICH E2A, Clinical Safety Data Management: Definitions and Standards for Expedited Reporting — https://database.ich.org/sites/default/files/E2A_Guideline.pdf
    • ICH E2F, Development Safety Update Report — https://database.ich.org/sites/default/files/E2F_Guideline.pdf
    • ICH E3, Structure and Content of Clinical Study Reports — https://database.ich.org/sites/default/files/E3_Guideline.pdf
    • Commission Decision 2003/490/EC of 30 June 2003 (Argentina adequacy) — https://eur-lex.europa.eu/legal-content/EN/TXT/HTML/?uri=CELEX:32003D0490
    • Argentina, Ley 25.326 (Protección de los Datos Personales) — https://servicios.infoleg.gob.ar/infolegInternet/anexos/60000-64999/64790/texact.htm
    • Argentina, AAIP Resolución 198/2023 (RESOL-2023-198-APN-AAIP, BO 18/10/2023), model international-transfer clauses — https://servicios.infoleg.gob.ar/infolegInternet/anexos/390000-394999/391538/norma.htm
    • Argentina, AAIP Resolución 198/2023 Anexo I (IF-2023-108581614-APN-DNPDP#AAIP) — https://servicios.infoleg.gob.ar/infolegInternet/anexos/390000-394999/391538/res198.pdf
    • Argentina, Disposición ANMAT 12792/2016 (post-study import procedure) — https://www.boletinoficial.gob.ar/detalleAviso/primera/154162/20161117
    • Argentina, Disposición ANMAT 7516/2025 (GCP, in force 1 December 2025) — https://www.boletinoficial.gob.ar/detalleAviso/primera/332695/20251009
    • Brazil, Lei nº 13.709/2018 (LGPD) — https://www.planalto.gov.br/ccivil_03/_ato2015-2018/2018/lei/l13709.htm
    • Brazil, Lei nº 14.874/2024, Arts. 30–37 — https://www.planalto.gov.br/ccivil_03/_ato2023-2026/2024/lei/l14874.htm
    • Brazil, Decreto nº 12.651/2025, Art. 31 — https://www2.camara.leg.br/legin/fed/decret/2025/decreto-12651-7-outubro-2025-798105-publicacaooriginal-176652-pe.html
    • Mexico, Ley Federal de Protección de Datos Personales en Posesión de los Particulares (DOF 20 March 2025; last reform DOF 14 November 2025) — https://www.diputados.gob.mx/LeyesBiblio/pdf/LFPDPPP.pdf
    • Chile, Ley 19.628 sobre Protección de la Vida Privada — https://www.bcn.cl/leychile/navegar?idNorma=141599
    • Chile, Ley 21.719 (published 13 December 2024; in force 1 December 2026) — https://www.bcn.cl/leychile/navegar?idNorma=1209272
    • Chile, Ley 20.850 and Código Sanitario Art. 111 C — https://www.bcn.cl/leychile/navegar?idNorma=1078148
    • Peru, Decreto Supremo N° 016-2024-JUS (Reglamento de la Ley 29733) — https://www.gob.pe/institucion/anpd/normas-legales/6554453-16-2024-jus
    • Peru, Reglamento de Ensayos Clínicos, DS 021-2017-SA, Arts. 115–118 — https://ensayosclinicos-repec.ins.gob.pe/images/Reglamento_de_EC.pdf
    • Colombia, Ley Estatutaria 1581 de 2012 — https://www.funcionpublica.gov.co/eva/gestornormativo/norma.php?i=49981
    • Panama, Decreto Ejecutivo No. 21 de 23 de abril de 2026, Art. 68, Gaceta Oficial Digital No. 30510-C (primary-source Gaceta PDF, read 6 September 2026)

  • Post-trial access in Latin America: the operator’s map

    Ten Latin American countries legally require a trial sponsor to keep supplying the investigational product after the study closes. Three more address post-trial continuation in binding instruments with weak or unassigned duties. Seven impose nothing. If your Phase 3 has LATAM sites, that distinction is a line item, not an ethics footnote.

    We built this map because the region is now diverging fast. Brazil enacted a statute in 2024 and its regulation in 2025. Honduras went from zero to a mandate in February 2026. Panama replaced its research decree in April 2026. Meanwhile most global vendor and law-firm summaries still cite instruments that have been repealed, and several repeat citation errors that a regulator would catch on the first review cycle.

    Where the mandates actually are

    Across 20 jurisdictions, the classification breaks down as follows.

    Binding statutory mandate (10): Argentina, Brazil, Chile, Peru, Ecuador, Costa Rica, Guatemala, Honduras, Nicaragua, Panama. Each has a law, decree, resolution or ministerial normativa that obliges continued provision of the investigational product after the trial ends.

    Binding instrument, weak or unassigned duty (3): Uruguay, Bolivia, Venezuela. Venezuela’s Buenas Prácticas Clínicas §6.12.1 requires the sponsor only to “procurar… la provisión del tratamiento” after the trial — endeavour, not provide (INHRR). Uruguay’s Decreto 158/019 Anexo numeral 24 says participants “deben tener la certeza de que contarán con los beneficios demostrados” but names no obligor at all (IMPO). Bolivia’s Art. 99 routes continuation entirely into the compassionate-use chapter, requiring per-patient DINAMED authorization (AGEMED).

    No mandate (7): Mexico, Colombia, Paraguay, El Salvador, Dominican Republic, Cuba, Puerto Rico. In each case we read the operative clinical-trial instrument and it contains no post-trial supply obligation.

    The comparative matrix

    Country Mandate status Primary instrument Cost allocation Import mechanism
    Argentina Binding statute Disp. ANMAT 12792/2016; GCP base reset by Disp. 7516/2025 Sponsor, free to participant, site and payer (Art. 3(g)) Dedicated PTA import expediente to ANMAT–DERM, valid 12 months (Art. 4); physical import via INAME (Art. 5)
    Brazil Binding statute Lei 14.874/2024 Arts. 30–37 + Decreto 12.651/2025 Art. 31 Sponsor (Lei Art. 31 §4); free supply (Decreto Art. 31) ANVISA authorization + import licence under RDC 38/2013
    Chile Binding statute Ley 20.850 Art. 17; Cód. Sanitario Art. 111 C “Sin costo para el paciente”; duty on provisional-authorization holder, then registration holder ISP special provisional-use authorization (Art. 111 A); CENABAST exceptional import
    Peru Binding statute DS 021-2017-SA Arts. 115–118 Sponsor-funded, provided free (Arts. 40(p), 89) OGITT extension trial or case-by-case ANM/DIGEMID authorization (Art. 116) with a seven-document set (Art. 117)
    Panama Binding statute Decreto Ejecutivo 21/2026 Art. 68, Gaceta Oficial 30510-C, 23 Apr 2026 Investigators and sponsors co-obligated to ensure access; cost not stated verbatim Extension of the trial import permit for exclusive participant use (Art. 68); RESEGIS registration + DNFD authorization (Art. 99)
    Ecuador Binding statute AM 00069-2024 Arts. 80–81, 95(c) Sponsor or legal representative, “entrega gratuita” (Art. 80) No PTA-specific route; general ARCSA import authorization
    Costa Rica Binding statute Ley 9234 Arts. 28, 53(k) Sponsor, free, “mientras lo requieran” None identified in the statute for post-trial product
    Guatemala Binding statute (instrument version unconfirmed) AM 82-2019 Art. 64; MSPAS index lists AM 206-2021 Supply “podrá ser solicitada al patrocinador” — request-driven, not automatic Compassionate-use authorization by the DRCPFA (Art. 65)
    Honduras Binding statute (new) Acuerdo 0256-ARSA-2025 Art. 63 Sponsor or legal representative, “sin costo” (Art. 63) Extension trial or compassionate use (Art. 63); special ARSA import authorization (Art. 86)
    Nicaragua Binding statute Normativa-166 Cap. VI num. 16 Sponsor obliged; free-of-charge stated for the trial phase only General trial import rules; no PTA route
    Uruguay Binding guidance Decreto 158/019 Anexo num. 24 No obligor named n.a.
    Bolivia Binding guidance Norma para Estudios Clínicos Art. 99 → Arts. 74–76 Not allocated post-trial Per-patient DINAMED compassionate-use authorization
    Venezuela Binding guidance Normas de BPC §§5.4.5, 6.12.1 Free during trial only; post-trial duty is “procurar” None described
    Mexico No mandate for product supply NOM-012-SSA3-2012 §11.2.2 Investigator must arrange continued “tratamiento y cuidados” — not IP supply n.a.
    Colombia No mandate Res. 2378/2008 n.a. n.a.
    Paraguay No mandate Resol. DINAVISA 238/2024 n.a. n.a.
    El Salvador No mandate Lineamientos Técnicos, Ac. Ejec. 1530 (2025) n.a. n.a.
    Dominican Republic No mandate Manual CONABIOS, 2ª ed. n.a. — §7.1 gives an information right only n.a.
    Cuba No mandate BPC en Cuba (CECMED) n.a. — §4.3.2 covers adverse-event medical care only n.a.
    Puerto Rico (US) No mandate 21 CFR 312 Subpart I n.a. — permissive expanded-access framework n.a. (US customs territory)

    Why this is a closing cost, not an ethics footnote

    A sponsor that runs sites in Brazil, Chile, Peru, Panama and Argentina and then closes the study has, in five jurisdictions, a legally enforceable duty to keep shipping product to responders — free of charge, under separate authorizations, for a period the sponsor does not control.

    Brazil’s Ministry of Health states the position without hedging: continued post-study treatment “não é uma expectativa, mas um dever legal, aplicável desde o planejamento da pesquisa até o período pós-estudo” (INAEP FAQ). That duty is priced nowhere in a standard Phase 3 budget. It requires a cohort-scale filing distinct from the trial dossier, an import authorization with its own clock, GDP-compliant cold chain for as long as the cohort persists, and pharmacovigilance reporting after database lock.

    The obligation also survives corporate events. Chile’s Código Sanitario Art. 111 C states the duty “afectará al titular del registro sanitario, aun cuando no haya sido el titular de la autorización provisional o haya adquirido con posterioridad el registro sanitario” (BCN). Buy a Chilean registration and you buy the free-supply obligation attached to it. That belongs in diligence, not in a site-activation checklist.

    The five strongest sponsor obligations

    Brazil. Lei 14.874/2024 Art. 30 requires the sponsor and investigator to file a post-study access plan with the CEP before the trial starts. Art. 31 §4 puts the cost on the sponsor. Art. 33 permits interruption only on listed grounds, including the “transcurso do prazo de 5 (cinco) anos, contado da disponibilidade comercial do medicamento experimental no País.” Decreto 12.651/2025 Art. 31 restates the free-supply duty whenever the investigator judges the product the best therapeutic alternative. Full detail in our Brazil post-trial access pillar.

    Chile. Art. 111 C obliges continuity “sin costo para el paciente… por todo el tiempo que persista su utilidad terapéutica” — no commercialization endpoint, no five-year cap. See the Chile Ley 20.850 analysis.

    Panama. Article 68 of Decreto Ejecutivo 21/2026 (Gaceta Oficial 30510-C, 23 April 2026) reads: “Los investigadores y patrocinadores deben asegurar a todos los participantes el acceso al producto, siempre que se haya comprobado el beneficio clínico o de salud pública de la intervención durante el estudio; hasta su comercialización en el país.” It then requires the sponsor to apply for “una extensión del permiso de importación del producto utilizado durante la investigación para uso exclusivo de los participantes.” The decree entered into force on promulgation under Art. 105. Detail in the Panama Decreto 21/2026 pillar.

    Argentina. Disposición ANMAT 12792/2016 is the only instrument in the region that is purely a post-trial access import procedure. Art. 3(g) requires a sworn sponsor declaration that supply will be “sin costo alguno para el participante, el establecimiento asistencial o su cobertura de salud” — note that the site and the payer are named, not just the patient. Art. 4 gives the DERM authorization a 12-month validity. Art. 2 excludes authorized extension studies, which run on a different track. See the Argentina Disposición 12792 pillar.

    Peru. DS 021-2017-SA is the best-drafted operational regime in the region: Art. 115 defines the obligation and its trigger conditions, Art. 116 names two authorization routes (OGITT extension trial or case-by-case ANM/DIGEMID authorization), Art. 117 lists the documents, Art. 118 assigns post-access pharmacovigilance. Art. 40(p) makes it a sponsor duty. See the Peru DS 021-2017-SA pillar.

    Where the duty reaches devices

    Most LATAM post-trial provisions were drafted for medicines. Four jurisdictions reach hardware textually.

    Costa Rica is the clearest. Ley 9234 Art. 53(k) obliges the sponsor to provide, free of charge and after the study concludes, “el medicamento, dispositivo o procedimiento que ha sido objeto de investigación,” with four exhaustive exits — including a reasoned treating-physician resolution filed in the record and communicated to the CEC within three working days. Art. 28 sets the duration at “mientras lo requieran.”

    Brazil reaches devices through Lei 14.874/2024 Art. 37: “Aplicar-se-ão aos produtos e dispositivos médicos e aos produtos de terapias avançadas experimentais… as disposições deste Capítulo, no que couber.” Chile reaches them through Código Sanitario Art. 111 A, which covers “los productos farmacéuticos y los elementos de uso médico.” Peru reaches them through the definition of producto en investigación in Art. 2.1.36.

    Ecuador does not. AM 00069-2024 is a reglamento for medicines and processed natural medicinal products, so a device sponsor’s Ecuadorian exposure runs through ethics-committee expectations and the informed consent, not through Arts. 80–81.

    What changed between 2024 and 2026

    Honduras added a mandate. Acuerdo 0256-ARSA-2025 Art. 63 defines post-trial access as “la entrega sin costo por parte del patrocinador o su representante legal,” even where the product has no Honduran sanitary registration, subject to three cumulative conditions. Published in La Gaceta on 28 January 2026, in force 30 days later. The predecessor Acuerdo 041-2020 had no post-trial provision at all. Read Art. 63 alongside Art. 18 numeral 5, which softens the duty to facilitating access “cuando el patrocinador lo considere” — a real internal tension, and a reason not to treat Honduras as equivalent to Brazil.

    Panama replaced its research decree. Decreto Ejecutivo 21/2026 reglamenta Titles III and IV of Ley 84 de 14 de mayo de 2019 and entered into force on promulgation, 23 April 2026. Its Art. 104 repeals Decreto Ejecutivo 1843 of 2014, Decreto Ejecutivo 6 of 2015 and Resolución 390 of 2003.

    Ecuador deleted its endpoint. AM 00069-2024 Art. 80 states the free-supply duty with no termination point. The repealed AM 0075-2017 had capped it: Art. 39(w) ran only “hasta que el producto se comercialice en el país” (MSP Ecuador). Art. 81 narrowed the trigger to three cumulative conditions while the duration became open-ended. Almost nobody has flagged that trade.

    Brazil completed a two-step build. Statute in 2024, regulation in 2025, with further INAEP guidance promised by Decreto 12.651/2025 Art. 31 §2.

    Argentina reset its GCP base. Disposición 7516/2025 took effect 1 December 2025 (Art. 8). Its Art. 7 repealed Disposiciones 6677/10, 4008/17, 9929/19 and 2172/25 plus Circulares 0001/11 and 004/18. Disp. 12792/2016 is absent from that repeal list, so the post-trial import procedure stands — but the substantive continuity duty moved into the new GCP annex, and sponsors are filing against instruments that no longer exist. The legal architecture of LATAM PTA piece works through how the obligation layer and the import layer interact.

    Colombia: no binding post-trial access statute

    We read Resolución 2378 de 2008 and Resolución 8430 de 1993 in full, checking expressly for post-trial supply language. Neither contains any. Res. 8430/1993 allocates only harm-related costs — Art. 13 medical care for research-related injury, Art. 15(j) treatment availability and indemnification, Art. 15(k) additional costs against the research budget.

    That makes Colombia a cost-certainty jurisdiction: no statutory tail obligation, no separate post-trial filing, no open-ended supply exposure. It does not make post-trial access impossible. A sponsor that wants to continue supplying responders in Colombia can run a voluntary continuity program on its own initiative, handled through the ethics committee, the informed consent and the general product import rules. The exposure is contractual and reputational rather than statutory, which means it has to be allocated in the CRO and site agreements rather than assumed away.

    Mexico sits in an adjacent position and is routinely misdescribed. NOM-012-SSA3-2012 §11.2.2 obliges “el investigador principal” to arrange continuation of “el tratamiento y cuidados” to prevent withdrawal effects. That is an investigator duty about care, not a sponsor duty to supply the investigational product.

    What sponsors get wrong

    Citing repealed instruments. Argentina’s Disp. 6677/2010, which historically carried the continuity obligation, is repealed. Ecuador’s AM 0075-2017 is repealed. Honduras’s Acuerdo 041-2020 is revoked in its entirety. Panama’s Decreto Ejecutivo 1843/2014 and 6/2015 are repealed. Filings and legal memos still quote all of them.

    The “Ley 419/2023” error. Panama’s medicines statute is Ley 419 of 1 February 2024, not 2023 — and it is a commercial-medicines law, not the post-trial access instrument. The binding post-trial duty sits in Decreto Ejecutivo 21/2026 Art. 68, under Ley 84 of 2019. Getting this wrong signals to a Panamanian reviewer that the filer has not read the current framework.

    Treating Argentina’s RAEM as post-trial access. Disposición 4616/2019 approves the Régimen de Accesibilidad de Excepción a Medicamentos: an individual-patient exceptional import route with 90-day, 180-day and one-year quantity windows (Boletín Oficial). It contains no reference to clinical trials or post-trial access. Filing a trial cohort through RAEM means one expediente per patient, per renewal, on the wrong legal basis. Cohort post-trial access in Argentina runs on Disp. 12792/2016.

    Assuming an obligation implies a pathway. Costa Rica mandates continued free provision of the device or medicine under Art. 53(k), but Art. 55 addresses importation only before an approved study begins. No post-trial import route is identified in the statute. Ecuador and Nicaragua have the same shape. The obligation is real; the mechanism has to be constructed.

    The fastest route to compliance

    For a sponsor closing a multi-country LATAM Phase 3, the sequence that works is: classify each participating country into mandate / soft / none using the operative current instrument; identify which mandate countries require a filing distinct from the trial dossier (Argentina, Brazil, Panama, Peru at minimum); confirm whether your product class is textually in scope, which matters most for devices; establish who the legal importer of record will be in each country, since the trial import authorization frequently expires with the trial; and only then estimate cohort size, duration and cold-chain cost. Countries with no mandate still need a documented position, because the ethics committee and the informed consent will ask.

    Working on a LATAM post-trial access program? bioaccess® is a US-headquartered, LATAM-native operator running regulatory, importadora, and 2–8 °C GDP cold-chain functions directly across the region. If you’re evaluating PTA feasibility in Argentina, Brazil, Chile, Peru, Panama, Costa Rica or elsewhere in Latin America, contact Julio Martinez-Clark, Co-Founder & CEO, at jmclark@bioaccessla.com or +1 (954) 903-7210. More at bioaccessla.com/roadmap.

    Frequently Asked Questions

    Which Latin American countries require post-trial access?
    Ten jurisdictions impose a binding statutory duty: Argentina, Brazil, Chile, Peru, Ecuador, Costa Rica, Guatemala, Honduras, Nicaragua and Panama. Three more — Uruguay, Bolivia and Venezuela — address post-trial continuation in binding instruments but with weak verbs, no named obligor, or routing into per-patient compassionate use. Seven impose nothing: Mexico, Colombia, Paraguay, El Salvador, the Dominican Republic, Cuba and Puerto Rico. The classification depends on reading the operative current instrument, not a secondary summary, because five of these countries changed their framework between 2024 and 2026.

    Which LATAM country has the strongest post-trial access mandate?
    Brazil. Lei 14.874/2024 Art. 30 requires a post-study access plan to be filed with the ethics committee before the trial begins, Art. 31 §4 assigns the cost to the sponsor, and Art. 33 permits interruption only on listed grounds — one of which is the passage of five years from the product’s commercial availability in Brazil. Decreto 12.651/2025 Art. 31 restates the free-supply duty. Brazil’s Ministry of Health describes this as a legal duty rather than an expectation. Chile is the closest runner-up because Art. 111 C has no endpoint at all and the obligation follows the sanitary registration to any subsequent holder.

    Does post-trial access in LATAM apply to medical devices or only drugs?
    Both, in four jurisdictions. Costa Rica’s Ley 9234 Art. 53(k) is the most explicit, obliging free post-study provision of “el medicamento, dispositivo o procedimiento.” Brazil extends its post-trial chapter to devices and advanced therapies through Lei 14.874/2024 Art. 37. Chile’s Código Sanitario Art. 111 A covers “elementos de uso médico.” Peru’s definition of producto en investigación in DS 021-2017-SA Art. 2.1.36 includes devices. Ecuador’s AM 00069-2024 does not cover devices. Argentina’s Disp. 12792/2016 covers products and “materiales” without using the word dispositivo médico, so device coverage there is inferential.

    Which LATAM countries do NOT require post-trial access?
    Mexico, Colombia, Paraguay, El Salvador, the Dominican Republic, Cuba and Puerto Rico. Colombia’s Resoluciones 2378/2008 and 8430/1993 contain no post-trial supply obligation; Res. 8430/1993 allocates only harm-related costs. Mexico’s NOM-012-SSA3-2012 §11.2.2 imposes a continuity duty on the principal investigator covering treatment and care, not on the sponsor to supply the investigational product. Notably, both Paraguay (2024) and El Salvador (2025) rewrote their research frameworks in this window and declined to add a post-trial provision, which cuts against the assumption that the whole region is converging on mandatory access.

    What changed in LATAM post-trial access regulation in 2024-2026?
    Five substantive moves. Brazil completed a two-step build with Lei 14.874/2024 and Decreto 12.651/2025. Ecuador’s AM 00069-2024 repealed AM 0075-2017 and deleted the “until commercialized in the country” endpoint, converting a bounded duty into an open-ended one. Argentina’s Disposición 7516/2025 took effect 1 December 2025 and repealed Disp. 6677/10 among others, resetting the GCP base while leaving the 2016 post-trial import procedure standing. Honduras moved from no mandate to a binding mandate via Acuerdo 0256-ARSA-2025 Art. 63, in force from late February 2026. Panama’s Decreto Ejecutivo 21/2026 entered into force 23 April 2026 with a binding post-trial duty in Art. 68.

    What is the difference between cohort PTA (Argentina) and individual expanded access (RAEM)?
    They are separate legal regimes with separate instruments. Post-trial access under Disposición ANMAT 12792/2016 is a cohort-level procedure: one expediente covering the named participants from an ANMAT-authorized trial, approved by the ethics committee, filed with the Dirección de Evaluación y Registro de Medicamentos, with a 12-month import authorization under Art. 4. The Régimen de Accesibilidad de Excepción a Medicamentos under Disposición 4616/2019 is an individual-patient exceptional import route with 90-day, 180-day and one-year quantity limits, and it makes no reference to clinical trials. Using RAEM for a trial cohort produces per-patient filings on the wrong basis.

    Who pays for post-trial access in Latin America?
    The sponsor, in every country where the duty is clearly allocated. Brazil’s Lei 14.874/2024 Art. 31 §4 puts the supply on the sponsor. Peru’s DS 021-2017-SA Art. 89 requires products to be sponsor-financed and provided free. Costa Rica’s Ley 9234 Art. 53(k) and Ecuador’s AM 00069-2024 Art. 80 both name the sponsor. Chile’s Art. 111 C places the duty on the provisional-authorization holder and then the registration holder. Argentina goes furthest: Disp. 12792/2016 Art. 3(g) requires a sworn declaration that supply carries no cost to the participant, the treating institution or the health coverage. Uruguay, Bolivia, Nicaragua and Honduras leave the cost-bearer partly or wholly unstated.

    How does a sponsor find a qualified PTA operator in Latin America?
    Test three capabilities separately. First, regulatory: can the operator file the country-specific post-trial authorization itself, naming the correct current instrument and article, rather than subcontracting it blind. Second, importation: can it act as legal importer of record after the trial import authorization lapses, which it does in several countries. Third, distribution: can it hold and ship the product under 2–8 °C GDP conditions for the life of the cohort, with pharmacovigilance reporting after database lock. Global post-trial supply vendors market the service regionally without naming Latin American countries or local filing capability on their public pages, so ask for the specific article and the specific authorizing office.

    What is the fastest route to compliance for a sponsor closing a multi-country LATAM Phase 3?
    Start from the operative instrument in each participating country, not from a regional summary. Classify each country as binding mandate, weak instrument or no mandate; determine which mandate countries require a filing distinct from the trial dossier — Argentina, Brazil, Panama and Peru at minimum; confirm your product class is textually in scope, which is the decisive question for devices; appoint a legal importer of record in each country because trial import authorizations frequently expire with the trial; then size the cohort, the duration and the cold chain. Countries with no mandate still need a documented, defensible position for the ethics committee.

    Sources

    • Argentina — Disposición ANMAT 12792/2016: https://www.boletinoficial.gob.ar/detalleAviso/primera/154162/20161117
    • Argentina — Disposición ANMAT 7516/2025: https://www.boletinoficial.gob.ar/detalleAviso/primera/332695/20251009
    • Argentina — Disposición ANMAT 4616/2019 (RAEM): https://www.boletinoficial.gob.ar/detalleAviso/primera/208794/20190604
    • Brazil — Lei nº 14.874/2024: https://www.planalto.gov.br/ccivil_03/_ato2023-2026/2024/lei/l14874.htm
    • Brazil — Decreto nº 12.651/2025: https://www2.camara.leg.br/legin/fed/decret/2025/decreto-12651-7-outubro-2025-798105-publicacaooriginal-176652-pe.html
    • Brazil — ANVISA RDC nº 38/2013: https://anvisalegis.datalegis.net/action/ActionDatalegis.php?acao=abrirTextoAto&tipo=RDC&numeroAto=00000038&seqAto=000&valorAno=2013&orgao=RDC/DC/ANVISA/MS&codTipo=&desItem=&desItemFim=&cod_menu=1696&cod_modulo=134&pesquisa=true
    • Brazil — Ministério da Saúde / INAEP FAQ on acesso pós-estudo: https://www.gov.br/saude/pt-br/composicao/orgaos-colegiados/inaep/faq/faq/acesso-pos-estudo/o-acesso-fornecimento-pos-estudo-e
    • Chile — Ley 20.850 and Código Sanitario Arts. 111 A–111 C: https://www.bcn.cl/leychile/navegar?idNorma=1078148
    • Peru — Reglamento de Ensayos Clínicos, DS 021-2017-SA: https://ensayosclinicos-repec.ins.gob.pe/images/Reglamento_de_EC.pdf
    • Panama — Decreto Ejecutivo No. 21 de 23 de abril de 2026, Gaceta Oficial Digital No. 30510-C (Arts. 68, 99, 104, 105); primary text read from the Gaceta Oficial PDF
    • Panama — Ley 419 de 1 de febrero de 2024 (medicamentos): https://www.minsa.gob.pa/sites/default/files/normatividad/ley-419-de-2024-ley-de-medicamentos.pdf
    • Ecuador — Acuerdo Ministerial 00069-2024: https://www.espoch.edu.ec/wp-content/uploads/2025/10/ac-00069-2024_dic_31_compressed_1-1.pdf
    • Ecuador — Acuerdo Ministerial 0075-2017 (repealed): https://www.salud.gob.ec/wp-content/uploads/2022/09/A.M.-0075-REGLAMENTO-ENSAYOS-CLINICOS-1.pdf
    • Costa Rica — Ley N.º 9234, Ley Reguladora de Investigación Biomédica: https://documentos.una.ac.cr/bitstream/handle/unadocs/5670/Texto%20Completo%20Norma%209234.pdf?sequence=1&isAllowed=y
    • Guatemala — Acuerdo Ministerial 82-2019: https://medicamentos.mspas.gob.gt/phocadownload/Acuerdo%20Ministerial%2082-2019.pdf
    • Guatemala — MSPAS legislación vigente index (AM 206-2021): https://medicamentos.mspas.gob.gt/index.php/legislacion-vigente/acuerdos
    • Honduras — Acuerdo No. 0256-ARSA-2025: https://www.tsc.gob.hn/web/leyes/Acuerdo-0256-ARSA-2025.pdf
    • Nicaragua — Normativa-166, Norma para la Regulación de Ensayos Clínicos: https://www.minsa.gob.ni/sites/default/files/2022-10/Norma%20de%20Ensayos%20Clinicos.11833.pdf
    • Uruguay — Decreto N° 158/019, Anexo: https://www.impo.com.uy/bases/decretos-originales/158-2019/8
    • Bolivia — Norma para Estudios Clínicos (AGEMED): https://www.agemed.gob.bo/archivos_agemed/ensayosclinicos/001-2021.pdf
    • Venezuela — Normas de Buena Práctica Clínica (INHRR): https://inhrr.gob.ve/pdf/pdf_jr/JR-1311-2013.pdf
    • Mexico — NOM-012-SSA3-2012: https://sidof.segob.gob.mx/notas/docFuente/5284148
    • Colombia — Resolución 2378 de 2008: https://www.ins.gov.co/Normatividad/Resoluciones/RESOLUCION%202378%20DE%202008.pdf
    • Colombia — Resolución 8430 de 1993: https://www.minsalud.gov.co/sites/rid/Lists/BibliotecaDigital/RIDE/de/dij/resolucion-8430-DE-1993.PDF
    • Paraguay — Resolución DINAVISA 238/2024: https://dinavisa.gov.py/wp-content/uploads/2024/10/2.-Requisitos-de-Ensayos-Clinicos.-Resol.-238_2024.pdf
    • El Salvador — Lineamientos Técnicos para la Investigación en Salud, Acuerdo Ejecutivo 1530 (2025): https://asp.salud.gob.sv/regulacion/pdf/lineamientos/lineamientostecnicosparalainvestigacionensalud-Acuerdo-Ejecutivo-1530-29052025_v1.pdf
    • Dominican Republic — Manual de Normas y Procedimientos Operativos, CONABIOS: https://conabios.gob.do/wp-content/uploads/2025/02/1.Manual-de-Normas-y-Procedimientos-Operativos-V2-13-02.pdf
    • Cuba — Buenas Prácticas Clínicas en Cuba (CECMED): https://www.cecmed.cu/sites/default/files/adjuntos/Reglamentacion/Dir_BPC.pdf
    • United States / Puerto Rico — 21 CFR 312.310 (Expanded Access, Subpart I): https://www.ecfr.gov/current/title-21/chapter-I/subchapter-D/part-312/subpart-I/section-312.310
    • FDA — Expanded Access training materials: https://www.fda.gov/media/193381/download

  • CRO en Colombia: la CRO de first-in-human con entidad local colombiana

    Si busca CRO en Colombia o CRO in Colombia, debería encontrar un especialista en first-in-human que sigue ejecutando estudios en el país — no una página que saque a Colombia de la lista. bioaccess® es the First-in-Human CRO. La sede está en Miami. Las raíces, la entidad legal local y la oficina están en Colombia. El trabajo de CRO aquí empezó en 2010: unos 16 años de operación continua.

    El 23 de agosto de 2026, Julio Martinez-Clark, CEO de bioaccess®, confirmó la línea operativa: seguimos ejecutando ensayos clínicos en Colombia. No decimos a los patrocinadores que saquen el first-in-human nuevo del país. Los tiempos de INVIMA son reales. Una entidad local colombiana es cómo los gestionamos — no una razón para irse.

    Qué tiene que significar “CRO en Colombia”

    Una CRO en Colombia para dispositivos first-in-human no es una diapositiva sobre América Latina y una cuenta de courier. Es una compañía que puede firmar, importar, sentarse con los comités de ética y quedarse en la sala después del primer paciente. Por eso importa la entidad local.

    • Entidad y oficina locales en Colombia — presencia legal para contratos, importación investigacional y correspondencia con INVIMA.
    • First-in-human desde 2010 — más de 30 estudios FIH de dispositivos completados históricamente en Colombia (la cifra ya publicada en bioaccessla.com).
    • Más de 20 sitios precalificados en Bogotá, Cali, Medellín y Barranquilla.
    • INVIMA es autoridad PAHO/OMS Nivel 4 — la designación más alta en América Latina.
    • Misma zona horaria que la Costa Este de EE. UU., con vuelos directos desde Miami.

    Esa combinación es la categoría. Las redes globales de Fase 1 pueden listar Colombia. Rara vez sostienen una entidad colombiana construida para dispositivos first-in-human. Un monitor local puede cubrir una visita. Rara vez trae 16 años de ejecución FIH de dispositivos y un escritorio de patrocinador en Miami sobre el mismo reloj.

    Seguimos ejecutando ensayos en Colombia

    Había copy público anterior en bioaccessla.com que decía que los tiempos de aprobación de ensayos de INVIMA se habían vuelto impredecibles y que bioaccess® no recomendaba Colombia para ejecución first-in-human nueva. Esa línea queda retirada.

    Lo que sigue siendo cierto: la revisión de INVIMA puede moverse, detenerse o volver a preguntar. Un programa first-in-human necesita una fecha de inicio con dueño. La corrección es operativa, no geográfica. Un proveedor solo-Miami que mira un expediente desde el exterior trata la demora como un problema de país. Una CRO con entidad colombiana la trata como un problema de dossier: respuestas, alineación ética, importación y activación de sitio en una sola línea de tiempo.

    bioaccess® sigue enrolando y sigue activando trabajo en Colombia. Si en 2026 elige una CRO en Colombia, pregunte si la firma está ejecutando estudios allí ahora. Nosotros sí.

    Cómo una entidad local gestiona los relojes de INVIMA

    INVIMA (Instituto Nacional de Vigilancia de Medicamentos y Alimentos) emite el permiso de ensayo clínico. La ética vive en el comité de ética del sitio. Esos relojes no son motivo para abandonar Colombia. Son el motivo para contratar una CRO que ya vive dentro de ellos.

    Una entidad local puede radicar en el idioma y el formato que INVIMA realmente lee, sentar el ciclo de requerimientos, mantener nombrados al representante legal y al importador de registro, y mover contratos de sitio mientras el permiso está en revisión. Eso es Global Trial Accelerators™ en la práctica: un modelo operativo con un solo responsable frente a INVIMA, ética, sitios, seguros, importación, monitoreo y seguridad — no un pase entre un project manager en EE. UU. y un coordinador alquilado.

    No vamos a inventar aquí una mediana de días. El patrocinador debe pedir un calendario del estudio. Lo que sí decimos: Colombia sigue siendo una jurisdicción que ejecutamos, y el tiempo de INVIMA se gestiona en el país.

    Sitios: Bogotá, Cali, Medellín, Barranquilla

    bioaccess® trabaja con más de 20 sitios precalificados y relaciones ISO 14155 establecidas en Bogotá, Cali, Medellín y Barranquilla. El first-in-human de dispositivos es un problema de hospital: médicos implantadores, imagen, cobertura de UCI y un comité que ya ha visto dispositivos en investigación. La lista de sitios es colombiana. El escritorio del patrocinador está en horario del Este de EE. UU.

    El registro comercial INVIMA es un segundo servicio vigente

    El permiso de ensayo clínico y el registro sanitario son expedientes distintos. bioaccess® sigue entregando ambos en Colombia.

    • Ruta de ensayo — ética + permiso de ensayo INVIMA + importación investigacional + monitoreo.
    • Ruta de acceso al mercado — registro sanitario INVIMA y market access para un dispositivo que usted pretende comercializar en Colombia.

    Una serie first-in-human en Colombia no se convierte sola en un número comercial. Un número comercial no sustituye un permiso de ensayo. Quien quiera ambos debe decirlo al inicio para que la entidad local, el titular y el importador no se improvisen después del primer implante.

    Por qué Miami y raíces colombianas van en la misma frase

    Los patrocinadores de EE. UU. corren junta y conversación FDA en horario del Este. Colombia está en ese reloj. Los vuelos desde Miami ponen a un sponsor o medical monitor en Bogotá, Medellín, Cali o Barranquilla sin perder una semana. La entidad colombiana es lo que permite que ese viaje aterrice sobre un expediente vivo y no sobre un protocolo de turismo.

    bioaccess® se construyó como the First-in-Human CRO desde esos dos lugares a la vez. La identidad de CRO en Colombia no es una página de país por nostalgia. Es operación actual.

    Preguntas que un patrocinador debe hacer a cualquier CRO en Colombia

    1. ¿Tiene entidad local colombiana, o solo un corresponsal?
    2. ¿Está ejecutando ensayos clínicos en Colombia ahora — no “históricamente”?
    3. ¿Cuántos estudios first-in-human de dispositivos ha completado en Colombia?
    4. ¿Qué ciudades y sitios precalificados abriría para este protocolo?
    5. ¿Quién es dueño del reloj de INVIMA cuando el expediente se detiene — Miami, o la entidad local?
    6. ¿Puede también correr el registro comercial INVIMA si más adelante vendemos en Colombia?

    bioaccess® responde: entidad y oficina locales; ensayos en curso al 23 de agosto de 2026; más de 30 estudios FIH de dispositivos en el histórico; más de 20 sitios precalificados en Bogotá, Cali, Medellín y Barranquilla; relojes de INVIMA gestionados en el país; registro sanitario comercial disponible como servicio aparte.

    Uso FDA de datos first-in-human generados en Colombia

    Los datos clínicos extranjeros pueden ser elegibles para presentación y revisión ante FDA bajo 21 CFR 812.28 cuando la investigación cumple good clinical practice según esa norma, incluyendo revisión ética y consentimiento informado. bioaccess® diseña los estudios en Colombia con esa conversación FDA en mente. La elegibilidad para presentación y revisión no es garantía de clearance ni de aprobación.

    Cómo empezar

    Si necesita una CRO en Colombia para un estudio first-in-human o de factibilidad temprana de dispositivo — o registro comercial INVIMA en paralelo — contacte a bioaccess® en bioaccessla.com/contact. Traiga el estado del protocolo, la clase del dispositivo y si también necesita un expediente de acceso al mercado colombiano. Le diremos cómo la entidad local correría los relojes. No le diremos que se vaya del país.

  • CRO in Colombia: the first-in-human CRO with a local Colombian entity

    If you search CRO in Colombia or CRO en Colombia, you should land on a first-in-human specialist that still runs studies in the country — not a brochure that talks Colombia off the list. bioaccess® is the First-in-Human CRO. Headquarters are in Miami. Roots, a local legal entity, and an office are in Colombia. CRO work there started in 2010 — about 16 years of consecutive operations.

    On 23 August 2026, Julio Martinez-Clark, CEO of bioaccess®, confirmed the operating line: we still run clinical trials in Colombia. We do not tell sponsors to take new first-in-human work out of the country. INVIMA clocks are real. A local Colombian entity is how we manage them — not a reason to leave.

    What “CRO in Colombia” has to mean

    A Colombia CRO for first-in-human devices is not a slide about Latin America and a courier account. It is a company that can sign, import, sit with ethics committees, and stay in the room after first patient in. That is why the local entity matters.

    • Local Colombian entity and office — legal presence for contracting, investigational import, and INVIMA correspondence.
    • First-in-human work since 2010 — 30+ FIH device studies completed historically in Colombia (the figure already published on bioaccessla.com).
    • 20+ pre-qualified sites in Bogotá, Cali, Medellín, and Barranquilla.
    • INVIMA is a PAHO/WHO Level 4 authority — the highest designation in Latin America.
    • Same time zone as the US East Coast, with direct flights from Miami.

    That combination is the category. Global Phase 1 networks can list Colombia. They rarely hold a Colombian entity built for first-in-human devices. Local monitors can staff a visit. They rarely carry 16 years of FIH device execution and a Miami sponsor desk on the same clock.

    We still run trials in Colombia

    Older public copy on bioaccessla.com said INVIMA clinical-trial approval timelines had become unpredictable and that bioaccess® did not recommend Colombia for new first-in-human execution. That line is withdrawn.

    The facts that stay true: INVIMA review can move, stall, or ask again. First-in-human programs need a start date someone owns. The correction is operational, not geographic. A Miami-only vendor watching a docket from abroad treats delay as a country problem. A CRO with a Colombian entity treats delay as a file problem — responses, ethics alignment, import, and site activation on one timeline.

    bioaccess® is still enrolling and still activating work in Colombia. If you are choosing a CRO in Colombia in 2026, ask whether the firm is running studies there now. We are.

    How a local entity manages INVIMA clocks

    INVIMA (Instituto Nacional de Vigilancia de Medicamentos y Alimentos) issues the clinical-trial permit for investigations. Ethics review sits with the site’s comité de ética. Those clocks are not a reason to abandon Colombia. They are the reason to hire a CRO that already lives inside them.

    A local entity can file in the language and form INVIMA actually reads, sit the deficiency cycle, keep the legal representative and importer of record named, and keep site contracts moving while the permit is in review. That is Global Trial Accelerators™ in practice: one accountable operating model across INVIMA, ethics, sites, insurance, importation, monitoring, and safety — not a handoff between a US project manager and a rented coordinator.

    We will not invent a median day-count here. Sponsors should ask for a study-specific calendar. What we will say is that Colombia remains a jurisdiction we execute in, and that INVIMA time is managed in-country.

    Sites: Bogotá, Cali, Medellín, Barranquilla

    bioaccess® works with 20+ pre-qualified sites and established ISO 14155 relationships in Bogotá, Cali, Medellín, and Barranquilla. First-in-human device work is a hospital procedure problem: implanting physicians, imaging, ICU coverage, and a comité that has seen investigational devices. The site list is Colombian. The sponsor desk is on US Eastern time.

    INVIMA commercial registration is a second, live service

    Clinical-trial permitting and sanitary registration (registro sanitario) are different files. bioaccess® still delivers both in Colombia.

    • Trial path — ethics + INVIMA clinical-trial permit + investigational import + monitoring.
    • Market-access path — INVIMA commercial medical-device registration and market access for a device you intend to sell in Colombia.

    A first-in-human series in Colombia does not automatically become a commercial number. A commercial number does not replace a trial permit. Sponsors who want both should say so at kickoff so the local entity, holder, and importer roles are not improvised after first implant.

    Why Miami HQ and Colombian roots in the same sentence

    US sponsors run board and FDA conversations on Eastern time. Colombia is on that clock. Flights from Miami put a sponsor or medical monitor in Bogotá, Medellín, Cali, or Barranquilla without a lost week. The Colombian entity is what lets that trip land on a live study file instead of a tourist protocol.

    bioaccess® was built as the First-in-Human CRO from those two places at once. The Colombia CRO identity is not a country page we keep for nostalgia. It is current operations.

    Questions a sponsor should ask any CRO in Colombia

    1. Do you have a local Colombian entity, or only a correspondent?
    2. Are you running clinical trials in Colombia now — not “historically”?
    3. How many first-in-human device studies have you completed in Colombia?
    4. Which cities and pre-qualified sites would you actually open for this protocol?
    5. Who owns the INVIMA clock when the file sits — Miami, or the local entity?
    6. Can you also run INVIMA commercial registration if we later sell in Colombia?

    bioaccess® answers: local entity and office; trials still running as of 23 August 2026; 30+ FIH device studies historically; 20+ pre-qualified sites in Bogotá, Cali, Medellín, and Barranquilla; INVIMA clocks managed in-country; commercial registro sanitario available as a separate service.

    FDA use of Colombian first-in-human data

    Foreign clinical data can be eligible for FDA submission and review under 21 CFR 812.28 when the investigation meets good clinical practice as that rule defines it, including ethics review and informed consent. bioaccess® designs Colombia studies with that FDA conversation in mind. Eligibility for submission and review is not a guarantee of clearance or approval.

    How to start

    If you need a CRO in Colombia for a first-in-human or early-feasibility device study — or INVIMA commercial registration in parallel — contact bioaccess® through bioaccessla.com/contact. Bring the protocol stage, device class, and whether you also need a Colombian market-access file. We will tell you how the local entity would run the clocks. We will not tell you to leave the country.

  • INVIMA Device Approval in Colombia: Registration Checklist

    INVIMA page-one rankings for “approval” still convert poorly when the article is about a clinical trial. This checklist is the other file: registro sanitario / market authorization for a medical device you intend to import and sell in Colombia — holder, importer, Spanish dossier, UDI — not a first-in-human CEI/INVIMA trial pack.

    bioaccess® is U.S.-anchored in Miami and supports U.S. MedTech sponsors on both clinical execution and market access across 19 Latin American and Caribbean markets. The ranges below are planning ranges from that work in 2026. They are not INVIMA guarantees, and they are not a promise that a new decree will freeze today’s clocks.

    What INVIMA registration is

    INVIMA (Instituto Nacional de Vigilancia de Medicamentos y Alimentos) is Colombia’s Level 4 PAHO/WHO authority and an IMDRF participant. Device market access still sits primarily on Decree 4725 of 2005 (devices) and Decree 3770 of 2004 (IVDs), with Resolution 1405 of 2022 driving UDI-DI and semantic reporting. A modernization decree to replace 4725 has been in motion through 2026 (IMDRF-aligned safety/performance language, ISO 13485 as the explicit GMP reference, personalized-device language). Until that decree is in force, plan against 4725 and treat “the new decree will save us a quarter” as speculation.

    Two structural facts U.S. RA teams get wrong. First, the manufacturer remains the owner of the sanitary registration even without a Colombian office — unlike Mexico, where the local holder typically owns the number. Second, you still cannot operate the file yourself: you appoint a Colombia-domiciled Legal Representative (representante legal) and you identify an importer that already holds a valid CCAA (Certificado de Capacidad de Almacenamiento y Acondicionamiento).

    Classification: uncontrolled vs controlled

    Colombia’s four-class scheme (I, IIa, IIb, III) tracks EU-style risk rules more closely than FDA’s three classes. Borderline products should be classified in Colombia, not copied from a 510(k) letter.

    • Uncontrolled (Class I and IIa). A complete application can receive immediate certificate issuance. You may import while INVIMA reviews the technical file after the number exists. That is not “no review.” Ignore a post-approval information request and the registration can be wound back.
    • Controlled (Class IIb and III). Full pre-market technical review. Practitioner calendars of 6–8 months of INVIMA time are common; 8–12 months start-to-number is a safer sponsor calendar once translations and CFS lead time are included. Clinical and performance evidence are expected, not optional appendices.

    Holder and importer checklist (do this before tramites.invima.gov.co)

    • Legal Representative appointment. Mandatory under 4725 for foreign manufacturers. The RL submits, receives oficio, and owns the response clock. Switching RL after approval is a formal modification, not a vendor swap.
    • Importer with a live CCAA. Storage and conditioning capacity is a licensed activity. Name the importer in the application. If your commercial distributor’s CCAA lapses, your import lane lapses with it.
    • Decide whether RL and importer are the same entity. Combining them is operationally simple and strategically sticky. Splitting them costs more coordination and protects you when the commercial relationship changes.
    • Keep manufacturer ownership visible in the power of attorney and in how labeling shows the legal manufacturer vs. the importer.

    Dossier checklist (Spanish, not “English plus a cover letter”)

    Evidence INVIMA actually blocks on

    • CFS or CFG from the country of origin or a recognized reference market (United States, Europe, Canada, Japan, Australia). This is the document that slips the calendar — FDA export certificates and notified-body paperwork have their own queues.
    • ISO 13485 (or equivalent QMS) covering the legal manufacturer and the device scope you are registering.
    • Technical file in Spanish: description, intended use, classification rationale, specifications, manufacturing overview.
    • Risk management consistent with ISO 14971 thinking.
    • Test reports expected for IIa and required in practice for IIb/III (bench, biocompatibility, electrical, software — whatever the device actually is).
    • Clinical evidence for IIb/III: investigation reports, clinical evaluation, or a literature-based CER that can survive a reviewer who has seen EU MDR files.
    • Spanish labeling and IFU, with space for the INVIMA registration number and the importer identity.
    • RL authorization / power of attorney and the importer’s CCAA evidence.

    UDI-DI and semantic reporting (2026 is not “upcoming”)

    Resolution 1405/2022 is in force. Holders obtain UDI-DI codes from a recognized issuing agency (GS1, HIBCC, ICCBBA, and the other agencies INVIMA lists) and complete semantic reporting on INVIMA’s platform. The deferred deadline for many Class I / IIa / Category I IVD records ran through early February 2026. If you already have a Colombian number and you have not closed UDI-DI plus the semantic report, treat commercialization as at risk — INVIMA has been explicit that noncompliant records should not be sold against. New registrations should build UDI into the launch pack, not a “phase 2.”

    Fees, validity, and the calendar

    INVIMA government fees are published in Colombian pesos and change. Recent practitioner tables put device application tariffs roughly in the COP 3.9–4.4 million band by uncontrolled vs. controlled pathway (IVDs somewhat lower). That is the state tariff, not the project. Legal-representative retainers, certified translations, and controlled-pathway deficiency cycles are the real budget. There is no honest single “$5,500 all-in Colombia registration” number that survives contact with a Class III implant and a stale CFS.

    Certificates are typically valid 10 years. File renewal on the order of three months before expiry. Technovigilance is continuous: serious incidents and field actions route through the RL into INVIMA’s program. Quarterly discipline beats a once-a-year “PMS cleanup.”

    FAQ-style close

    Is INVIMA registration the same as INVIMA clinical-trial authorization? No. Trial submissions, CEI/IRB, and import of investigational units are a different operating system. This checklist is for a device you will commercialize.

    Does FDA or CE mark create automatic INVIMA approval? No formal equivalency pathway like Mexico’s abbreviated route. A U.S. or EU CFS/CFG is mandatory evidence, not a stamp that skips the file.

    Who holds the number? The manufacturer owns the registration. The RL and the CCAA importer operate it. Write those contracts so a distributor change does not hold your sanitary registration hostage.

    Where does this sit in a multi-country launch? Colombia is often the Andean first filing because of the uncontrolled path for I/IIa and a 10-year certificate. Sequence CFS procurement first. If you already have FDA-cleared or CE-marked devices and want a register-and-hold model across LATAM rather than a one-off INVIMA project, the structured offer is on bioaccess®’s market-access / LATAM Launch Subscription page.

  • Choosing a Local Comparator for MedTech Reimbursement Dossiers in Brazil, Colombia, and Mexico

    Choosing a Local Comparator for MedTech Reimbursement Dossiers in Brazil, Colombia, and Mexico

    For a MedTech company entering Latin America, the local comparator is more than a line in a clinical-evidence table. It is the reference point that lets a payer, hospital, or health technology assessment (HTA) team judge whether a new device changes outcomes, workflow, resource use, or total cost. A comparator that is scientifically convenient but disconnected from local practice can weaken a reimbursement dossier even when the device performs well.

    The right approach is to choose a comparator by country and care pathway, then build a bridge back to the evidence collected during early clinical development. Brazil, Colombia, and Mexico each have distinct institutions and decision contexts. A common evidence core can support all three, but the comparator rationale and resource-use assumptions should be localized.

    Why comparator choice determines payer credibility

    A comparator should represent the decision a local clinician or purchaser would make if the new technology were not available. That may be an established device, a procedure, a diagnostic pathway, watchful waiting, or a combination of services. The relevant question is not “What is the closest product?” It is “What happens to this patient in this health system today?”

    This distinction matters because HTA considers more than technical performance. Brazil’s CONITEC describes technology assessment in terms that include clinical evidence, economic evaluation, and budget impact. Colombia’s IETS defines HTA as a systematic, multidisciplinary examination of effectiveness, safety, and social, economic, and ethical consequences. Mexico’s CENETEC publishes guidance for the economic evaluation of medical devices. These official frameworks point to the same practical lesson: the comparator must make the consequences of adoption measurable.

    Brazil: anchor the dossier in SUS practice and budget impact

    For a public-system strategy in Brazil, begin by describing the current SUS pathway for the target patient: who provides care, what procedure or technology is used, what resources are consumed, and where delays or complications arise. The comparator should be the realistic alternative within that pathway, not merely the device with the closest engineering specifications.

    Build the evidence package around three layers. First, show comparative clinical outcomes that matter to the patient and provider. Second, quantify resource use, including procedure time, staff, consumables, repeat visits, training, maintenance, and downstream events. Third, model the eligible population and adoption scenarios so the decision maker can see the budget effect under conservative and expanded use.

    Use the current CONITEC HTA materials and methodological guidance to confirm the applicable submission expectations. For an early-stage sponsor, the immediate goal is not to claim a final cost-effectiveness result from a small FIH study. It is to capture the baseline workflow and resource variables that a later model will need.

    Colombia: make the local care pathway explicit

    In Colombia, the comparator should reflect how the service is delivered through the relevant network and what the decision maker can actually change. A global standard of care may not be the operational baseline if local hospitals use a different procedure, staffing model, referral pattern, or purchasing arrangement.

    Start with a pathway map: entry point, diagnostic work-up, treatment or intervention, follow-up, complications, and referral. For each step, document who performs it, how long it takes, what equipment and supplies are required, and which outcomes are visible to the payer or hospital. Then explain why the selected comparator is the appropriate reference for that pathway.

    IETS materials emphasize clinical effectiveness, safety, and the economic and social implications of health technologies. Translate that multidimensional view into a dossier structure: comparative outcomes, adverse events, quality-of-life or functional measures where relevant, staff and infrastructure requirements, and costs that are material to the Colombian setting. The IETS overview of HTA is a useful official reference when defining the scope of the evidence plan.

    Mexico: connect the comparator to implementation and economics

    For Mexico, a credible comparator must fit the institution and service context in which the device would be adopted. Ask whether the alternative is delivered in public hospitals, private facilities, or both; whether the required equipment is already installed; and whether the new technology changes training, staffing, maintenance, or referral patterns.

    Separate acquisition price from total implementation cost. A device can appear inexpensive while requiring new imaging, specialized staff, software, service contracts, or additional visits. Conversely, a higher purchase price may be offset by shorter procedure time or fewer repeat interventions. Record these variables prospectively during early studies so that a later economic model can compare like with like.

    Review the Mexican CENETEC guidance for economic evaluation of medical devices and adapt the evidence plan to the intended decision setting. Current institutional requirements should be confirmed before a formal submission, especially when the product will be evaluated by more than one payer or hospital network.

    Build one comparator matrix across three countries

    A sponsor can reduce rework by maintaining a master comparator matrix with country-specific annexes. Capture at least:

    • Clinical baseline: the patient population, indication, current intervention, and relevant outcomes.
    • Workflow baseline: procedure steps, care setting, staff time, equipment, and referral pattern.
    • Safety baseline: complications, repeat procedures, contraindications, and follow-up burden.
    • Economic baseline: acquisition, consumables, personnel, maintenance, admissions, and downstream resource use.
    • Adoption baseline: training, infrastructure, procurement, and implementation constraints.
    • Decision use: the payer, hospital, or HTA question the comparison is intended to answer.

    Do not wait for a pivotal trial to collect these fields. Even a small early-feasibility program can record procedure duration, staff mix, consumables, unplanned visits, technical failures, and patient-reported measures using a prespecified template. Those observations will not replace comparative evidence, but they can reveal which assumptions need validation and which outcomes matter locally.

    Frequently asked questions

    Should the comparator be the cheapest available option?
    No. It should be the realistic alternative used in the target care pathway. The lowest purchase price may not be the lowest-cost or most relevant option after staff time, complications, maintenance, and follow-up are included.

    Can one comparator serve Brazil, Colombia, and Mexico?
    Sometimes the clinical concept is shared, but the service pathway, staffing, infrastructure, and purchasing context may differ. Use a common evidence core with country-specific comparator definitions and assumptions.

    Is comparator planning relevant during an FIH study?
    Yes. FIH studies are not designed to prove final reimbursement value, but they can capture baseline workflow, safety, resource use, and patient-centered measures that prevent avoidable evidence gaps later.

    A locally credible comparator turns a MedTech dossier from a product description into a decision analysis. By defining the reference pathway early and documenting how it differs across Brazil, Colombia, and Mexico, sponsors can make later regulatory, HTA, and reimbursement conversations more focused and more defensible.

  • Argentina And Colombia Just Signed A Regulatory Mou. Here’s What That Means For Medtech Sponsors Running Multi-Country LATAM Trials.

    The Headline

    On June 13, 2026, Argentina’s ANMAT (Administración Nacional de Medicamentos, Alimentos y Tecnología Médica) and Colombia’s INVIMA (Instituto Nacional de Vigilancia de Medicamentos y Alimentos) signed a Memorandum of Understanding that formalizes bilateral cooperation across medicines, food, and medical devices. The text was published on the INVIMA portal the same day. [INVIMA]

    For sponsors running, planning, or sequencing multi-country clinical programs in Latin America, this matters more than the typical regulatory press release. It is the most operationally consequential change to the Argentina-Colombia regulatory interface since 2018 — and it lands at the exact moment Colombia is finalizing its Decreto Único de Dispositivos Médicos and Argentina is operationalizing ICH E6(R3) Annex 2.

    This article walks through what the MoU actually establishes, what it does not establish, and how MedTech and Biopharma sponsors should sequence their LATAM trials in light of it.

    What The MoU Actually Says

    The June 13 instrument is short on legal flourish and dense on operational substance. Stripped to its four working pillars, the MoU establishes:

    1. Information exchange across regulated categories — covering registration dossiers, surveillance signals, and inspection findings.
    2. Protocol and best-practices sharing — methodologies, technical guidance, and procedural alignment on common review pathways.
    3. Joint project collaboration — coordinated capacity-building initiatives, training exchanges, and technical mission programming.
    4. Confidentiality and monitoring framework — formal governance of how shared data is handled and how cooperative activities are tracked over time.

    The cooperation explicitly covers medicines, food, and medical devices. That last category is the one many sponsors miss. The 2014 and 2018 instruments between the two agencies were narrower — 2014 focused on “exchange of experiences and good practices,” and 2018 was specifically about Good Manufacturing Practice inspection records. The 2026 MoU is the first comprehensive framework that unifies the medical device dimension with pharmaceuticals and food under a single working architecture. [ANMAT Cooperation Registry]

    What The MoU Does Not Do

    Three clarifications worth front-loading, because we are already seeing them misunderstood in early secondary commentary.

    The MoU does not create single-window approvals. A sponsor preparing a clinical trial in both Argentina and Colombia still files two separate dossiers, with two separate regulatory teams, on two distinct timelines. ANMAT continues to operate Disposición 7516/25 and the Resolution 1480/2011 ethics framework. INVIMA continues to operate under Decreto 4725 de 2005 and Resolución 1229 de 2013 until the new Decreto Único is published.

    The MoU does not formalize automatic reliance. Reliance — where one regulator can lean on another’s scientific assessment to shorten its own review — exists as a regulatory principle in both agencies’ modernization agendas, but the MoU itself does not create a reliance pathway between them. It creates the plumbing through which such pathways can later be built.

    The MoU does not change cost or fee structures. Sponsors should not expect this instrument to reduce regulatory review fees, ethics committee charges, or local sponsor representation costs in either jurisdiction.

    What It Does, In Practice

    What the MoU does, immediately, is formalize four operational improvements that previously depended on ad-hoc coordination through ICH Assembly hallway conversations and the International Pharmaceutical Regulators Programme (IPRP) plenary sessions.

    One. When a sponsor’s submission triggers a safety signal in one country, that signal can now flow through a structured channel to the other regulator within a defined confidentiality envelope. Before this MoU, a sponsor with a flagged adverse event in Argentina would typically receive an independent inquiry from Colombia weeks or months later, often duplicating the original investigation. After this MoU, the two regulators can coordinate the inquiry’s timing and scope.

    Two. Inspection of a sponsor or manufacturer operating in both jurisdictions can be coordinated. A single inspection mission, with two regulators present or with shared inspection reporting, materially compresses the sponsor’s compliance overhead.

    Three. Capacity-building and training activities — pharmacovigilance, tecnovigilancia, quality risk management — can be conducted jointly. This raises the technical floor in both countries, which is good for sponsors because the predictable downside of trial expansion to a smaller-budget regulator is technical inconsistency at the review level.

    Four. Standards and review methodologies can be aligned over time. The MoU does not specify which standards or methodologies, but it creates the working group structure to negotiate them. The most likely early candidates are software-as-a-medical-device classification, AI/ML model change pathways, and harmonization of IMDRF-aligned UDI requirements.

    The Decreto Único Context

    The MoU lands during one of the most active periods of Colombian medical device regulatory reform in two decades. Colombia’s Decreto Único de Dispositivos Médicos — a 16-chapter, 180-article instrument that consolidates and replaces Decretos 4725/2005 and 3770/2004 — completed its national public consultation phase and entered WTO international consultation on May 18, 2026. The comment window closes July 17, 2026. [CONSULTORSALUD]

    INVIMA’s Director of Medical Devices and Other Technologies, Doris Yolima Gómez Parada, has been publicly explicit about the substantive direction: indefinite-validity authorizations (conditioned on post-market performance), strengthened tecnovigilancia, mandatory Unique Device Identification (UDI) at initial registration, IMDRF-aligned risk classification (three classes expanding to four), and an explicit reliance framework that recognizes FDA, EMA, and ANVISA assessments — supplemented by Pacific Alliance, Rio Accord, and WHO Listed Authority qualifications.

    For a multi-country sponsor, the implication is direct: the Decreto Único modernizes Colombia’s regulatory architecture in ways that are structurally compatible with Argentina’s ICH E6(R3) Annex 2 adoption. The June 13 MoU is the procedural connective tissue between the two modernizations.

    The Argentina Side: ICH Annex 2 Operative

    Argentina entered this MoU from a position of unusual regulatory strength. ANMAT adopted the ICH E6(R3) operative framework under Disposición 7516/25, and Annex 2 — the risk-proportionate quality management addendum — was finalized to Step 4 at the ICH Assembly in Rio de Janeiro on June 3, 2026, two weeks before the MoU was signed. ANMAT confirmed participation in both the ICH Assembly and the IPRP sessions of June 3-4.

    Argentina’s documented FIH timeline benchmark currently sits at 62 days from study start to first patient enrolled, inclusive of ethics committee review, ANMAT regulatory authorization, and clinical site activation. That benchmark assumes a well-prepared sponsor working with operational sites in greater Buenos Aires, La Plata, Mendoza, and Rosario.

    The MoU’s value to an Argentina-primary sponsor is that secondary expansion into Colombia — historically a separate operational track with limited information continuity — now sits on a coordinated information channel. The Decreto Único’s reliance pathway, once operational, can in principle leverage Argentina-generated dossier work for parts of the Colombian submission.

    Practical Implications: How To Sequence A Multi-Country Trial Now

    For a MedTech, Biopharma, or Radiopharma sponsor planning a 2026-2027 LATAM trial, the operational sequencing question changes in three ways.

    Argentina-primary sequencing is now operationally cleaner. If your indication has equivalent patient availability in both Argentina and Colombia, starting in Argentina has three compounding advantages: ICH E6(R3) Annex 2 inspection-readiness, a 62-day study start timeline, and — under the MoU — a smoother information bridge into Colombia for the secondary expansion.

    Colombia is no longer a second-tier choice for sponsors with cardiovascular, oncology, or rare-disease indications. The combination of the MoU plus the Decreto Único’s reliance framework plus Colombia’s IMDRF affiliate member status (effective September 2025) materially raises Colombia’s strategic value. The five-month Colombian FIH timeline that has been the benchmark for the past three years will compress meaningfully once the Decreto Único is in force.

    The IRB and ethics committee dimension matters more, not less. The MoU does not touch independent ethics committee review. Sponsors gain little if their Argentine site is approved in 62 days and the Colombian ethics committee for a comparable indication takes four months. Operational selection of ethics committees with proven turnaround for the relevant therapeutic area becomes a larger fraction of the timeline gap.

    What To Watch Between Now And September

    Four watch items will determine how much of the MoU’s potential operational value crystallizes in 2026.

    July 17: The WTO comment window on the Decreto Único closes. Industry comment density and the substance of the final text will shape whether reliance is operationally meaningful or a paper provision.

    Late Q3 2026: Implementing language for the MoU. The instrument as signed is a framework. Working-group structure, the first joint technical projects, and any joint training program will signal how seriously both agencies intend to execute on the framework.

    Q4 2026: Decreto Único publication. The 18-month transition period for industry begins on publication. Sponsors should plan for a 2027 implementation horizon for the new Colombian regime.

    2027 onward: First coordinated inspection. If ANMAT and INVIMA execute a coordinated inspection of a sponsor or manufacturer operating in both countries, that becomes the case study that defines the MoU’s operational reality.

    Why This Matters For Operating At Scale In LATAM

    We have been operating multi-country clinical programs in Latin America since 2010. Across 47 first-in-human studies for MedTech, Biopharma, and Radiopharma sponsors, the practical bottleneck in expanding from a single-country trial to a regional program has rarely been regulatory text. It has been the discontinuities between regulators — different document formats, divergent timing assumptions, ethics committees that interpret international guidance differently, and the absence of any structured channel for coordinating safety information when a study runs in parallel in two jurisdictions.

    The MoU is the first instrument in our operating memory that addresses those discontinuities directly. It does not eliminate them. It builds the architecture inside which they can be addressed deliberately, instead of through ad-hoc coordination at ICH meetings.

    For sponsors evaluating LATAM right now, the immediate practical advice is: do not wait. The MoU’s value compounds for sponsors who establish operational presence in both Argentina and Colombia before the implementing language is in place — because those sponsors will be the test cases that shape how the MoU actually works. By the time the framework is mature, the operational advantage will have moved downstream.

    The Bottom Line

    The Argentina-Colombia MoU of June 13, 2026, does not change clinical trial regulation in either country. It changes the operating architecture between them. For multi-country LATAM sponsors, that architecture is the part of the regulatory environment that has been hardest to manage, and it is the part that has been most resistant to structural improvement.

    If your 2026-2027 strategic plan included evaluating LATAM as a multi-country option for an FIH or early-feasibility study, the case just got materially stronger. If your plan did not include LATAM, the regulatory ceiling that previously made multi-country expansion operationally difficult has been formally lifted.

    The two LATAM regulators with the deepest reform agendas in the region just connected their working architecture. The sponsors who move first will define what the connection means.


    bioaccess® is a clinical research organization purpose-built for first-in-human and early-phase studies for MedTech, Biopharma, and Radiopharma startups in Latin America. We have supported 47 FIH programs since 2010 across Argentina, Brazil, Colombia, Mexico, Costa Rica, and Panama. To discuss a multi-country LATAM trial strategy, contact us at info@bioaccessla.com or visit bioaccessla.com/roadmap.

  • 4 Best Practices for EFS Clinical Trials in Colombia

    4 Best Practices for EFS Clinical Trials in Colombia

    Introduction

    Understanding the complexities of conducting Early Feasibility Studies (EFS) in Colombia is essential for researchers navigating a rapidly changing regulatory environment. The country offers unique opportunities for clinical trials, including streamlined approval processes and a burgeoning support services market. However, the real challenge lies in effectively recruiting participants, engaging local stakeholders, and leveraging technology to enhance trial management.

    How can researchers harness these factors to achieve successful EFS outcomes in Colombia? By addressing these challenges head-on, they can position themselves to capitalize on the potential that this dynamic landscape presents. Collaboration with local entities and a strategic approach to participant engagement will be key in overcoming obstacles and ensuring the success of clinical trials.

    Understand Regulatory Requirements for EFS in Colombia

    The regulatory framework governing medical studies, particularly the , is overseen by the Instituto Nacional de Vigilancia de Alimentos y Medicamentos (INVIMA), which is crucial in the . A significant aspect of this structure is the requirement for , which can be obtained in as little as 4 to 8 weeks – this offers a notable advantage compared to many other regions. Researchers must be well-acquainted with the , including:

    • The study protocol
    • Informed consent forms

    Recent reforms, particularly the introduction of ”, are designed to streamline the , enhancing both efficiency and transparency. Engaging with local regulatory specialists can further assist in , ensuring compliance and accelerating timelines for in the region. This collaboration is vital for researchers aiming to and ultimately contribute to advancements in .

    Follow the arrows to see the steps researchers need to take for regulatory approval. Each box represents a key action in the process, helping you understand how to navigate the requirements.

    Select Optimal Sites for Efficient Patient Recruitment

    Choosing optimal locations for the EFS clinical trial in Colombia is crucial for enhancing participant , especially within the framework of INVIMA and COFEPRIS regulations. Key factors to consider include:

    1. The site’s prior experience with clinical studies
    2. The availability of

    boast a higher concentration of potential participants, while rural areas may present unique patient demographics that can be advantageous for specific studies.

    Collaborating with significantly strengthens . These partnerships foster trust and enhance communication with potential participants, which is essential for successful studies. Moreover, leveraging technology for site feasibility evaluations can streamline the selection process, ensuring that chosen locations are adequately prepared to meet the study’s requirements.

    This strategic approach not only boosts recruitment but also aligns with the growing in the region, projected to reach USD 161.9 million by 2033. Notably, are expected to be the fastest-growing segment. By utilizing bioaccess’s expertise in and market access strategies, medical researchers can navigate Colombia’s regulatory landscape more effectively.

    Start at the center with the main topic, then explore each branch to see the important factors influencing site selection. Each color represents a different category of consideration, helping you understand how they connect to the overall recruitment strategy.

    Engage Local Stakeholders for Enhanced Collaboration

    Involving local stakeholders – particularly , regulatory bodies, and – is essential for the success of the EFS . This collaboration fosters and teamwork throughout the testing process. By arranging , researchers can gather valuable insights and feedback, ensuring that study designs align with community needs and expectations. Moreover, engaging in the recruitment process not only enhances trust but also significantly among potential subjects.

    For instance, a referral strategy prescreened 37 individuals, with 19 screened and all 19 completing the study, resulting in a remarkable 100% completion rate. Notably, 57% of individuals cite as the primary reason for not participating in research studies, underscoring the critical importance of establishing trust through local involvement. As emphasized by bioaccess’s founders, who possess extensive clinical knowledge and a commitment to medical advancement, is vital for effectively addressing challenges and enhancing the overall quality of .

    Start at the center with the main idea of engaging stakeholders, then follow the branches to see the different groups involved and the actions that enhance collaboration and trust.

    Utilize Technology for Streamlined Trial Management

    Incorporating technology into EFS management significantly enhances efficiency and data integrity. , enabling real-time communication among trial teams and reducing the administrative burden during visits. By utilizing , stakeholders gain and easy access, fostering collaboration and transparency.

    Moreover, the integration of by analyzing data to identify suitable candidates more effectively. Studies show that organizations using and substantial cost savings, with Phase II studies saving approximately $350,000 compared to traditional methods. Additionally, EDC systems lead to a 25% reduction in testing times in research studies. Eliminating just one 20-minute task per visit across several visits can save thousands of hours of work for Associates (CRAs).

    With , can and enjoy through pre-qualified networks. By leveraging these technologies, researchers can alleviate operational burdens and focus on delivering high-quality results, ultimately accelerating the path from trial initiation to market introduction.

    The central node represents the main theme, while the branches show different aspects of how technology improves trial management. Each sub-point provides specific benefits or statistics related to that aspect.

    Conclusion

    Navigating the landscape of EFS clinical trials in Colombia demands a strategic approach that encompasses a thorough understanding of regulatory requirements, the selection of optimal sites, engagement with local stakeholders, and the effective use of technology. Each of these elements is vital in enhancing the efficiency, trust, and overall success of clinical research endeavors in the region.

    Key insights from this discussion underscore the critical nature of regulatory compliance through INVIMA, the necessity of selecting sites that facilitate participant recruitment, and the immense value of collaboration with local healthcare professionals and communities. Furthermore, integrating technological solutions can streamline trial management, enhance data accuracy, and ultimately lead to significant cost savings and expedited enrollment.

    As the field of clinical trials continues to evolve, embracing these best practices is essential for researchers who aspire to make impactful contributions to medical science in Colombia. By prioritizing effective strategies and fostering local partnerships, the potential for successful EFS trials will not only advance clinical research but also significantly improve healthcare outcomes for communities across the nation.

    Frequently Asked Questions

    What is the primary regulatory body overseeing EFS clinical trials in Colombia?

    The primary regulatory body overseeing EFS clinical trials in Colombia is the Instituto Nacional de Vigilancia de Alimentos y Medicamentos (INVIMA).

    What is the typical timeframe for obtaining ethical approval for clinical trials in Colombia?

    Ethical approval for clinical trials in Colombia can be obtained in as little as 4 to 8 weeks.

    What essential documentation must researchers submit for EFS clinical trials in Colombia?

    Researchers must submit the study protocol, informed consent forms, and investigator brochures.

    What recent reforms have been introduced to improve the approval process for clinical trials in Colombia?

    Recent reforms include the introduction of ‘Ley 191’, which is designed to streamline the approval process and enhance efficiency and transparency.

    How can local regulatory specialists assist researchers in Colombia?

    Local regulatory specialists can help navigate the approval landscape, ensure compliance, and accelerate timelines for research studies in the region.

    List of Sources

    1. Understand Regulatory Requirements for EFS in Colombia
      • gabionline.net (https://gabionline.net/policies-legislation/colombia-and-brazil-introduce-reforms-to-enhance-healthcare-regulation)
      • grandviewresearch.com (https://grandviewresearch.com/horizon/outlook/clinical-trials-support-services-market/colombia)
      • linkedin.com (https://linkedin.com/posts/juliomartinezclark_colombialeader-innovationinhealth-activity-7369731048160534549-nEFj)
    2. Select Optimal Sites for Efficient Patient Recruitment
      • grandviewresearch.com (https://grandviewresearch.com/horizon/outlook/clinical-trials-support-services-market/colombia)
      • grandviewresearch.com (https://grandviewresearch.com/horizon/statistics/clinical-trials-support-services-market/service/patient-recruitment-management/global)
      • researchandmarkets.com (https://researchandmarkets.com/reports/6174398/clinical-trial-patient-recruitment-services?srsltid=AfmBOoofVrs05YdBjU7c7nj4gJ9XI6dBoWL4xcT7-op4PwZ0jbchmn2o)
    3. Engage Local Stakeholders for Enhanced Collaboration
      • statnews.com (https://statnews.com/2024/07/10/community-based-research-increase-diversity-clinical-trials)
      • blog.leapcure.com (https://blog.leapcure.com/enhancing-clinical-trials-the-role-of-physicians-nurses-and-community-advocacy)
      • mdpi.com (https://mdpi.com/2076-3271/12/3/39)
      • Checking your browser – reCAPTCHA (https://pmc.ncbi.nlm.nih.gov/articles/PMC8993962)
      • Identifying the Stakeholders Vital to Clinical Trial Success – Petauri (https://petauri.com/insights/identifying-the-stakeholders-vital-to-clinical-trial-success)
    4. Utilize Technology for Streamlined Trial Management
      • careset.com (https://careset.com/10-benefits-of-edc-electronic-data-capture-for-clinical-trials)
      • Clinical Research Technology Adoption Report: AI and Digital Health in Trials (2025) (https://ccrps.org/clinical-research-blog/clinical-research-technology-adoption-report-ai-and-digital-health-in-trials-2025)
      • linkedin.com (https://linkedin.com/posts/andreabastek_2026-state-of-clinical-trial-technology-activity-7424550789219606528-IuNT)
      • 8 key benefits of electronic data capture for clinical trials | Viedoc (https://viedoc.com/blog/key-benefits-electronic-data-capture-clinical-trials)
      • Using Artificial Intelligence to Manage Clinical Trial Conduct | Applied Clinical Trials Online (https://appliedclinicaltrialsonline.com/view/artificial-intelligence-manage-clinical-trial-conduct)